Why Your Coag Results Keep Getting Flagged
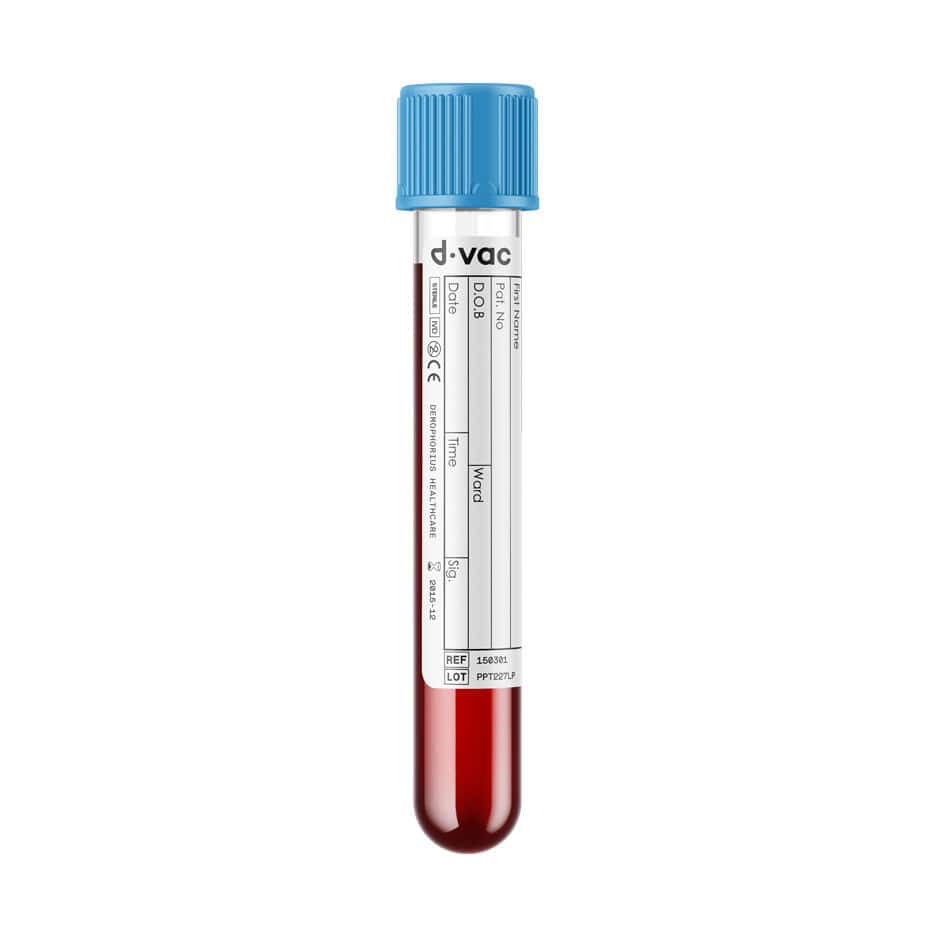
I spend most of my Tuesday mornings watching aPTT results drift upward for no obvious reason. It's usually a collection issue, not a reagent problem. The lab gets blamed for the wrong answer when the real culprit is sitting in a plastic tube that was filled one milliliter short of the line. I've learned to stop arguing with pathologists and start training phlebotomists instead. The standard is a light blue top tube containing 3.2% or 3.8% sodium citrate. The citrate chelates calcium to keep the sample from clotting before you run it. The ratio between blood and anticoagulant matters more than anything else on that shelf. Overfilled tubes give falsely prolonged results. Underfilled tubes give the same problem in the opposite direction, and that one trips people up constantly because the math feels backwards to them. The FDA recommends 3.2% sodium citrate, but you'll still find 3.8% sitting in plenty of hospital stockrooms. The ISHA guideline switched to 3.2% back in 2010, and most reference labs comply. INR values shift slightly between the two concentrations, so mixing them on the same floor without reconciling the calibration is a quiet source of inter-batch variation. Pick one and stick with it unless your lab has validated both.
Fill volume is non-negotiable. These tubes contain a precise liquid-to-additive ratio. If the tube says 2.7 mL and you draw 2.2 mL, the excess citrate dilutes the plasma and your PT time will read long. A hematology analyzer won't complain about this, but the coagulation instrument will produce a result that looks clinically significant when the patient hasn't changed at all. I had a case where a stable warfarin patient's INR jumped from 2.4 to 3.8 over three draws. The fourth tube was properly filled and the INR dropped back to 2.5. The difference was literally half a milliliter of blood.
The Pre-Analytical Minefield
Turnaround time matters. Once the blood is in citrate, the coagulation factors start degrading. Platelet-rich plasma can release factor V and fibrinogen into the supernatant if you wait too long, and you end up with a falsely shortened aPTT that looks like a heparin effect. The typical acceptable window is two hours at room temperature before you need to centrifuge and separate. After that, the results become unreliable without a specific stability study behind them. Centrifugation is the next place things go wrong. A first spin at room temperature for ten minutes at 1500 times G gets most labs to a platelet-poor plasma, but the ISTH now recommends a double-spin method when you're measuring Lupus Anticoagulant or doing factor assays. A second spin at 2000 to 2500 times G for fifteen minutes knocks the residual platelet count below ten per microliter, which is the threshold for reliable LA testing. If you skip the second spin, platelet fragments can consume reagent phospholipids and give a false-positive LA result that sends the patient down a rheumatology rabbit hole. I ran into this exact problem last year. Our hemostasis lab was flagging a handful of samples as LA-positive on a screening dilution test. Nothing confirmed on mixing studies. We started doing the double-spin as a reflex and every single positive turned negative on the second pellet. The instrument wasn't broken. The protocol was just insufficient for that particular assay.
Get the Full Details

Common Pitfalls That Waste Time and Reagents
Hemolysis from a difficult draw introduces free hemoglobin into the plasma and can interfere with optical detection methods. It's less of an issue for some modern coagulometers than it used to be, but severe hemolysis still skews results. Lipemic samples do the same thing through light scatter. The instrument registers turbidity as absorbance change and the calculated clotting time drifts. I've seen triglyceride levels above 2000 mg per deciliter push an aPTT up by nearly twenty seconds on a refractive index-corrected photometer. Checking the sample visually for lipemia takes three seconds and prevents a whole re-run. Contamination from IV lines is another one people don't talk about enough. Drawing a coagulation tube from a line that has heparin flush running through it will drop your aPTT to unmeasurable levels. The same applies to citrate-containing flush solutions if you're trying to measure something like fibrinogen by the Clauss method and the tube itself got pre-rinsed with citrate solution. Label the tube, draw it from a fresh venipuncture, and if you have to pull from a line, discard at least five milliliters first. Not always practical, but usually possible. Ice cooling the sample is sometimes recommended for unstable patients or when transport takes longer than an hour. Cold inhibits coagulation factor activity and can actually improve stability for certain assays, but it also changes the viscosity and can affect pipetting accuracy if the sample refreezes during handling. Most routine PT and aPTT testing doesn't benefit from refrigeration and I'd avoid it unless you have a documented protocol that accounts for the temperature shift.
How to Actually Get Reliable Results
Start with proper collection technique. Use a butterfly or straight needle with a holder that maintains vacuum integrity. Fill the light blue tube until it reaches the recommended volume, then immediately invert it gently five to eight times. Vigorous mixing creates foam and hemolysis. Inverting slowly and thoroughly keeps the citrate evenly distributed without destroying red cell membranes. Process the sample within the timeframe your lab validates. For most facilities, that means centifuge within two hours of collection. Separate the plasma into a secondary tube and run it within another four hours if you're holding it at room temperature. Refrigerate at two to eight degrees Celsius only if your validation data supports it for the specific assays you're running. Keep your quality control materials at the right temperature and check them against your instrument's lot-specific range. Coagulation reagents degrade differently depending on the manufacturer and the instrument type. A thromboplastin with an ISI of 1.1 will give you a different INR slope than one rated at 1.4, even on the same patient sample. Cross-check your results periodically with an external proficiency testing program and watch for systemic drift that might indicate a reagent issue rather than a patient issue.
The biggest practical tip I can give is to build a rejection criteria list and enforce it. Grossly lipemic, visibly clotted, underfilled, or hemolyzed samples get rejected before they hit the analyzer. It costs you a recollection but it saves you from spending an hour investigating why a stable patient's INR just doubled. Your technologists will thank you, and the pathologist won't have to explain unexpected results to a attending who hasn't touched the anticoagulation order in weeks.

When the Tube Isn't the Problem
Sometimes the sample is fine and the result is still weird. Cryofibrinogen, paraproteins, and rare factor inhibitors can all interfere with clot-based assays in ways that no amount of proper collection will fix. A sample from a patient with Waldenström macroglobulinemia gave us an aPTT of 45 seconds on three separate draws with perfect technique. The IgM levels were causing pseudo-prolongation through viscosity effects on the mechanical detection endpoint. Switching to a chromogenic assay resolved the discrepancy because it measures factor Xa activity directly rather than relying on clot formation timing. Not every coagulation lab needs chromogenic methods, but knowing when the standard assays lie is what separates a technician who follows protocol from someone who actually understands what the result means. I stopped trying to chase every outlier with better collection technique and started asking whether the assay methodology itself was appropriate for the clinical picture. The answer changed how I interpret results more than anything else I've done in this job.