What TB Of The Skeleton Actually Looks Like In Practice
Skeletal tuberculosis accounts for roughly fifteen percent of all extrapulmonary TB cases worldwide, and when you're dealing with it clinically, it behaves nothing like pulmonary TB. There is no cough, no sputum, no obvious infectious droplet spread. You are often hunting for a patient who has had insidious back pain for months and has already been treated for mechanical issues by two or three different specialists before anyone ever considers an infectious etiology. That delay is the norm, not the exception. The most common site is the spine, specifically the thoracolumbar junction. This is what we call Pott's disease. The infection typically starts in the vertebral body near the subchondral bone plate, tracks forward under the long anterior longitudinal ligament creating a paravertebral abscess, and then erodes into adjacent vertebrae. The intervertebral disc is actually relatively resistant to Mycobacterium tuberculosis in the early stages, which is a key diagnostic clue. Bacterial meningitis and pyogenic spondylodiscitis destroy the disc early, but TB tends to spare it until later in the disease course. That difference matters when you are looking at MRI sequences.
Diagnosing Tuberculosis Of Bones And Joints Before It Destroys The Spine
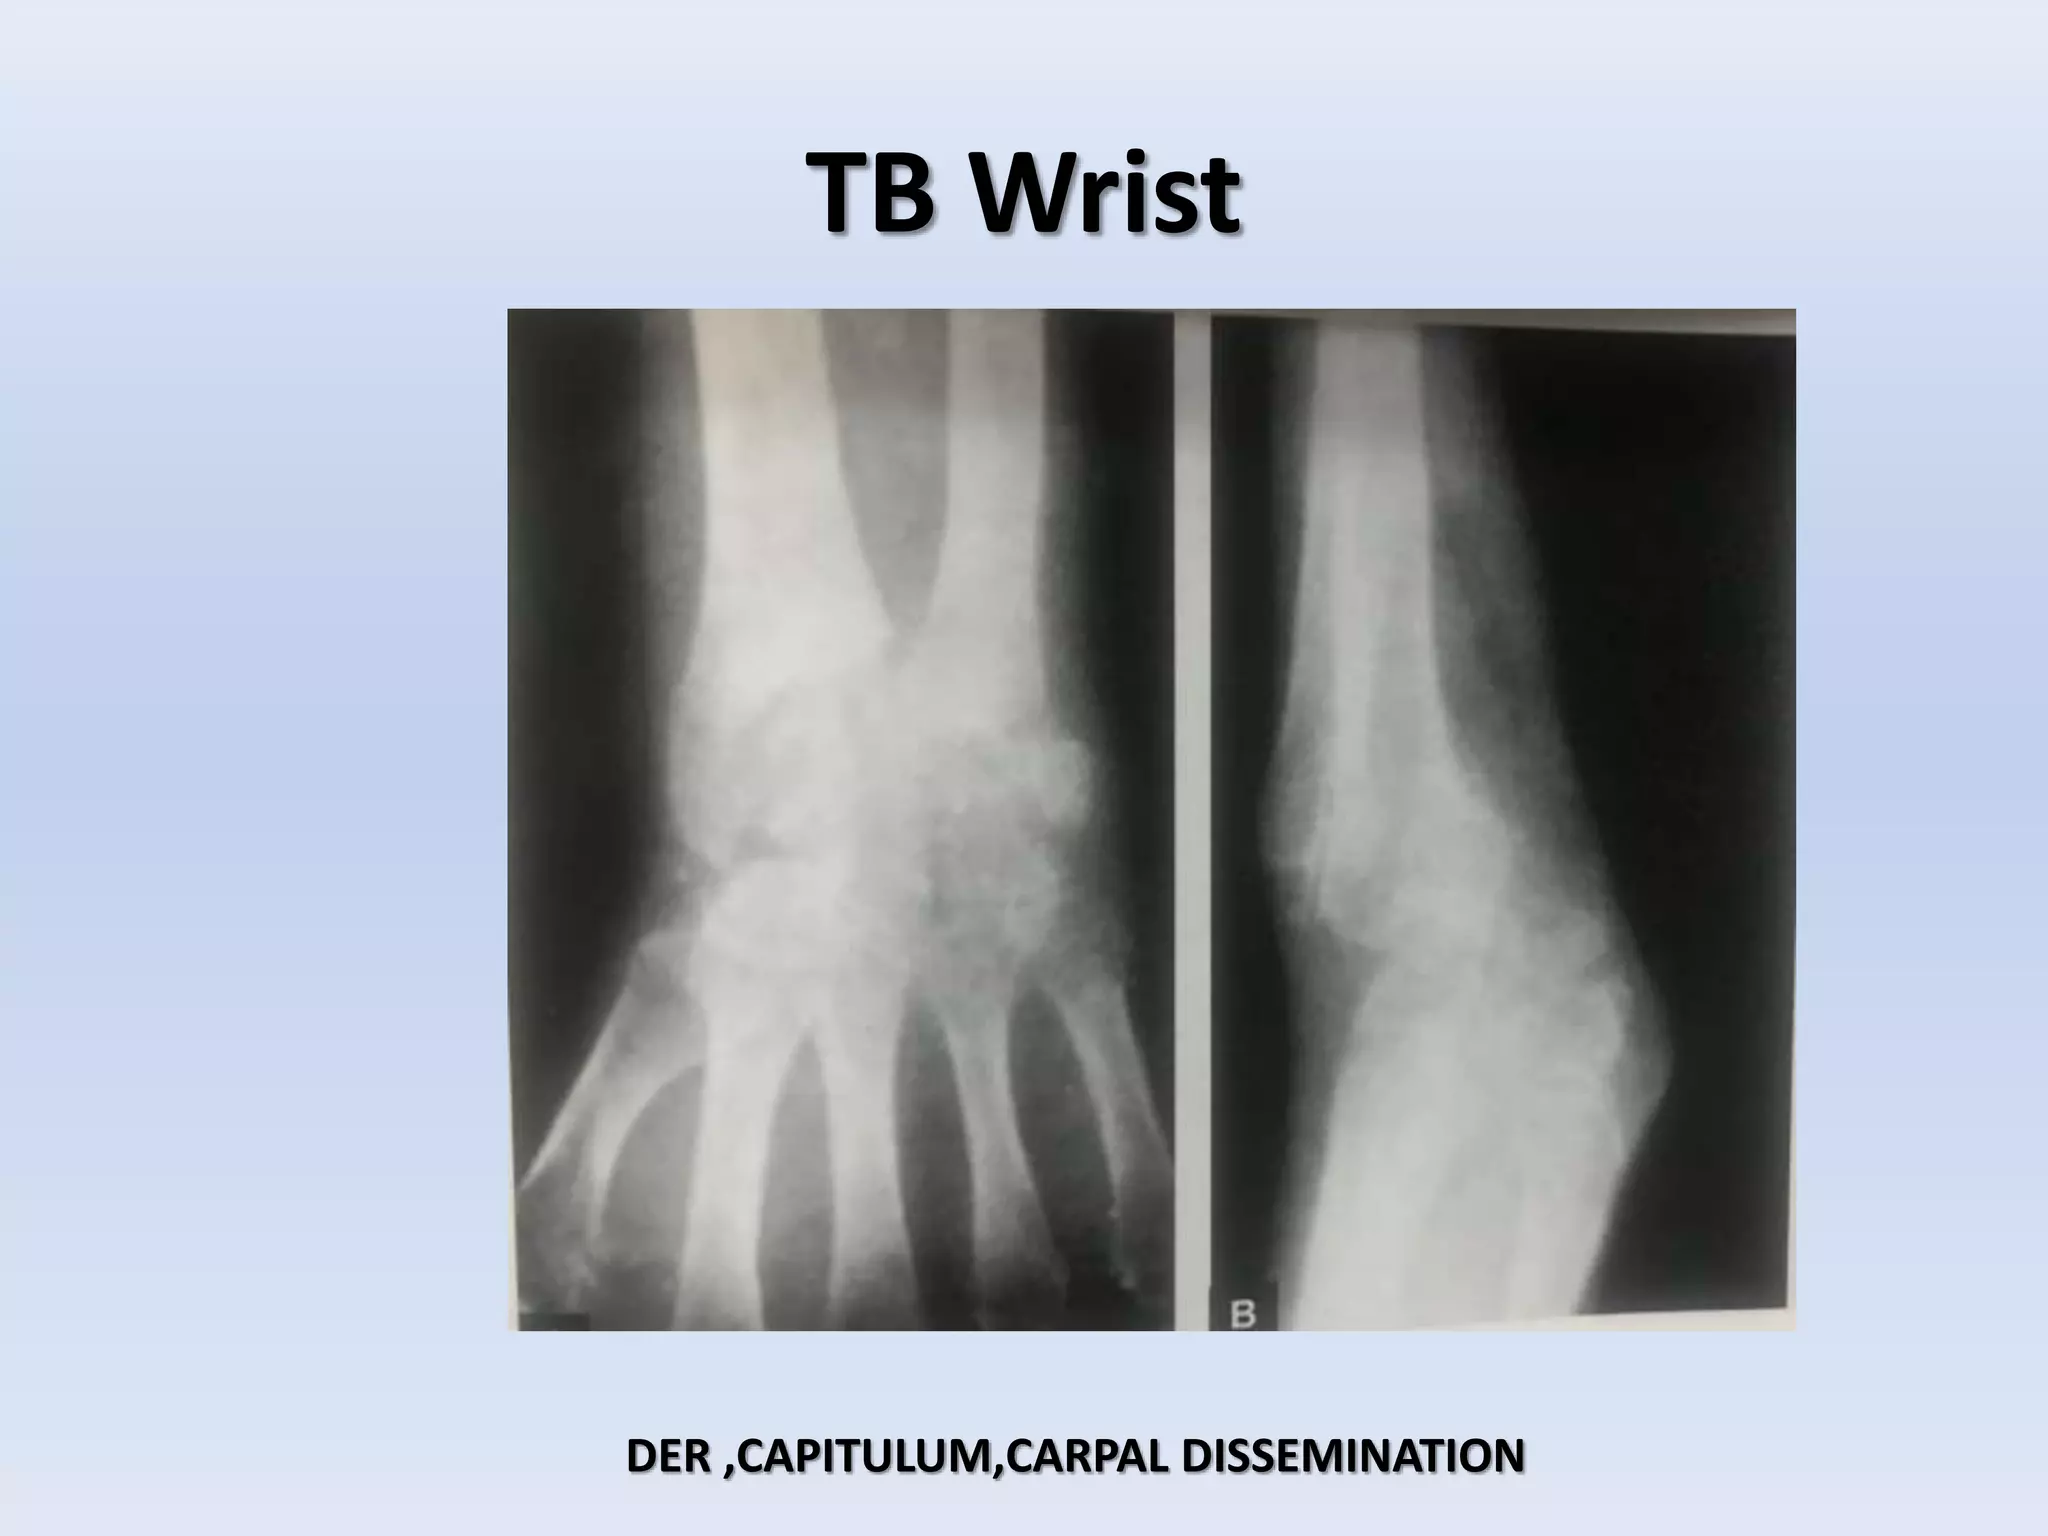
I have had patients come in with complete collapse of three vertebral bodies and a large cold abscess tracking into the psoas muscle, and they were still ambulatory. That is the deceptive nature of this condition. The cold abscess does not cause the acute inflammatory pain you see with pyogenic infections. Instead, patients present with deep, aching pain that worsens at night and mild low-grade fever that they dismiss as exhaustion. Weight loss is common but non-specific. By the time you see the classickyphotic deformity, structural damage is usually already advanced. The diagnostic workup starts with imaging but imaging alone will not confirm the diagnosis. A chest X-ray may show old granulomatous changes from a prior pulmonary infection, but up to half of these patients have a completely clear chest film. CT of the affected region gives you better detail on bony destruction and the extent of paravertebral involvement than plain radiographs. MRI is the single most useful modality for evaluating spinal TB because it shows the full extent of marrow edema, epidural extension, and cord compression. I always request gadolinium enhancement with MRI. Rim-enhancing collections in the psoas or paraspinal regions with corresponding vertebral body destruction are the classic appearance. The definitive diagnosis requires microbiological or histological confirmation. I prefer CT-guided core needle biopsy over fine needle aspiration because you need tissue architecture to demonstrate caseating granulomas, and the sensitivity of culture is significantly higher with core biopsy samples. GeneXpert MTB/RIF on the biopsy specimen gives you results within twenty-four hours and can simultaneously detect rifampin resistance, which changes everything about treatment planning. Standard smear microscopy of biopsy tissue has very low sensitivity, below thirty percent, so a negative smear does not rule out TB. Culture on Lowenstein-Jensen medium remains the gold standard but takes six to eight weeks for growth, which is a lifetime when you are dealing with a patient who has progressive neurological deficits.
I once dealt with a thirty-four-year-old woman who presented with isolated left hip pain and a three-month history of limping. She had no pulmonary symptoms, normal inflammatory markers, and an X-ray that looked essentially normal except for subtle joint space narrowing. We did an MRI of the hip and found extensive synovitis with multiple rheumatoid-like pannus formations and a small effusion. Standard synovial fluid analysis showed lymphocytic predominance with an ADA level of eighty-four U/L, which is well above the typical cutoff of forty U/L for tuberculous arthritis. We proceeded to arthroscopic synovial biopsy, and GeneXpert came back positive for M. tuberculosis. She had never had a known exposure, no family history of TB, and her HIV test was negative. This was isolated monoarticular TB of the hip with no pulmonary component and no other skeletal involvement. The lesson from that case is that you should have a low threshold for checking ADA in synovial fluid and pursuing biopsy when you see chronic monoarthritis with lymphocytic predominance, even in immunocompetent patients from low-prevalence areas. Waiting for culture results before starting treatment would have resulted in complete destruction of her articular cartilage within weeks.
Get the Full Details
How Treatment Actually Works And Where It Fails
The pharmacological standard remains four-drug induction therapy with isoniazid, rifampicin, pyrazinamide, and ethambutol for two months, followed by a continuation phase of isoniazid and rifampicin for at least seven more months. Total treatment duration for skeletal TB is generally nine to twelve months, and some guidelines recommend extending to eighteen months for extensive spinal disease with neurological involvement. This is considerably longer than the six-month regimen used for pulmonary TB, and compliance over that timeframe is a real problem in practice. Pyrazinamide penetrates into caseous tissue and abscess cavities better than the other first-line drugs, which is why it is essential in the initial phase. Ethambutol carries a risk of optic neuritis, so you need baseline visual acuity and color vision testing before starting, and periodic monitoring during treatment. I check visual symptoms weekly during the first month and then monthly thereafter. Liver function tests are required at baseline and every two to four weeks during therapy. Rifampicin induces cytochrome P450 enzymes, which means it interacts with a wide range of medications including antiretrovirals, anticoagulants, and hormonal contraceptives. If your patient is on any chronic medications, you need to review the interaction profile before prescribing rifampicin. One counter-intuitive point that many clinicians miss is that skeletal TB responds more slowly to treatment than pulmonary TB, and this is not simply a matter of drug penetration. The vascular supply to necrotic bone and caseous abscesses is poor, and the bacterial population in these areas is metabolically inactive, existing in a slow-growing or dormant state that makes them less susceptible to the bactericidal activity of first-line drugs. You should expect radiological improvement to lag behind clinical improvement by several months. A patient may feel better and have normalized inflammatory markers after three months of therapy while their MRI still shows active disease. This discrepancy is normal and does not indicate treatment failure unless there is clinical deterioration.
Surgical intervention is necessary in approximately twenty to thirty percent of spinal TB cases. The main indications are neurological deficit that is progressive or refractory to medical therapy, spinal instability or severe kyphotic deformity, large abscesses that do not resolve with treatment, and diagnostic uncertainty where biopsy has not yielded a definitive answer. The surgical approach depends on the level and extent of disease. For thoracolumbar lesions, I favor anterior debridement and strut grafting because it allows direct removal of necrotic material and decompression of the spinal cord. Posterior instrumentation alone can provide stability but does not address the anterior column destruction that is characteristic of Pott's disease. I encountered a patient with a L1 vertebral body destroyed by TB and a large anterior epidural abscess causing bilateral leg weakness. We attempted CT-guided drainage of the abscess and started anti-TB medication, but after two weeks there was no neurological improvement and the MRI showed persistent compression. We moved to surgical decompression through a transperitoneal approach with corpectomy and titanium cage reconstruction. The postoperative recovery was straightforward, and after completing twelve months of therapy the patient had returned to normal ambulation. The key takeaway is that you should not delay surgery if there is no clinical response to adequate medical therapy within two to four weeks. Continued conservative management in the face of progressive deficit risks permanent neurological damage.
The Pitfalls That Get People In Trouble
Monotherapy is one of the most dangerous errors, and it happens more often than it should. A patient presents with back pain, you start empiric analgesics and then add a single anti-TB drug because you are waiting for culture results, and by the time resistance is detected the organism has already developed mutations. Always start four-drug therapy once TB is suspected, even before confirmation. If the diagnosis is later ruled out, you can stop the drugs without consequence. If it is confirmed, you have already started appropriate treatment. Another common mistake is stopping treatment too early because the patient feels better. Skeletal TB requires longer treatment than pulmonary TB precisely because of the reasons I outlined above, and premature discontinuation leads to relapse at rates exceeding twenty percent. I tell every patient that feeling better at three months does not mean the disease is cured. It means the drug is working. The bacteria are still present in the bone, and stopping now guarantees recurrence. Immune reconstitution inflammatory syndrome is a consideration in co-infected patients. When you start anti-TB therapy in someone with advanced HIV, the recovering immune system can mount an exaggerated inflammatory response to the dying mycobacteria, leading to transient worsening of symptoms and expansion of abscesses. This is not treatment failure. It typically occurs within the first one to three months of therapy and resolves spontaneously or with a short course of NSAIDs. Starting ART too soon after beginning TB treatment can trigger this, so timing of ART initiation relative to TB therapy matters in co-infected patients.

Drug-resistant TB of the skeleton is increasingly common in areas with high rates of acquired resistance. If your patient is from a region with significant MDR-TB prevalence or has a history of incomplete prior TB treatment, you should assume resistance until proven otherwise and adjust your regimen accordingly based on molecular resistance testing rather than waiting for full phenotypic susceptibility profiles. Linezolid, fluoroquinolones, and injectable agents like amikacin have roles in MDR regimens, and consultation with a TB specialist is strongly recommended in these cases. The prognosis for skeletal TB is generally good with appropriate treatment, but outcomes depend heavily on how early the diagnosis is made. Spinal TB with neurological involvement has a higher morbidity rate, and joint TB can lead to permanent functional impairment if the articular cartilage is destroyed before treatment begins. Early recognition, adequate diagnostic workup including biopsy, timely initiation of four-drug therapy, and surgical intervention when indicated are the factors that determine whether a patient walks out of the hospital the same way they walked in, or whether they are left with chronic pain and disability.