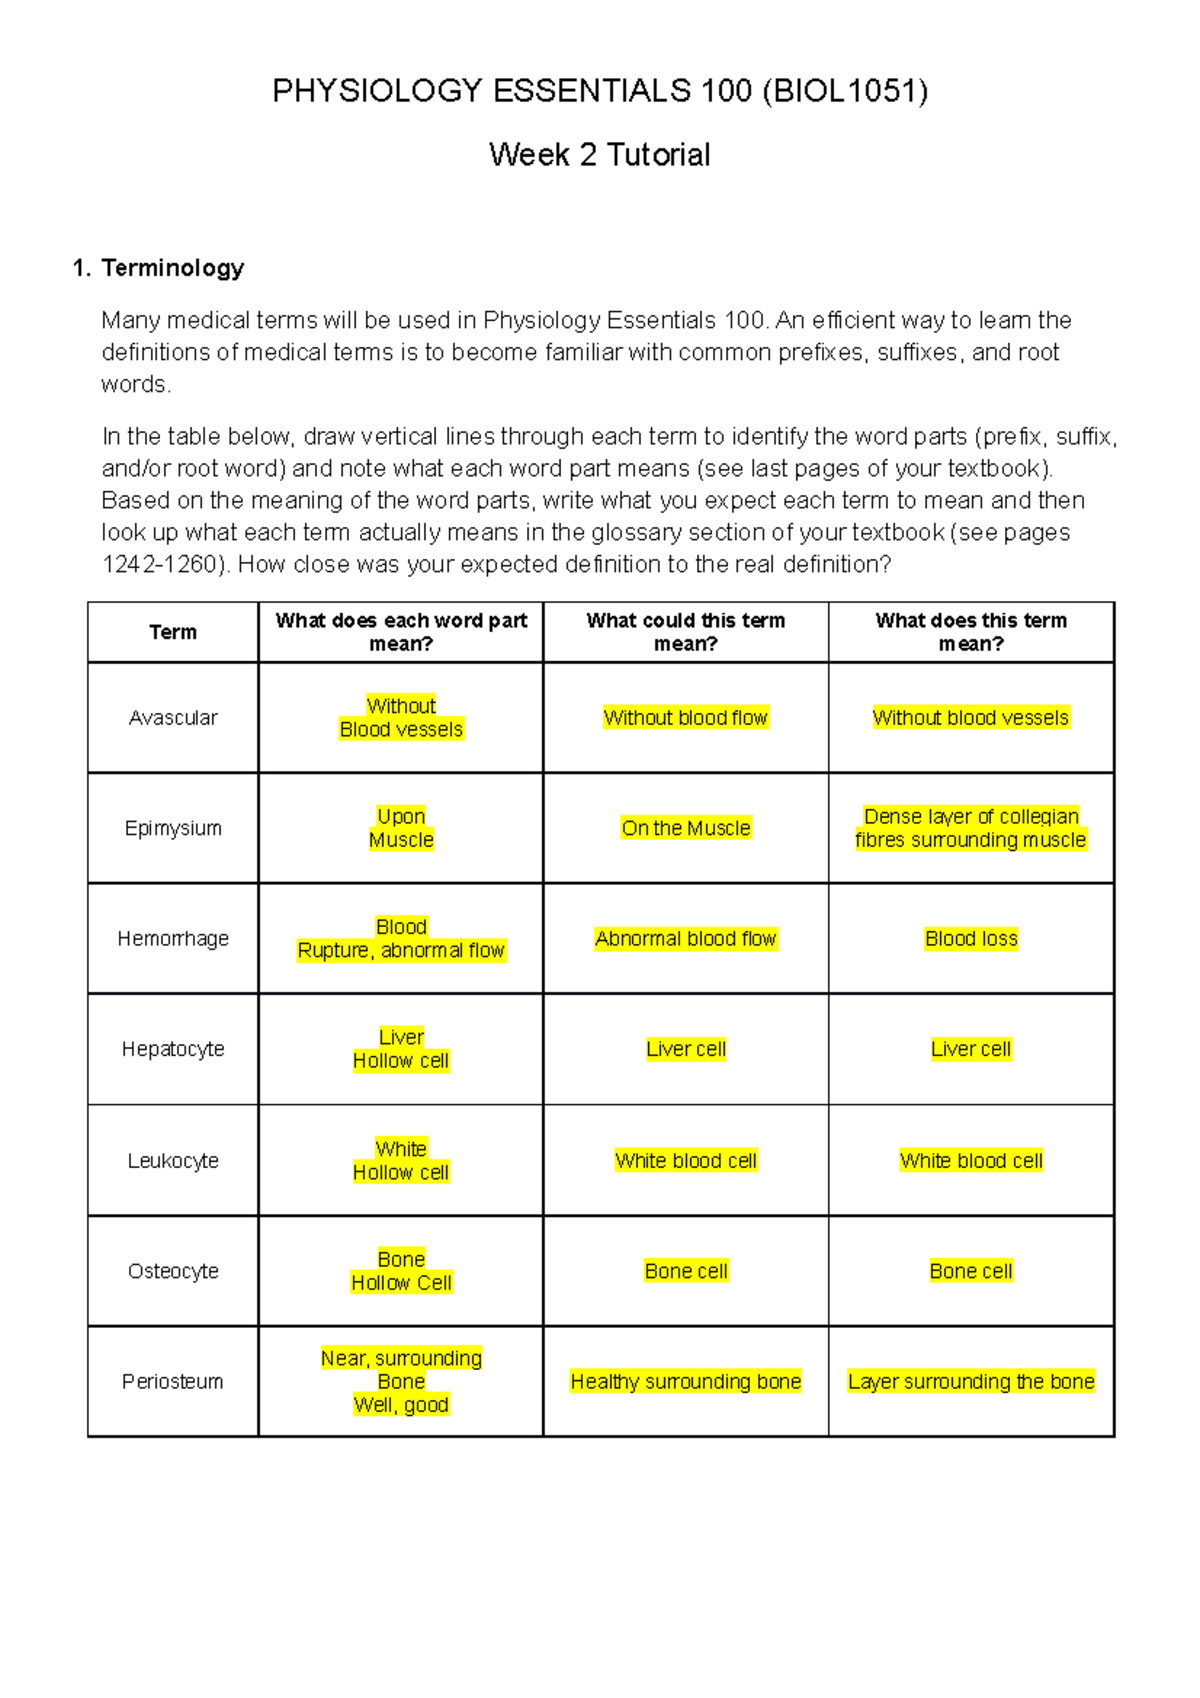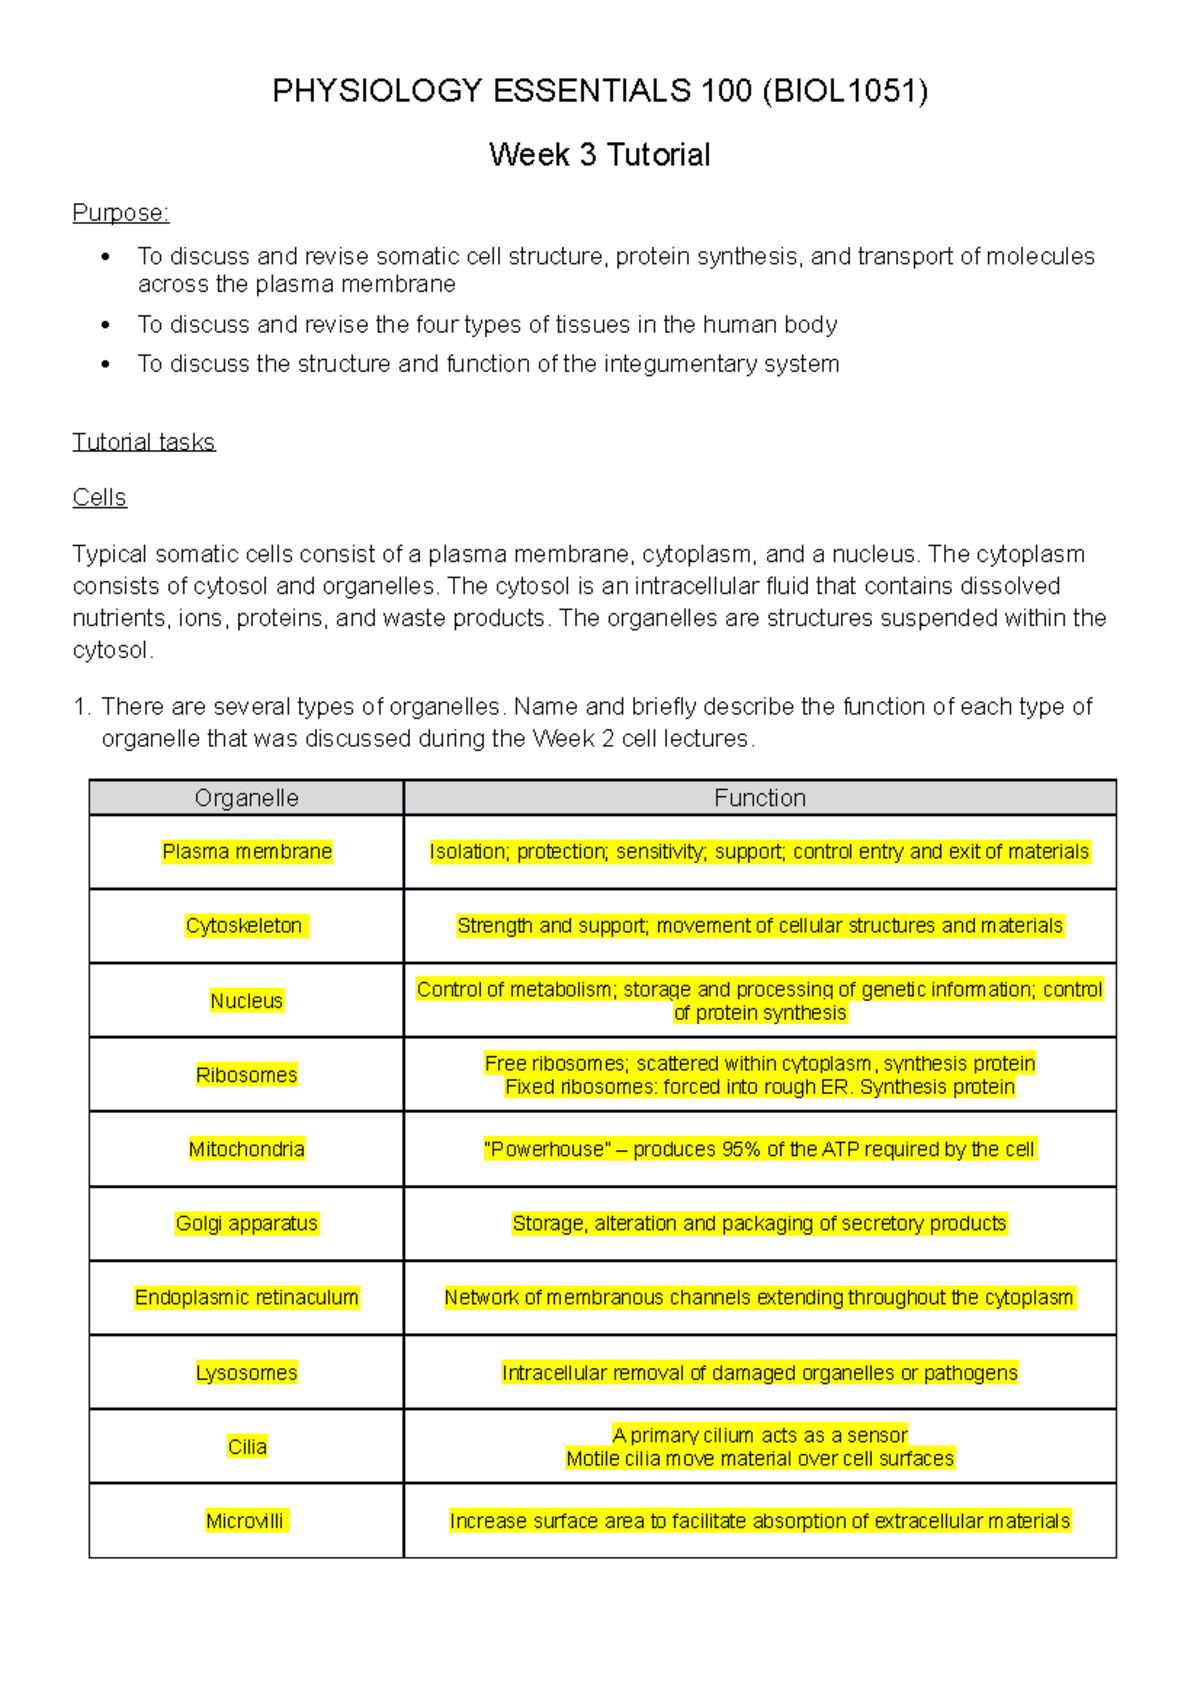
What You Actually Need To Know About Physiology
Physiology is one of those subjects where everyone assumes it is just memorization. It is not. It is applied physics and chemistry inside a wet machine. If you treat it like anatomy flashcards, you will fail the harder courses. I have seen students blow through gross anatomy with 90s and then crash in respiratory physiology because they never learned to think in terms of gradients, resistances, and compliance curves. The core idea is simple enough: the body maintains function through feedback loops, and every system can be modeled mathematically if you stop panicking about the math. The problem is most textbooks present the math implicitly and expect you to reverse-engineer it. They show you the result without showing you the steps. That gap is where people fall apart.
Tutorial For Physiology Essential Concepts And How They Actually Work
I started by mapping everything onto first principles. Start with Fick's principle for cardiac output, then build from there. Once you understand that flow equals pressure gradient divided by resistance, half the cardiovascular section practically writes itself. Pulmonary circulation is the same equation with different numbers. Systemic vascular resistance versus pulmonary vascular resistance is a numbers game, not a conceptual one. Here is a specific problem I ran into repeatedly when teaching this material. Students would correctly memorize that ADH increases water reabsorption in the collecting duct. Then a question would ask about a patient with SIADH who has hyponatremia and inappropriately concentrated urine, and they would freeze. The issue was not that they did not know the fact. The issue was they had no mental model for osmolar clearance versus free water clearance. Without that distinction, every renal question beyond the basics looks like guesswork. The workaround was to force a calculation. I made them compute free water clearance using C_H2O equals V minus C_osm for three different clinical scenarios. Not theoretical ones. Actual labs with real values. Once you watch the number go negative in SIADH and positive in diabetes insipidus, the concept stops being text and becomes something you can see moving. That shift from abstract to arithmetic is where understanding actually happens.
Renal physiology is the best teacher if you let it be. It forces you to deal with clearance, filtration fractions, and tubular handling in a way no other system does. The same logic applies to pulmonary gas exchange. Alveolar gas equation is straightforward algebra. PaO2 equals FiO2 times atmospheric pressure minus PaCO2 divided by respiratory quotient, all corrected for altitude. That is it. Everything else is adjusting variables. Endocrine physiology trips people up because of the naming conventions. Negative feedback is the rule, not the exception. Hypothalamus releases releasing hormone, pituitary releases tropic hormone, target gland releases the actual hormone. Three layers. Break that chain at any point and the downstream numbers collapse in predictable ways. When you see elevated TSH with low free T4, you do not need to panic. The chain broke at the thyroid. When TSH is low and free T4 is low, the problem is upstream. Central hypothyroidism. The pattern tells you the lesion location before you even look at the lab values again. Neurophysiology is the part where most people give up, and I get it. Action potentials involve ion concentrations, membrane potentials, voltage-gated channels, and refractory periods all at once. The trick is to separate the resting state from the event. At rest, potassium leak channels dominate. The membrane sits near E_K because permeability to potassium is roughly a hundred times higher than sodium at rest. That is why the resting potential is around minus eighty millivolts and not near zero. Then a stimulus opens sodium channels, sodium rushes in, and you get depolarization. Potassium channels open more slowly and repolarize the membrane. The sodium-potassium pump does not cause the action potential. It maintains the gradients over hours and days. Confusing those two timelines is a common error.
Get the Full Details

There is a counter-intuitive point about the neuromuscular junction that almost nobody emphasizes. Acetylcholine release is calcium-dependent, not sodium-dependent. The depolarization of the presynaptic terminal opens voltage-gated calcium channels, and calcium influx triggers vesicle fusion. If you are studying pharmacology alongside physiology, remember that botulinum toxin blocks SNARE proteins and prevents vesicle fusion, while organophosphates inhibit acetylcholinesterase and prolong transmission. Same synapse, completely opposite mechanisms. Knowing both helps you answer questions about either poison class without having to relearn the synapse from scratch. Gastrointestinal physiology gets shortchanged in most programs. People skim past it because the math seems lighter. But the enteric nervous system operates semi-independently, and understanding motility patterns requires knowing the difference between peristalsis and segmental contractions. Peristalsis moves content forward. Segmentation mixes it. Both are controlled by the myenteric plexus. The vagus modulates but does not initiate. That detail matters when you are interpreting motility studies or managing patients with gastroparesis. Endocrine physiology also has a trap that catches advanced students. Steroid hormones cross the membrane and bind intracellular receptors. Peptide hormones bind surface receptors and trigger second messenger cascades. The speed difference is enormous. Epinephrine acts in seconds through beta-adrenergic signaling. Thyroid hormone changes gene expression and takes days to show full effect. Treatment timelines follow the mechanism, not the severity of the symptom. Hyperthyroid patients do not improve on methimazole within a week because the existing thyroid hormone already in circulation has a half-life of about seven days. The drug stops new production. It does not remove what is already there.
The biggest limitation of self-studying physiology is the feedback gap. You can read about Starling forces and understand them in theory. Then you see a question where the patient has nephrotic syndrome, low albumin, and peripheral edema, and you second-guess whether oncotic pressure or hydrostatic pressure is the primary driver. It is oncotic pressure in that case, but the question writers love to make you doubt yourself by adding confounding variables like venous congestion or lymphatic obstruction. Without someone to run those scenarios past, you develop blind spots. A group study format helps, but only if the people in it are at a similar level. A smarter student will fill the silence with answers and you will learn nothing. A weaker student will slow everything down. The sweet spot is three people who can each explain one system without looking at notes. Rotate who teaches which section. You will discover gaps in your own knowledge the moment you try to explain glomerular filtration rate to someone else. Another practical constraint is time. Physiology requires more repeated exposure than any other basic science subject. One pass through the material gives you familiarity. Two passes give you understanding. Three passes give you retention that survives an exam. Most students stop at one and wonder why they cannot apply what they read. The volume of content in a standard medical physiology course runs roughly four hundred to six hundred pages of dense text. You should budget six to eight weeks minimum for proper coverage, not cramming it into two weeks before the test.
If you want a streamlined path, start with Guyton and Hall for the conceptual framework, use Costanzo for the high-yield summaries and practice questions, and supplement with BRS Physiology for board-style problems. That combination covers about ninety-five percent of what you need for coursework and licensing exams. Anything beyond that is specialty territory and not relevant to general physiology mastery. Lab work helps more than textbooks admit. Watching a frog heart skip beats when you change the potassium concentration in the bath solution teaches you more about cardiac electrophysiology than three chapters of text. The visual of the heart slowing, then stopping in diastole, makes the concept of hyperkalemic cardiac arrest permanent in your memory. If your program does not include dissection or animal labs, online simulations from sources like PhysioEx or visible body modules are the next best thing. They are not identical to real tissue, but they show the relationships between variables clearly enough. The bottom line is that physiology rewards people who build models in their head and then test those models against clinical scenarios. Memorization gets you through the first exam. Modeling gets you through the second, third, and final boards. Pick a system, write out the governing equations, derive the key relationships yourself, and then check them against a question bank. That cycle of construct-verify-correct is the actual workflow, not passive reading.