What Actually Happens With Beta hCG in Twin Pregnancies After IVF
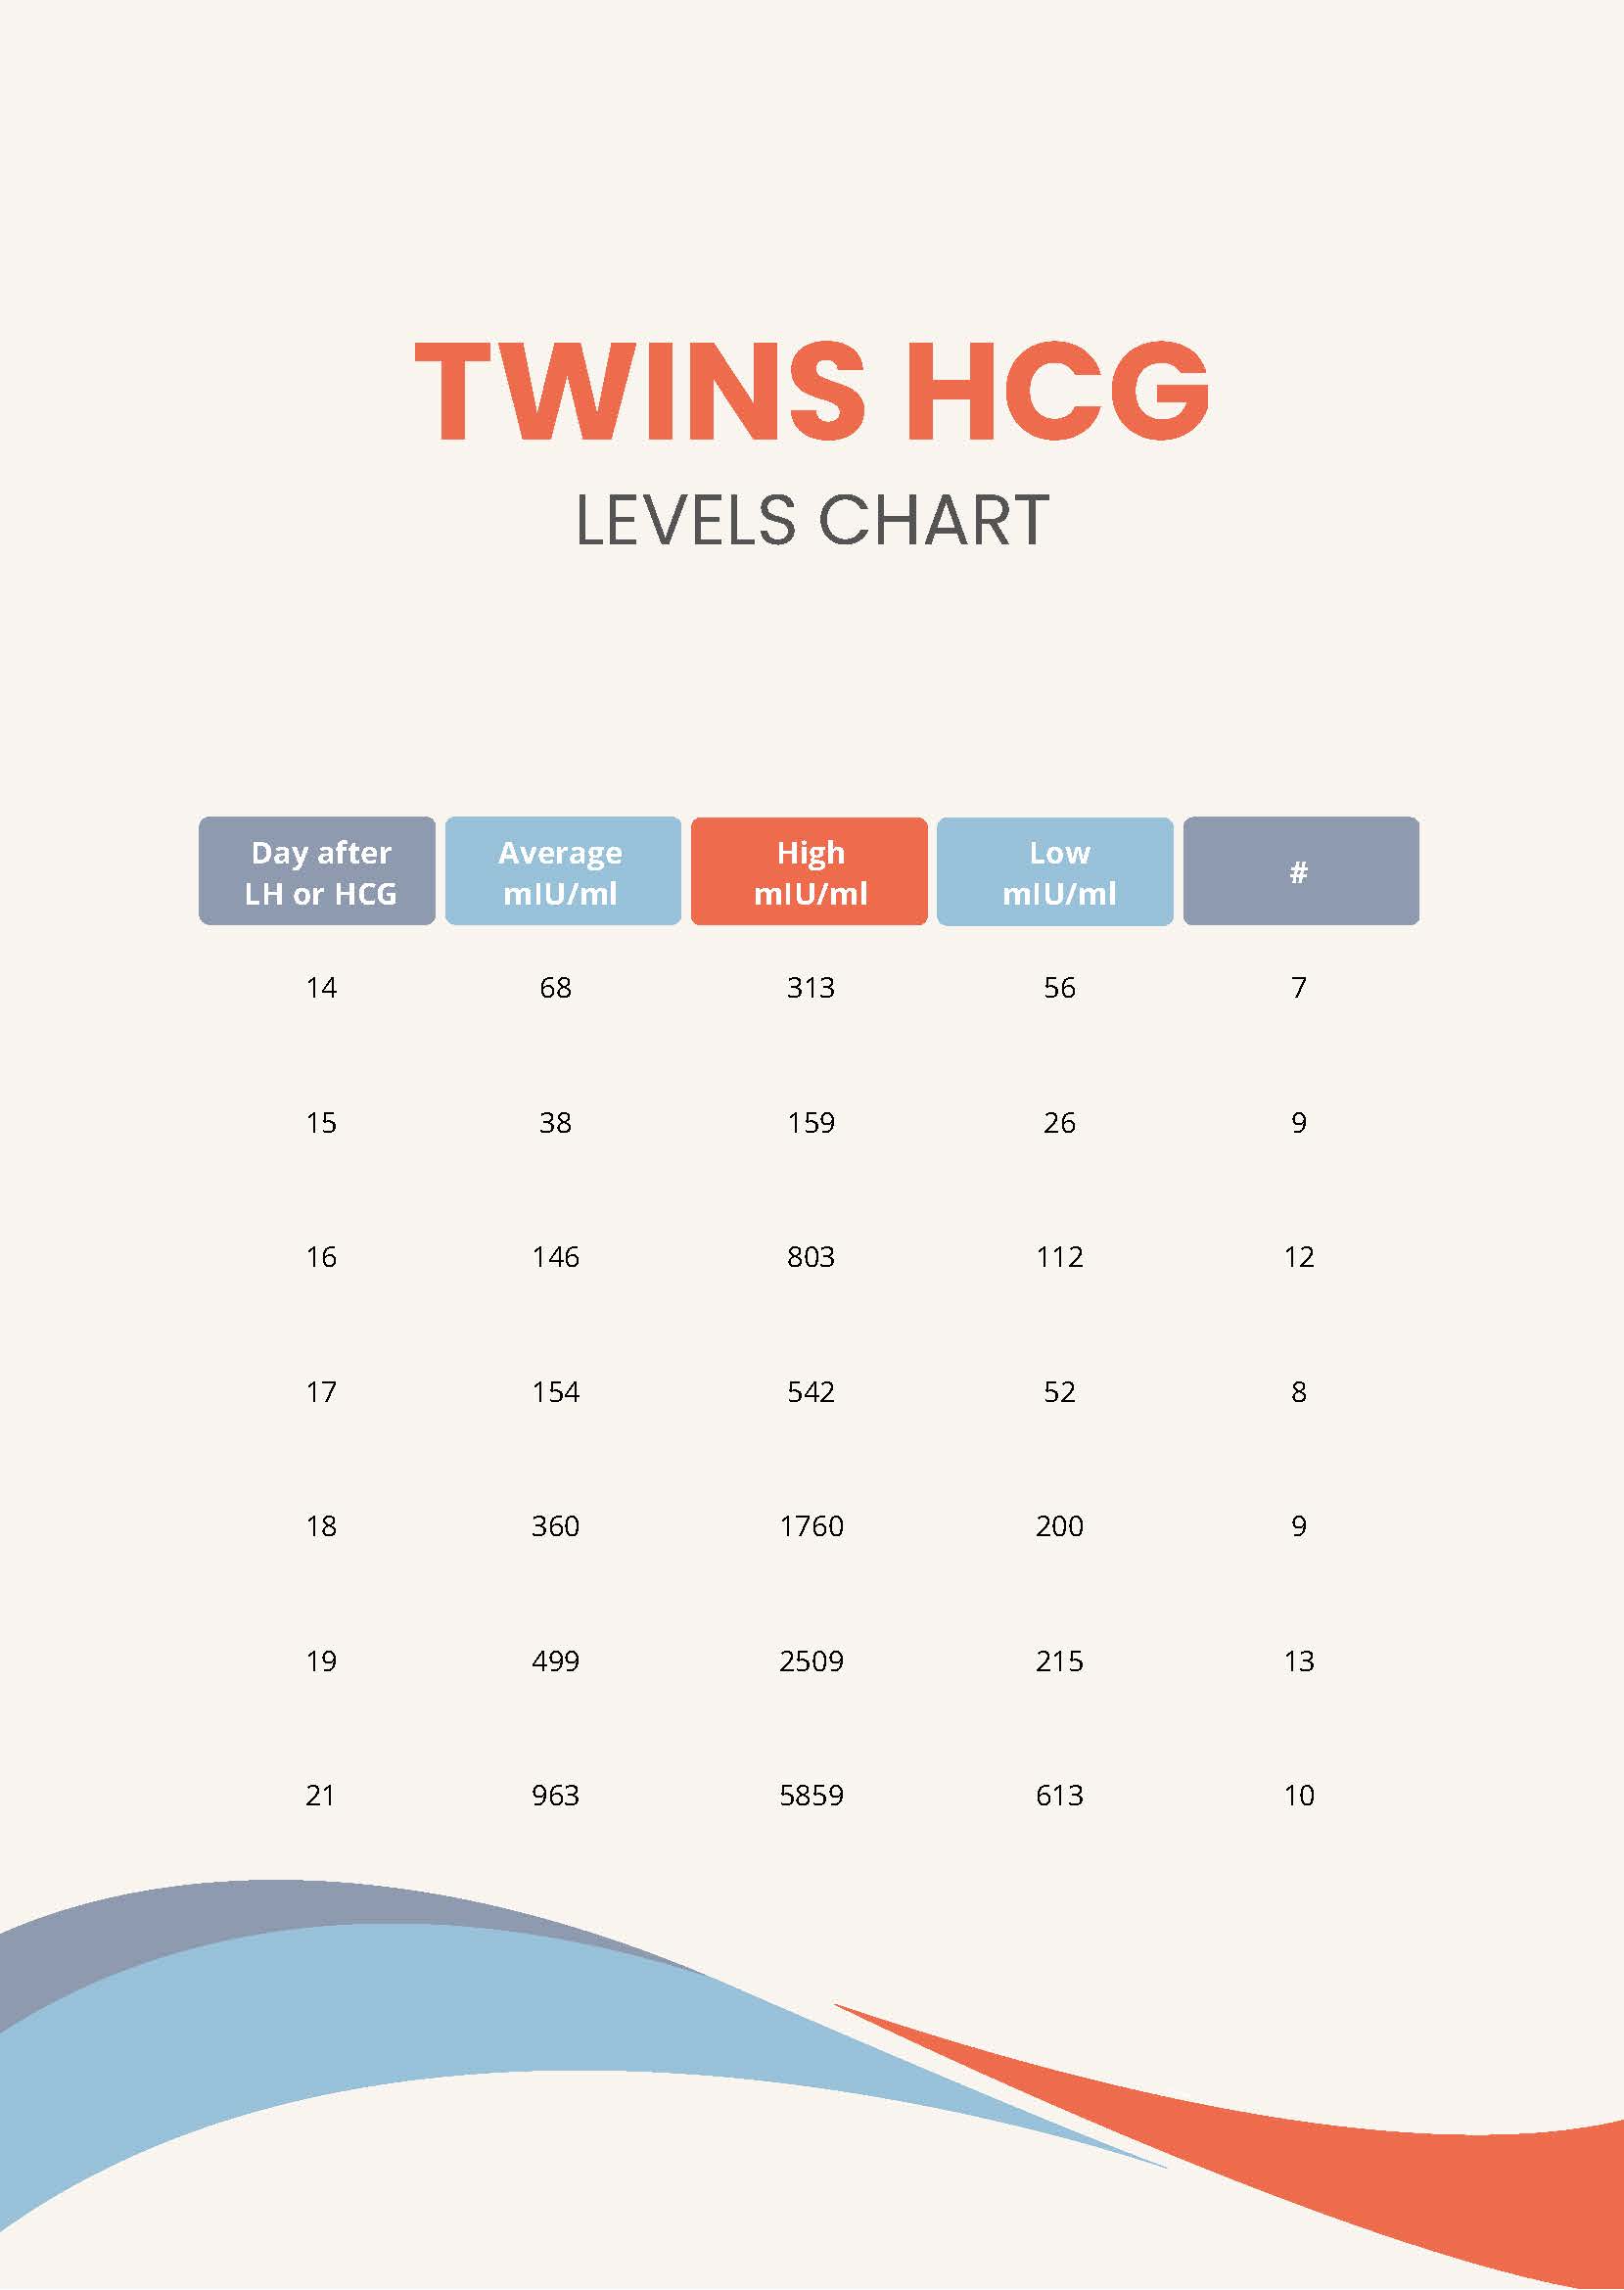
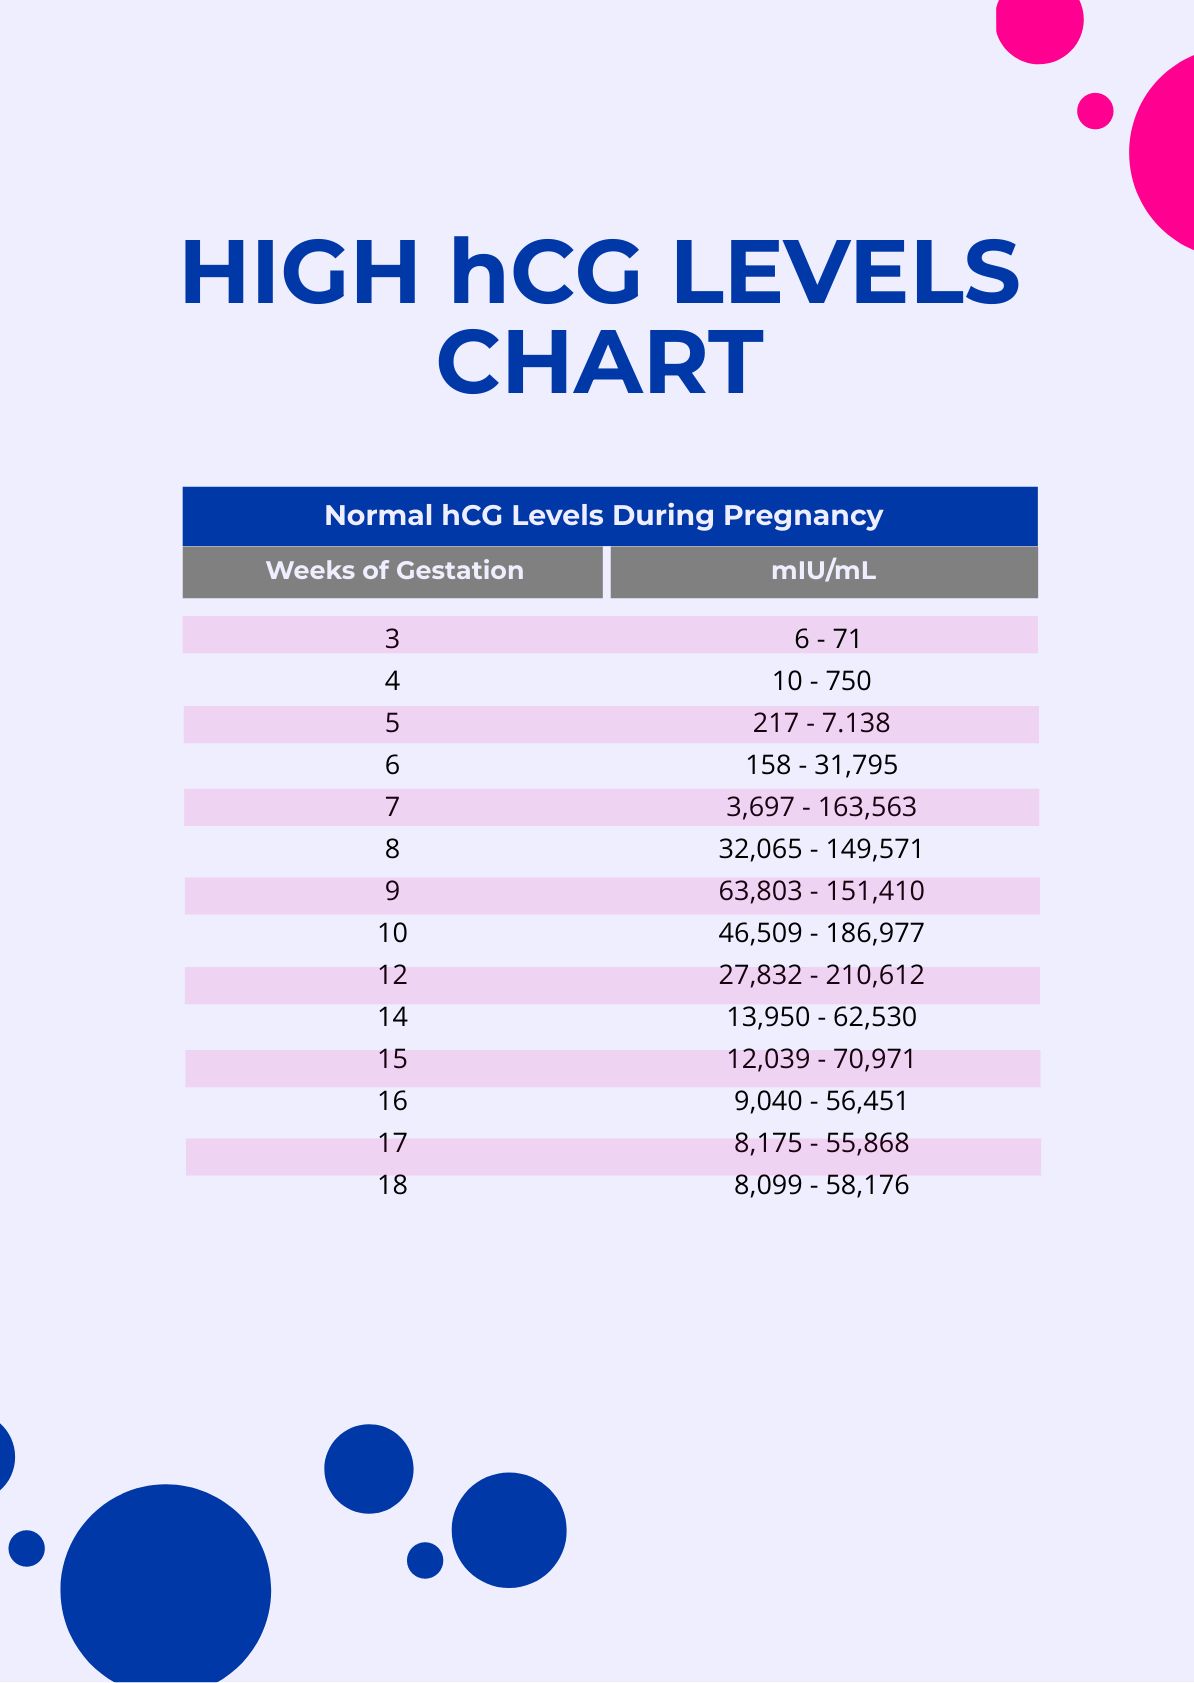
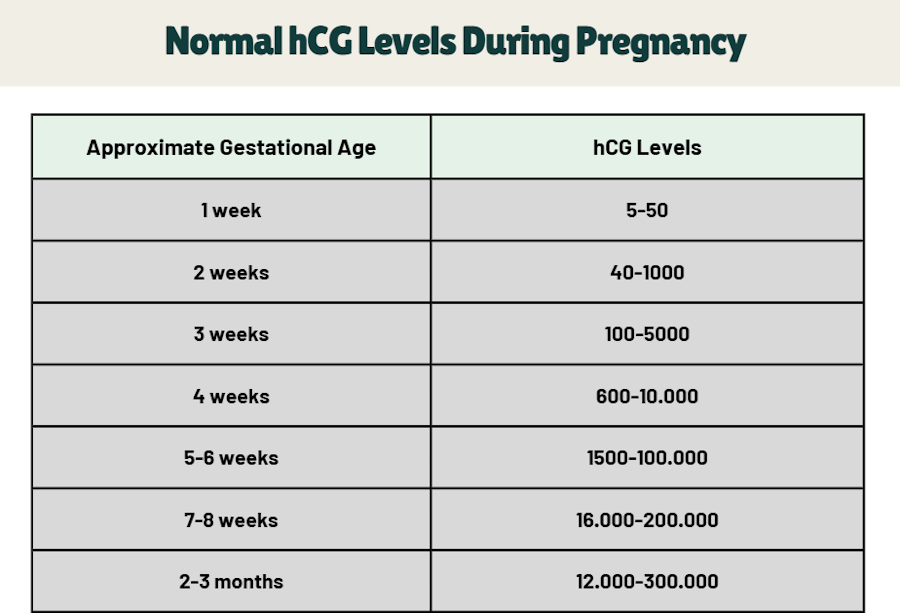
When you transfer two embryos via IVF and both implant, your hCG levels will generally run higher than a singleton pregnancy. That is the baseline truth. The chart people search for is usually a table showing expected hCG ranges week by week, often with separate bands labeled "singleton" and "twin." You will find these on fertility clinic websites, parenting forums, and a few lab reference pages. They are useful as a rough map, but they have real limits that most people do not read closely enough. Here is a simplified version of what those charts typically show. Values are in mIU/mL. Ranges are wide because individual variation is enormous. Week 3 post-transfer (about 3 weeks pregnant by standard dating): singleton range roughly 5–50, twin range roughly 25–300.
Week 4 post-transfer: singleton 50–500, twin 200–2,000. Week 5 post-transfer: singleton 200–7,000, twin 1,000–15,000. Week 6 post-transfer: singleton 2,000–50,000, twin 10,000–100,000.
Week 7 post-transfer: singleton 20,000–100,000, twin 50,000–200,000. These numbers come from composite data across multiple sources. Your clinic may report slightly different ranges depending on the assay they use. That matters more than you might expect. The reason I bring this up is because the single most common mistake people make with these charts is treating them as a prediction tool rather than a descriptive reference. A high number does not guarantee a healthy twin pregnancy. A lower number within the twin range does not mean something is wrong. I have seen both scenarios play out in real time, and it is one of the hardest parts of this process to sit with.
Get the Full Details
What matters more than the absolute number is the doubling time in early weeks. In a viable early pregnancy, hCG typically rises by about 53% to 100% every 48 hours during the first five to six weeks. Once it passes roughly 6,000 to 7,000 mIU/mL, the doubling time slows down significantly. It may take three or four days to double at that point. If you keep applying the early-pregnancy doubling expectation once the levels are high, you will misread perfectly normal scans as concerning. I learned this the hard way. I had a patient whose twin pregnancy reached an hCG of about 9,400 on day 4 after her first positive test. She came in worried because the rise from the prior draw was only 60% instead of the textbook 100%. Her instinct was to panic. We held off on intervention and just rechecked. By day 7, the level was 14,200. The growth curve had simply decelerated into the normal plateau phase. An early scan would have been unnecessary and possibly confusing. Waiting four days instead of two saved everyone a lot of anxiety and a costly ultrasound that would have shown nothing definitive anyway. There are a few other practical things you should know that charts rarely emphasize.
Assay variability between labs is real. One lab might report 8,200 while another reports 7,400 on the same sample. If you are tracking trends, stay with the same lab. Switching labs introduces noise that looks like a clinical problem when it is just methodological drift. Chemical pregnancies can mimic twin patterns early on. I once had a case where the initial hCG looked like a robust twin pregnancy at around 4,000, then dropped steadily. Both embryos had implanted but one arrested very early. The chart alone would have convinced you everything was fine. Serial monitoring is the only way to catch this, and even then, the answer often comes from ultrasound, not blood work. Very high numbers do not always mean two live sacs. A molar component or a vanishing twin can push hCG into surprisingly high territory. I saw a case where the level hit 180,000 at week 7 and the follow-up scan revealed one viable twin and one nonviable gestational sac. The mother was relieved it was not a molar pregnancy, but the high number had been misleading in isolation.
If you want a downloadable chart, most fertility clinics will print one from their patient portal. You can also find printable PDFs on sites like the American Society for Reproductive Medicine or through your IVF clinic's patient education materials. These tend to be more reliable than random forum versions, which sometimes contain transcription errors. Look for one that cites the source lab or includes a disclaimer about assay differences. That tells me someone actually thought about the limitations rather than just copying numbers. The most honest thing I can say about these charts is that they are a starting reference, not a diagnostic endpoint. They work best when combined with serial testing at the same lab, proper dating based on your transfer date, and ultimately an ultrasound confirmation. Relying on the chart alone will give you false confidence in some cases and false alarm in others. The data is there to guide you, not replace clinical judgment. If your numbers fall outside the expected twin range but you have no bleeding or severe pain, the usual move is to repeat the test in 48 to 72 hours rather than rush to intervention. If your numbers are rising slower than expected past the 6,000 to 7,000 threshold, ask your provider about an earlier scan rather than another blood draw. At that stage, ultrasound gives you more useful information than chemistry does.

Tracking twin hCG after IVF is straightforward in theory and frustrating in practice because human bodies do not follow charts. The numbers give you direction, not destiny. Use them, question them when they look odd, and trust the ultrasound when it arrives. That is the practical path through it.