Managing Type 1 Diabetes In Children Is More About Logistics Than Learning Medicine
Most parents are told within days of diagnosis that they need to learn carbohydrate counting, insulin dosing, and blood glucose monitoring. That is the official position. What nobody mentions is the sheer volume of micro-decisions a kid with T1D forces you to make between breakfast and bedtime. It accumulates. The kind of exhaustion that shows up around month four is not emotional, it is cognitive. I will walk through the practical side of managing Type 1 Diabetes In Children, starting with how most families actually structure insulin therapy, then the monitoring setup, then a few edge cases that do not appear in the pamphlets.
Type 1 Diabetes In Children and the Insulin Basics
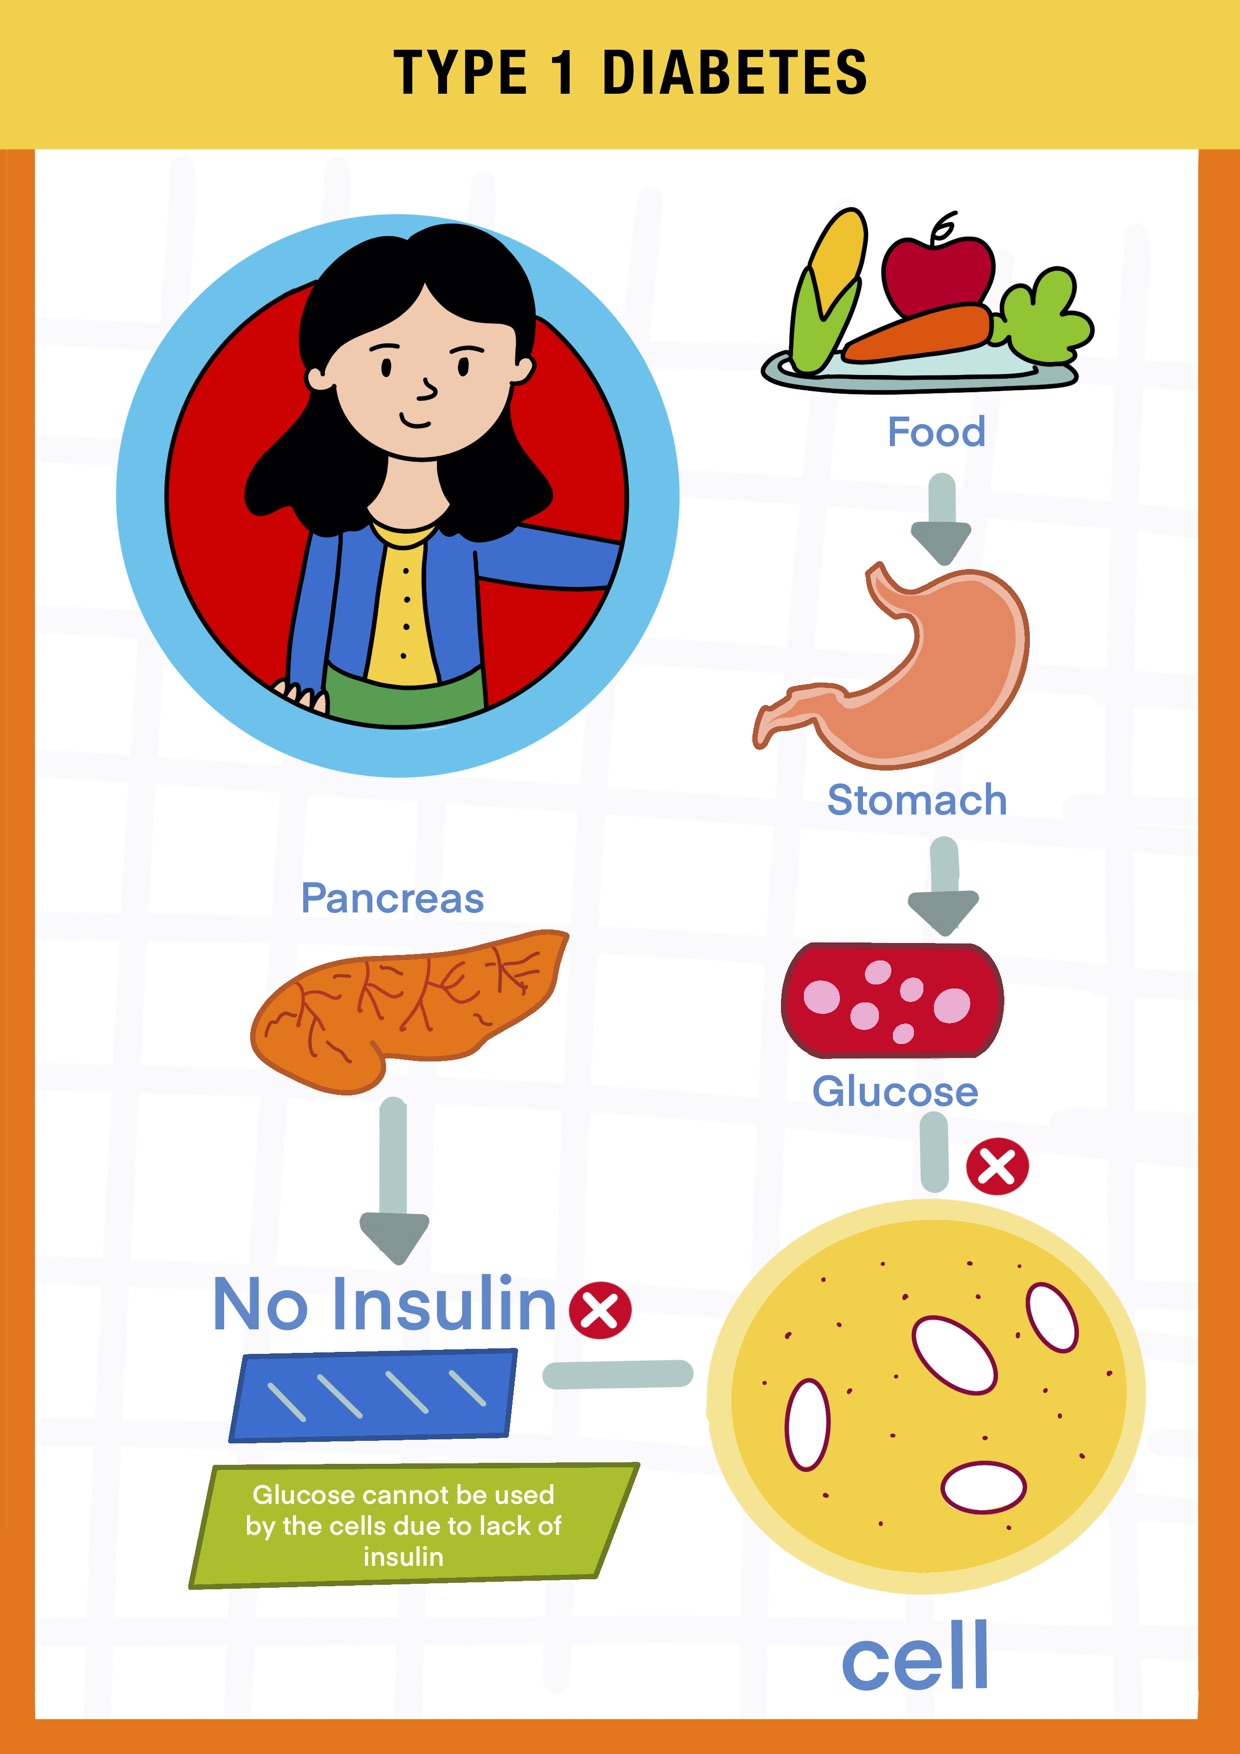
Children with T1D produce zero endogenous insulin. That means exogenous insulin is not optional, it is structural. The two main types used are rapid-acting insulin analogs like lispro, aspart, or glulisine for mealtime coverage, and long-acting analogs like glargine or detemir for baseline needs. Some programs still use NPH, but the newer analogs have flatter profiles and less unpredictability. The standard approach is basal-bolus dosing. A long-acting injection once or twice daily handles background needs. Rapid-acting doses are calculated per meal based on carbohydrate content and current blood glucose. The usual starting point for a carb-to-insulin ratio is one unit of rapid insulin for every 10 to 15 grams of carbohydrate, but that number varies wildly by age, weight, and insulin sensitivity. Most kids settle somewhere between a 1:8 and a 1:20 ratio after a few months of fine-tuning. Insulin sensitivity factor, sometimes called the correction factor, determines how much one unit of rapid insulin drops blood glucose. A common estimate is the 1800 rule for kids on regular insulin or the 1500 rule for analogs: divide 1500 by total daily dose to get roughly how many mg/dL one unit will lower blood sugar. If a child is on 30 units per day, one unit might drop glucose by about 50 mg/dL. This is a starting point, not a law. You adjust from there.
Monitoring: CGM versus Fingersticks
Continuous glucose monitors have made this significantly easier. The Dexcom G7 and Libre 3 are the current standards for pediatric use. These sensors measure interstitial glucose every few minutes and send readings to a phone or receiver. The main advantage is trend arrows and alerts. Parents get warned before a child hits hypoglycemia rather than discovering it after the kid starts shaking. Fingerstick checks are still necessary. CGMs lag behind blood glucose by roughly five to fifteen minutes because interstitial fluid changes slower than capillary blood. During rapid glucose shifts, after a glucose tablet for a low, or when symptoms do not match the CGM reading, a fingerstick is the reference point. Always calibrate if your device requires it, though the newer models like Dexcom G7 are factory calibrated and do not need routine fingerstick verification. For children under six, some endocrinologists still recommend a mix of CGM and periodic fingersticks because growth spurts change insulin needs frequently and the sensor can drift during those periods. The data from a CGM alone during a growth phase may look stable but actually be consistently offset by ten to twenty mg/dL until recalibrated.
Get the Full Details

The Pump Question
Pancreatic pumps deliver rapid-acting insulin through a catheter under the skin. They allow basal rate adjustments, extended boluses for high-fat meals, and automated suspend features when glucose drops. For children, pumps can reduce the number of injections and offer more granular control. But they also introduce a new failure mode. I had a family deal with this directly. Their seven-year-old was on a Tandem t:slim pump. The infusion set was placed on the abdomen. After about eighteen months, the child started having unexplained highs in the late afternoon, especially after soccer practice. The pattern was consistent but unexplained. Blood ketones were negative. Carb counting was accurate. The pump was delivering correctly according to the log. The issue turned out to be lipohypertrophy at the infusion site. Scar tissue from repeated injections in the same area had created a firm lump under the skin where the catheter tip sat. Insulin absorption from that site was delayed and erratic. The workaround was straightforward but not obvious to most parents: rotate the site more aggressively, use a new site every time instead of topping up the same one for three days, and do regular abdominal exams for lumps. We switched to rotating sites in a strict grid pattern, moving the insertion point at least two centimeters each time. The afternoon highs disappeared within a week. That problem costs families weeks of confusion if you do not know what you are looking for.
Pump use also carries a risk of ketosis if the infusion set fails silently. A kinked catheter or dislodged cannula can stop insulin delivery without the parent noticing immediately. Modern pumps have occlusion detection and low-resistance alarms, but they are not foolproof. That is why even pump users should check ketones during illness or unexplained hyperglycemia.
Hypoglycemia Management
Low blood glucose is the immediate danger. The goal is always prevention, but lows happen. The standard rule for treating a conscious child with a glucose below 70 mg/dL is fifteen grams of fast-acting carbohydrate, wait fifteen minutes, and recheck. Juice, glucose tablets, or regular soda work. Honey is an option for younger children who cannot swallow solids safely. There is a common mistake here. Parents often give more than fifteen grams because the child looks badly symptomatic. That overshoots and creates a roller coaster. A child weighing under twenty kilograms may only need eight to ten grams. Weight-based dosing matters even for hypoglycemia treatment. Ten grams of glucose is roughly a quarter cup of juice for a small child, not a full cup. Severe hypoglycemia requiring assistance is treated with glucagon. Injectable glucagon like Baqsimi is now available as a nasal powder, which is far easier for schools and daycare providers to administer than an injection. Keep a glucagon kit accessible at all times. Not just at home, at school too. I have seen too many kids treated only at home because the school did not have an action plan in place.

Sick Day Rules
Illness raises blood glucose through stress hormones like cortisol and epinephrine. This happens even with a stomach bug. The standard advice is to never stop basal insulin, even if the child is not eating. Basal needs may actually increase during illness. Check blood glucose every two to four hours. Check ketones if glucose is above 240 mg/dL. Offer fluids with electrolytes and small amounts of carbohydrate if the child cannot eat normally, but do not skip insulin to match reduced food intake without consulting the care team. Skipping basal insulin during illness is how diabetic ketoacidosis starts. A Section 504 plan or an individualized health plan is necessary for school. It should cover blood glucose checking, snack access, insulin administration, glucagon availability, and accommodation for hypoglycemia during class. Most schools can handle this without difficulty once the documentation is in place. The harder part is the social side. Older children notice the differences. A nine-year-old may refuse to check glucose before a birthday party. That is normal. The workaround is negotiation, not force. Let the child check themselves if they are old enough. Give them the CGM receiver or let them see the app on your phone. Autonomy reduces resistance. Type 1 Diabetes In Children requires lifelong management. There is no cure yet. Islet cell transplantation exists but is reserved for severe cases with frequent hypoglycemic unawareness due to the immunosuppression required. Artificial pancreas systems, or closed-loop insulin delivery, are the closest thing to a breakthrough currently available. Systems like the Medtronic 780G and Tandem Control-IQ automatically adjust basal insulin every five minutes based on CGM data. Studies show these systems improve time in range by roughly ten to fifteen percent compared to manual management, which translates to fewer highs and lows over a year. They are not perfect. They can overshoot after high-fat meals, and the algorithm needs a stable baseline to work well. If a child's daily insulin needs fluctuate wildly day to day, the closed loop may struggle until the pattern stabilizes.
Most kids with well-managed T1D live normal lives. The data is clear on that. The burden falls on the parents and the children themselves to manage the constant calculations. The system works when you understand the mechanics and anticipate the friction points before they become emergencies.