Most people learn CBT for anxiety wrong because they skip the mechanics
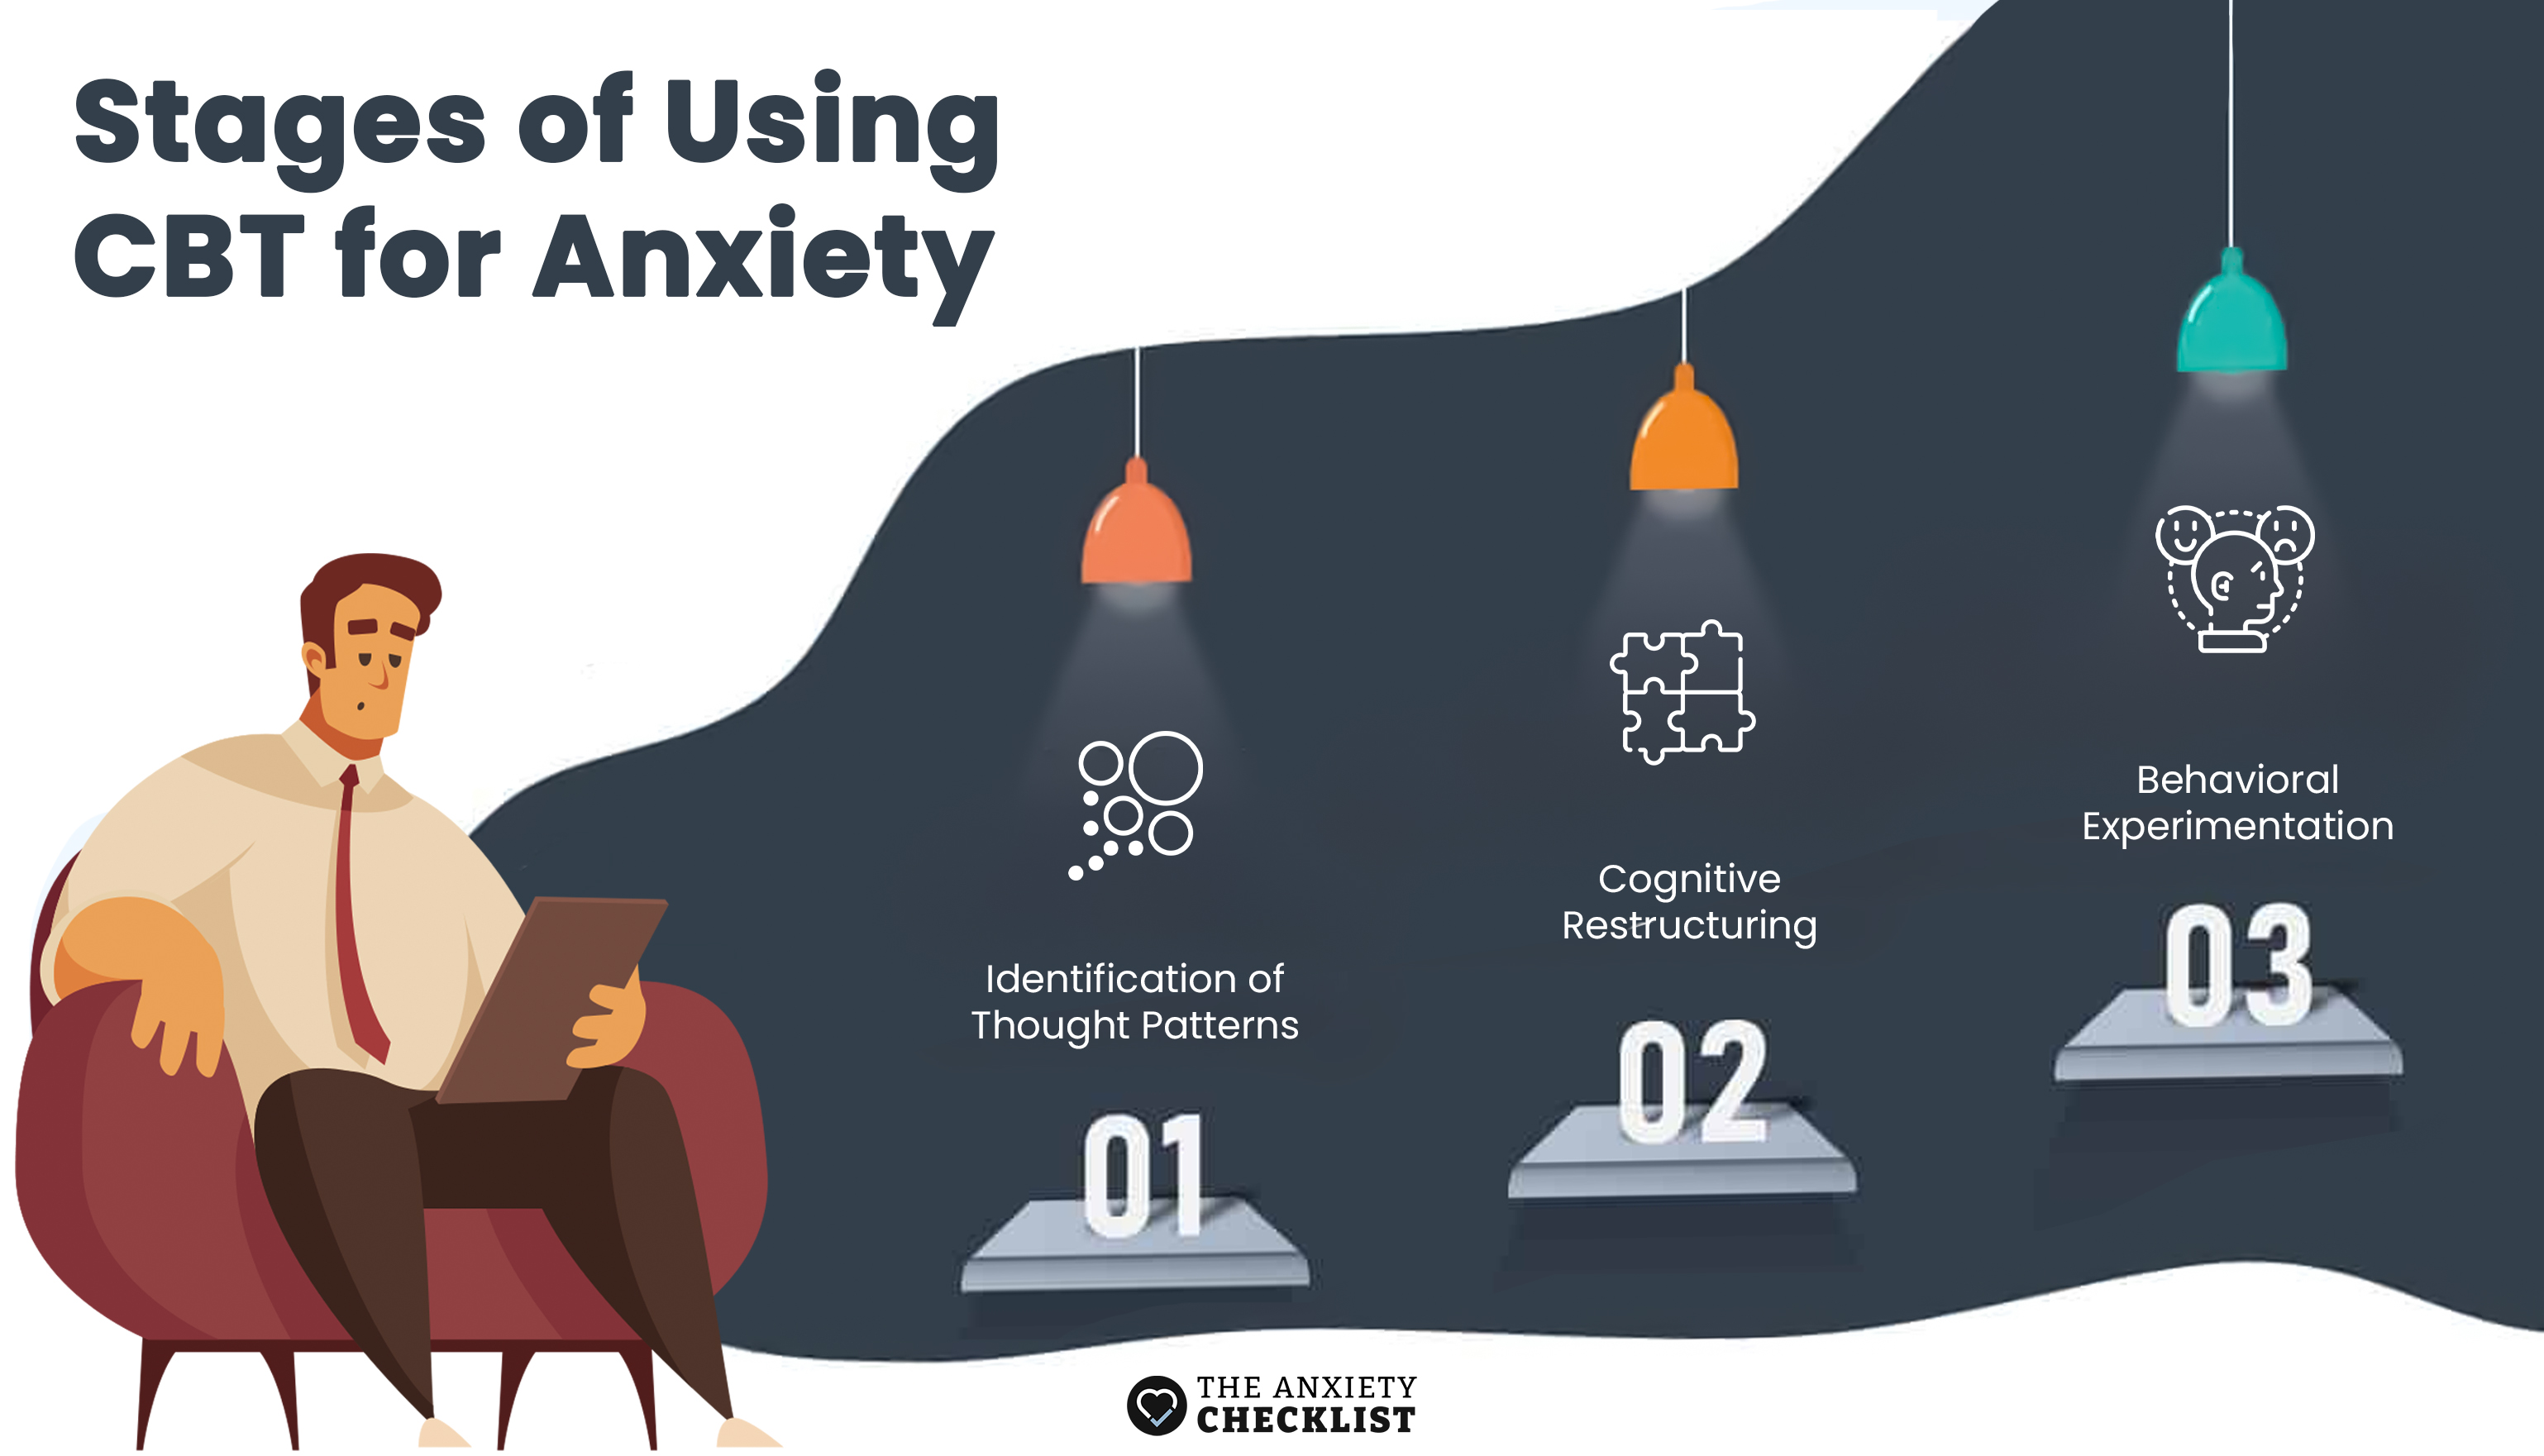
I spent years watching patients and peers try the standard cognitive restructuring scripts and fail because they treated anxiety like a logic problem instead of a conditioned response. The brain doesn't care about your evidence list when it's in full amygdala mode. You can read every rational argument you wrote down and still not feel safer walking past that intersection. That gap between knowing something cognitively and actually feeling it is where most CBT approaches for anxiety break down. "Cognitive behavioral therapy" is an umbrella term that covers several distinct techniques, and most online resources lump them together without explaining which ones actually address which anxiety mechanisms. Standard CBT focuses on identifying and challenging cognitive distortions—catastrophizing, mind reading, emotional reasoning. But exposure-based protocols,ACT (Acceptance and Commitment Therapy), and metacognitive therapy each work through completely different pathways. Treating all of them as the same thing is why so many people report that CBT didn't help them when they really just tried the wrong subtype for their particular anxiety pattern. The three most practically useful subtypes for anxiety are cognitive restructuring, exposure therapy, and metacognitive therapy. They're not interchangeable. Cognitive restructuring works best for anxiety driven by high threat appraisal—people who genuinely believe dangerous outcomes are likely. Exposure works best when avoidance is the maintaining factor. Metacognitive therapy works when the person's anxiety about their anxiety is what keeps it spinning. Getting the subtype wrong means you're either not treating the real driver or you're treating it inefficiently.
I had a client once who'd been doing standard CBT for two years for social anxiety. She could articulate every cognitive distortion on demand and her thought records were immaculate. She still couldn't go to a restaurant where she had to speak to a server. The problem wasn't her thinking patterns. It was that she'd never done behavioral experiments under actual anxiety conditions. She'd been cognitive-restructuring her way around the stimulus for eighteen months. I switched her to in-vivo exposure with stimulus control—specifically having her order food at increasingly busy restaurants while blocking all safety behaviors like rehearsing what she'd say or gripping her water glass. Progress that should have taken three sessions took six months because we'd spent all that prior time on the wrong lever. Not saying this to shame anyone. Just noting how common it is to treat the symptom instead of the mechanism.
How Each Subtype Actually Works Under the Hood
Cognitive restructuring follows a structured process: identify the automatic thought, evaluate the evidence for and against it, generate a balanced alternative thought, and test it behaviorally. The technical term is Socratic questioning, and it's most effective when you're working with explicit threat beliefs. "If I speak up in this meeting, everyone will think I'm incompetent." You find evidence for that, evidence against it, and build a more calibrated prediction. The limitation is that this approach requires intact prefrontal cortex function. When anxiety spikes high enough to cause cognitive impairment—which happens with panic disorder, severe social anxiety, and OCD-related anxiety—the person literally cannot access the rational reasoning pathway during the episode. Cognitive restructuring is useless in that moment and often gives false hope if presented as the primary tool. Exposure therapy operates on inhibitory learning principles, which is a significant shift from the older habituation model. The old model assumed repeated exposure would reduce anxiety through mere repetition until the fear weakened. Modern exposure therapy, based on Craske and colleagues' work, recognizes that anxiety doesn't just fade with time. Its when the brain learns that the feared outcome didn't occur, or occurred but was tolerable. The key mechanism is prediction error—the discrepancy between what the person expects and what actually happens. Your therapeutic strategy should focus on manipulating expectations before exposure, not just putting the person in the situation. If you expose someone without addressing their predictions, you're just doing desensitization, which has high relapse rates because the underlying threat expectancy remains unchanged. I ran into a specific edge case with exposure that surprised me consistently. Some clients with health anxiety would go through their exposure hierarchy perfectly—touching doorknobs, going to the gym, eating unfamiliar food—and still report no improvement. The issue was that they were performing the exposures with covert safety behaviors they hadn't acknowledged. One person would touch a public restroom door handle but immediately rub it off on their pant leg, which is a form of washing-adjacent compulsion that nullifies the learning. Another would go to a crowded place but constantly check her pulse, which is a body-scanning safety behavior. The workaround was simple: I required them to film themselves during exposures or describe their safety behaviors in real-time. You'd be shocked how many people don't realize they're doing them until you make them visible.
Get the Full Details

Metacognitive therapy is the least intuitive of the three but the most powerful for certain anxiety profiles. It targets mTypesof CBT For Anxietyegative beliefs about thinking itself—things like "I need to control my thoughts to stay safe" or "If I notice this worry, it means something bad is coming." Worry, in MCT theory, is a cognitive avoidance strategy. The person believes that worrying about a problem gives them a sense of control, so they engage in prolonged worry to avoid confronting the emotional content of their fears. The therapy involves distinguishing between Type 1 worry (about external events) and Type 2 worry (worry about worrying itself), then using detached mindfulness to disengage from the thought stream without trying to replace or suppress it. The technique feels counterintuitive because you're literally teaching the person not to fight their thoughts, which is the opposite of everything most anxiety sufferers have been told. Interoceptive exposure deserves mention as a specialized subtype specifically for panic disorder. This involves deliberately producing physical sensations that the person fears—spinning in a chair to create dizziness, breathing through a straw to simulate breathlessness, running in place to elevate heart rate. The rationale is that panic attacks are often maintained by fear of the bodily sensations themselves, not the sensations being dangerous. A person who interprets a rapid heartbeat as a heart attack will panic because of the interpretation, not the sensation. Repeatedly inducing the sensation without the catastrophic outcome occurring rewrites that association. This is technically a form of exposure therapy but so specific that it's often discussed separately in the literature.
Common Pitfalls That Derail Treatment
The first major pitfall is the hierarchy trap. Exposure hierarchies are standard practice, but when they're too gradual, they become avoidance by another name. A client who starts with imagining a social situation rather than entering one is essentially avoiding the actual learning opportunity. The research by Farchione and colleagues suggests that starting closer to the feared stimulus—what they call "intensive exposure"—produces stronger inhibitory learning than slow gradational approaches. This isn't about throwing people into the deep end without support. It's about recognizing that small steps don't always compound into big results when the anxiety system treats a mildly scary situation and a terrifying situation as roughly equivalent in terms of threat prediction. The second pitfall is cognitive fusion masquerading as cognitive restructuring. A person with anxiety will often agree with a balanced thought during a session—"Yes, it's possible the presentation will go fine"—and then immediately revert to the anxious thought outside the room. This happens because they intellectually accept the alternative but haven't emotionally disconfirmed the original threat belief. The workaround is to move quickly from cognitive work to behavioral experiments. The cognitive restructuring should serve as a hypothesis generator, not a conclusion. "You think the presentation will go fine now. Let's go give a five-minute talk to three people and see what actually happens." The behavior is where the learning occurs. The thought is just a prediction to be tested. A third pitfall specific to online CBT programs is the absence of therapeutic alliance effects. Research consistently shows that the therapeutic relationship accounts for a substantial portion of CBT outcomes, regardless of the specific technique. Self-guided CBT for anxiety has moderate effect sizes, but therapist-guided CBT shows significantly larger effects across most studies. If you're working with a self-help resource, be aware that the effect is real—many people reach a ceiling in improvement because they lack the feedback loop that a therapist provides. This doesn't mean self-help doesn't work. It means it works better for mild-to-moderate anxiety than for severe or comorbid presentations.
Practical Steps If You're Starting This
If you're beginning to work with Types Of Cbt For Anxiety on your own, start by identifying which subtype fits your anxiety pattern. Ask yourself: is my anxiety mainly driven by distorted threat predictions, by avoidance of feared situations, or by a persistent worry loop that I can't shut off? If it's the first, cognitive restructuring plus behavioral experiments will likely be most helpful. If it's the second, exposure-based work is the priority. If it's the third, metacognitive strategies may be more effective than any form of cognitive restructuring. The second step is to map your specific triggers and avoidance patterns. Not in a clinical assessment way, but in a practical way that lets you see the structure of your anxiety. What situations do you avoid? What bodily sensations do you monitor? What thoughts precede your anxious episodes? This isn't about self-diagnosis. It's about building a data set that tells you which intervention target is most relevant. The third step is to engage with the appropriate technique consistently and measure progress objectively. Self-monitoring sheets, anxiety ratings before and after exposures, frequency counts of worry episodes—whatever metric makes sense for your pattern. Without measurement, you're guessing whether the approach is working. With measurement, you can adjust mid-course rather than abandoning something that needs six more sessions instead of quitting after four.
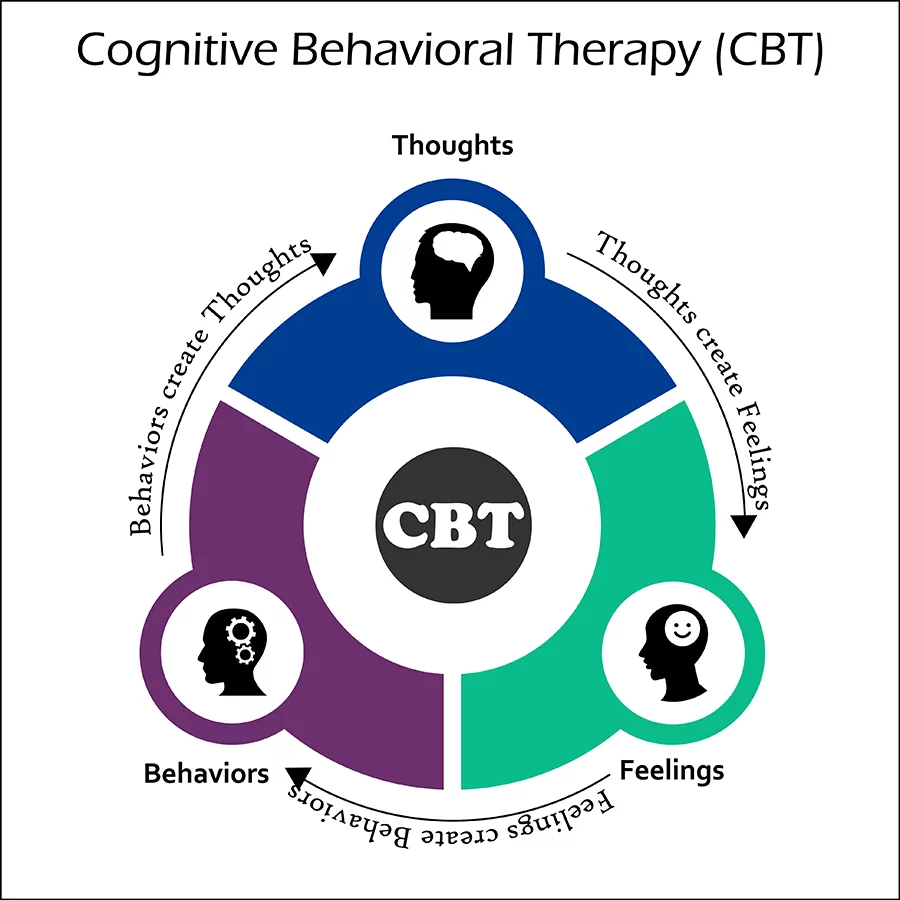
I should note that these approaches have real limitations. Cognitive restructuring has limited utility when anxiety is severe enough to impair prefrontal function. Exposure therapy can temporarily increase distress and has dropout rates of roughly 20-25% in some studies, particularly when the exposure protocol isn't properly individualized. Metacognitive therapy is less studied for generalized anxiety than CBT is, and the evidence base, while growing, is smaller. None of these are universal solutions. Some people with complex trauma histories, for example, will find that standard exposure protocols can be destabilizing rather than helpful, and that a phase-based approach focusing on stabilization first is more appropriate. Knowing when an approach is insufficient is as important as knowing how to use it when it is appropriate. If your anxiety is severe, impairing daily functioning, or accompanied by depression or substance use, professional guidance is not optional. These tools work best when applied with knowledge of the mechanisms involved, and that knowledge is difficult to acquire from reading alone. A qualified therapist can help you distinguish which subtype fits your presentation and adjust the approach as you respond—or don't respond—to initial intervention.