The Phases You Actually Deal With
Types Of Clinical Trials
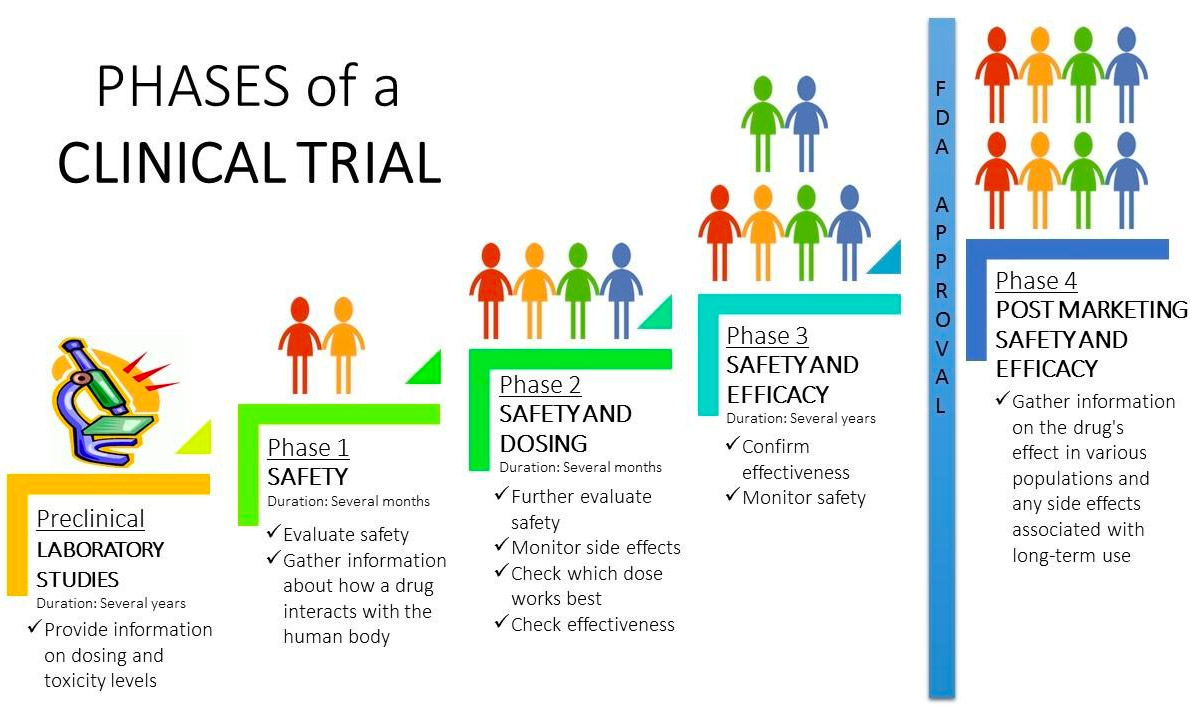
I spend more time reviewing trial protocols than I care to admit. Most people think clinical trials are a straightforward sequence of Phase 1, Phase 2, Phase 3, Phase 4. That's the textbook version. In practice, the landscape is messier, and the distinctions matter when you're trying to figure out which design fits your question and which one will get your protocol sent back by the IRB for not making enough sense on page three. Phase 1 trials are where the drug goes into humans for the first time after preclinical work. You're looking at healthy volunteers in about 70 percent of cases, though oncology Phase 1s use patients because the toxicity profile makes it unethical to give a cytotoxic agent to someone who doesn't have cancer. The sample size is small, usually between 20 and 80 people. The primary endpoint is safety and dose-escalation, which means you're trying to find the maximum tolerated dose or the recommended Phase 2 dose. This is where the frequentist approach hits its limits, and people are switching to model-informed drug development with Bayesian adaptive designs that update dose probabilities in real time as data comes in. Phase 2 splits into two subcategories that don't get enough attention. Phase 2a is dose-finding. You already know roughly what dose range is tolerable from Phase 1, and now you're narrowing it down. Phase 2b is efficacy-signal generation. You're still looking at safety, but the question shifts from "does this kill people?" to "does this do anything at all?" Sample sizes run from 50 to 300. If you skip a proper Phase 2 and go straight to Phase 3 with an underpowered study, you'll waste three years and $30 million finding out your drug doesn't work. I've seen it happen twice in my career.
Phase 3 is the confirmatory stage. This is where regulatory decisions are made. Randomized controlled trials with hundreds to thousands of patients, comparing your intervention against standard of care or placebo. The endpoints need to be clinically meaningful, not surrogate markers, if you want the FDA to actually approve something. I remember reviewing a Phase 3 protocol for a diabetes drug where the sponsor wanted to use HbA1c reduction as the sole primary endpoint without any hard cardiovascular outcomes data. The FDA rejected it and asked for a separate CVOT, which added two years and $80 million to the development timeline. That could have been avoided if they'd read the guidance document beforehand. Phase 4 trials happen after approval. Post-marketing surveillance, pharmacovigilance, sometimes optional studies required by the agency as a condition of approval. These catch rare adverse events that Phase 3 never would have seen because you simply didn't have enough patients. The thalidomide disaster is the textbook example, but there are more recent ones like Vioxx being pulled from the market because post-marketing data revealed increased cardiovascular risk that wasn't detectable in the pre-approval trials.
The Designs That Aren't Phases
There are clinical trial designs that cut across phases, and most beginners don't understand how they work until they've made the mistake of trying to use them wrong. Adaptive designs are the big one. You modify aspects of the trial while it's running based on interim data, things like changing the sample size, dropping an arm, or switching the primary endpoint. They sound efficient on paper, and they can save weeks or months, but they introduce operational complexity that most sites aren't set up to handle. You need independent data monitoring committees, pre-specified adaptation rules baked into the statistical analysis plan before you start, and a lot more coordination between biostatisticians and clinical operations than a traditional trial requires. Platform trials are another design worth knowing about. Instead of testing one drug against placebo, you test multiple drugs against a shared control arm, and drugs can drop out or new ones can join as data accumulates. The REMAP-CAP trial during COVID-19 is the most famous example. It ran for years and tested dozens of interventions across ICU patients. The design is elegant, but it requires significant upfront investment in infrastructure and regulatory buy-in. Most sponsors don't have the resources or the appetite for that level of complexity. Pragmatic trials blur the line between research and routine clinical practice. You're testing whether an intervention works in real-world conditions, not under the tightly controlled circumstances of a Phase 3 RCT. These are becoming more important for health services research and payers who care about effectiveness, not just efficacy. The downside is that they're noisy, harder to interpret, and the results can be ambiguous because there's less control over confounding variables. A pragmatic trial that shows a drug works "in the real world" might not tell you much about why it works or for whom it works best.
Get the Full Details

Where Things Go Wrong
I've reviewed enough protocols to know the common failure points. One issue that comes up constantly is endpoint selection. Sponsors often pick surrogates that regulators don't accept, or they design trials with composite endpoints that are so broad they mean nothing. A trial reporting "major adverse cardiovascular events" as a composite of death, heart attack, and stroke sounds impressive, but when you dig into the data and half the events are minor strokes that barely affected quality of life, the clinical meaningfulness evaporates. Another problem is population heterogeneity. I worked on a neurology trial a few years ago where the inclusion criteria were so loose that we ended up with patients at widely different stages of their disease. The treatment effect looked promising overall, but when we did a post-hoc analysis stratified by disease severity, the drug only worked in mild-to-moderate patients. The Phase 3 protocol missed this entirely because it was designed with a heterogeneous population that diluted the signal. Lesson learned: define your population narrowly enough to detect a real effect, but broadly enough that the results generalize. There's also the issue of site selection. Phase 1 sites tend to be specialized clinical research organizations with experience in first-in-human studies. Phase 3 sites are more varied, and that variability matters. A site that routinely treats the disease you're studying will recruit faster, retain patients better, and collect higher-quality data than a site that sees one case a year. I used to recommend looking at a site's historical performance data before contracting with them, but most sponsors skip that step because it adds two to three weeks to site activation. It's a false economy.
What Nobody Tells You
Biological plausibility matters more than the statistical design on paper. I've seen beautifully designed Phase 2 trials fail because the mechanism of action didn't hold up in humans, and I've seen ugly trials succeed because the target was right. The phase classification tells you something about the regulatory pathway, but it doesn't tell you whether your drug has a shot. That depends on preclinical data, target validation, and whether the biology actually translates from animals to people. The cost escalation between phases is steeper than most people realize. A typical Phase 1 runs around $5 to $10 million. Phase 2 can hit $20 to $50 million depending on the indication. Phase 3 is where budgets explode, easily $100 to $500 million for a large cardiovascular or oncology trial. The variance is enormous because it depends on patient numbers, geographic scope, endpoint complexity, and how many sites you need. I once had a Phase 3 cardiology trial blow past its $180 million budget and end up at $310 million because the enrollment targets weren't met for eight months and the sponsor had to open 40 additional sites at short notice. Regulatory pathways vary by jurisdiction in ways that trip people up. The FDA, EMA, and NMPA in China all have different requirements for clinical trial data. A trial designed to satisfy the FDA might not meet EMA expectations on statistical methodology, and vice versa. If you're planning a global development program, you need to align with both agencies early, ideally during the pre-IND or scientific advice meetings, not after you've already collected data that one of them considers inadequate.
The types of clinical trials available to you depend heavily on what stage your product is at and what your regulatory strategy is. There's no one-size-fits-all answer, and the trial design you choose will shape everything from your budget to your timeline to whether your drug gets approved. Most failures aren't caused by bad trial designs in the abstract; they're caused by mismatched designs, where the sponsor picks a phase or a trial type without fully considering whether it actually answers their question.




