So you need to pick a cueing approach for your therapy sessions.
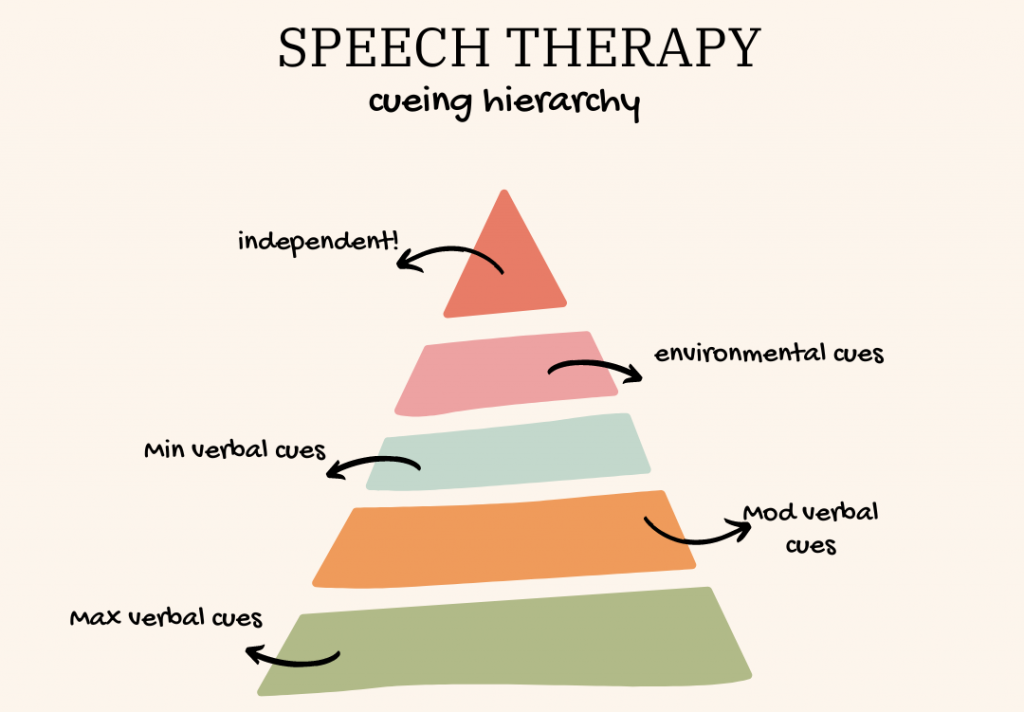
The reality is that most clinicians just grab whatever feels easiest in the moment. That tends to produce messy results. I spent years building a system that actually sticks, and the biggest shift was realizing cueing isn't one thing — it's a menu you pull from based on the client's specific error pattern and stage of acquisition. Before I get into the types, here's the framework most people skip. Cues exist on a hierarchy from most intrusive to least intrusive. You start high and systematically fade down. If you stay too high in intrusiveness for too long, the client becomes dependent on your prompt and never generalizes. If you drop too fast, you lose traction on the target sound. Both happen constantly in my practice.
Types Of Cueing Speech Therapy
Auditory cueing is the baseline. You model the correct production and the client imitates. That's it. This works beautifully for kids who have the motor plan but just need a clear template. I've seen it fail spectacularly with motor planning disorders, which is worth noting because a lot of new clinicians treat all errors the same way. The workaround there is pairing auditory input with a visual or tactile cue so the client has more than one channel to latch onto. Visual cueing involves showing the client what the articulators should do. Mirrors are the standard tool. Some therapists draw simple diagrams on paper showing tongue placement. Others use real-time ultrasound, which is powerful but access-restricted and expensive. What I've found is that visual cues work best when paired with auditory modeling rather than standing alone. A kid watching a mirror while hearing the sound produced makes the connection faster than either input by itself. Tactile cueing is where you physically guide the client's articulators. Touching the lips together for /p/ and /b/. Placing a finger under the chin to feel the lip raise for /t/ and /d/. Pressing gently on the throat to demonstrate vocal fold vibration for voiced versus voiceless contrasts. This is the most concrete type and it tends to produce the quickest initial acquisition for sounds that require specific articulatory positioning. The trade-off is that tactile cues can be overused to the point where the client won't attempt the sound without physical guidance. I keep a hard rule: fade tactile input by half the intensity every three to five successful productions.
Kinesthetic cueing asks the client to feel the movement themselves, often by having them touch their own throat or jaw to monitor the sensation. It's essentially self-monitoring training wrapped into the cue. This is the type that bridges the gap between therapist-guided production and independent use. I consider it the most important cue type for long-term retention, which is why it gets underutilized. Most people stop at tactile and call it a day. Gestural or mnemonic cueing uses a hand sign, symbol, or visual marker to represent a sound or rule. A thumbs up for correct placement. A specific finger gesture that stands in for "put your tongue behind your teeth." I picked up this approach from work with nonverbal and minimally verbal clients, and it translates surprisingly well to typical populations when you need a consistent, portable cue that doesn't require you to be physically touching the person. Then there's the cascade or hierarchy model, which isn't a single cue type but a system for sequencing them. You present the target with maximum support, then systematically remove each layer. Auditory only, then visual only, then no cue at all. The research on this goes back to the 1980s and it still holds up as one of the most reliable frameworks for structuring a session. What the literature doesn't emphasize enough is that the fade rate needs to be individualized. Some kids drop from tactile to independent in a single session. Others regress three steps back if you move too quickly.
Get the Full Details

A common mistake I see is applying the same cueing type across all target sounds in a session. It doesn't work that way. The /r/ sound needs different cues than /s/, and a lateral lisp requires completely different tactile input than a frontal substitution. I keep a quick reference sheet at my desk mapping common error types to their most effective cue strategies, and it cuts my planning time from about twenty minutes per session down to roughly four. Another thing nobody warns you about: cueing interference. When a client is working on two sounds simultaneously and the cues for each one conflict, you can actually make their error patterns worse. I ran into this with a seven-year-old who was targeting both // and /s/ in the same block. The tactile cue for // involved tongue-between-teeth placement, which accidentally triggered a lateral /s/ production instead of the targeted sound. Switching to a gestural cue for // and keeping /s/ on auditory-only resolved it within two sessions. The biggest limitation of cueing-based therapy as a whole is that it assumes the barrier to production is motor or perceptual. It doesn't help when the underlying issue is linguistic processing, auditory processing disorder, or apraxia of speech where the plan itself is degraded. For those cases, you need a different framework entirely. Don't force cueing into a situation where it won't work just because it's comfortable.
If you want a practical starting point, pick one error sound, map its articulatory requirements, choose the least intrusive cue that can still produce a correct model, and set a measurable fade schedule before the session begins. Writing that plan down takes about ninety seconds and saves you from drifting into trial-and-error during the actual session.