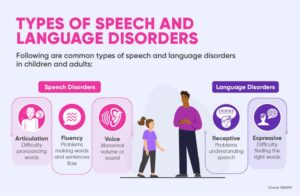
Actually Understanding Expressive Language Disorders
Most people conflate expressive language disorders with general speech problems, and that confusion causes real issues in clinical settings. I've seen assessment reports where a kid was labeled with a phonological disorder when they actually had a morphological deficit, and the treatment plan went completely sideways because of it. Let me walk through how this actually breaks down in practice.Expressive language disorder isn't one condition. It's a category, and the subtypes matter enormously for intervention. You've got pragmatic language impairment on one end, specific language impairment on the other, and a bunch of middle-ground presentations that don't fit neatly into either box. The DSM-5 collapsed most of these under Language Disorder, but clinicians still work with the subtype framework because treatment approaches diverge significantly depending on where the breakdown happens. Morphological deficits are the most commonly missed subtype. A child might have decent vocabulary but consistently drop past-tense markers, confuse pronoun agreement, or fail to add plural -s. These look like carelessness to untrained observers. They're not. The neural pathway for morphological rule application is just not developing on schedule.
I had a nine-year-old last year who could quote entire passages from chapter books verbatim but couldn't construct a single complex sentence on his own. His vocabulary was in the 90th percentile for receptive comprehension, but his expressive output maxed out at 3-4 word strings with zero subordination. We spent six weeks running a structured syntax elicitation protocol before we saw meaningful gains. The workaround was abandoning traditional story-retell exercises entirely and switching to forced-choice generation tasks where he had to produce a specific grammatical structure to get what he wanted. Hunger motivation works better than social motivation for this population, honestly. Semantic-lexical deficits present differently. Word-finding difficulty, or anomia, is the hallmark. These kids pause frequently during speech, use vague fillers like "thing" or "stuff," and often give up on complex utterances altogether. The frustrating part for therapists is that their comprehension is usually intact, so they know exactly what they want to say. The disconnect between productive and receptive capacity is what makes this subtype particularly isolating for children. Pragmatic language impairment sits at the intersection of expressive and social communication. These kids struggle with discourse-level organization, turn-taking, topic maintenance, and adjusting language to different listeners. A typical example: they can produce grammatically correct sentences in isolation but can't string them into a coherent narrative or adapt their register when talking to a peer versus an adult.
Phonological expressive disorder is sometimes grouped here too, though technically it overlaps with speech sound disorders. The key differentiator is whether the issue is purely motor-phonological or truly linguistic in nature. Kids with pure speech sound disorders often have normal language structure once you account for the articulation errors. Kids with expressive language disorders have structural problems that exist independently of phonology.
Get the Full Details

Assessment Nuances That Matter
Standardized testing alone will miss a significant portion of expressive language disorders. I've seen cases where a child scored in the average range on a formal battery but functionally couldn't follow a two-step direction in a noisy classroom. The discrepancy comes from the fact that most tests are given in quiet, controlled conditions with visual support and patient administration. Dynamic assessment is the workaround here. You test, intervene briefly, then retest to measure learning potential rather than static ability. A child who shows rapid improvement after minimal scaffolding likely has an expressive language disorder rather than a cognitive or attentional issue. The protocol takes about 20 minutes per domain and gives you more predictive validity than any norm-referenced score alone. Achievement tests also mask expressive deficits. When a kid reads aloud, they're demonstrating decoding and comprehension, not necessarily expressive language. When they write, fine motor skills and spelling knowledge confound the picture. The best single indicator I've found is a picture-description task with follow-up questions that require active construction, not recognition. It takes about 8 minutes and reveals gaps that standardized tests consistently miss.
Treatment Approaches and Their Limits
Structured input-output training is the evidence-based standard. The core mechanism is repeated retrieval practice within increasingly complex syntactic frames. A typical session runs 30 to 45 minutes, three times weekly, with measurable gains appearing around week six for most children. The limitation most clinicians gloss over is generalization. A child can learn to produce past-tense -ed in the therapy room and then fail to use it in every other context for months, sometimes years. Generalization isn't automatic. It requires deliberate practice across multiple settings, multiple partners, and multiple modalities. If you're not scheduling carryover activities into home and classroom environments, you're probably wasting about half your intervention time. Narrative intervention shows moderate effect sizes but requires significant parental involvement. Parents need training in elaborative questioning techniques, which adds roughly 15 minutes per day to existing routines. Compliance drops off sharply after week four without ongoing therapist check-ins. I've found that biweekly parent coaching calls the carryover rates above 60 percent, compared to maybe 20 percent with written instructions alone.
Pharmacological approaches don't exist for expressive language disorders specifically. Some clinicians prescribe stimulants for comorbid ADHD to improve engagement, but that's treating the attention component, not the language disorder itself. The evidence for any medication directly improving expressive language is essentially nonexistent.

Common Pitfalls
The biggest mistake I see is treating all expressive language difficulties as the same condition and applying uniform intervention. A child with morphological deficits needs different drills than a child with pragmatic impairment, and a child with semantic-lexical deficits needs vocabulary-intensive work that looks completely different from both. Mixing these up delays progress by months. Another pitfall is over-relying on parent-reported milestones. Parents are excellent at noticing when a child isn't talking as much as peers, but they're poor discriminators between typical variation and clinical disorder. My rule of thumb: if a child under five is producing fewer than 50 words or hasn't combined two words spontaneously, that warrants immediate formal assessment regardless of what the parents report at home. The third pitfall is stopping intervention too early. Expressive language disorders have long tails. Gains plateau around age 12 as academic language demands increase dramatically, and what looked like adequate expression in elementary school becomes a significant disability in middle school science and history classes. Monitoring should continue through at least eighth grade, preferably longer.



