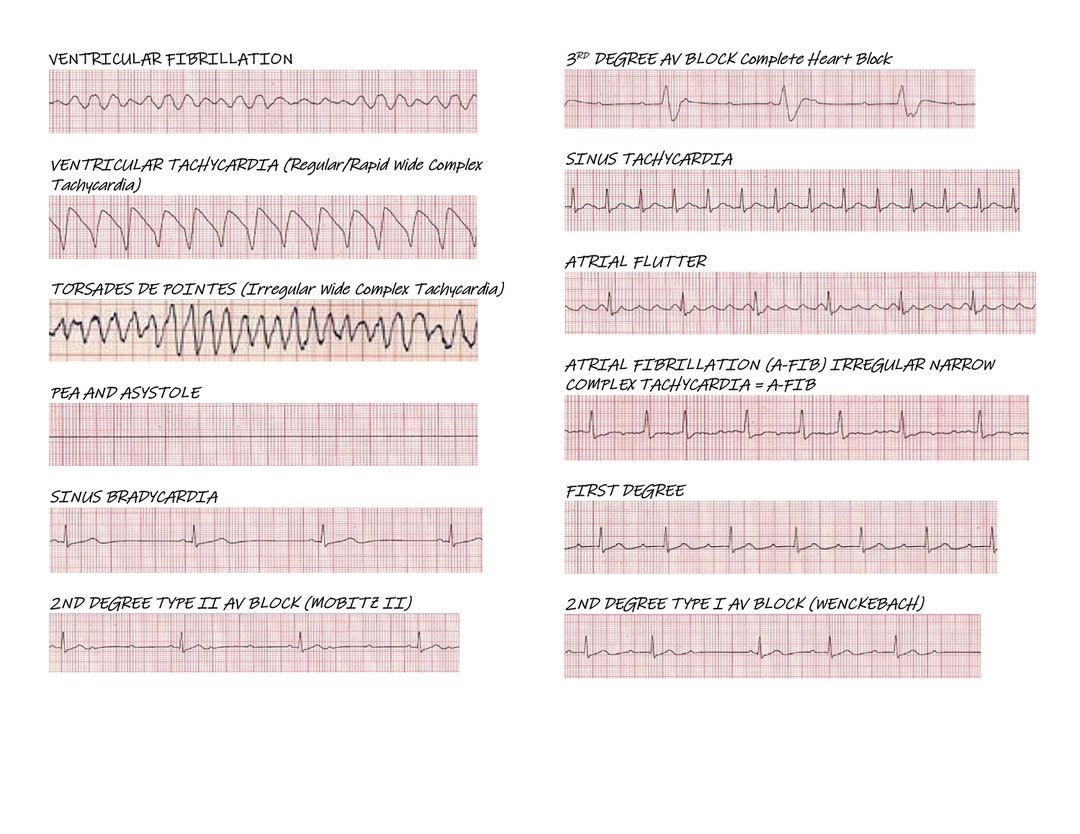
Understanding Cardiac Rhythm Patterns in Clinical Practice
The heart conducts electricity through a specific pathway, and when that pathway changes, the rhythm changes with it. This is basic electrophysiology, but the way different types of heart rhythms present on an ECG strip can be confusing if you're just starting out. I've spent years reading telemetry strips and 12-leads, and honestly, the biggest problem isn't memorizing definitions—it's learning to recognize patterns under pressure when the monitor is alarming and you have about thirty seconds to decide what's going on. Sinus rhythm is the baseline. Regular P wave before every QRS, rate between 60 and 100, PR interval between 0.12 and 0.20 seconds. Anything outside those parameters gets labeled with a qualifier—sinus bradycardia, sinus tachycardia, sinus arrhythmia. The qualifier matters because it changes the clinical context, but the underlying mechanism is the same: the SA node is firing and the conduction system is working as designed. Atrial fibrillation is probably the most common sustained arrhythmia you'll see in adults over fifty. No P waves, just irregularly irregular ventricular response with coarse or fine fibrillatory waves somewhere between the QRS complexes. The atria are essentially quivering instead of contracting. Rate control is usually the first priority—beta blockers or calcium channel blockers to slow the AV node down. Rhythm control with cardioversion or antiarrhythmics is a separate decision that depends on symptoms, duration, and stroke risk. Don't forget anticoagulation. A CHADS-VASc score of 2 or higher in men means you're talking about blood thinners, full stop. I've seen too many people sent home on nothing after a new AF diagnosis because nobody checked the score.
Atrial flutter is more organized than fibrillation but just as clinically significant. You'll see those classic sawtooth F waves, usually at an atrial rate around 300 beats per minute. The AV node blocks some of those impulses, so the ventricular response often comes in at 150 with a 2:1 block—that's a telltale sign. Less commonly you'll see 3:1 or 4:1 blocking. The tricky part is that atrial flutter can coexist with atrial fibrillation, and once you convert one, the other shows up. I had a patient who came in with what looked like controlled AF, we started anticoagulating and rate controlling, then converted him and the flutter was already there waiting. Make sure you look for it. Ventricular tachycardia is where things get serious fast. Three or more consecutive premature ventricular complexes at a rate above 100, wide QRS, usually no relationship to P waves. Sustained VT lasts more than thirty seconds or causes hemodynamic collapse before thirty seconds are up. The distinction between sustained and non-sustained matters for treatment decisions. Non-sustained VT in a stable patient might just need monitoring and finding the underlying cause—ischemia, electrolyte imbalance, cardiomyopathy. Sustained VT in an unstable patient is a code situation. Amiodarone, synchronized cardioversion, or defibrillation depending on whether there's a pulse. I learned this the hard way early in my career. Missed the signs of degener-ation from run of couplets to monomorphic VT on a post-op cardiac surgery floor. By the time I called the code, the patient was already pulseless. The lesson was that occasional PVCs in the right context are a warning light, not a benign finding. Bradycardias are their own category of headache. Sinus bradycardia below 60 isn't automatically pathological—athletes have low resting rates, and so do a lot of perfectly healthy people. Symptomatic bradycardia is what you treat: dizziness, syncope, hypotension, heart failure. The ACLS bradycardia algorithm starts with atropine 0.5 mg IV every three to five minutes, maximum 3 mg, then moves to transcutaneous pacing or dopamine/epinephrine infusions if atropine doesn't work. I've seen atropine fail in heart transplant patients because the denervated heart doesn't have vagal tone to block. That's a special population where pacing is first-line, not second-line.
Heart blocks are another area where pattern recognition saves time. First-degree AV block is just a prolonged PR interval above 0.20 seconds. Usually benign, usually no treatment needed unless it's worsening. Second-degree Mobitz type I, also called Wenckebach, shows progressively lengthening PR intervals until a beat drops. It's typically benign and often seen in athletes or during sleep. Mobitz type II is different—constant PR intervals with random dropped beats, usually indicating disease in the His-Purkinje system. That one needs a pacemaker, often urgently. Third-degree or complete heart block means no atrial impulses conduct to the ventricles. The atria and ventricles beat independently. Symptomatic complete heart block is an emergency. Atropine rarely works here because the block is usually below the AV node. You're looking at transcutaneous pacing immediately and an permanent pacemaker as soon as you can get one placed. Premature ventricular contractions are extra beats that originate in the ventricles instead of the SA node. They show up as wide, bizarre QRS complexes without a preceding P wave. Occasional PVCs are extremely common and usually harmless. Bigeminy—every other beat is a PVC—can feel terrible for a patient even though it's often not dangerous. Couplets and triplets are two or three PVCs in a row, and those are the ones that make attendants sit up and take notice because they can degenerate into VT. Multifocal PVCs coming from different sites in the ventricles suggest more widespread irritability and you should be thinking about electrolyte disturbances, ischemia, or structural heart disease. Supraventricular tachycardias cover a group of rhythms that all share a narrow QRS complex and a rapid rate above 100. AV nodal reentrant tachycardia and AV reentrant tachycardia through an accessory pathway are the two most common mechanisms. Both typically present with a sudden onset and offset—you'll hear patients describe it as the heart suddenly clicking into a fast gear and then just as suddenly snapping back. Vagal maneuvers can sometimes break these, though the evidence for their effectiveness is mixed. Adenosine is the pharmacologic go-to, and it works by temporarily blocking the AV node. If the tachycardia depends on the AV node, which most SVTs do, adenosine will terminate it. The trick is giving it fast enough—push it over ten seconds, not thirty. I've watched residents waste the dose chasing the IV line across the room while the syringe sits half-empty in the hub.
Get the Full Details

Junctional rhythms originate from the AV node when the SA node fails or is suppressed. The rate is usually between 40 and 60, the QRS is narrow, and P waves may be absent, inverted, or buried in the QRS. They're often a escape rhythm, meaning the lower conduction system is keeping the heart beating because the upper system isn't doing its job. An escape rhythm is a safety mechanism, not the primary problem. The real question is why the SA node stopped leading. Hyperkalemia, increased intracranial pressure, drug toxicity, sick sinus syndrome—all the usual suspects. Treating the escape rhythm itself usually isn't necessary unless it's too slow, in which case you're back to atropine and pacing territory.
Reading the Strip Matters More Than Memorizing the List
The real skill here is systematic analysis. I always go through the same steps: rate, rhythm, P waves, PR interval, QRS duration, axis, and then any abnormalities. Doing it in order means you don't miss things because you got excited by a fast rate and forgot to check whether P waves were actually present. A regular narrow-complex tachycardia at 180 could be sinus tach, atrial flutter with 2:1 block, or AVNRT, and the treatment differs for each. Sinus tach needs you to find and treat the cause—pain, fever, hypovolemia, anxiety. The others might need vagal maneuvers or adenosine. Misidentifying sinus tach as SVT and giving adenosine won't kill anyone usually, but it's unnecessary and delays finding what's actually wrong. One thing that trips people up is that some rhythms look similar on a quick glance but have very different implications. Atrial fibrillation with rapid ventricular response and atrial flutter with 2:1 block can look nearly identical. The difference is whether you can spot those flutter waves, and that requires actually looking at the baseline between QRS complexes instead of just counting R-R intervals. I teach students to put the strip on pause and go through lead II systematically. If you rush, you'll miss it every time. Another counter-intuitive point: not every wide-complex tachycardia is VT. Some supraventricular rhythms with aberrant conduction can look wide and ugly. The general rule in emergency medicine is to treat wide-complex tachycardia as VT until proven otherwise because missing VT is far more dangerous than mislabeling a benign tachycardia. But the reverse is also true—if you cardiovert every wide-complex tachycardia, you're exposing people who might have responded to something simpler to unnecessary sedation and procedures. The Brugada criteria help, but they're not perfect, and in practice you're often making a call with incomplete information.
Electrolyte abnormalities are the silent amplifier in all of this. Hypokalemia makes everything irritable—PVCs, atrial tachycardia, even bidirectional VT in the severeDigoxin toxicity version. Hyperkalemia can mimic heart block, cause sine-wave patterns that look like they're about to degenerate into VF, or just flatten P waves until you can't find a rhythm to identify at all. If you're struggling to make sense of an ECG, check the potassium and magnesium before you spend twenty minutes arguing with a colleague about whether those are delta waves or artifact. The limitations of rhythm classification itself are worth acknowledging. These categories are useful teaching tools and clinical shortcuts, but real patients don't always fit neatly into them. Some arrhythmias are transitional—fibrillation turning into flutter, sinus tach accelerating into SVT, VT degenerating into VF. Some are mixed, like atrial fibrillation with an accelerated junctional rhythm happening at the same time. And some are just artifacts that look alarming but mean nothing, which is the worst kind because you can't prove it until you grab a manual blood pressure and confirm the patient actually has a pulse matching that chaotic-looking strip. If you're studying this for an exam, focus on pattern recognition through repeated strip reading rather than rote memorization. Do hundreds of strips. Get your eye trained to see the shape of the P wave, the consistency of the PR interval, the width of the QRS. When you've seen enough, you'll start recognizing rhythms the way you recognize faces—without consciously going through a checklist every time. The checklist still matters when you're unsure, but fluency comes from volume, not from any clever shortcut.