
The Two Buckets You Need to Know
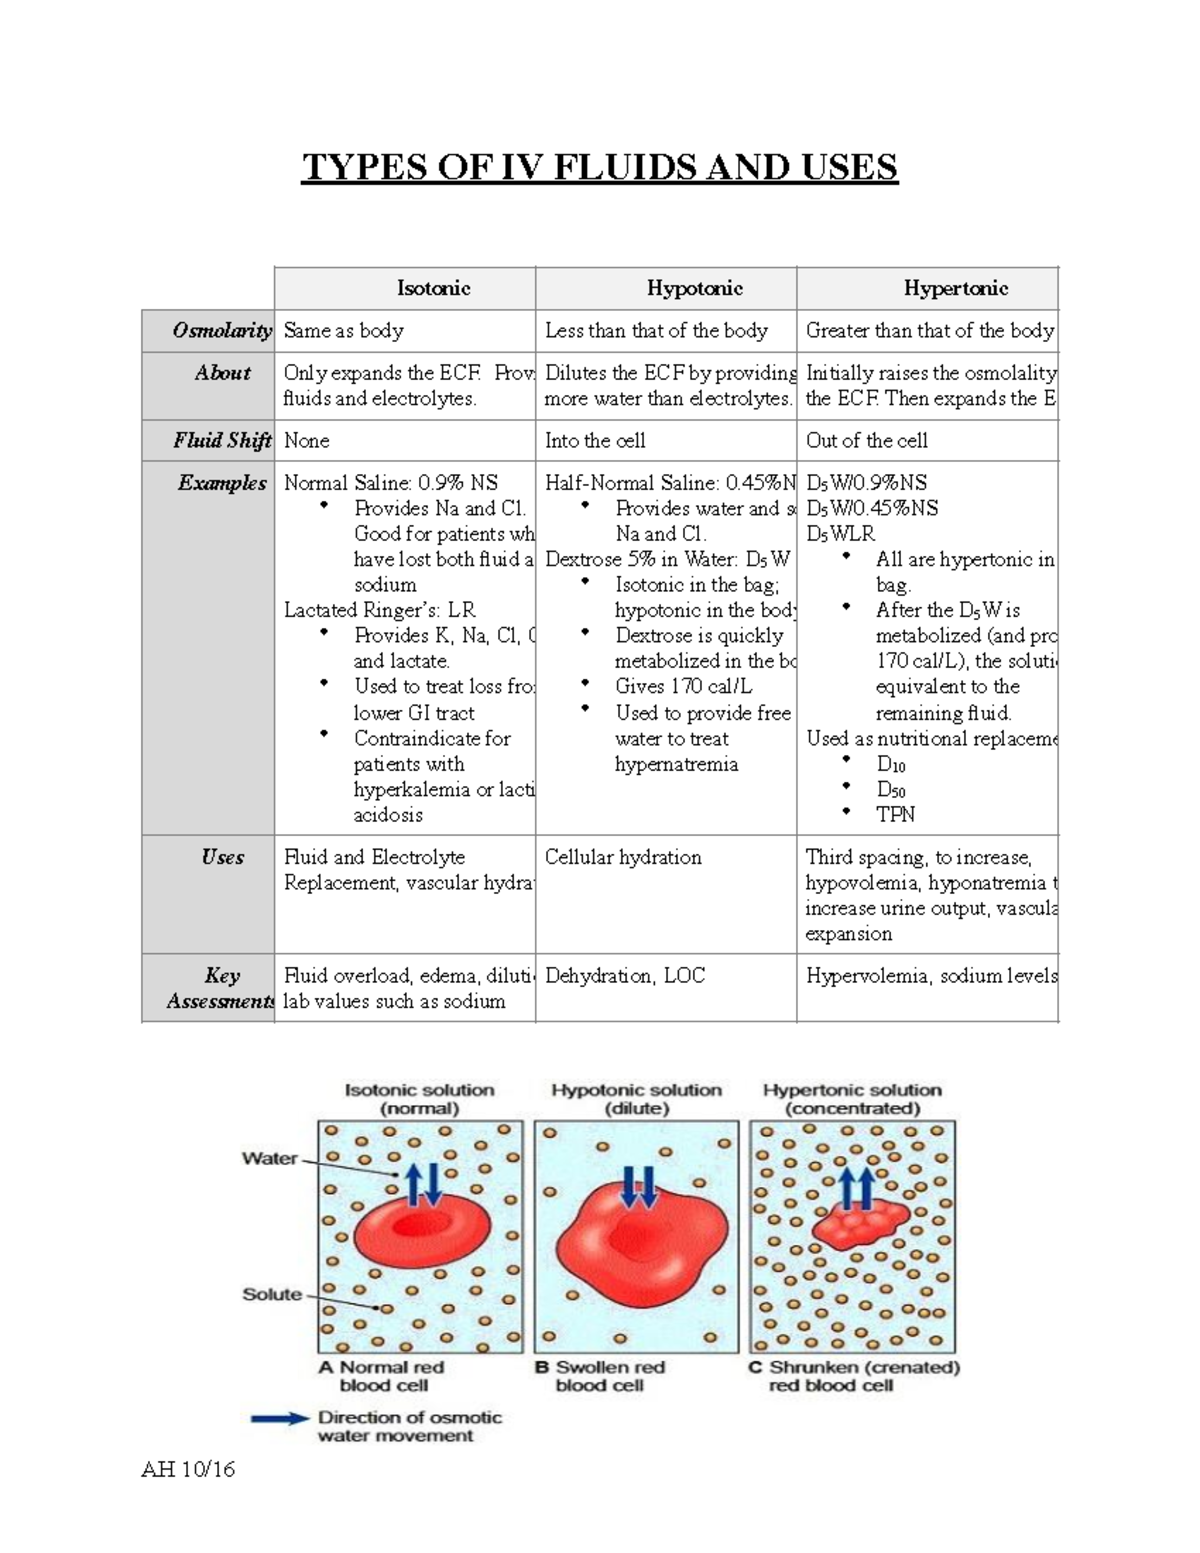
Intravenous fluids aren't complicated once you stop treating them like a textbook diagram and start thinking about what they actually do in a patient's vessels. There are really only two functional categories: crystalloids and colloids. Everything else is a sub-variant or a formulation choice. Crystalloids contain dissolved salts and sometimes sugar. They flow through needle and catheter easily, they're cheap, and most of what nurses hang in a hospital room falls into this group. Colloids contain larger molecules — starches, gelatins, albumin — and they sit in the bloodstream longer because those big particles can't easily slip through capillary walls.
Common Types Of Intravenous Fluids in Practice
Let me walk through what I actually see on the floor, not what a chart says. Normal saline — 0.9% sodium chloride — is the workhorse. It's isotonic, meaning the osmolarity roughly matches blood plasma. When you need volume replacement and don't have a strong reason to do anything fancy, you reach for NS. The problem most people don't mention upfront is that running large volumes of it will push a patient toward a hyperchloremic metabolic acidosis. The chloride load is real. I had a trauma case a few years back where a patient got over six liters of NS in the first shift and their bicarbonate dropped to eighteen. We switched to a balanced crystalloid and stabilized. That's not a theory — it's just chemistry in the blood. Lactated Ringer's is the other big one. It has sodium, potassium, calcium, chloride, and lactate. The lactate gets converted to bicarbonate in the liver, which is why it's called a "balanced" crystalloid. It's closer to actual plasma composition than saline is. The catch is the calcium — if a patient is getting blood products through the same line, the calcium in LR can interact with the citrate in the blood product and cause microclots in the tubing. I learned that the hard way watching the line turn opaque. Never run LR and blood through the same IV without a separate line or a Y-site with proper flushing.
Half-normal saline — 0.45% NaCl — is hypotonic. It shifts water into cells. Useful when you're dealing with hypernatremia or diabetic ketoacidosis after the initial resuscitation phase, but dangerous if you hang it on a patient with raised intracranial pressure. Water moving into brain cells is not a good time. D5W — five percent dextrose in water — sounds like it should expand volume. It doesn't. Once the dextrose gets metabolized, you're left with free water, which crosses cell membranes freely. It's essentially a way to deliver water, not volume. I've seen residents start D5W thinking they're giving fluid resuscitation. They're not. The volume effect lasts about fifteen minutes before the water distributes across total body water. Ringer's acetate and Ringer's gluconate are the European cousins of LR. Same idea — balanced electrolyte solution with a buffer precursor — just using acetate or gluconate instead of lactate. Useful in patients with liver dysfunction where lactate clearance is impaired. I worked a shift where our LR supply ran out during a busy Saturday and we had to use what we had. Knowing the alternatives kept us from panicking.
Get the Full Details
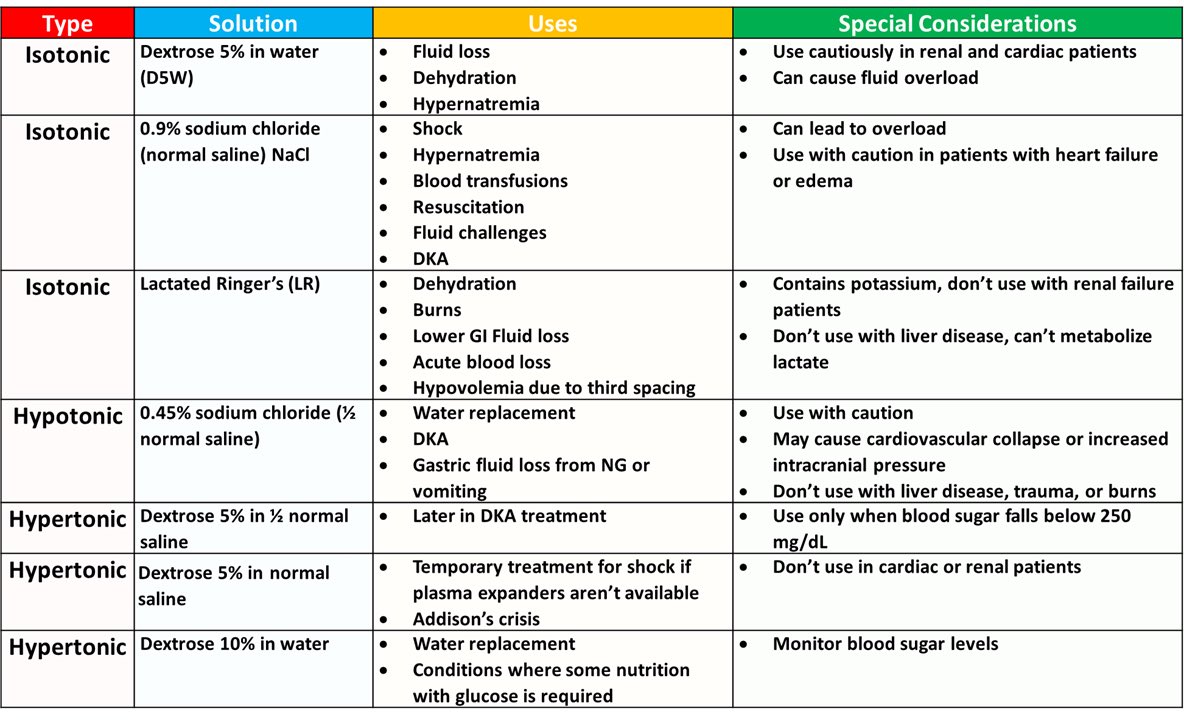
Plasmalyte is another balanced crystalloid option. It uses acetate and gluconate as buffers, no calcium, which means it plays nicer with blood transfusions than LR does. Slightly more expensive than saline but worth it when you're running big volumes. Now colloids. Albumin 5% and 25% — the percentage tells you concentration, not volume. 5% is roughly isotonic. 25% is highly hypertonic and pulls fluid into the vessels aggressively. I've seen 25% albumin drop a patient's blood pressure because it pulled so much fluid from the interstitial space so fast that the heart couldn't keep up with the preload shift. You hang it slowly and watch the patient. Heta starch solutions — hespan, hydroxyethyl starch — were the go-to colloid for years. Then the evidence came in showing increased risk of acute kidney injury and mortality in critically ill patients. Many hospitals stopped using them entirely. If you encounter an old protocol still ordering HES, flag it. The 2012 SAFE study and subsequent meta-analyses changed practice significantly.
Gelatins — succinylated gelatin, urea cross-linked gelatin — are cheaper alternatives to starches with a different side effect profile. They carry a risk of anaphylactoid reactions at a higher rate than starches, around two to three percent in some European studies. Not zero, not massive, but something to discuss with anesthesia if you're doing major surgery.
How to Choose Without Overthinking It
Start with the clinical question: does the patient need volume expansion or just hydration? Volume expansion means you want the fluid to stay in the intravascular space. Crystalloids distribute quickly — only about a quarter to a third stays in the vessels after thirty minutes. Colloids stay longer. But "longer" doesn't mean "better outcomes." The CRISTAL meta-analysis published in The Lancet found no mortality difference between crystalloid and colloid resuscitation across multiple patient populations. The choice should be driven by cost, availability, and specific contraindications, not by a myth that colloids save more lives. Hydration means you're replacing insensible losses or treating a free water deficit. In that case, hypotonic fluids or D5W make sense. But never use hypotonic fluids for resuscitation. They won't stay in the vessels and they'll swell cells.
Here's the practical decision tree I use: Trauma or hemorrhagic shock — balanced crystalloid (LR, Plasmalyte, or acetate-based). Avoid massive NS. Start early with blood if there's active bleeding. Dehydration without shock — D5W or half-normal saline depending on sodium status. Check the lab before you hang anything.
Sepsis resuscitation — balanced crystalloid, three zero milliliters per kilogram in the first hour per the Surviving Sepsis Campaign. I've seen people argue about saline versus balanced solutions here. The BASE trial showed a hint of benefit with balanced solutions in ICU patients. It's small but real. Use what's available and don't waste time debating it at two AM. Maintenance fluids — this is where most mistakes happen. The old "two-thirds maintenance, one-third deficit" approach from the 1950s is still taught in some places and it's wrong for most adult patients. Look at the patient's sodium, look at their urine output, look at what they're actually losing. The 4-2-1 rule for pediatric maintenance is a starting point, not a prescription. I had a post-op patient who developed hyponatremia because someone hung a standard maintenance bag without checking the context. The sodium was one twenty-eight. We stopped the fluid, gave saline, and monitored. It corrected over twelve hours. Don't set and forget. Burn patients — the Parkland formula uses LR, four milliliters per kilogram per percent total body surface area, half in the first eight hours. But that formula is a guide, not a law. You titrate to urine output — point five milliliters per kilogram per hour in adults. I've seen burns where following the formula exactly led to compartment syndrome from over-resuscitation. The "fluid creep" problem is real. Watch the extremities.
What Nobody Warns You About
Temperature matters. Cold IV fluid causes vasoconstriction and discomfort, and in vulnerable patients it can trigger arrhythmias. I keep a fluid warmer in the trauma bay now. It costs about two hundred dollars and prevents a lot of headaches. Warm fluids to thirty-seven degrees before hanging on a patient who's losing volume or is hypothermic. Pressure bags — you can bag most IV fluids up to three hundred millimeters of mercury for rapid infusion. Normal syringes and gravity bags won't move fast enough in an emergency. I once tried to push fluid through a standard IV setup during a code and realized too late that a pressure bag would have cut the time in half. Keep one on the crash cart. Drug compatibility — some fluids interact with medications. Phosphate solutions precipitate in LR because of the calcium. I've seen cloudy lines and stopped infusions mid-stream. If you're mixing anything into an IV line, check the compatibility before you commit. The official injection references are better than memory here.

Rhubarb root contamination in older gelatin products — this is niche but relevant if you're working with imported or older stock in certain regions. Gelatin derivatives can carry allergenic contaminants. It's why some countries have different approval standards for gelatin-based colloids.
Special Populations Change the Math
Renal failure — you can't dump fluid the way you would in a healthy patient. The kidneys won't excrete the excess. I've managed patients on continuous renal replacement therapy where fluid balance was tracked milliliter by milliliter over seventy-two hours. The principle is the same: balanced crystalloids are still preferred, but the rate changes completely. Consult nephrology early. Don't guess. Heart failure — the same fluids that resuscitate a normal patient will flood a failing heart. I once calculated that a standard one-liter bag of LR represented about twelve percent of a particular patient's total blood volume. That matters when the ejection fraction is twenty-five percent. Restrict to two fifty milliliters boluses and reassess. Serial lung exams and bedside ultrasound beat any formula. Liver disease — avoid lactate-containing fluids if the liver is severely compromised. The lactate won't convert to bicarbonate efficiently. Use Plasmalyte or acetate-based solutions instead. I had a cirrhotic patient whose lactate stayed elevated despite adequate perfusion because the liver couldn't clear it. It looked like ongoing shock on paper. The numbers lied. Don't let a lab value blind you to the clinical picture.
Pediatrics — children are not small adults. Their surface area to mass ratio means they lose heat and fluid faster. Their glycogen stores deplete quickly, which is why D5-containing fluids matter more in peds than in adults. A neonate getting plain saline for maintenance is a recipe for hypoglycemia. Check the age, check the weight, check the glucose.

Reading the Response Is the Real Skill
Fluid management isn't about picking the right bag. It's about knowing whether the patient is responding and adjusting accordingly. The tools are simple: blood pressure, heart rate, urine output, mental status, lactate trends, and if you have access to it, passive leg raise with stroke volume monitoring or inferior vena cava ultrasound. Static numbers like central venous pressure are notoriously unreliable for predicting fluid responsiveness. I've seen patients with a CVP of ten who flooded and patients with a CVP of four who still needed volume. The number alone doesn't tell you the story. Dynamic measurements do. A rise in stroke volume after a small bolus means the patient is on the steep part of the Frank-Starling curve and will benefit from more fluid. No change means you've probably reached the plateau and more fluid won't help — it might hurt. Beware of third spacing. In sepsis, trauma, or major surgery, capillary leak moves fluid out of the vessels and into the interstitium. The patient may look volume depleted even though their total body water is high. I once managed a patient with severe pancreatitis who needed aggressive resuscitation despite obvious peripheral edema. The edema was the third spacing talking. Don't let surface signs fool you into under-resuscitating.
Over-resuscitation has its own morbidity. Abdominal compartment syndrome, pulmonary edema, wound edema that impairs healing — these are real complications I've seen in surgical patients who got "just one more bag." The FLOTATION trial and other studies have documented increased complications with aggressive fluid strategies in major surgery. Balanced is better. Liberal is not always better. The bottom line is simpler than the literature makes it sound. Match the fluid to the patient's physiology, not to a protocol you memorized. Use balanced crystalloids for resuscitation. Respect the chloride load of normal saline. Know when a colloid makes sense and when it doesn't. Watch the patient, not the bag. And when in doubt, ask a senior. I still do.

