Sampling Methods That Actually Work in Practice
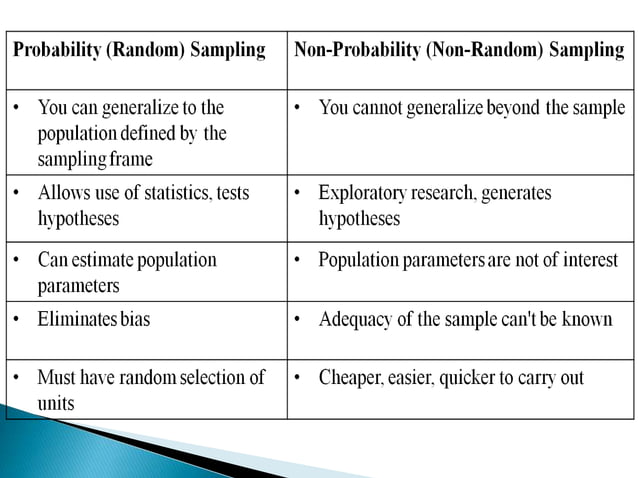
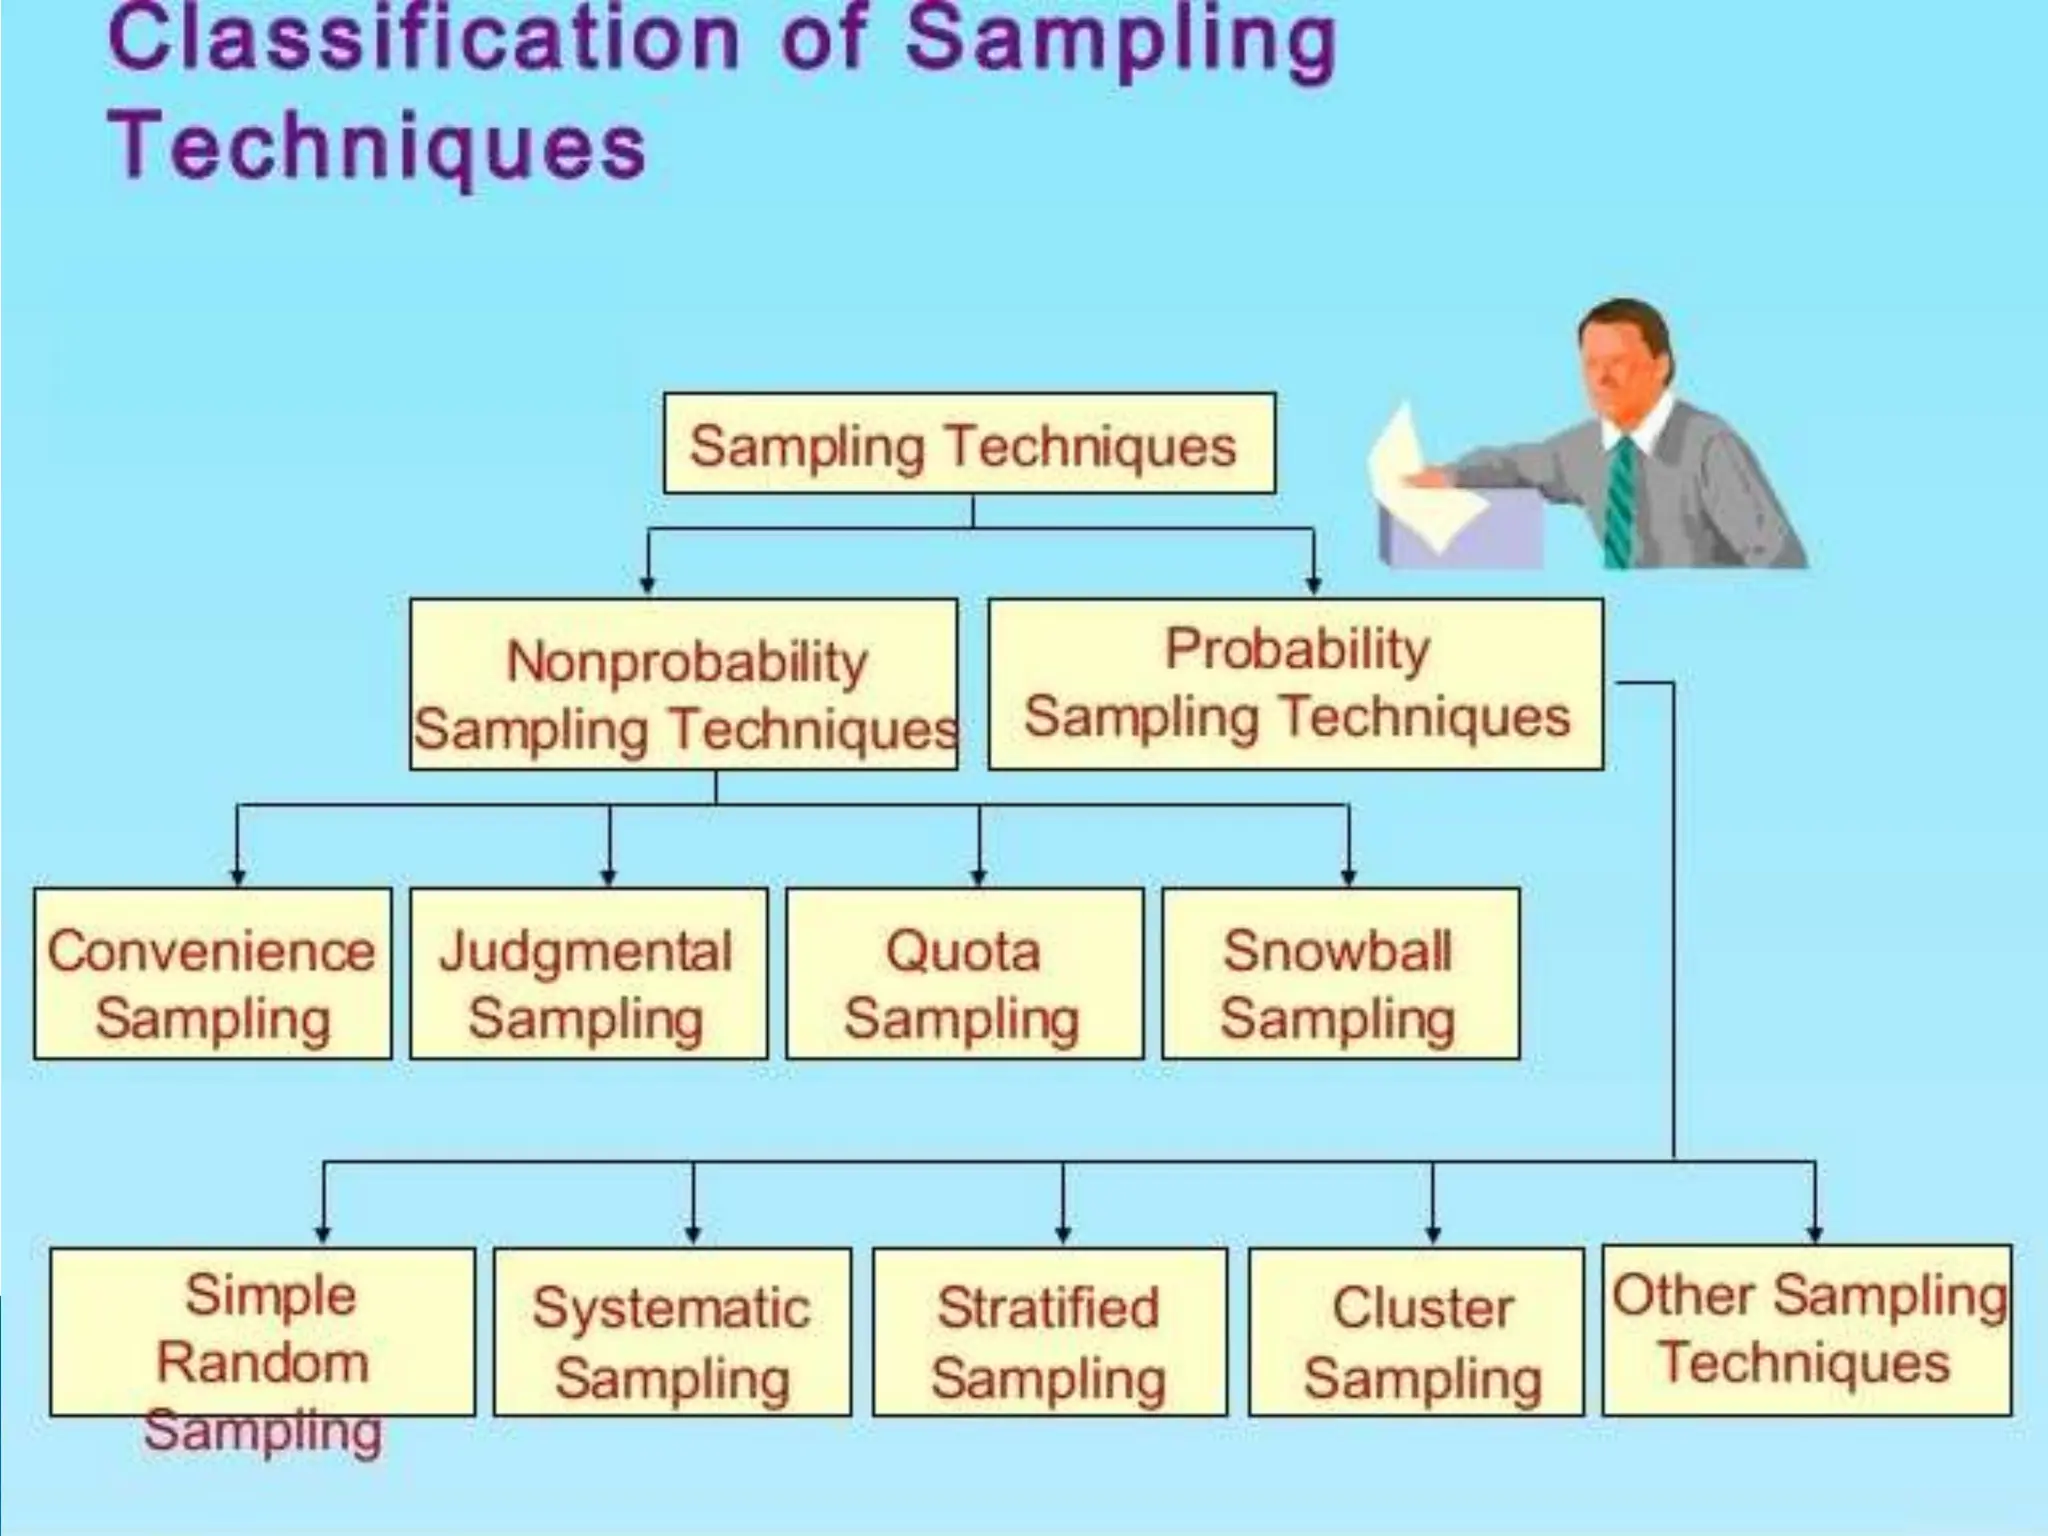
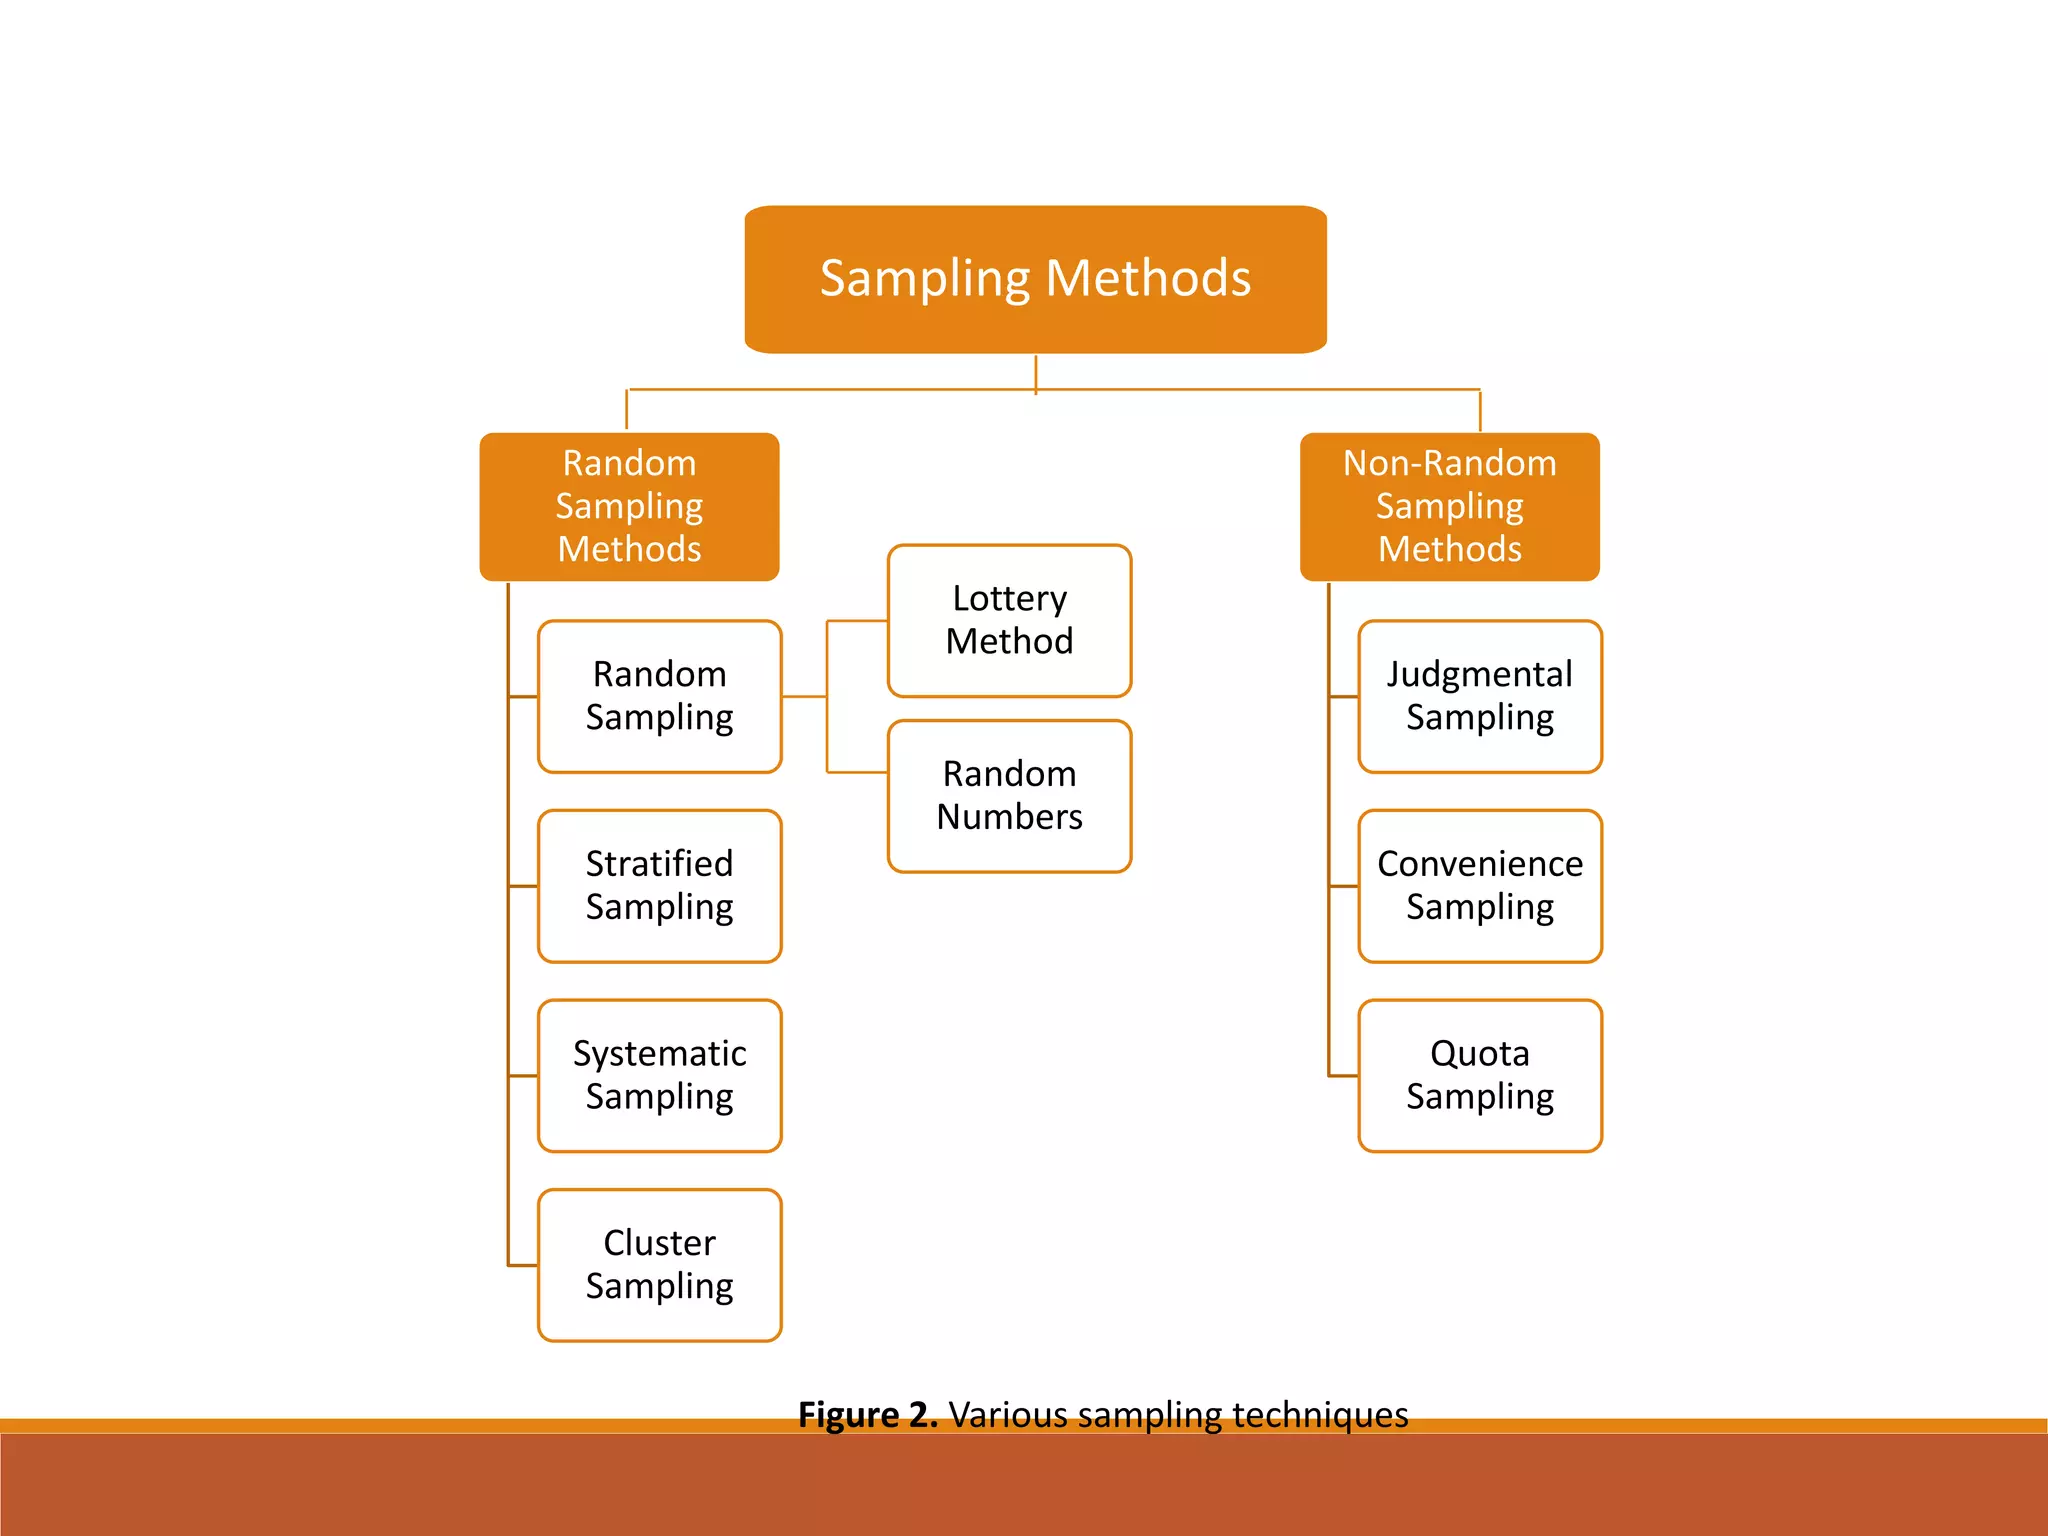
I spent about six months sorting through the mess that is a multi-center clinical trial dataset last year. The site coordinators had no idea what probability sampling was. We ended up with 400 patients where half were convenience picks from the waiting room and the other half were referrals from colleagues who wanted to be authors. Standard error estimates were garbage. That experience changed how I think about every study design going forward. Probability sampling means every member of the target population has a known, nonzero chance of being selected. Nonprobability sampling breaks that rule. In biostatistics, this distinction is not academic. It determines whether your confidence intervals mean anything or whether they are just decorative numbers. Simple random sampling is the baseline most people learn first. You assign each individual a number, generate random values, and pull the sample. It is clean in theory. In practice, you need a complete sampling frame, which is rarely the case in hospital-based studies where patient lists are fragmented across departments. I once tried to use simple random sampling for a diabetes prevalence study and realized halfway through that the clinic database only covered patients who returned for follow-up. The sampling frame was biased by visit frequency.
Systematic Sampling and Its Hidden Assumptions
Systematic sampling picks every kth individual after a random start. It is computationally simple and often more practical than pure random sampling. The catch is periodicity. If the list has a repeating pattern that matches your interval, your sample collapses into something nonrepresentative. I ran into this when sampling lab results from a hospital information system. The patient ID sequence had a subtle pattern tied to department assignments that aligned with my sampling interval of 50. The result was a sample heavily skewed toward one clinical unit. I caught it by plotting the selected IDs against department codes before running any analysis. A quick check like that saves hours of wasted modeling.
Stratified Sampling for Small Populations
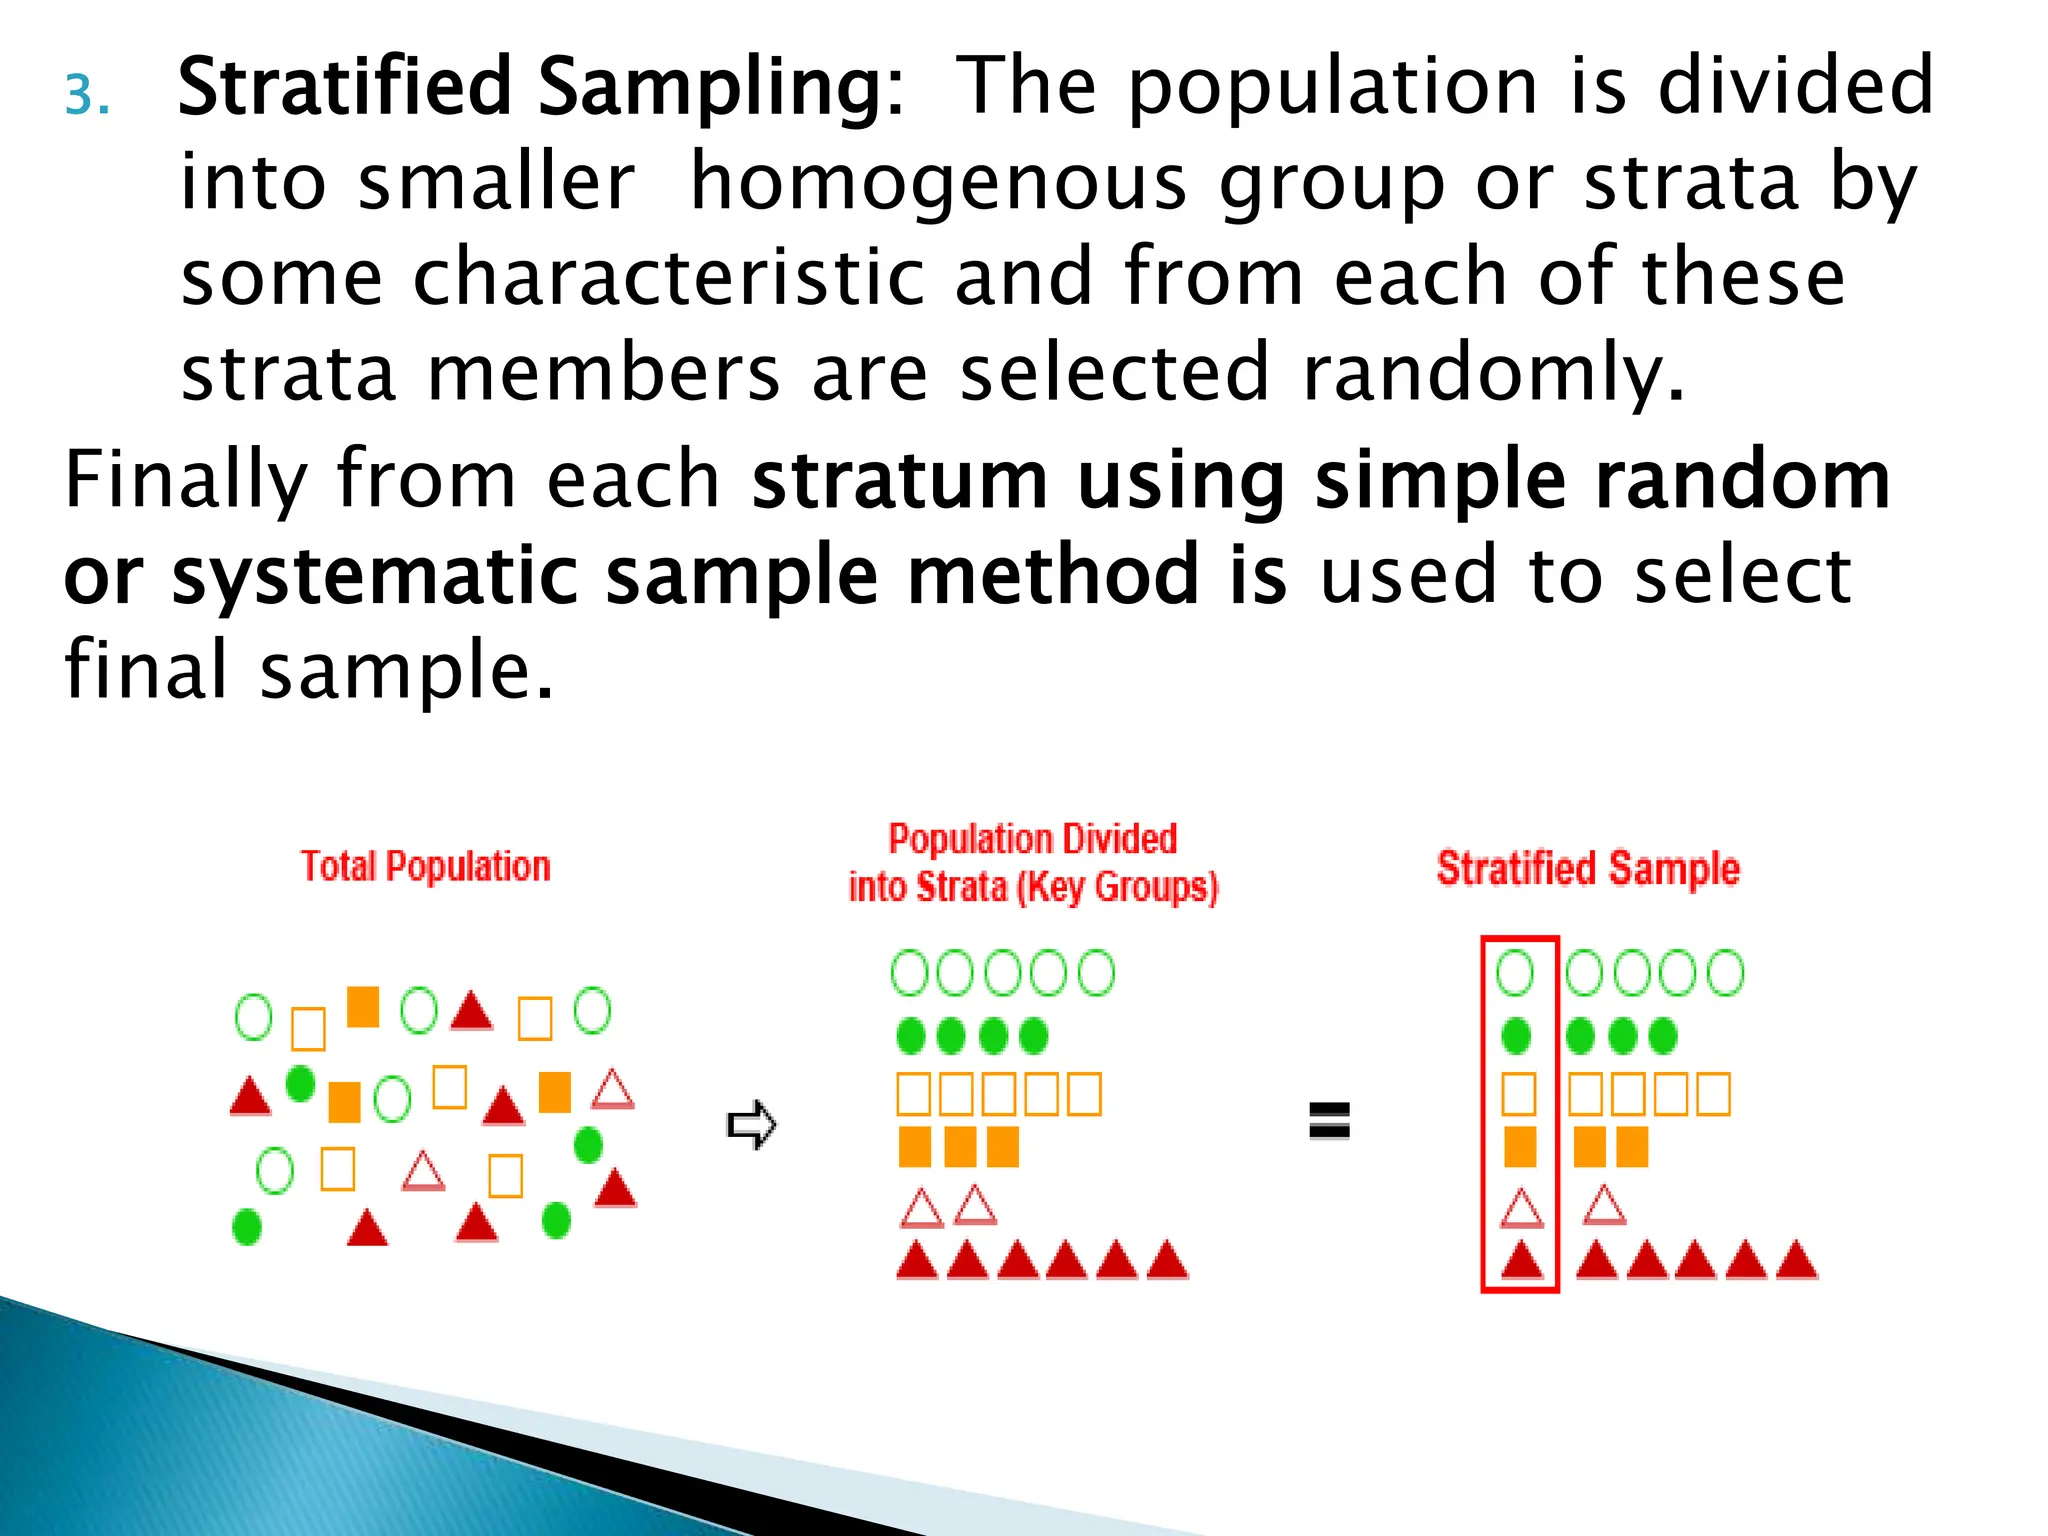
Stratified sampling divides the population into homogeneous subgroups, then samples within each stratum. It reduces variance compared to simple random sampling when the stratification variable is correlated with your outcome. In biostatistics, age groups, sex, and disease stage are common stratification variables. The tricky part is proportional versus disproportional allocation. Proportional allocation keeps the same fraction in each stratum. Disproportional allocation oversamples smaller but important groups. I used disproportional stratified sampling for a study on rare adverse drug reactions. The overall population was 50,000 patients on a specific medication, but only about 120 experienced the reaction. By stratifying by dosage level and oversampling the highest dose group, I increased the number of events from roughly 15 to 47 in my sample. The tradeoff is that you need post-stratification weighting to recover population-level estimates. Modern statistical software handles this, but you must specify the weights explicitly or your standard errors will be wrong.
Get the Full Details
Cluster Sampling When Your Population Is Spread Out
Cluster sampling selects groups rather than individuals. You might sample villages, hospitals, or clinics, then survey everyone within selected clusters. This is common in epidemiology where travel costs make individual sampling prohibitive. The design effect is the problem. Clustered samples have less information per subject because individuals within the same cluster share environmental and genetic factors. The intracluster correlation coefficient determines how much your effective sample size shrinks. If the ICC is 0.05 and your cluster size is 30, the design effect is about 2.4. You need more than double the subjects compared to simple random sampling to achieve the same precision. I learned this the hard way during a vaccination coverage survey in rural districts. The initial sample size calculation ignored clustering. We enrolled 600 households across 30 villages and found our margin of error was twice what we planned. The fix was straightforward: rerun the power analysis with a design effect of 1.5, which is conservative for rural populations with moderate heterogeneity. We added three more villages and completed fieldwork in five days instead of redesigning the whole protocol.
Multistage Sampling for Large-Scale Studies
Multistage sampling combines several sampling methods in sequence. You might select provinces first, then districts, then health centers, then households, then individuals. Each stage introduces its own sampling error, and the variances compound. The advantage is logistical feasibility. You cannot easily maintain a complete list of all hospitals in a country. But you can get a list of regions from the health ministry, sample regions, then get lists within sampled regions. This is the approach used in most national health surveys, including the Demographic and Health Surveys program that operates across dozens of low- and middle-income countries. The statistical burden is real. Variance estimation requires specialized techniques like Taylor linearization or replicate weights. Standard software defaults assume simple random sampling. If you feed multistage data into SPSS without adjusting the survey design parameters, your p-values will be too small and your conclusions too confident. I have seen this error repeated in published papers multiple times.
Nonprobability Methods: Convenience and Quota Sampling
Convenience sampling selects whoever is available. Quota sampling divides the population into categories and fills each category until a preset number is reached, without random selection within categories. These methods are fast and cheap, which makes them attractive when funding is tight or timelines are aggressive. The problem is selection bias. Convenience samples systematically overrepresent certain types of individuals. Hospital-based controls in case-control studies are a classic example. Patients seeking care are sicker, more health-conscious, or have different socioeconomic profiles than the general population. Using them as comparison groups can distort odds ratios by 20 to 40 percent depending on the exposure. I worked on a study comparing dietary habits between patients with inflammatory bowel disease and healthy controls recruited from a nearby university. The controls were mostly students under 25. The cases ranged from 18 to 65. Age and education confounded every comparison. We ended up restricting the control group to match the age range of cases, but that eliminated half the available controls and reduced statistical power. A properly sampled control group from the same catchment area would have been better, but the ethics review board required recruiting from the same institution for practical reasons.

Purposive Sampling for Qualitative Work
Purposive sampling selects participants based on specific characteristics relevant to the research question. It is standard in qualitative biostatistics and mixed-methods studies where the goal is depth rather than generalizability. Patient experience interviews, focus groups on treatment adherence, and provider perception studies all use purposive sampling regularly. The key is explicit justification. You must state why each participant meets the inclusion criteria and how the sample covers the variation in the population. Vague descriptions like "selected based on relevance" are insufficient for peer review. Reviewers expect to see the sampling matrix, the recruitment pathway, and the point at which saturation was reached.
Respondent-Driven Sampling for Hidden Populations
Respondent-driven sampling uses existing social networks to recruit hard-to-reach populations. Participants recruit peers from their own networks, and incentives are structured so that recruitment quality matters as much as quantity. This method is widely used in HIV research among key populations where registry-based sampling is impossible. The analysis requires specialized estimators that account for network size and recruitment weight. Simple proportions calculated from RDS data are biased. The software packages like Radial or the R package respondentdriven handle this, but the assumptions are strong. Homophily, where people tend to associate with similar others, can distort estimates if the population is highly segregated. I encountered this when studying substance use patterns in a mobile worker population. The network was split into distinct subgroups with minimal cross-group contact. The RDS estimator assumed sufficient mixing. The results for the minority subgroup were unreliable despite a large final sample size of over 400 participants.
Adaptive Sampling for Rare Events
Adaptive sampling changes the selection process based on observations from earlier samples. If you find cases with the outcome of interest, you intensify sampling in that area or among those contacts. This is useful when the outcome prevalence is below 1 percent and conventional sampling would require thousands of subjects to detect a handful of events. Threshold adaptive cluster sampling is the most common variant. You define a threshold, sample initially, then expand to neighbors of units exceeding the threshold. The variance estimation is complex because the expansion creates dependency between sampled units. The Goodman-Kruskal estimator or bootstrap methods are typical choices. I used adaptive sampling for a rare toxicity surveillance program in oncology. The baseline sample of 2,000 patients across five centers yielded only three cases of the adverse event. By triggering expanded sampling around each case, we identified 12 additional cases from neighboring clinics that would otherwise have been missed. The total enrollment was 2,600 instead of 8,000, which saved roughly eight weeks of recruitment time. The statistical analysis used conditional likelihood methods appropriate for adaptive designs.
Practical Decision Rules for Study Design
The choice of sampling method depends on the sampling frame availability, population heterogeneity, outcome prevalence, budget, and timeline. There is no universal best method. What matters is matching the method to the constraints and acknowledging the limitations in the paper. I use a simple checklist before committing to a design. First, can I obtain a complete list of all population members? If yes, simple random or systematic sampling is viable. If no, I consider cluster or multistage approaches. Second, is the outcome rare? If prevalence is below 2 percent, adaptive or oversampling strategies may be necessary. Third, what is the budget per subject? Cluster sampling reduces per-subject cost but increases total sample size requirements. Fourth, will the results need to generalize beyond the study population? If yes, probability sampling is essential. If the goal is exploratory or qualitative, nonprobability methods may suffice.
Common Mistakes That Undermine Published Studies
One mistake is reporting confidence intervals calculated under simple random sampling assumptions when the data come from a complex survey design. The intervals are too narrow and give false precision. Another mistake is ignoring nonresponse adjustment. When 30 percent of sampled individuals do not participate, the effective sample is smaller and the remaining participants may differ systematically from nonparticipants. Weighting for response propensity can help, but it requires auxiliary data on the full sample. A third mistake is using quota sampling and calling it representative. Quota sampling fills demographic categories, but within each category the selection is nonrandom. The resulting sample may match population margins on observed variables while being biased on unobserved variables. I have seen this in nutrition studies where quota sampling produced age and sex distributions identical to census data, but the dietary recall results were skewed toward health-conscious participants because recruitment happened through wellness clinics.
Software and Implementation Notes
R provides the survey package for complex sample analysis. The svydesign function handles stratified, clustered, and multistage designs. Specify the strata, cluster ID, sampling weights, and pseudo-replication degrees of freedom. Python users can use the statsmodels survey module or the pingouin package for some designs. Stata has the svy prefix for all standard complex survey analyses. The critical step is building the correct weight variable. Weight equals the inverse of the selection probability at each stage. For multistage sampling, multiply the stage-specific probabilities together. Adjust for nonresponse by inflating weights for respondents in each nonresponse class. Adjust for post-stratification by aligning marginal totals with known population parameters. Each adjustment adds variance, so track the inflation factor. Weight inflation above 3.0 usually signals that the sample is poorly representative or that the adjustment model is overfit.
When to Consult a Methodologist Early
Sampling decisions made after data collection begins are costly. I recommend involving a biostatistician during protocol development, not after recruitment is complete. A one-hour conversation about sampling frame construction can prevent months of remedial analysis later. The cost of a methodologist consultation is trivial compared to the cost of a flawed study that cannot be published or that requires a costly replication. The field has moved beyond simple random sampling for most real-world applications. Complex designs are the norm in observational research, clinical trials, and public health surveillance. Understanding the tradeoffs between methods, the assumptions behind each variance estimator, and the practical constraints of data collection is what separates adequate studies from rigorous ones. The details matter more than the label you put on the method in your manuscript.