Understanding Speech Defects in Practice
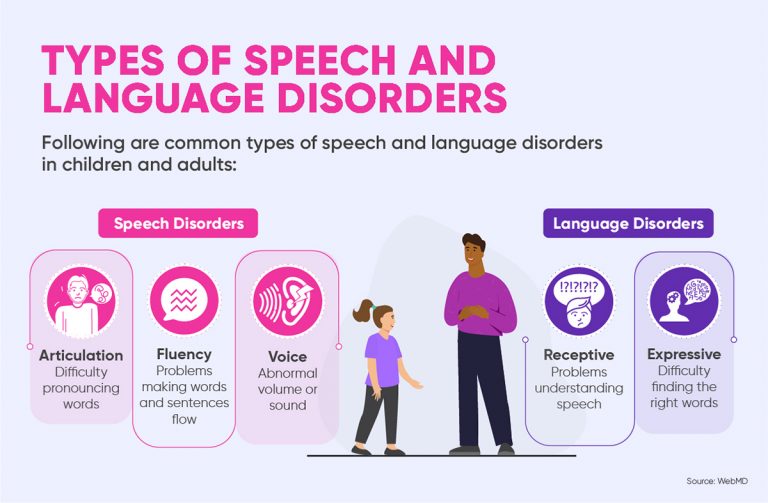
Speech pathologists call them speech sound disorders, but the reality is messier than any textbook category. I've spent years watching clients struggle with things that look identical on paper but require completely different intervention approaches. The taxonomy exists, but applying it accurately takes more than reading definitions. The biggest mistake beginners make is conflating articulation disorders with phonological disorders. They both involve "mispronunciation," but the mechanisms are entirely different and require opposite treatment strategies. An articulation disorder is mechanical - the person can't position their tongue, lips, or jaw to produce a specific sound correctly. A phonological disorder is cognitive-linguistic - the brain has the motor plan, but it's organizing sound patterns wrong. Treating a phonological disorder with articulation drilling is a waste of everyone's time and demoralizes the client. Fluency disorders are more recognizable. Stuttering involves repetitions, prolongations, and blocks. Cluttering is less known but equally disruptive - rapid, irregular speech with excessive disfluencies and poor awareness. I worked with a teenager who was misdiagnosed with ADHD because his cluttering looked like distractibility. He could slow down when prompted, but only consciously, and it drained his working memory so he couldn't follow conversations at normal speed.
Voice disorders fall into two buckets: functional and organic. Functional means the vocal mechanism is healthy but the person is using it poorly - pressing too hard, holding tension in the larynx, speaking at an inappropriate pitch. Organic means there's a structural problem: nodules, polyps, paralysis, reflux damage. A voice disorder assessment without laryngoscopy is basically guesswork. I learned that the hard way early in my career when I spent six weeks doing breath support exercises on a client whose vocal folds had bilateral paralysis. The fix was a referral to an ENT, which led to a ventricle cord procedure that restored his voice within two weeks. Resonance disorders are another category people overlook. Hypernasality - too much air escaping through the nose on oral sounds - is classic with cleft palate, even repaired clefts. Hyponasality - not enough nasality on m, n, ng - can come from nasal obstruction like enlarged adenoids or a deviated septum. Here's the counter-intuitive part: hyponasality often goes undiagnosed because everyone assumes "nose stuffiness" and nobody considers the speech impact. A client of mine had untreated allergies for years. His /m/ and /n/ were essentially indistinguishable to listeners, and he had no idea why people kept asking him to repeat himself. Aphasia and other language-based communication disorders are technically separate from speech disorders, but they co-occur frequently enough that any practitioner needs to recognize them. Broca's aphasia produces effortful, agrammatic speech. Wernicke's aphasia produces fluent but meaningless output. Apraxia of speech is a motor planning disorder where the person knows what they want to say but the brain can't coordinate the sequence of movements. These require different approaches entirely, and mixing them up means you're helping nobody.
The overlap between these categories is where things get complicated. A child might have both a phonological disorder and a mild voice issue from compensating for unclear speech. An adult post-stroke might present with dysarthria and aphasia simultaneously, making it hard to tell which symptoms belong to which condition. That's why comprehensive assessment matters more than quick categorization.
Get the Full Details


