The Actual Work of Speech Therapy
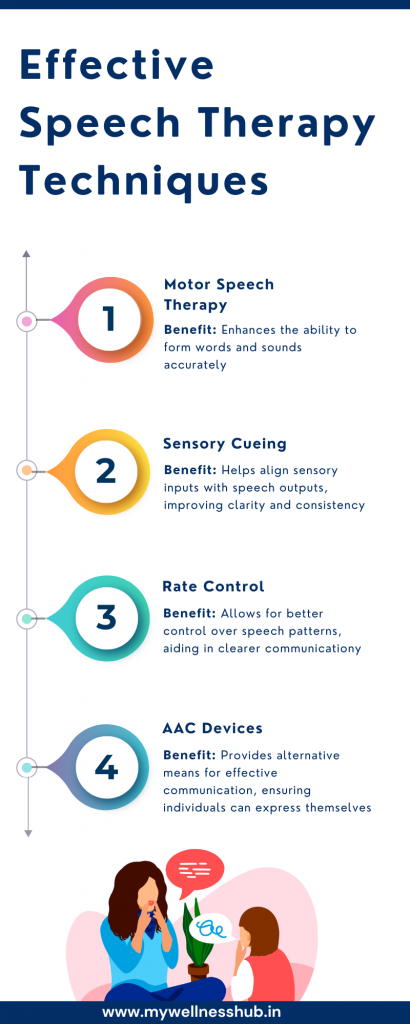
Most people think speech therapy is just sitting across from a kid and making them repeat words. It's not. The real practice involves a mix of motor planning drills, sensory feedback work, cognitive-linguistic tasks, and something that looks almost ridiculous to an outsider but is critical for progress. I've spent years watching therapists try the same old games and wondering why their clients aren't carrying skills over to real life. The gap between clinic and reality is where most treatment plans fall apart. Motor Learning Approaches form the backbone of a lot of what actually works, especially for stuttering, apraxia, and some fluency disorders. The principle here is pretty straightforward: you drill the target enough times that it stops being conscious effort and starts becoming automatic. But the way people usually apply it is wrong. They have a patient say the same word 50 times in isolation. That's not motor learning. Motor learning requires variable practice, distributed reps, and fading external cues. I had a client last year who could produce a target sound perfectly in the clinic but never used it at home. We switched to randomizing the production context — different words, different sentences, different emotional states, different distractions — and within six sessions the carryover actually happened. The trick is making the practice unpredictable.
Types Of Speech Therapy Techniques You'll Actually Use
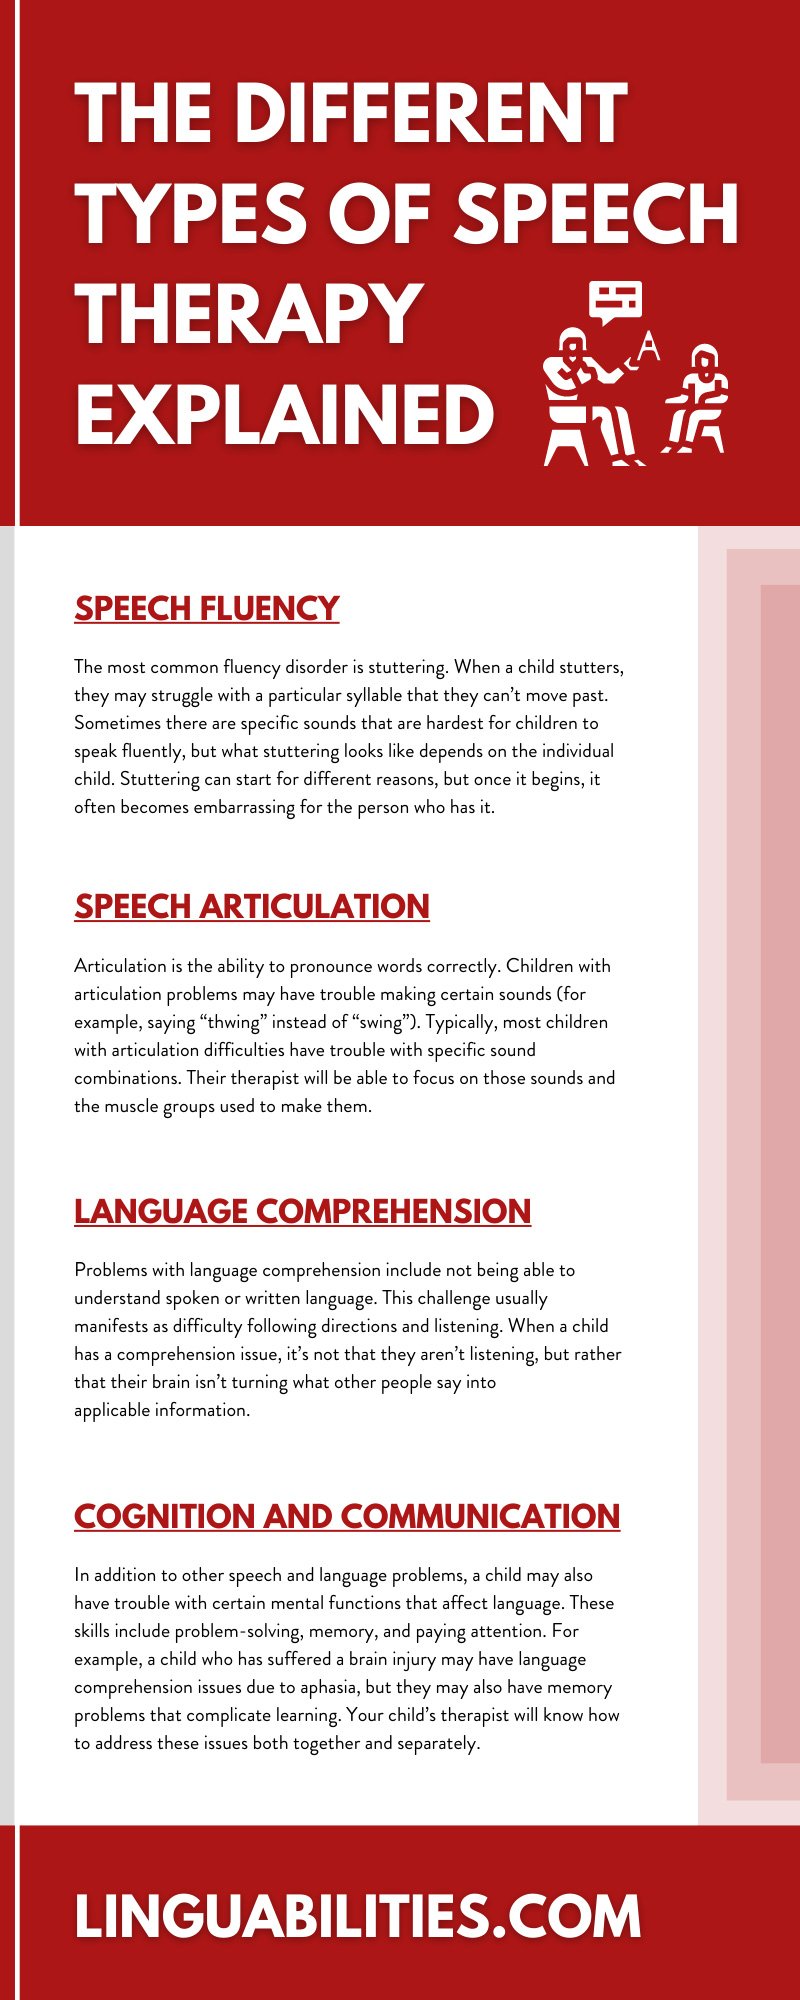
Articulatory-Kinematic Approaches are what you reach for when a person has trouble getting their mouth to a specific position quickly enough. This is big in childhood apraxia of speech and some adult acquired apraxia cases. The therapist works on forming gestures — the movement from one sound to the next — rather than just the end result. Tools like DTTC (Dynamic Temporal and Tactile Cueing) are built on this. You provide touch cues, you time the cues, and then you systematically remove them. The pitfall most people hit is removing the cues too fast. If you strip the tactile input before the motor plan is solid, the patient regresses. I once watched a therapist go from full manual cueing to independent production in one session with a 9-year-old. He lost everything by Friday. Slow fade, or don't fade at all. Resonance and Nasality Work is another category that doesn't get enough attention outside of cleft palate and velopharyngeal dysfunction circles. The technique here involves teaching the patient to feel the difference between oral and nasal resonance. Nose pinching during certain sounds, mirror work, real-time auditory feedback — these are the standard tools. The counter-intuitive part: a lot of people with hypernasality also have weak intraoral pressure because they're not closing off the nasal cavity properly. Strengthening oral airflow and teaching pressure building often matters more than the auditory feedback loop. I've had cases where the resonance improved significantly after we focused purely on strengthening airflow through the mouth, without any direct resonance training at all. Auditory-Verbal and Cued Articulation Methods dominate the pediatric side of things. You present a sound, the child imitates, you give immediate feedback. The feedback has to be precise. "Good try" does nothing. "Your tongue should be back there, not up on your teeth" is the difference between progress and a four-month plateau. I've seen therapists waste months because their corrective feedback was too vague to be useful. One specific case stands out: a teenager with a persistent lisp who'd been in therapy for two years with zero improvement. The previous therapist was using a generic "try again" approach. I switched to providing a visual mirror plus a precise tactile cue on tongue placement, and the lisp was gone in eight sessions. The technique wasn't new. The execution was.
Fluency Shaping and Stuttering Modification are two different philosophies that often get confused. Fluency shaping tries to prevent stuttering by changing how a person speaks — slower rate, gentle onsets, continuous vocalization. Stuttering modification, which comes out of the Van Riper tradition, accepts that stuttering will happen and teaches the person how to stutter less painfully. Both have merit. The problem is that a lot of clinics pick one and stick with it dogmatically. A child who stutters severely might benefit from fluency shaping first to build a baseline of controlled speech, then transition to modification work once they have some confidence. Or vice versa, depending on age and psychological factors. There's no universal answer. Cognitive-Linguistic Therapy is where things get complicated fast. This is the domain of aphasia, traumatic brain injury, and dementia-related language loss. The techniques range from constraint-induced language therapy to melodic intonation therapy to semantic feature analysis. Each has evidence behind it, each has limits. Melodic intonation therapy, for instance, works well for non-fluent aphasia but does almost nothing for fluent aphasia patients. Semantic feature analysis is surprisingly effective for word-finding difficulties but requires the patient to have enough preserved semantic knowledge to work with. I once worked with a patient whose expressive language was so fragmented that semantic analysis had nothing to latch onto. We pivoted to a phonological component analysis approach instead, focusing on sound structure rather than meaning, and that gave us a usable pathway. The lesson here is that the textbook technique doesn't always fit the person. Augmentative and Alternative Communication (AAC) is another category that therapists either over-rely on or underuse. Picture boards, speech-generating devices, app-based systems — these tools can be life-changing for someone with severe aphasia or ALS. The common mistake is introducing AAC too late, as if it's a failure of speech therapy rather than a valid treatment modality. Some clinicians still act like AAC means you've given up on oral speech. That's not how it works. AAC can actually support verbal speech development by reducing frustration and giving the patient a communicative outlet while motor planning improves. The research is clear on this, but practice hasn't caught up everywhere.
Get the Full Details

Pragmatic and Social Communication Therapy is essential for autism spectrum conditions and some social-cognitive disorders. Teaching someone to read facial expressions, understand sarcasm, maintain turn-taking in conversation — these aren't soft skills. They're structured targets with measurable outcomes. The hard part is that pragmatic skills don't generalize well. A patient might nail a role-play in the therapy room and then struggle completely at a family dinner. The workaround is to practice in increasingly naturalistic settings, not just simulated ones. I've had clients who could identify emotions from photos but couldn't tell if their coworker was annoyed in real time. The gap between controlled stimuli and real-world complexity is enormous, and most programs don't bridge it. Phonological Awareness and Literacy Interventions overlap heavily with speech-language pathology, especially in school settings. Phonological processing underpins reading and writing. A child who can't distinguish between similar sounds will struggle with decoding. The techniques here involve explicit instruction in sound manipulation — blending, segmenting, substituting. These skills transfer to literacy, which makes them high-leverage. The downside is that they require time, and in many school districts, SLPs are stretched so thin that the depth of instruction needed never happens. A 15-minute group session once a week won't fix a phonological deficit. It takes daily, structured practice over months. The bottom line is that no single technique works across the board. The effectiveness depends on the diagnosis, the severity, the patient's cognitive profile, and how well the therapist adapts the approach. The best therapists I know don't pick a method and stick with it. They assess, they choose, they monitor, and they change course when the data tells them to. If a technique isn't moving the needle after three to four weeks of consistent work, it's time to try something else. Continuing with a failing approach isn't dedication. It's waste of everyone's time.