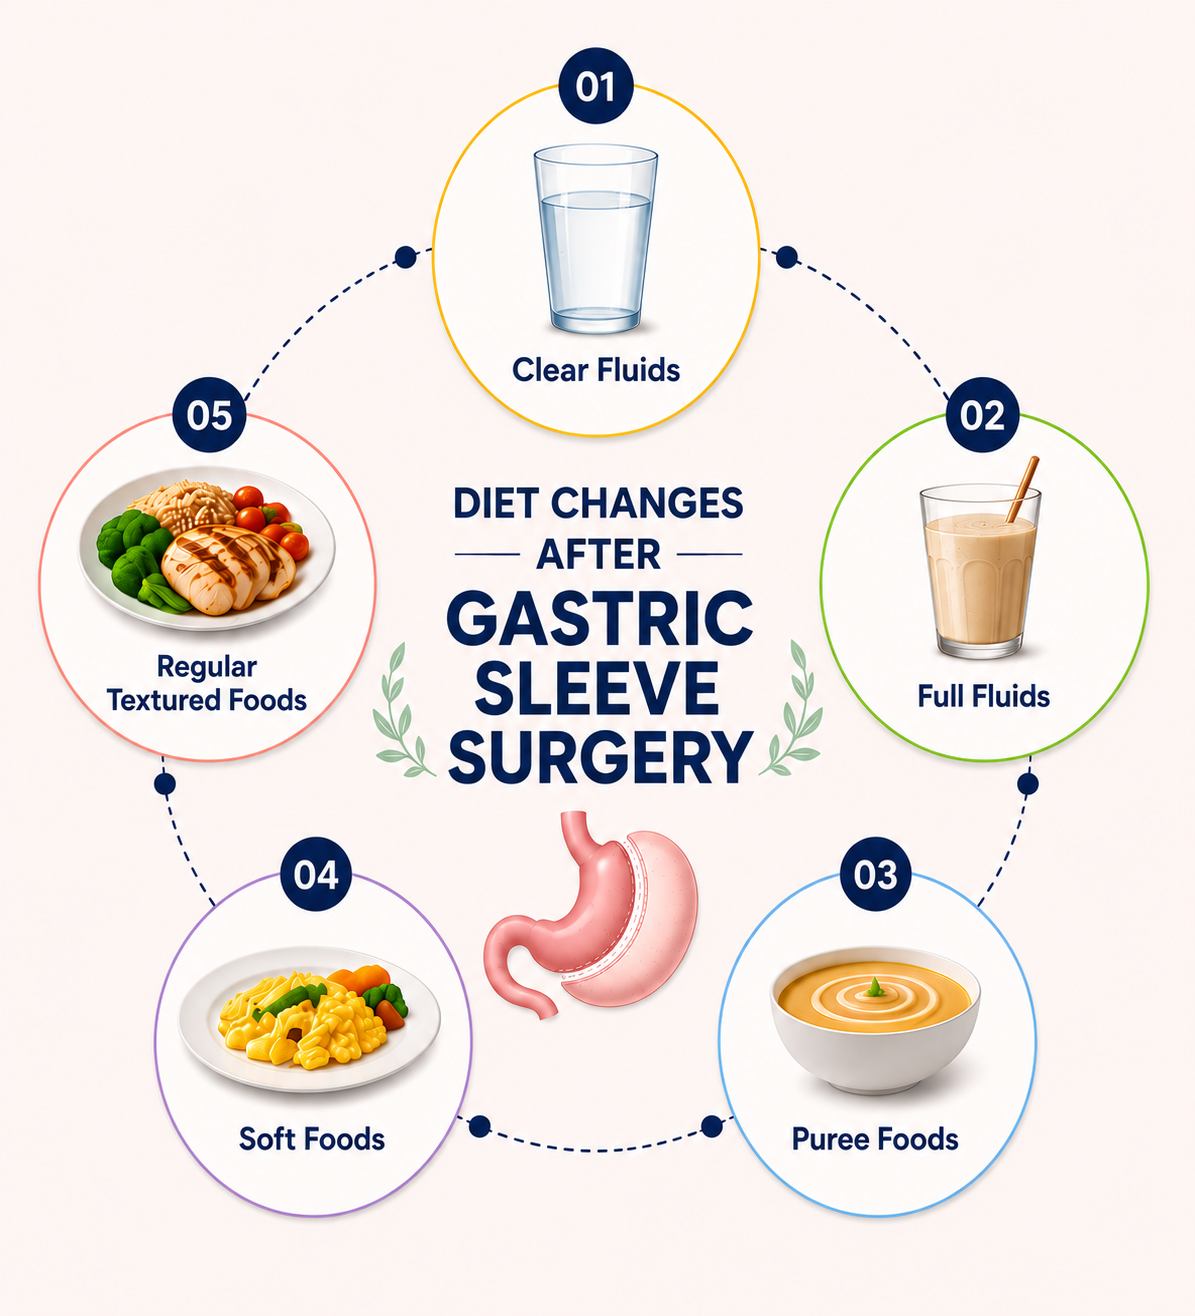
What You Actually Eat After the Procedure
The first two weeks are mostly liquid. Clear broth, then full liquids like skim milk or unsweetened almond milk, then protein shakes. That's the standard protocol most surgeons send you home with. I've seen plenty of patients skip straight to solid food too early because they feel fine, which is how you get vomiting episodes that send you back to the ER. The stomach remnant is swollen and raw inside. It doesn't care that you feel good. Weeks three and four introduce pureed foods. Think cottage cheese, blended soups, Greek yogurt, mashed tuna. Everything needs to be the consistency of baby food or thicker. You're not chewing much at this point. You're swallowing. That's the whole game. If you can see chunks, it's too thick. Blend it again.
Typical Diet After Gastric Sleeve Surgery
By week five you're transitioning to soft foods. Scrambled eggs, well-cooked pasta, flaky fish, soft bread that isn't crusty. This is where most people stumble. They hear "soft" and think a slightly undercooked steak qualifies. It doesn't. If it requires more than three chews, it's too tough for a sleeve that's roughly the size and shape of a banana at this stage. The long-term diet settles into smaller portions, higher protein focus, and slow eating. That's it. No fancy restrictions after the first six months unless your surgeon tells you otherwise. Most won't. The real constraint is volume, not food type. You can eat pizza. You just can't eat more than three bites of it before you feel full. Trying to force more is how you end up with painful vomiting or stretching the pouch, which undermines the whole procedure. I learned this the hard way with a patient who insisted on eating a full slice of dense banana bread on day twelve because she was starving. She threw up twice in an hour and couldn't keep fluids down until midnight. We had to restart her on clear liquids for another four days. She was frustrated, which is fair, but the sleeve doesn't negotiate. It shrinks and inflames and then gradually heals. You go at its pace or you deal with the consequences.
One thing most guides don't mention: carbonation becomes a problem almost immediately after the puree stage. Sparkling water, seltzer, diet soda — it expands in that small stomach and causes discomfort that can last hours. I've had patients call me at 2 AM thinking they were having complications, and it was just a diet coke they'd had at dinner. Switch to flat water or decaf tea. It sounds trivial but it matters more than you'd expect. Another counter-intuitive detail: drinking with meals is usually fine but timing matters. Don't drink a full glass of water during food. It displaces the limited space and makes you feel overly full or nauseated. Sip between meals instead, or have maybe three ounces with food if you need it for swallowing. Most people naturally learn this within a few weeks because their body corrects them pretty quickly. Protein priority is non-negotiable. You're looking at 60 to 80 grams daily minimum to preserve muscle mass and support healing. That translates to roughly four to five servings of protein-rich foods spread across the day. A single chicken breast might be too much for one sitting early on. Two smaller protein feeds are better than one big one. Protein shakes help but they don't replace whole food entirely. The texture work matters for retraining your mouth and throat anyway.
Get the Full Details

Fiber is another area where people get burned. Early on, raw vegetables and tough skins are off the table. Cooked carrots, peeled apples, well-cooked spinach — those work. Raw salad greens in the first three months are basically sandpaper for a healing sleeve. Some people reintroduce them by month four without issues. Others never tolerate them. There's no universal answer. Listen to your body and track what triggers discomfort rather than following a rigid list. Sugar intake deserves a separate mention. Not because it's restricted medically, but because sweet things taste overwhelmingly intense right after surgery. Chocolate that used to be enjoyable can now make you feel sick. This isn't a rule — it's a sensory shift. Some people bounce back to normal sugar tolerance within a year. Others keep a lasting aversion. Either outcome is normal.
What the Literature Says Versus What Actually Happens
Most patient handouts give you a phase-by-phase chart that looks clean and linear. Real life is messier. Some weeks you stall. You might do well for four days and then have a terrible day where nothing stays down. That happens. It doesn't mean you're failing. It means your stomach is still adapting. The one area where protocol really does matter is vitamin supplementation. You'll be on a bariatric multivitamin for life, plus calcium citrate and B12, usually. The sleeve removes the part of the stomach that helps absorb certain nutrients. That's permanent. Skipping supplements doesn't cause immediate problems but deficiency symptoms show up months or years later, and by then it's harder to reverse. I've seen cases of neuropathy from B12 deficiency in patients who thought they were fine because they felt okay. Weight loss expectations vary. The average patient loses 60 to 70 percent of their excess weight in the first year. Some lose less. Some lose more. Genetics, adherence to protein goals, activity level, and starting weight all factor in. There's no way to predict your individual result from the surgery alone. The diet is the tool. How well you use it determines the outcome more than the procedure itself.
If you're struggling with the texture progression or constantly hitting vomiting episodes past week three, that's worth bringing up with your surgical team. It could be a stricture or swelling issue that needs evaluation. Don't just push through it hoping it gets better on its own. Early intervention prevents longer setbacks. There's no download link or shortcut for this. The diet is straightforward in concept and frustrating in execution. You follow the phases, you prioritize protein, you eat slowly, and you let your body tell you when something is wrong. That's the whole thing in practice.


