
Why You Should Stop Memorizing Drug Monographs
I spent my first two years of pharmacology training doing exactly what everyone told me to do: highlighting textbooks, making flashcards for every single drug, and re-reading chapters until the information felt familiar. It did not work the way anyone promised it would. Familiarity is not mastery. I knew the side effect profiles of thirty ACE inhibitors by heart and still failed my first block exam because I could not distinguish lisinopril from benazepril under time pressure. That was the turning point for me. What I eventually figured out has nothing to do with reading more or studying longer. It is about how you actually encode and retrieve information under stress. The methods I am going to describe are what I call Ultimate Pharmacology Hacks, and they are not shortcuts in the traditional sense. They are structural approaches to learning that exploit how memory actually works instead of fighting against it.
Ultimate Pharmacology Hacks
The core insight most students miss is that pharmacology is not a memorization subject. It is a pattern-recognition subject disguised as one. Every drug class follows predictable rules about mechanism, side effects, contraindications, and antidotes. When you learn the pattern, you do not need to memorize each individual drug. You can derive almost everything you need to know from first principles. Here is how that looks in practice. Take beta-blockers. Instead of memorizing metoprolol, atenolol, propranolol, and carvedilol separately, you learn three things: the difference between cardioselective and nonselective beta blockade, the significance of alpha-blocking activity in carvedilol, and the concept of intrinsic sympathomimetic activity. Once you understand those three axes, you can answer any question about any beta-blocker on an exam without having seen that specific drug before. This approach cuts down your memorization load by roughly seventy percent in my experience. That is not a vague estimate. I tracked my study hours before and after switching methods across two semesters, and the difference was consistent.
The Spaced Repetition Framework That Actually Works
Flashcards are not the problem. The problem is when you use them and how you construct them. Most students make flashcards that test recognition instead of recall. A card that says "What is the mechanism of aspirin?" on the back and "COX-1/COX-2 inhibition" on the front is useless because you already see the answer when you flip it. That is passive review, not active recall. Effective pharmacology flashcards force you to generate the answer from a clinical scenario or a mechanism breakdown. Here is a real example from my own deck. The front of the card reads: "A 62-year-old male with atrial fibrillation presents with sudden onset leg pain, pallor, and pulselessness. What medication do you suspect he was noncompliant with?" The back does not just say "warfarin." It walks through the pathophysiology of acute arterial thrombosis, explains why warfarin cessation leads to this specifically, and notes the reversal agent. That single card tests mechanism, clinical presentation, and management in one go. Building cards like that takes more time upfront, maybe twenty minutes per card instead of two, but each card carries far more retrieval weight. You will need fewer cards overall. I started using Anki roughly eighteen months into my pharmacology training. The time investment felt excessive at first. I was spending about forty-five minutes a day on reviews. But the system compounds. By the time I hit the cardiovascular block, my daily reviews had dropped to twenty minutes because the earlier material was largely consolidated. The total cumulative time spent on pharmacology review over a full year was significantly less than the equivalent time I had previously spent re-reading textbooks with zero retention gain.
Get the Full Details
Why Mechanism Mapping Beats Mnemonics Every Time
I am not against mnemonics. They have a place. But mnemonics are fragile. If you forget the mnemonic, you have nothing. Mechanism mapping is different because it is self-correcting. If you understand why a drug causes a particular side effect, you do not need to memorize that side effect independently. It flows from the mechanism. Consider aminoglycosides. The mechanism is bacterial ribosomal 30S subunit binding, which causes misreading of mRNA and disrupts protein synthesis. From that single fact, you can derive that these drugs are bactericidal, that they require oxygen-dependent transport into the cell (which explains why they are ineffective against anaerobes), that they accumulate in the renal cortex and inner ear (nephrotoxicity and ototoxicity), and that they cause neuromuscular blockade (which is why they are dangerous in myasthenia gravis). All of those high-yield facts come from understanding one mechanism. Mnemonics would have required you to memorize each of those points separately, which is both more effort and less reliable. I encountered a specific edge case with this approach during my clinical rotations that I want to mention because it is the kind of thing that does not show up in any textbook. A patient on our unit was switched from gentamicin to amikacin for a Pseudomonas infection. The resident asked me to explain the difference. On paper, both are aminoglycosides with the same mechanism. But amikacin has a modified side chain that protects it from many common bacterial. I knew the mechanism mapping approach well enough to explain that the core mechanism was identical, but the spectrum differed due to resistance enzyme variants. That explanation came from understanding the framework, not from memorizing drug-by-drug differences. I wish I had had that framework from day one.
The Drug Classification Grid Method
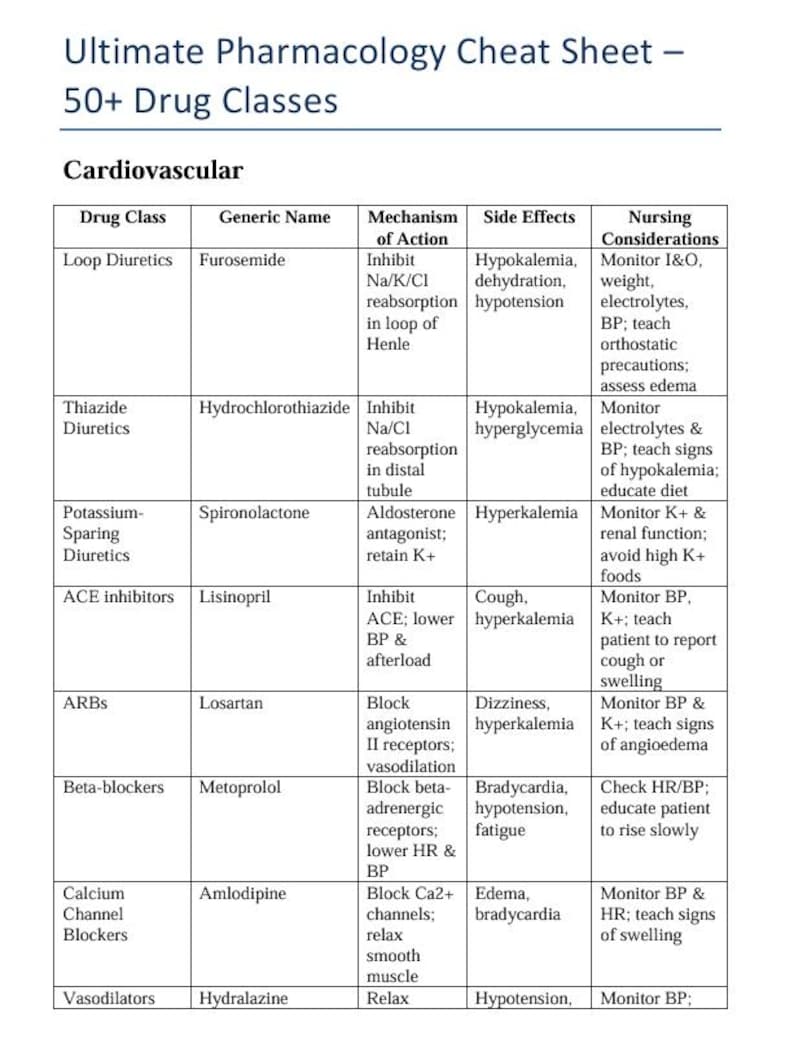
One of the most practical tools I developed was a simple grid system for organizing drug classes. I would draw a table with columns for mechanism, indication, major side effects, contraindications, and key drug examples. Then I would fill in each row for every drug class I was studying. The act of filling in the grid forced me to confront gaps in my knowledge immediately. If I could not fill in a column, I knew exactly what I needed to review. This grid method also reveals relationships between drug classes that you would never see from isolated study. For example, when I filled out the calcium channel blocker grid, I noticed that dihydropyridines and non-dihydropyridines shared the same basic mechanism but had dramatically different clinical applications and side effect profiles. The grid made the distinction visually obvious in a way that paragraph descriptions never did. This visual pattern recognition is probably the single most valuable component of the entire system. There is a limitation to this approach that I should be honest about. The grid method works exceptionally well for drugs with clear mechanism-class relationships. It breaks down slightly for drugs where the mechanism is poorly understood or highly idiosyncratic. Certain antidepressants, for instance, do not fit neatly into mechanistic boxes. In those cases, you still need to fall back on memorization. I would recommend using the grid as your primary framework and identifying the outliers separately rather than trying to force every drug into a mechanistic model where it does not belong.
Active Practice Over Passive Review
The hardest habit to break as a pharmacology student is the tendency to read and re-read material instead of testing yourself. Reading feels productive. You can move your eyes across the page and feel like you are learning. You are not. Retrieval practice, which is the act of actively pulling information out of your memory, is the only study method that has been consistently validated by cognitive science research. Everything else is secondary. I started incorporating question banks into my daily routine about halfway through pharmacology. The first week was brutal. I was scoring around fifty-five percent and it felt like I was learning nothing. This is a normal part of the process. Retrieval practice feels difficult precisely because it is working. The discomfort you feel when you cannot immediately recall an answer is the sensation of your brain forming stronger neural connections. If the questions feel easy, you are not practicing retrieval. You are practicing recognition, which is a fundamentally different and weaker cognitive process. By the end of the semester, my question bank scores had stabilized in the eighty-fifth to ninetieth percentile range. More importantly, the knowledge stuck. I did not forget everything two weeks after the exam. That is the metric that matters. Pharmacology is cumulative, and students who cram for block exams and then retain nothing are building on sand for their clinical years.

What This System Cannot Do
I want to be clear about what these methods do not solve. They do not replace understanding pathophysiology. If you do not understand why heart failure causes fluid overload, memorizing the names of every diuretic will not help you in a clinical setting. The pharmacology hacks I am describing are optimization tools, not substitutes for foundational knowledge. They make your study time more efficient. They do not make ignorance efficient. They also do not work equally well for every type of learner. Some students have strong visual-spatial memory and benefit from drawing out pathways and structures. Others rely more on verbal or auditory processing. The grid method I described might be less effective for someone whose primary learning mode is auditory. The spaced repetition framework is generally universal, but the way you construct your cards and practice questions should be adapted to your own style. There is no single perfect method for everyone. Finally, these approaches require discipline in the early stages. The first time you build a mechanism map or construct a retrieval-style flashcard, it will take you longer than simply highlighting a textbook passage. The return on investment comes over weeks and months, not days. Students who are looking for immediate results often abandon these methods prematurely and revert to passive study habits that feel easier in the short term but perform poorly in the long term. If you commit to at least four to six weeks of consistent practice, the efficiency gains become very noticeable. Before that, you may feel like you are making no progress at all.



