
Section 1557 Compliance for Health Plans: A Practical Walkthrough
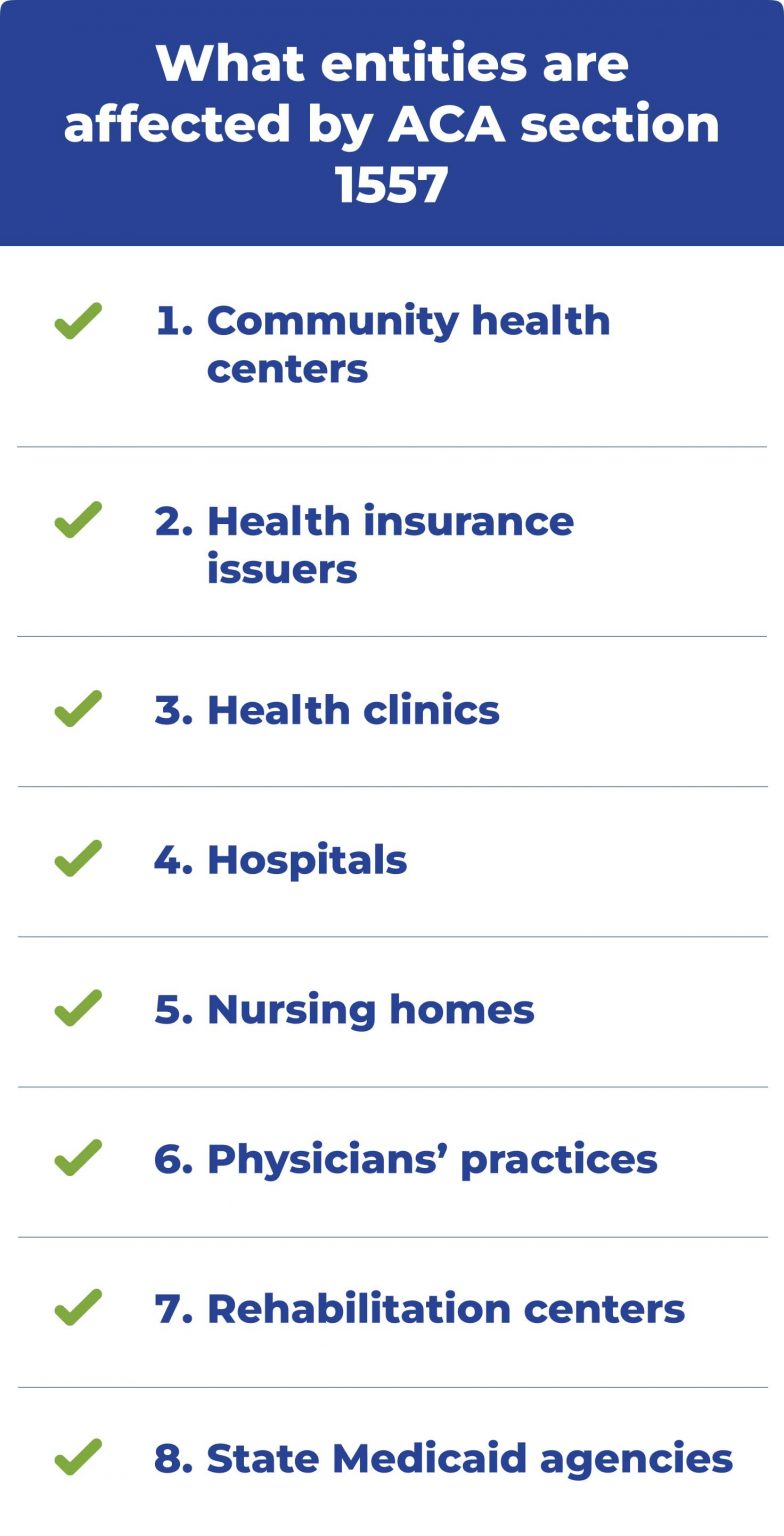
The Health and Human Services Office for Civil Rights enforces Section 1557 of the Affordable Care Act, which prohibits discrimination in any health program or activity that receives federal financial assistance. That covers most health plans, hospital systems, and insurance exchanges. If you are a compliance officer, benefits administrator, or plan sponsor trying to figure out where to actually start, this is how it works in practice. I have spent the last several years fielding requests from plan administrators who got caught off guard during an OCR audit. The thing nobody tells you upfront is that Section 1557 compliance is not just about posting a bilingual notice somewhere and hoping for the best. The requirement has multiple moving parts, and the recent regulatory updates from 2024 made things both stricter and more detailed than they were when the rule first took effect.
Under Aca Section 1557 A Health Plan: What You Actually Need to Do
Start by identifying every language service obligation you have. Section 1557 requires that individuals with limited English proficiency receive meaningful access to your health programs. That means providing translation of key documents and competent interpretation services at no cost to the patient. The 2024 rule specifically calls out written notices of availability, enrollment materials, claims forms, and grievance procedures as documents that must be translated into languages that represent at least 10% of the population served in your service area. Most plans I have worked with only translate the top three or four languages. That is a mistake if your demographic data shows a significant Spanish-speaking population, let alone Vietnamese, Mandarin, Tagalog, Arabic, or Korean speakers in your coverage area. OCR has flagged plans that ignore large non-English populations because they assume English-only is fine. It is not fine. Next, address the disability accommodation side. People who are deaf, hard of hearing, or have speech disabilities are entitled to appropriate auxiliary aids and services. That includes qualified sign language interpreters, real-time captioning, TTY devices, and accessible electronic formats. Again, no cost to the individual. A common failure point I see is plans offering video remote interpreting when on-site certified interpreters are actually needed. Not every situation is appropriate for VRI. An intricate medical consultation or a mental health intake where nuanced communication matters should get an in-person qualified interpreter. If the plan just defaults to VRI across the board to save money, that is a compliance gap.
The notice requirement is straightforward but often botched. You need to post a notice in a prominent location, both physically and on your website, informing individuals of their rights under Section 1557 and how to request language assistance or disability accommodations. The notice must be available in the primary language of each covered group. The format matters too. Small print buried in a terms-of-service document does not count. It needs to be accessible and legible. Here is something most people miss. Section 1557 also prohibits discrimination based on sex, which the 2024 rule explicitly includes gender identity and sexual orientation. This has been the most litigated and politically contested portion of the regulation. Some plans continue to resist this aspect under various legal challenges, and the litigation landscape shifts frequently. My advice is to comply with the current rule as written while monitoring court developments. Non-compliance based on hope that a court will overturn the rule is a risky strategy. The Department of Justice and HHS have consistently defended the provision. Training is another area where plans cut corners. You need to train staff who interact with patients and enrollees on Section 1557 requirements. This is not optional. Front desk personnel, call center agents, and intake coordinators need to know how to offer interpretation services, how to document accommodation requests, and what to do when a patient asks for a translator. I had a case where a plan's call center agent told a Spanish-speaking enrollee to just try English because that was the only language the company offered support in. That single conversation became the basis of a discrimination complaint, and the plan ended up paying settlement and implementing a remediation plan with ongoing reporting obligations.
Get the Full Details
The Real Work: Building a Functional Compliance Infrastructure
Compliance is not a checkbox exercise. It requires operational infrastructure. Here is what that looks like on the ground. First, maintain a language identification tool. This is usually built into your patient management or enrollment system. When a member or enrollee self-identifies a language preference or when staff detect limited English proficiency during intake, the system should flag that and route the interaction to appropriate language services. If your system does not have this capability, you are operating blindly. I recommend integrating a language line service that provides on-demand interpretation in 200-plus languages. The cost is typically a few dollars per minute, and having it available immediately prevents many compliance failures. Second, establish a documented process for requesting auxiliary aids and services. Someone needs to handle interpreter requests, and there needs to be a timeline. For non-emergency situations, reasonable efforts should result in interpreter availability within 48 hours. Emergencies require immediate assistance. Document every request and response. OCR will ask for this documentation during an audit, and plans that cannot produce records of accommodation requests often look negligent regardless of whether they actually fulfilled them.
Third, translate your key documents. The 2024 rule specifies which documents must be translated and into which languages based on your service area demographics. Use qualified professional translators, not machine translation, for official documents. Machine-translated notices, enrollment forms, or claims information will not satisfy the meaningful access requirement, and OCR has noted that in enforcement actions. I ran into a plan that used a commercial translation app for its Spanish materials. It produced garbled, inaccurate content that was worse than nothing. The mistranslations caused patients to misunderstand their coverage options and make incorrect enrollment choices. That plan faced both a compliance violation and a spike in grievance filings. Fourth, review your policies and procedures. Every policy that affects patient access or treatment should be reviewed through a Section 1557 lens. Does your prior authorization process create barriers for people with disabilities? Does your telehealth option work for people who are deaf? Are your website and mobile app accessible under Section 504 of the Rehabilitation Act, which intersects with Section 1557? These questions are not always easy to answer, and they require coordination between your compliance, IT, and clinical operations teams.
Pitfalls and Limitations
I want to be blunt about what does not work. Buying a compliance software package and assuming it solves everything is a common error. These tools can help with document tracking and language identification, but they cannot replace operational diligence. They also tend to be expensive and require ongoing customization for your specific plan structure. Another pitfall is thinking that compliance is the legal department's job. It is not. It requires involvement from operations, IT, customer service, clinical staff, and senior leadership. Without that cross-functional commitment, compliance efforts remain superficial. The biggest bottleneck I see is the shortage of qualified interpreters, particularly for less common languages and for sign language. Even with language line services, wait times can be long, and the quality of remote interpretation varies. In some rural areas, there may be no qualified interpreter available for certain languages even with telephonic or video services. This is a real operational challenge. The workaround I have used effectively is maintaining a roster of qualified freelance interpreters on retainer for high-need languages in your area, even if it means paying a premium. The cost of a $150-per-hour interpreter is negligible compared to the cost of a discrimination complaint or settlement.

There is also the issue of enforcement consistency. OCR enforcement has been uneven across regions, and some plans gamble on non-compliance because they believe they will not be audited. That is a calculation I do not recommend. Once you are in an audit, the remediation costs and reputational damage far exceed the cost of getting it right from the start.
A Note on Documentation and Audit Readiness
If you want to be prepared, maintain a compliance file that includes your language access plan, copies of translated documents, training records, interpreter service contracts, accommodation request logs, and any grievance or complaint history. Keep this file current and review it at least annually. I recommend doing the review in the fall so you are ready before open enrollment, which is when most compliance failures surface. Also, consider conducting an internal audit before OCR does one for you. Hire someone with healthcare compliance experience who understands Section 1557 requirements and can give you an honest assessment of your gaps. The cost of an internal audit is modest compared to the cost of a failed external audit.


