Sublingual Administration: What It Actually Is and How It Works
The term for anything going under the tongue in a medical context is sublingual. It comes from the Latin "sub" meaning under and "lingua" meaning tongue. When you put a medication under your tongue, it absorbs directly through the mucous membrane into the bloodstream, bypassing the digestive system and liver metabolism. This is fundamentally different from swallowing a pill. I ran a clinic for about twelve years where we used sublingual routes fairly routinely, mainly for nitroglycerin, buprenorphine, and certain benzodiazepines. People who are new to this often mess it up because they treat it like a regular pill. It isn't. The technique matters more than the molecule itself in a lot of cases. Here's the practical breakdown of how it works and what goes wrong most often.
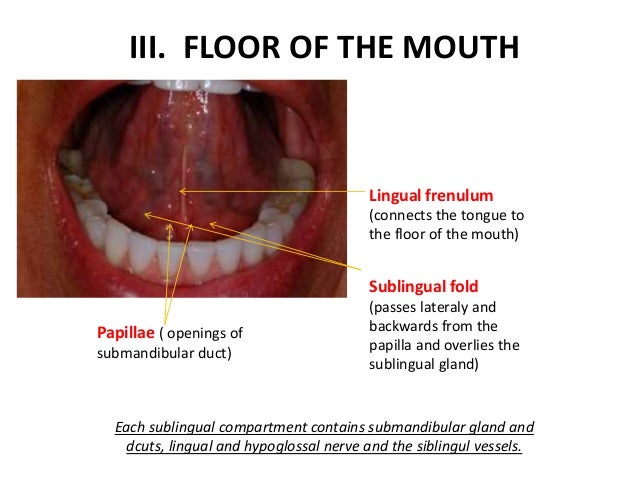
When you place the medication under the tongue, you want it centered toward the posterior portion, just behind where the front of the tongue meets the floor of the mouth. The mucous membrane there is thin and highly vascularized. Blood flow is decent, and the drugs pass directly into the venous system that drains into the superior vena cava. That means no first-pass hepatic metabolism, which is the whole reason this route exists as an alternative to oral swallowing. The absorption rate varies by compound. Nitroglycerin sublingual tablets can show onset in about three to five minutes. Buprenorphine takes longer, usually fifteen to thirty minutes for meaningful absorption. Fentanyl lozenges and buccal tablets work similarly. The key variable is the lipid solubility of the drug. More lipophilic compounds cross the mucosal barrier faster. Hydrophilic ones sit there doing nothing while you wonder if it even absorbed. One thing beginners miss completely: saliva dramatically reduces absorption for many sublingual drugs. If your mouth is wet when you place the tablet, it's going to dissolve into the saliva and get swallowed partially or fully, which routes it through the gastrointestinal tract instead of through the mucosa. That changes both the onset time and the bioavailability. I had a patient once who kept asking why her sublingual buprenorphine wasn't working. She was drinking coffee right before dosing. Her mouth was basically a river. I told her to stop hydrating for twenty minutes beforehand and to let the tablet sit undisturbed. She came back the next week and said it finally kicked in properly. Small thing, huge difference.
Here's the actual method. Place the tablet or film under your tongue. Close your mouth. Don't talk. Don't swallow. Try not to breathe through your mouth if you can help it, since that dries things out unevenly. Just wait. For most drugs, the recommended dwell time is between five and thirty minutes depending on the formulation. You'll know it's done when the tablet or film has largely dissolved and there's nothing left to manage. If you're using a film like Suboxone, it'll start dissolving within thirty seconds and should be fully gone in about five to ten minutes if you leave it alone. Now, the downsides. Not every drug works well sublingually. Some compounds simply don't cross the mucosa efficiently enough to be practical. Others irritate the tissue so badly that patients won't tolerate it. I've seen ulceration from people holding aspirin or NSAIDs under the tongue because they thought it would work better. It doesn't. It just burns the tissue and you swallow some of it anyway. Another issue is patient compliance. Some people can't sit still for ten minutes without swallowing or moving their tongue around. It sounds trivial but it's actually a real problem, especially with pediatric or anxious populations. For those cases, the buccal route (against the cheek) can be an alternative since the cheek mucosa is a bit more forgiving and easier to keep undisturbed.
Get the Full Details

If sublingual absorption is unreliable for a given patient or drug, the transdermal patch or intranasal route might be more appropriate. Intranasal fentanyl, for example, has comparable bioavailability to sublingual for certain indications and doesn't require the same level of patient cooperation during administration. The biggest pitfall I see in practice is assuming sublingual equals fast. It's faster than swallowing for the right drugs, but it's not instantaneous. People expect relief in sixty seconds and get frustrated when it takes eight. Set the expectation correctly from the start. Tell them three to five minutes for things like nitroglycerin, fifteen to thirty for most other medications. If it hasn't worked in thirty minutes, that's a different problem that needs a different approach.