Heart Rate Units: The Practical Stuff Nobody Tells You
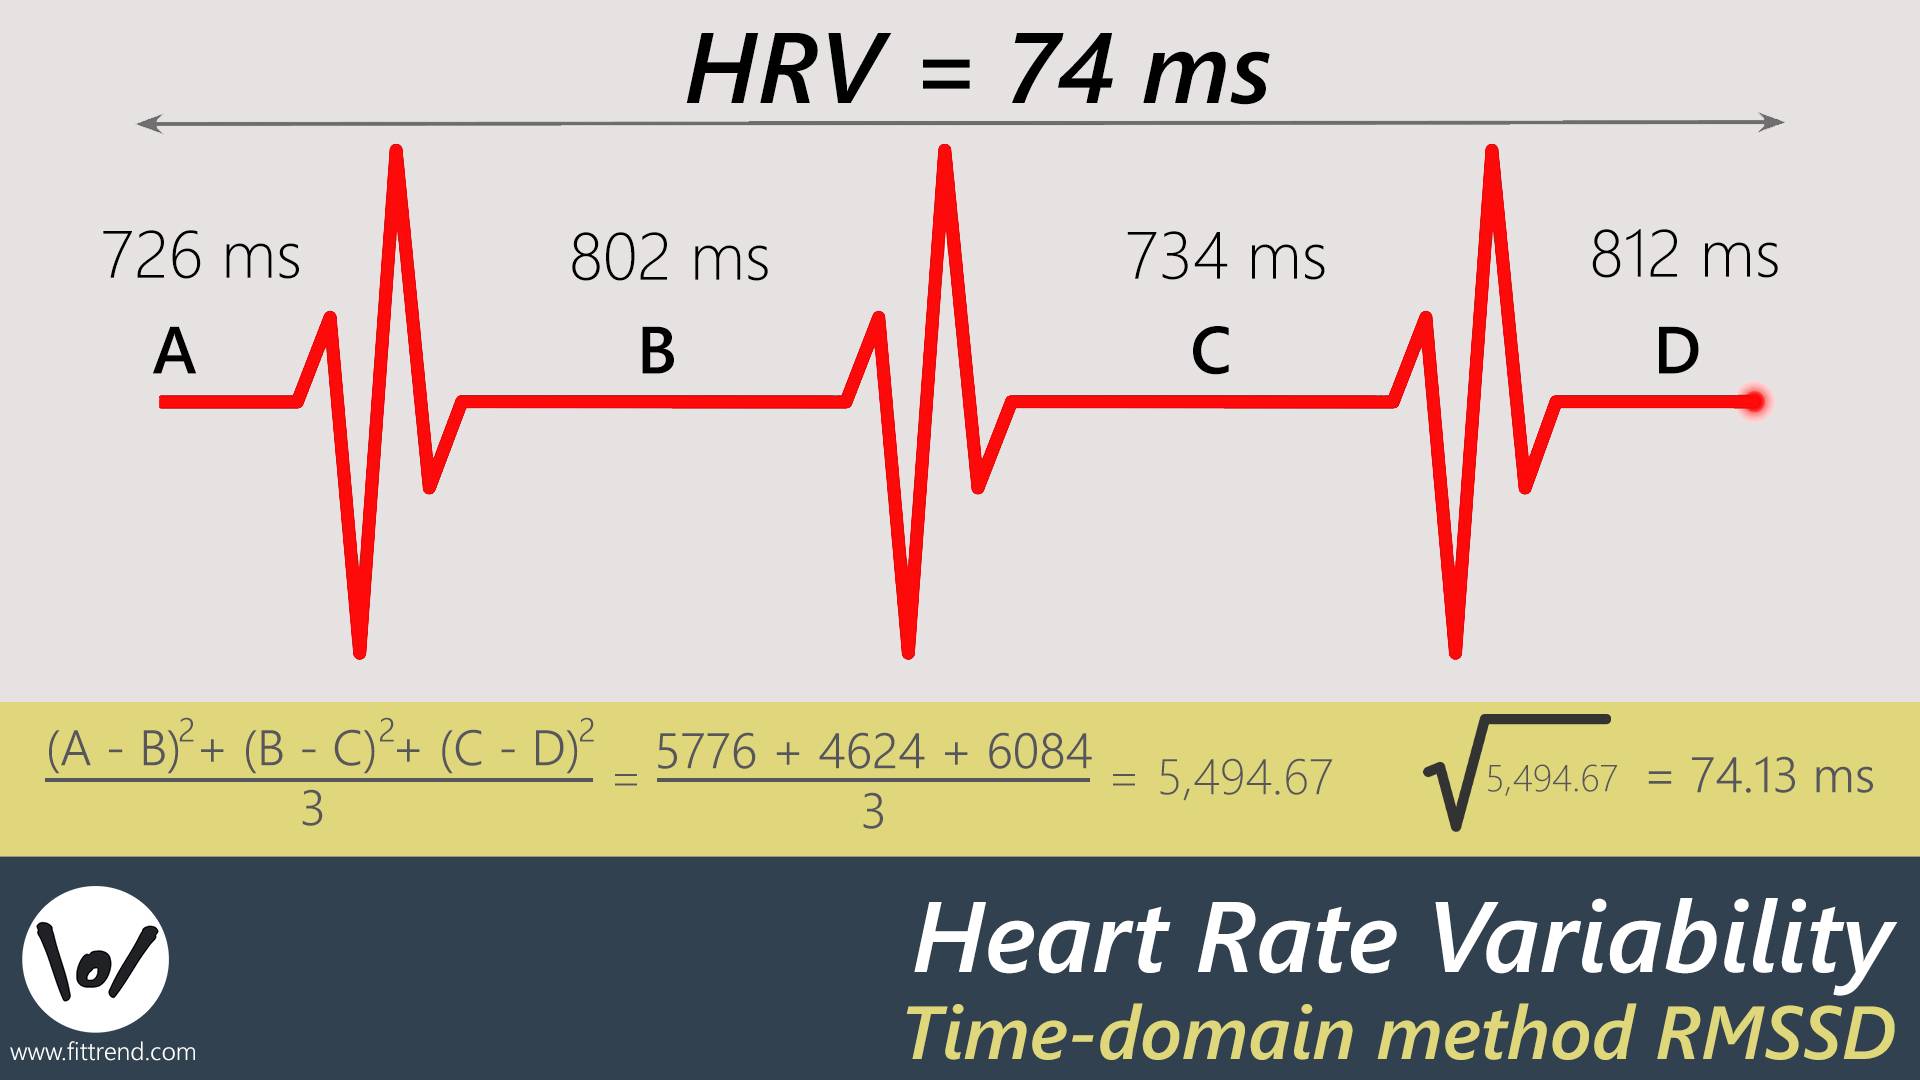
Most people think heart rate has only one unit. It doesn't. That's the first problem you'll hit if you're building anything that measures pulse automatically instead of just reading a number off a smartwatch. The standard unit is beats per minute, written as bpm. That's what every consumer device outputs. But in medical and research contexts, you also see beats per second (bps) and occasionally heart rate variability measured in milliseconds (ms). If you're integrating data across platforms, mixing these up silently will corrupt your entire dataset before you notice anything is wrong. A 72 bpm reading converted to bps is 1.2, not 1.2 bpm. Simple mistake, huge mess later.Understanding Units For Heart Rate in Practice
Here's how this actually plays out when you're not just reading from a polished app. I spent a couple years working with continuous heart rate telemetry from chest straps and medical-grade ECG patches, and the unit confusion alone cost us roughly three weeks of debugging before we realized one of our data pipelines was ingesting raw R-R intervals in milliseconds and then averaging them as if they were already in bpm. The resulting "heart rate" values were completely nonsensical — numbers like 800-900 that looked like sensor failure but were actually just a unit conversion error. The fix was straightforward: normalize everything to bpm at the ingestion layer, period. Any incoming data that wasn't in bpm got flagged and converted immediately. We added a validation rule that rejected any value outside 20-220 bpm as a quality check, which also caught a few genuinely broken sensor readings along the way. Let me explain how the conversion actually works under the hood, because understanding this changes how you debug issues when readings go haywire. Heart rate monitors that use ECG detect the R-wave complex — that sharp spike in the QRS cycle. The time between two consecutive R-waves is called the R-R interval, typically measured in milliseconds. To get bpm, you divide 60,000 by the R-R interval in milliseconds. So an R-R interval of 833 milliseconds equals 72 bpm. If the interval drops to 500 ms, that's 120 bpm. The math is trivial. Getting it right consistently across noisy real-world data is where things get complicated.
Optical sensors (PPG) work differently than electrical sensors (ECG). PPG measures blood volume changes in your wrist or finger using green or infrared light. The signal is noisier, especially during movement. Motion artifact is the killer here. I've seen gym-goers with heart rates reporting 180 bpm while sitting perfectly still on a bike just because their wrist strap was loose. The sensor was picking up arm swing as pulse. Switching to a chest strap solved it immediately, but only after we'd spent a day chasing phantom arrhythmias in the data.
When Standard Units Fail You
There are scenarios where bpm alone doesn't tell you anything useful. During high-intensity interval training, heart rate lag becomes a real problem. Your actual heart rate might spike to 170 bpm, but a chest strap will take 15 to 30 seconds to catch up. During that window, your bpm reading is stale. If you're calculating training load or Zone 5 time, those numbers will be wrong regardless of how accurate your sensor is. This isn't a unit problem. It's a fundamental limitation of cardiovascular physiology — your heart can't respond faster than it physically can, and no amount of better engineering removes that delay. Another edge case nobody talks about: athletes with high vagal tone, like distance runners, can have resting heart rates in the 30s or 40s. Most consumer algorithms assume a normal range and will flag these as sensor errors or drop the data entirely. I worked with a cyclist who trained at a resting 38 bpm and every device we tried reported "no heart rate detected" for the first ten minutes of every ride. The workaround was to manually override the minimum threshold in the device firmware. After that, readings were consistent. If you need sub-minute precision or are working in a clinical environment, bpm from a wrist-based optical sensor is not reliable enough. Hospital-grade pulse oximeters and ECG monitors are designed for this, but they're expensive and impractical outside a medical setting. For research or serious athletic analysis, a chest strap with antialiasing filtering and a sampling rate of at least 1 Hz is the minimum I'd recommend. Anything lower and you're losing information on every heartbeat.
Get the Full Details
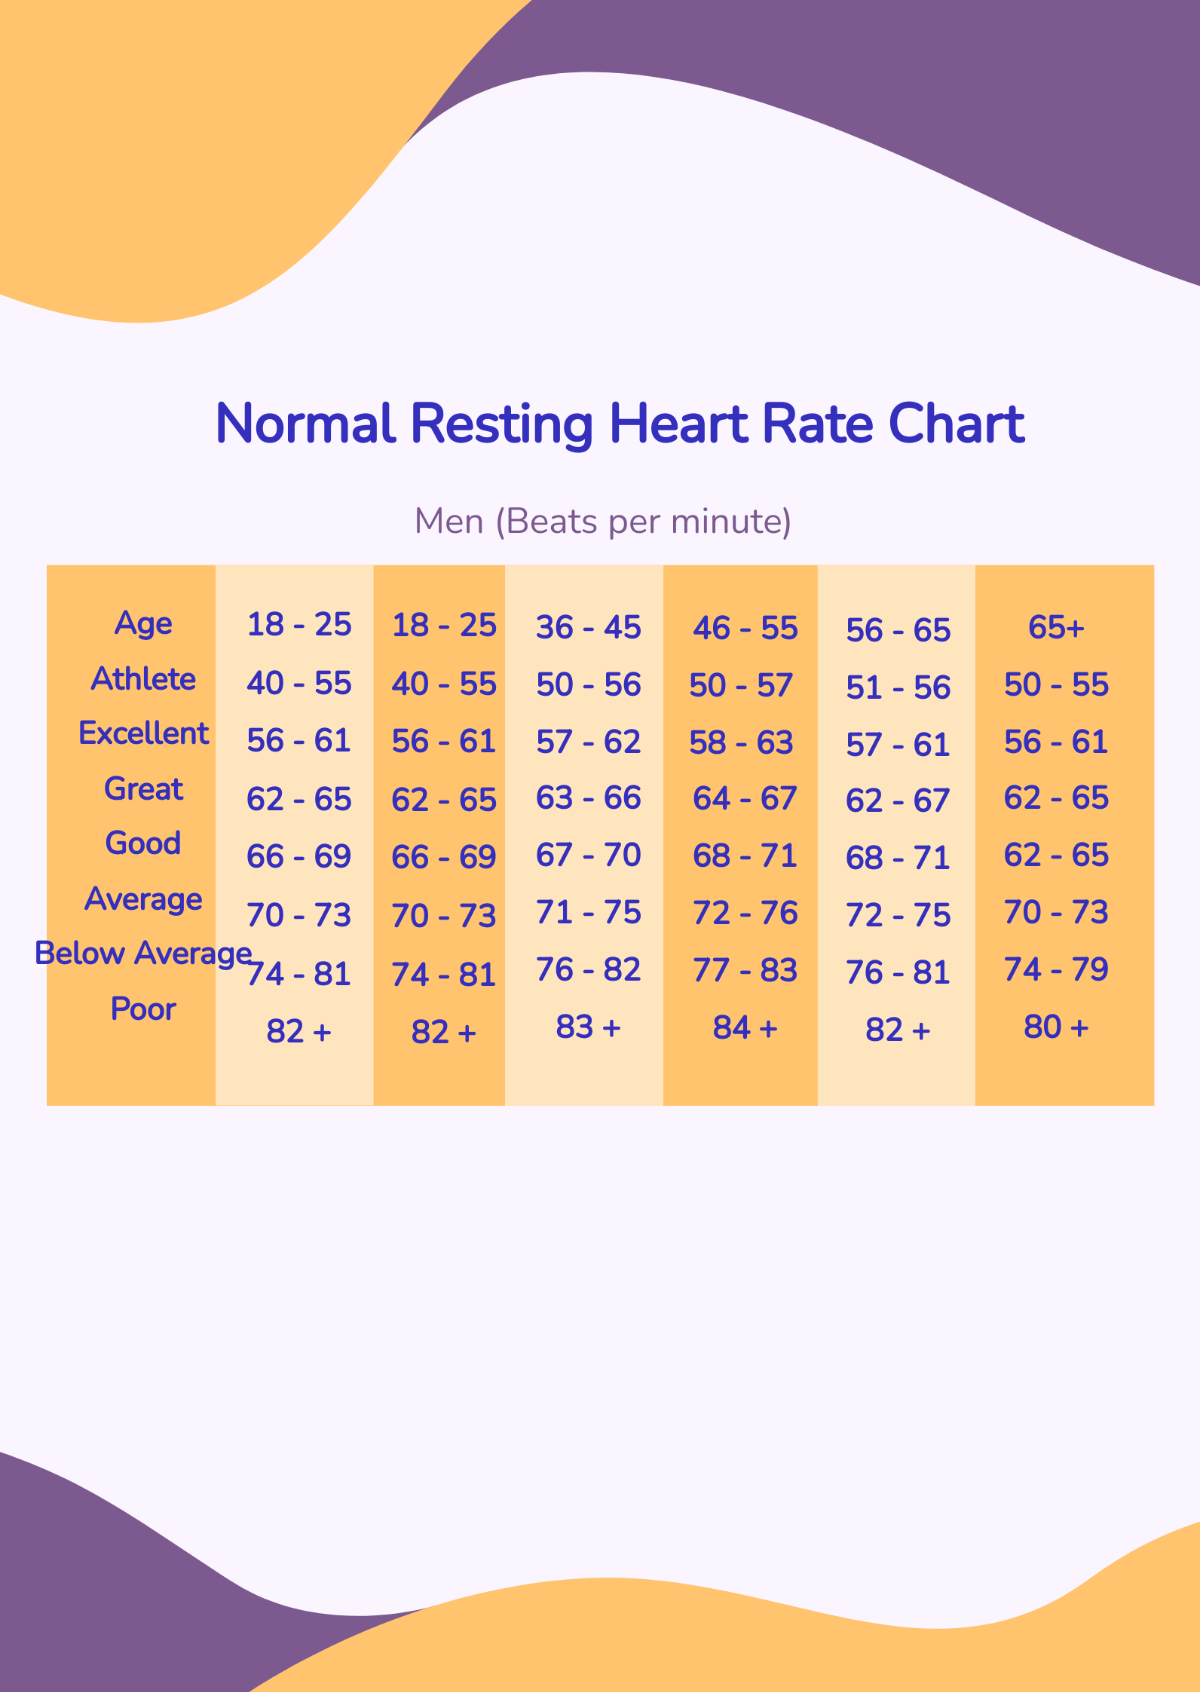
The bottom line is that bpm is the default unit, it's well understood, and it works fine for most applications. But the moment you start aggregating data from multiple sources, pushing values through automated pipelines, or dealing with edge-case physiology, the units stop being a simple detail and become the thing that makes or breaks your system. Pay attention to what unit your data is actually in at every stage. Assumptions will cost you more than verification ever will.