What the Urinary System Study Guide Actually Covers
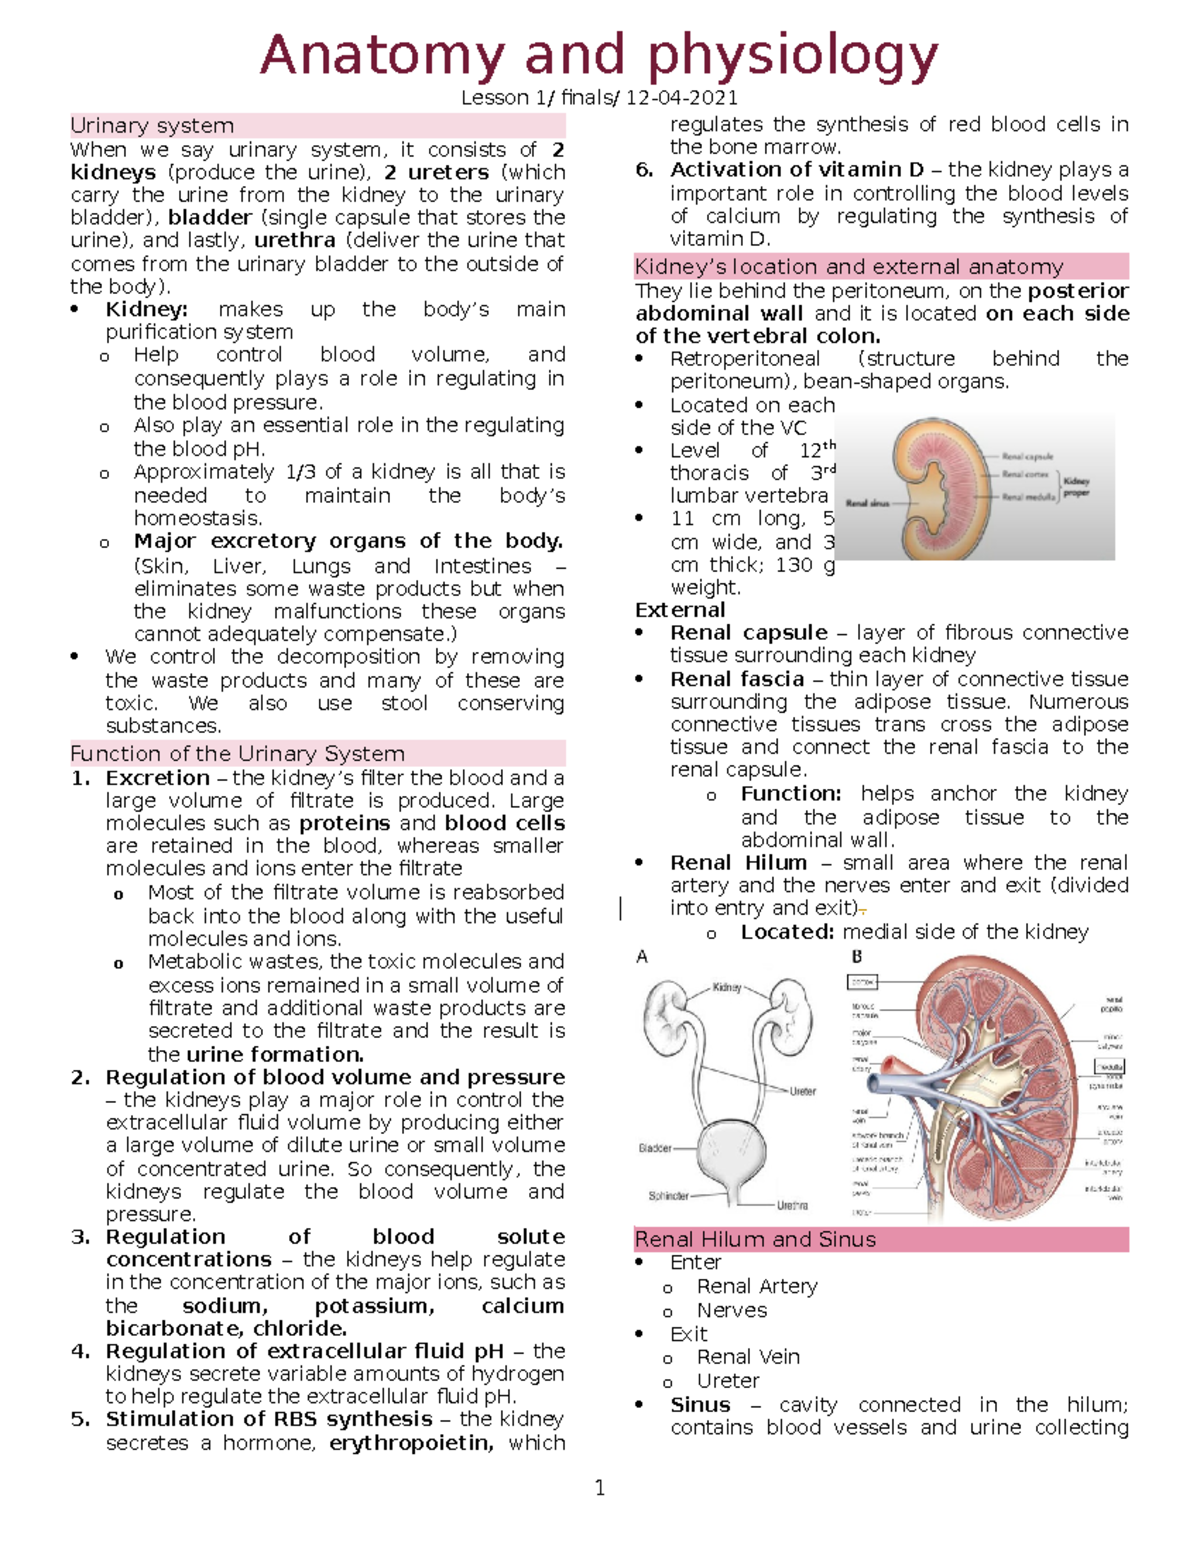
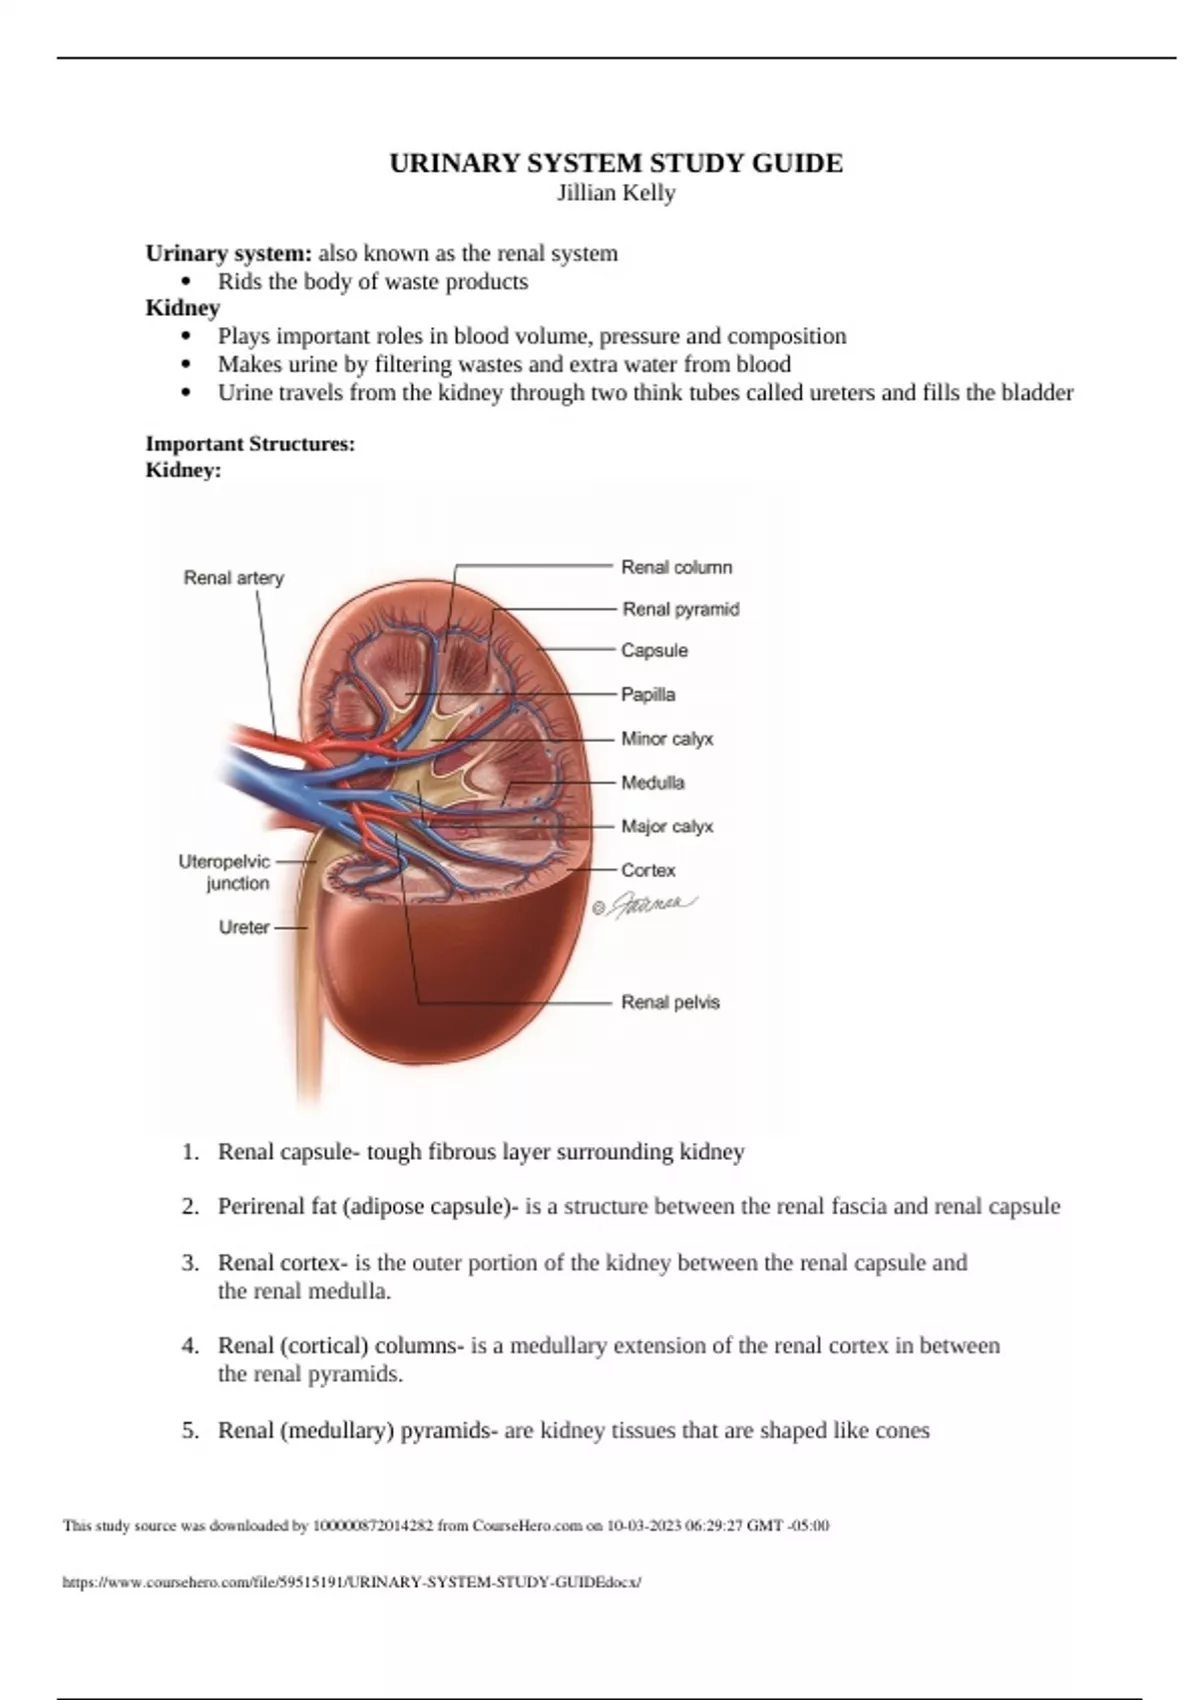
Most study guides on the urinary system hit the same surface-level facts: kidneys filter blood, ureters carry urine, bladder stores it, urethra gets rid of it. That's fine for an intro, but it won't help you on an actual exam or in clinical practice. A proper Urinary System Study Guide needs to get into the nephron, the renin-angiotensin-aldosterone system, electrolyte balance, acid-base regulation, and the hormonal controls that govern everything. If you're just memorizing organ names without understanding how they talk to each other, you'll forget it all within a week. I've watched way too many students try to memorize renal physiology like it's a list of vocabulary terms. It doesn't work. The system is highly interconnected, and when you hit questions about glomerular filtration rate or tubular reabsorption, the connections matter more than isolated facts. Here's how I'd approach building one that actually sticks. Start with the nephron. Draw it. Not from a textbook diagram, but from memory, and label every segment: Bowman's capsule, proximal convoluted tubule, descending loop of Henle, ascending loop of Henle, distal convoluted tubule, collecting duct. Once you can draw that cold, go back and fill in what happens at each section. Sodium reabsorption here, water reabsorption there, hydrogen ion secretion in the DCT. This takes about twenty minutes and it anchors everything else.
After that, layer in the regulation systems. The juxtaglomerular apparatus is where everything converges, and honestly, most guides gloss over it. The macula densa cells sense sodium chloride concentration in the tubular fluid. When NaCl drops, they signal the juxtaglomerular cells to release renin. Renin converts angiotensinogen to angiotensin I, ACE turns that into angiotensin II, and angiotensin II does three critical things: it constricts efferent arterioles to maintain GFR, it triggers aldosterone release from the adrenal cortex, and it stimulates ADH release from the posterior pituitary. That single cascade controls blood pressure, sodium balance, and water retention simultaneously. Understanding how these pieces fit together is what separates people who pass from people who actually understand the system. Acid-base balance is another area where beginners struggle. The kidneys regulate pH by reabsorbing bicarbonate and excreting hydrogen ions, primarily in the proximal tubule and collecting duct. It's not as simple as just filtering acid out. The process involves carbonic anhydrase, glutamine metabolism in the proximal tubule producing ammonium, and titratable acid excretion. If your guide doesn't cover the chloride-bicarbonate exchanger in the distal nephron, you're missing something important for understanding metabolic alkalosis and compensation.
Common Mistakes That Show Up on Exams
One thing I noticed repeatedly when tutoring is that students confuse the roles of ADH and aldosterone. ADH acts on the collecting ducts to increase water permeability through aquaporin-2 channels. Aldosterone acts on the principal cells of the DCT and collecting duct to increase sodium reabsorption and potassium secretion. They work together but through completely different mechanisms. When exam questions describe a patient with low blood volume and high potassium, the answer involves aldosterone, not ADH. Mixing those up costs easy points. Another frequent error involves the countercurrent multiplier. Students memorize that the ascending limb is impermeable to water and actively transports sodium out, but they don't always grasp why this creates the medullary osmotic gradient. The key insight is that the descending limb passively loses water to the hypertonic medulla, concentrating the filtrate as it goes down, while the ascending limb dilutes the filtrate as it pumps salt out without losing water. This separation of salt and water transport in adjacent limbs running in opposite directions is what makes the whole system work. Without that understanding, you can't explain how the kidney produces concentrated urine or what happens in diabetes insipidus. Loop diuretics are a good test of this concept. Furosemide blocks the Na-K-2Cl cotransporter in the thick ascending limb, which disrupts the countercurrent mechanism and reduces the medullary gradient. This means the collecting duct can't concentrate urine even with ADH present. The result is massive water loss. I once had a student who couldn't connect a drug mechanism to a physiological principle until we walked through it step by step, starting from the transporter protein and ending with the clinical presentation. That kind of integrated thinking is what a good study guide should push you toward.
Get the Full Details
What Most Guides Leave Out
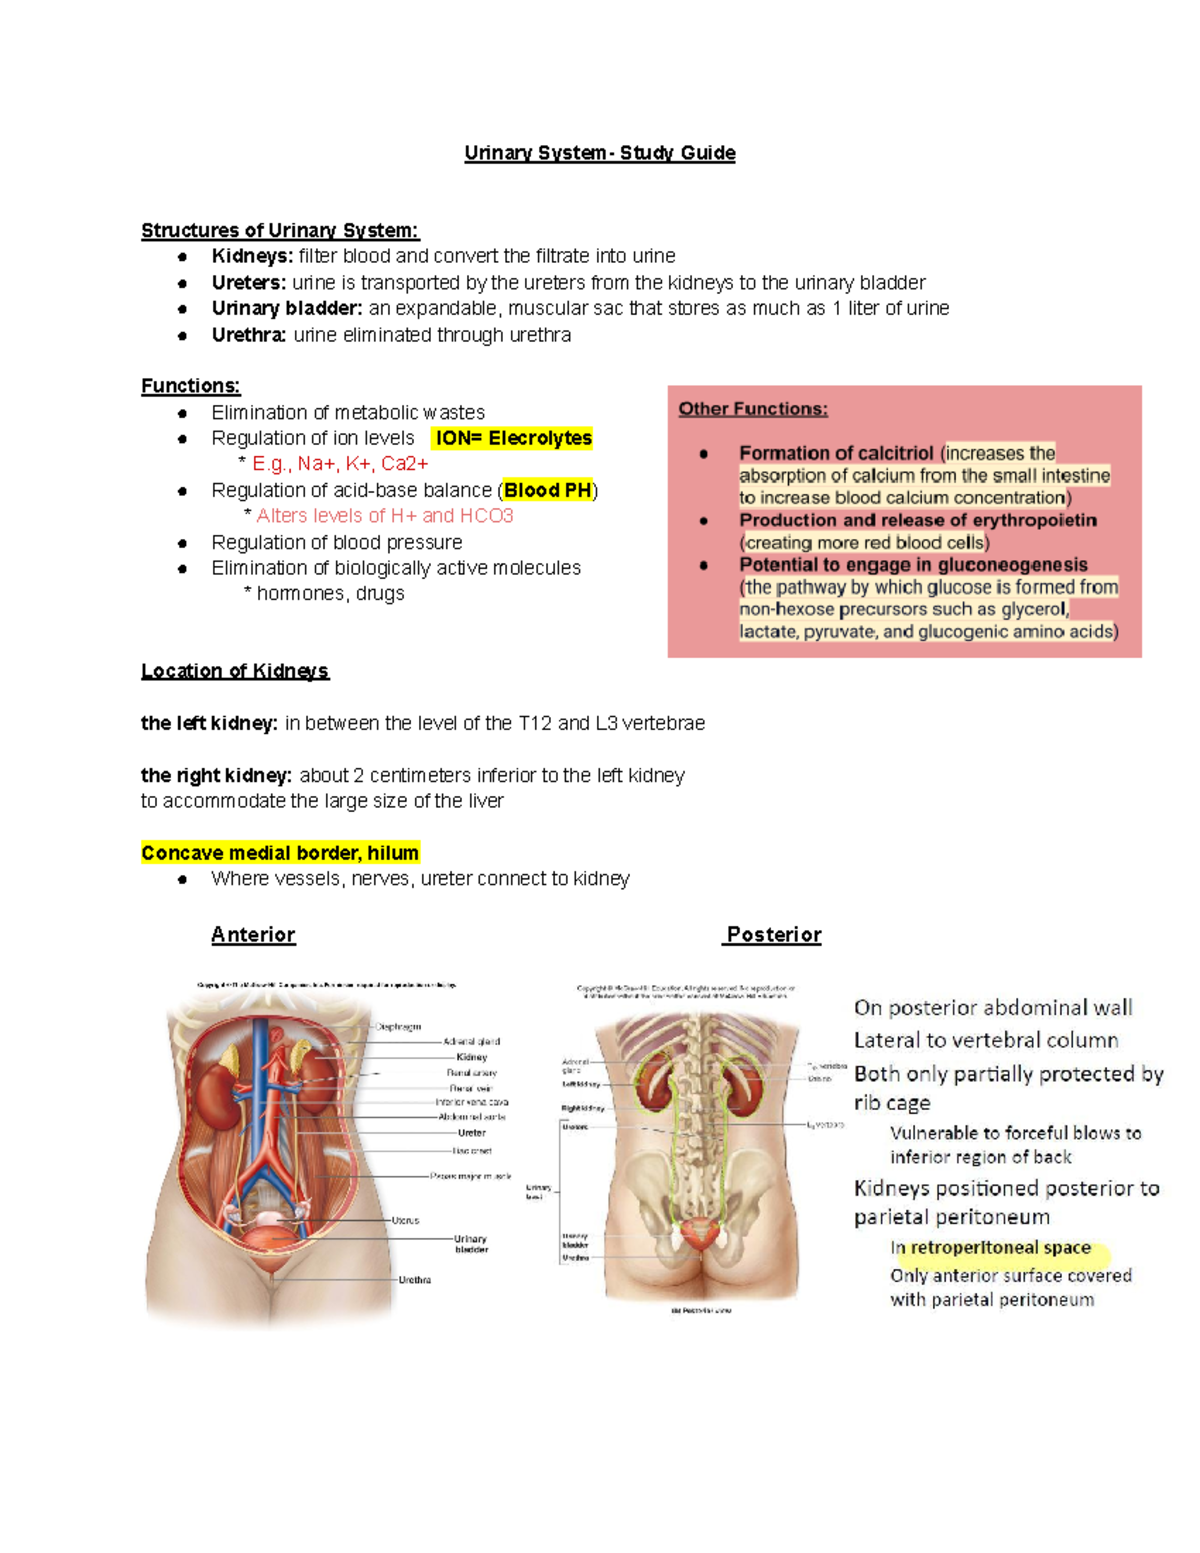
The bladder and urethra get very little attention in most resources, but they matter. The detrusor muscle is smooth muscle controlled by the autonomic nervous system. Parasympathetic stimulation causes contraction and urination. Sympathetic stimulation causes relaxation and urine storage. The external urethral sphincter is skeletal muscle under voluntary control. If you're studying neurogenic bladder or spinal cord injuries, these details become critical, and they're often missing from standard guides. Renal blood flow is another topic that deserves more space. The kidneys receive about 20 to 25 percent of cardiac output despite being only a small fraction of body mass. This high flow rate is necessary for the filtration function, but it also means the kidneys are vulnerable to changes in perfusion pressure. Autoregulation maintains relatively constant GFR across a mean arterial pressure range of about 80 to 180 mmHg through myogenic mechanisms and tubuloglomerular feedback. When autoregulation fails, as in severe hypotension or chronic hypertension, kidney damage follows quickly. There's also the endocrine function of the kidneys that gets shortchanged. Erythropoietin production, vitamin D activation, and renin secretion are all renal functions beyond filtration. In patients with chronic kidney disease, the loss of erythropoietin leads to anemia, and the failure to activate vitamin D causes secondary hyperparathyroidism and bone disease. These clinical correlations make the material feel less abstract and more relevant to real practice.
How to Use This Material Effectively
Flashcards have their place, but they're limited for a system this interconnected. I found that active recall through diagram labeling and explaining concepts out loud works far better. Draw the nephron, label it, then explain the entire process of urine formation from filtration to excretion without looking at anything. If you stumble, that's your gap. Do this daily for a week and your retention improves dramatically. Past exam questions are invaluable. They reveal what instructors consider important and expose the patterns in how questions are framed. Many questions test your ability to predict what happens when a specific variable changes, like what happens to GFR if the afferent arteriole constricts. Working through these scenarios builds the kind of reasoning skills that rote memorization never will. If you're preparing for a clinical exam, focus more on pathophysiology and pharmacology. Understanding normal function is necessary but not sufficient. Know how acute tubular necrosis differs from prerenal azotemia. Know the mechanism and side effects of common diuretics. Know the laboratory patterns in renal tubular acidosis types one, two, and four. These distinctions are where exams tend to separate the prepared from the rest.
A Note on Resources
There are a lot of study guides out there, and not all of them are reliable. Some oversimplify to the point of being misleading, especially on topics like the renin-angiotensin system where the details matter. I'd recommend cross-referencing whatever resource you use with a standard textbook like Guyton and Hall or Boron and Boulpaep for more depth. Online resources like Khan Academy and Osmosis have solid videos, but they sometimes skip the quantitative aspects that show up on harder exams. If you're looking for a comprehensive Urinary System Study Guide that covers both the foundational physiology and the clinical applications, you'll want something that integrates these elements rather than treating them separately. The material is dense, but it's also one of the more coherent systems in the body once you see how the pieces connect. The initial investment in understanding the framework pays off across multiple exam topics and clinical scenarios.