Why Most People Get This Wrong
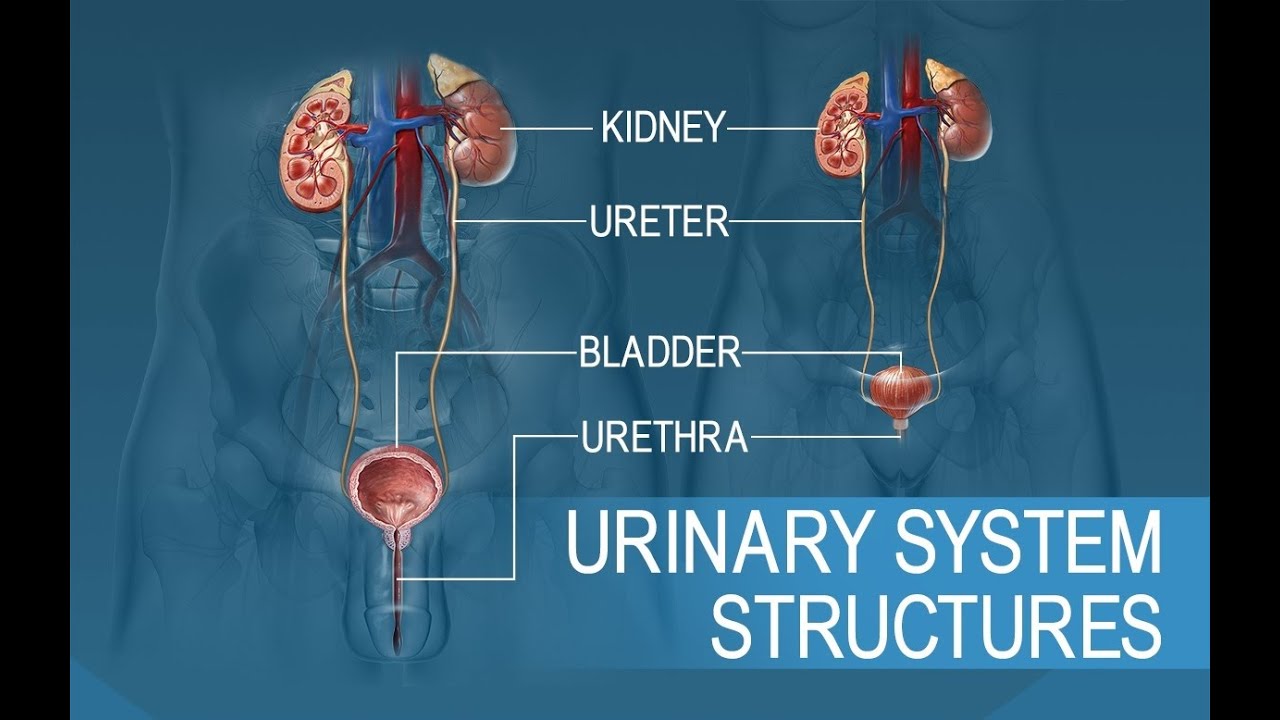
The urinary tract is one of those systems that looks simple on paper and completely falls apart when you try to actually work with it. You have kidneys that filter blood, ureters that transport urine down, a bladder that stores it, and a urethra that gets it out. That's the diagram version. The real version involves autonomic innervation patterns that change everything about how we think about surgery, imaging anomalies that show up constantly in cross-sectional scans, and a couple of anatomical variants that will make a urologist's life miserable if you don't catch them beforehand. I spent years reading CT urograms and doing laparoscopic dissections before I stopped second-guessing myself on basic ureteral anatomy. The problem isn't that the textbook is wrong. It's that the textbook assumes a standard patient, and standard patients don't really exist in clinical practice.
Urinary Tract Anatomy And Physiology In Practice
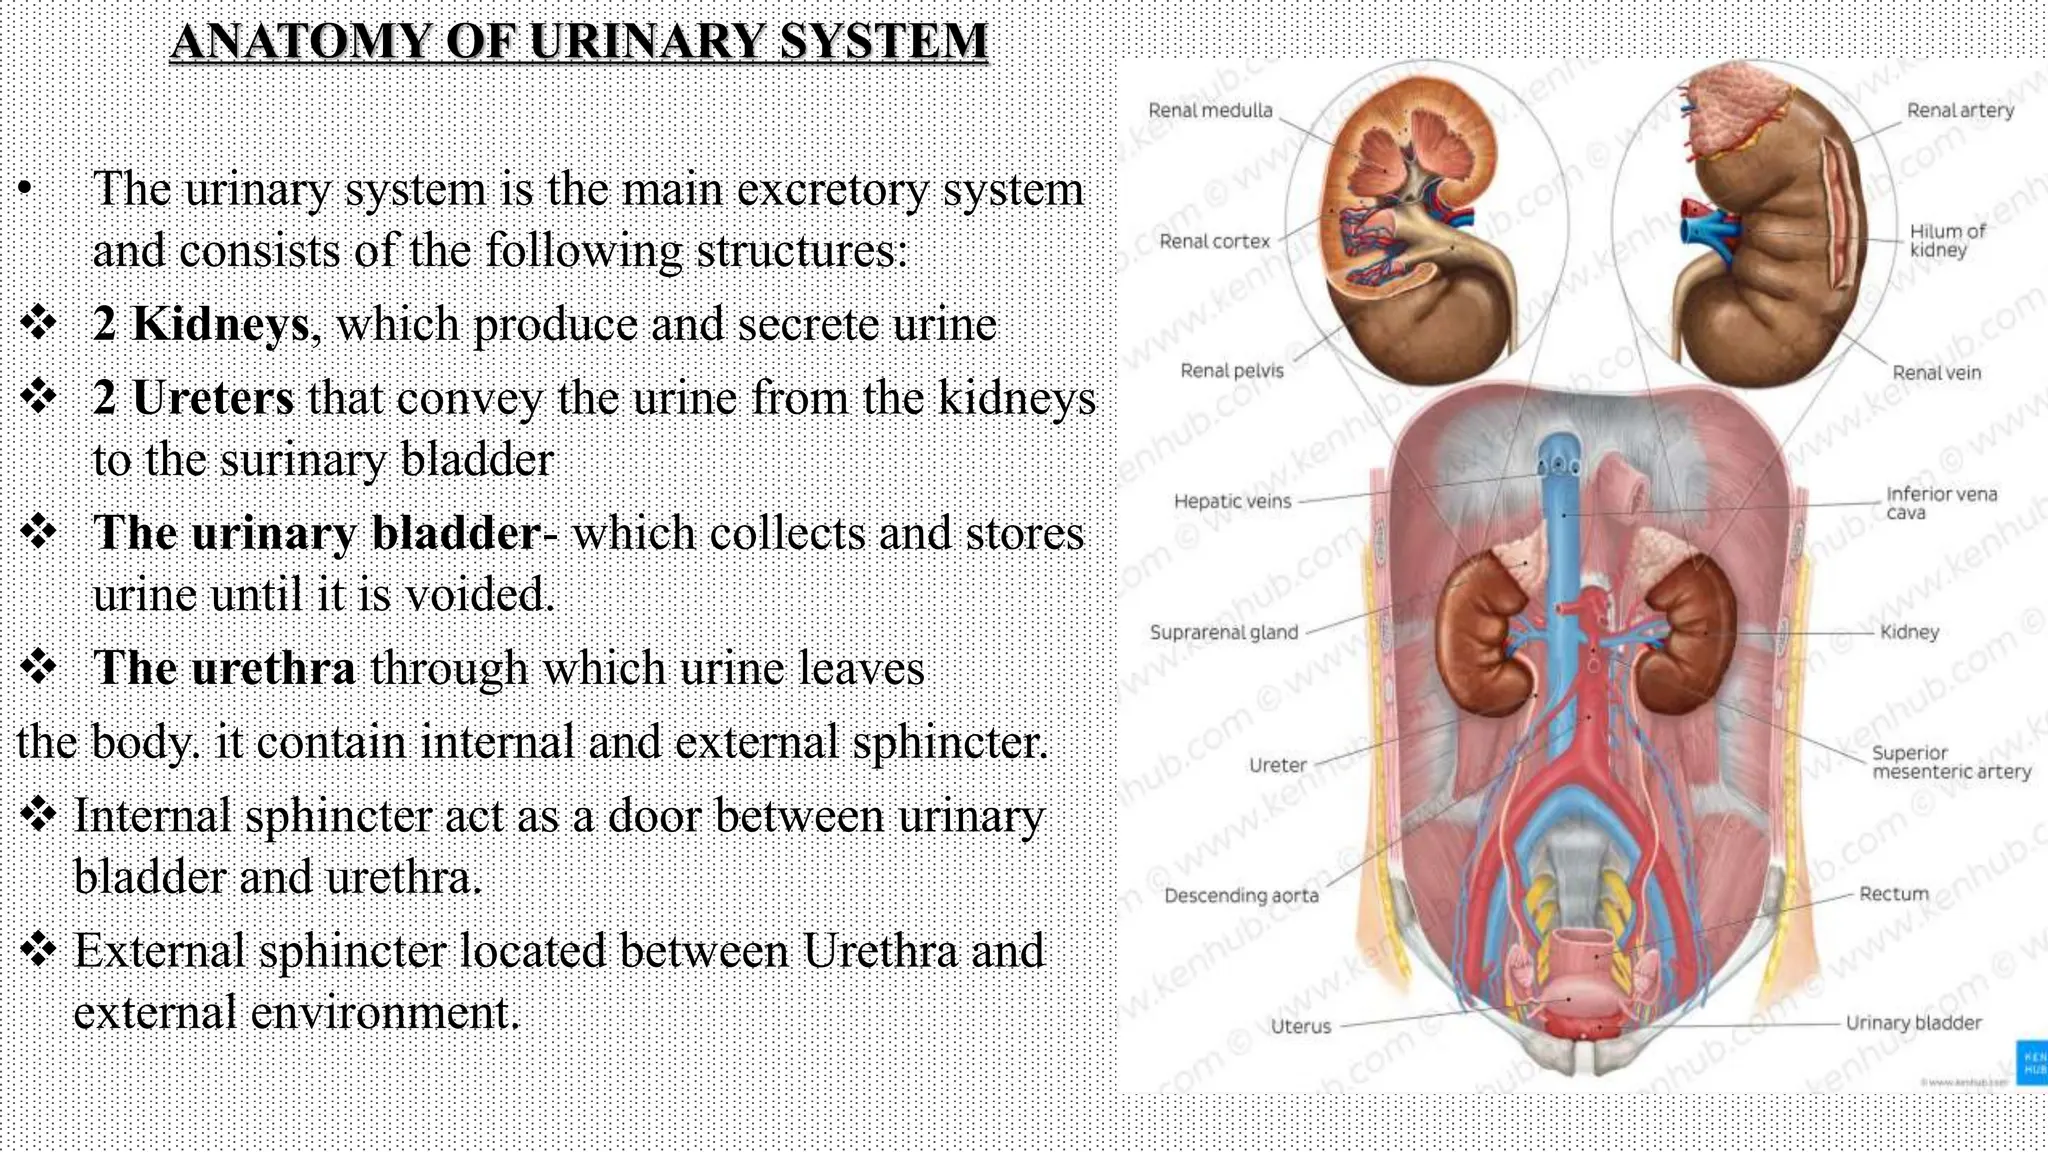
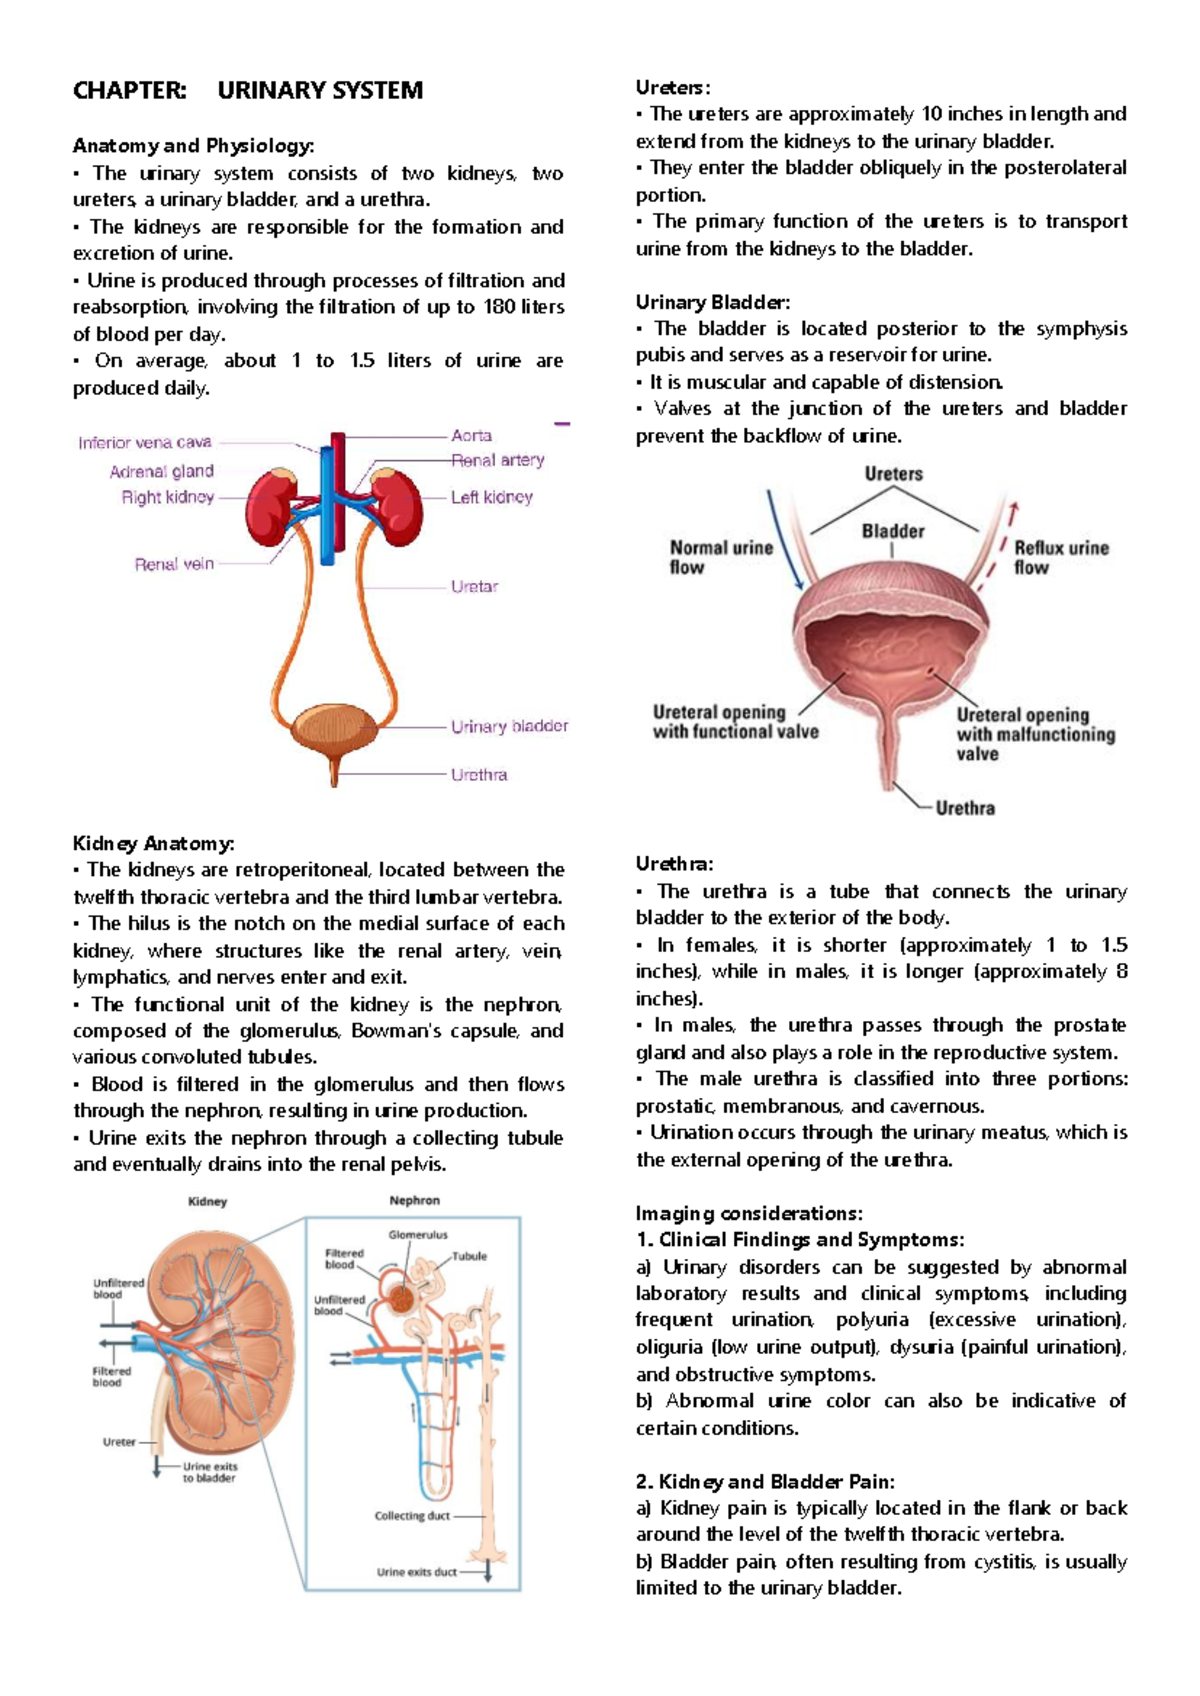
Let's talk about the kidneys first because this is where most people stop paying attention but should start. The renal hilum structures from anterior to posterior in roughly 90 percent of people: renal vein, renal artery, renal pelvis. That's the VAN sequence. Memorize it. But here's what they don't tell you — in about 8 to 10 percent of cases, there's an accessory or duplicated renal artery, and those accessory arteries often take a posterior or inferior course that doesn't follow the standard pattern. If you're planning any renal surgery or even a nephrectomy and you skip a preoperative CT angiogram, you're flying blind. I lost count of the number of times I've seen an accessory vessel get clamped or torn because someone assumed standard anatomy. In laparoscopic cases specifically, these aberrant vessels are the reason bleeding happens when you thought you had a clean plane. The renal blood supply itself deserves more attention than it gets. Segmental arteries branch off the main renal artery before it enters the hilum, and each segment is a vascular territory with relatively little collateral flow between adjacent segments. This matters enormously if you're doing partial nephrectomy. The anterior and posterior divisions feed different poles, and understanding which segmental branch goes where can mean the difference between saving functional parenchyma and removing too much. There's also the issue of early branching — sometimes the upper polar artery arises directly from the aorta or the main renal artery trunk rather than from a properly formed segmental branch. These variations aren't rare enough to ignore.
The Ureters Are Where Things Get Complicated
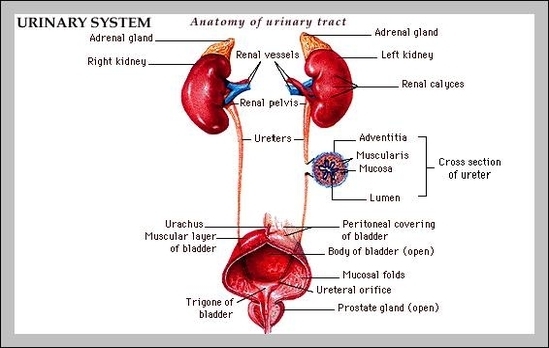
The ureter is roughly 25 to 30 centimeters long and has three natural points of narrowing. These are clinically significant because they're where stones tend to get stuck. The ureteropelvic junction at the renal pelvis, the point where the ureter crosses the iliac vessels at the pelvic brim, and the ureterovesical junction where it enters the bladder wall. The UVJ is the narrowest point at about 1 to 2 millimeters in diameter, which is why small stones that pass the other two locations often cause the most pain at that final segment. Here's something most people miss: the ureter has a dual blood supply. The upper third gets its blood from the renal artery, the middle third from the gonadal arteries and the abdominal aorta directly, and the lower third from branches of the internal iliac system, primarily the superior vesical artery. This matters surgically because if you're doing a pelvic operation and you clamp or ligate vessels carelessly in the retroperitoneum, you can compromise ureteral perfusion and create an ischemic stricture weeks or months later. The ureter looks fine during surgery. The damage is done at the microvascular level. I saw a case once where a patient presented six months after a hysterectomy with flank pain and a dilated upper ureter. The stricture was at the pelvic brim, exactly where the surgeon had used energy devices close to the ureter. No direct injury during the operation, but the thermal damage affected the blood supply. That's a delayed presentation that nobody caught immediately. The relationship of the ureter to surrounding structures is also a minefield. On the right side, the ureter crosses the bifurcation of the common iliac artery and runs posterior to the ovary in females or the vas deferens in males. On the left side, it crosses the bifurcation of the common iliac near the sigmoid mesocolon attachment. During pelvic lymph node dissections, the ureter is easily injured here because it's tucked up against the pelvic sidewall. The standard teaching is to identify the ureter before dissecting anything in the pelvic sidewall region, but in obese patients or in reoperative fields where anatomy is scarred, that identification becomes significantly harder. I use intraoperative fluorescein — inject it IV and look for green fluorescence under white light — and it reliably shows the ureter within 30 seconds. This trick alone has prevented more ureteral injuries than any amount of careful dissection.
Get the Full Details

The Bladder And What Actually Matters About It
The bladder is a smooth muscle organ, and that smooth muscle is called the detrusor. But the innervation is the part people get wrong. Parasympathetic fibers from S2 through S4 travel via the pelvic splanchnic nerves to the inferior hypogastric plexus and then to the bladder wall. These cause contraction. Sympathetic fibers from T11 through L2 travel through the hypogastric nerve and cause relaxation of the detrusor and contraction of the trigone and internal sphincter. Somatomotor fibers from S2 through S4 also go to the external urethral sphincter via the pudendal nerve for voluntary control. Damage to any of these pathways produces a different type of urinary dysfunction, and the pattern of dysfunction tells you exactly where the lesion is. When I'm evaluating a postoperative patient who can't void, the first question isn't about catheterization. It's about which nerves were manipulated during surgery. A low anterior resection puts the superior hypogastric plexus at risk. A radical prostatectomy can damage the pelvic plexus. A hysterectomy can affect the pelvic splanchnic nerves. The type of urinary retention — areful with overflow incontinence versus a flaccid bladder with no sensation — points to different levels of injury. This matters because the treatment is different. Anticholinergics help one pattern and make the other worse. Getting the innervation wrong means treating the symptom instead of the cause. The trigone is a specific region of the bladder base where the two ureters enter and the urethra exits. It's smooth, triangular, and relatively fixed compared to the rest of the bladder mucosa, which is highly folded and distensible. The trigone has a different embryological origin — it comes from the absorbed mesonephric ducts — which is why it has distinct smooth muscle organization and why it's the preferred site for certain bladder procedures. During cystoscopy, the trigone landmarks help you orient yourself immediately. The ureteral orifices are the key reference points. If you see them, you know where you are. If you can't find them, you need to consider that they might be obstructed, retracted by tumor, or in an abnormal position due to prior surgery.
The Urethra — Short Version, Lots of Clinical Relevance
The male urethra is about 20 centimeters long and divided into anterior and posterior segments. The posterior urethra includes the prostatic and membranous portions, and this is where the internal sphincter mechanism resides. The anterior urethra includes the bulbar and penile portions. Straddle injuries typically affect the bulbar urethra. Pelvic fracture urethral injuries typically affect the membranous urethra. Knowing which portion is involved changes the entire management approach. A proximal injury needs retrograde urethrography first. A distal injury might be managed with primary repair or stenting depending on the extent. The female urethra is roughly 4 centimeters long and runs from the bladder neck to the external meatus anterior to the vagina. The proximity to the vagina matters for two reasons. First, short urethras mean higher rates of ascending urinary tract infection — this is the anatomical reason women get UTIs far more frequently than men. Second, the periurethral glands and the Skene's glands around the distal urethra are sometimes involved in female urinary incontinence surgery. During sling procedures, placement too far laterally can injure the urethral sphincter mechanism, and placement too medially doesn't provide adequate support. The sweet spot is millimeters wide, which is why experience matters more than reading about the technique.
The Renal Physiology Side — What You Actually Need To Know
The glomerular filtration rate in a healthy adult is about 125 milliliters per minute, which translates to roughly 180 liters per day. The vast majority of that filtrate is reabsorbed. The proximal convoluted tubule handles about 65 percent of sodium and water reabsorption plus most of the glucose and amino acids. The loop of Henle creates the medullary concentration gradient through countercurrent multiplication. The distal tubule and collecting duct are where fine-tuning happens under hormonal control — aldosterone affects sodium reabsorption and potassium secretion, antidiuretic hormone affects water permeability. This isn't academic. When you're managing a patient with acute kidney injury or chronic kidney disease, understanding which segment is affected tells you what's reversible and what isn't. The tubuloglomerular feedback mechanism is one of those things that sounds simple but is actually quite elegant. The macula densa cells in the distal tubule sense sodium chloride concentration in the tubular fluid. If flow rate is high, sodium delivery is high, and the macula densa signals afferent arteriolar constriction to reduce GFR. If flow is low, the opposite happens. This keeps GFR relatively stable despite blood pressure fluctuations. But it breaks down in diabetes because the hyperfiltration state chronically overwhelms this mechanism. Over years, that's how diabetic nephropathy progresses. The initial hyperfiltration is adaptive but ultimately damaging.
A Real Problem I Ran Into
I had a patient with recurrent pyelonephritis and a normal cystogram, normal cystoscopy, and a normal retrograde pyelogram. Everything looked standard. We weren't finding the source of the infections. It turned out the patient had a congenital duplication of the right collecting system with a complete duplicated ureter — two ureters on one side. The upper pole moiety drained through a Weigert-Meyers rule situation, meaning the upper pole ureter inserted inferiorly and medially, below the lower pole ureter's insertion. This created a reflux channel that standard imaging had missed because the radiologist was looking for a single ureteral jet and assuming absence of reflux meant normal anatomy. The workaround was a dedicated MRI urography with thick-slice coronal reformats that showed both ureters and their insertion points clearly. That changed the surgical plan entirely. Instead of a simple ureteral reimplant, the patient needed a ureteroureterostomy to recombine the duplicated system before reimplanting into the bladder. This kind of duplication is present in about 1 in 1,200 people and is more common in women. Standard ultrasound and even standard CT can miss it if you're not specifically looking for two separate collecting systems. The lesson here isn't that imaging is unreliable — it's that you need to know what question to ask the imaging. "Is there hydronephrosis?" is the wrong question. "Show me every ureteral insertion and every collecting system on both sides" is the right one when you have unexplained recurrent infections.
What This Means For Imaging And Procedures
If you're interpreting renal ultrasounds, the key landmark is the hepatorenal recess on the right and the splenorenal recess on the left for identifying the kidneys in fluid-sensitive sequences. Renal parenchymal thickness should be about 1.5 to 2.5 centimeters. Thinner than that suggests chronic medical kidney disease. thicker than that can suggest infiltrative processes or early obstruction. The renal sinus fat increases with age and obesity, which can make the parenchyma appear artificially thinned on ultrasound if you're not accounting for it. For CT urography, the protocol matters. Non-contrast phase for stones, nephrographic phase for parenchymal lesions, and excretory phase for collecting system evaluation. Skipping the non-contrast phase means you'll miss radiolucent stones or undercharacterize calcifications. Skipping the excretory phase means you'll miss ureteral lesions. I've seen both happen when protocols are abbreviated to save time, and both lead to missed diagnoses. A complete CT urogram takes about 10 minutes of scanner time and provides more diagnostic information than half a dozen other imaging studies combined.
The Bottom Line On What Actually Works
Understanding urinary tract anatomy and physiology isn't about memorizing the textbook diagrams. It's about knowing where the variations are, where the injuries happen, and what the downstream consequences are when things go wrong. The renal hilum anatomy is standard in most people but the variations are common enough to require preoperative imaging. The ureteral blood supply is segmental and easily compromised during pelvic surgery. The bladder innervation patterns determine the type of dysfunction you'll see after nerve-sparing procedures fail. The urethral anatomy differs dramatically between sexes and dictates entirely different management strategies for trauma. The physiology side follows the same principle. GFR numbers are useful but the segmental function — what each part of the nephron actually does and what happens when it fails — is what guides clinical decisions. Proximal tubule damage presents differently from distal tubule damage. Glomerular disease presents differently from vascular disease. Knowing the difference between these patterns saves time and prevents misdiagnosis. The one thing I'd emphasize most is that the urinary tract doesn't behave like most other organ systems when it comes to compensation. The kidneys can maintain homeostasis with significantly reduced function because of the large functional reserve. But once you lose that reserve, decline is rapid and often irreversible. Same with the ureters — they can maintain drainage despite partial obstruction for a while, but prolonged partial obstruction causes permanent damage that you won't notice until the patient presents with elevated creatinine. Early recognition based on anatomical and physiological understanding is the only real preventive strategy available.