Setting Up Urodynamics Studies Without Losing Your Mind
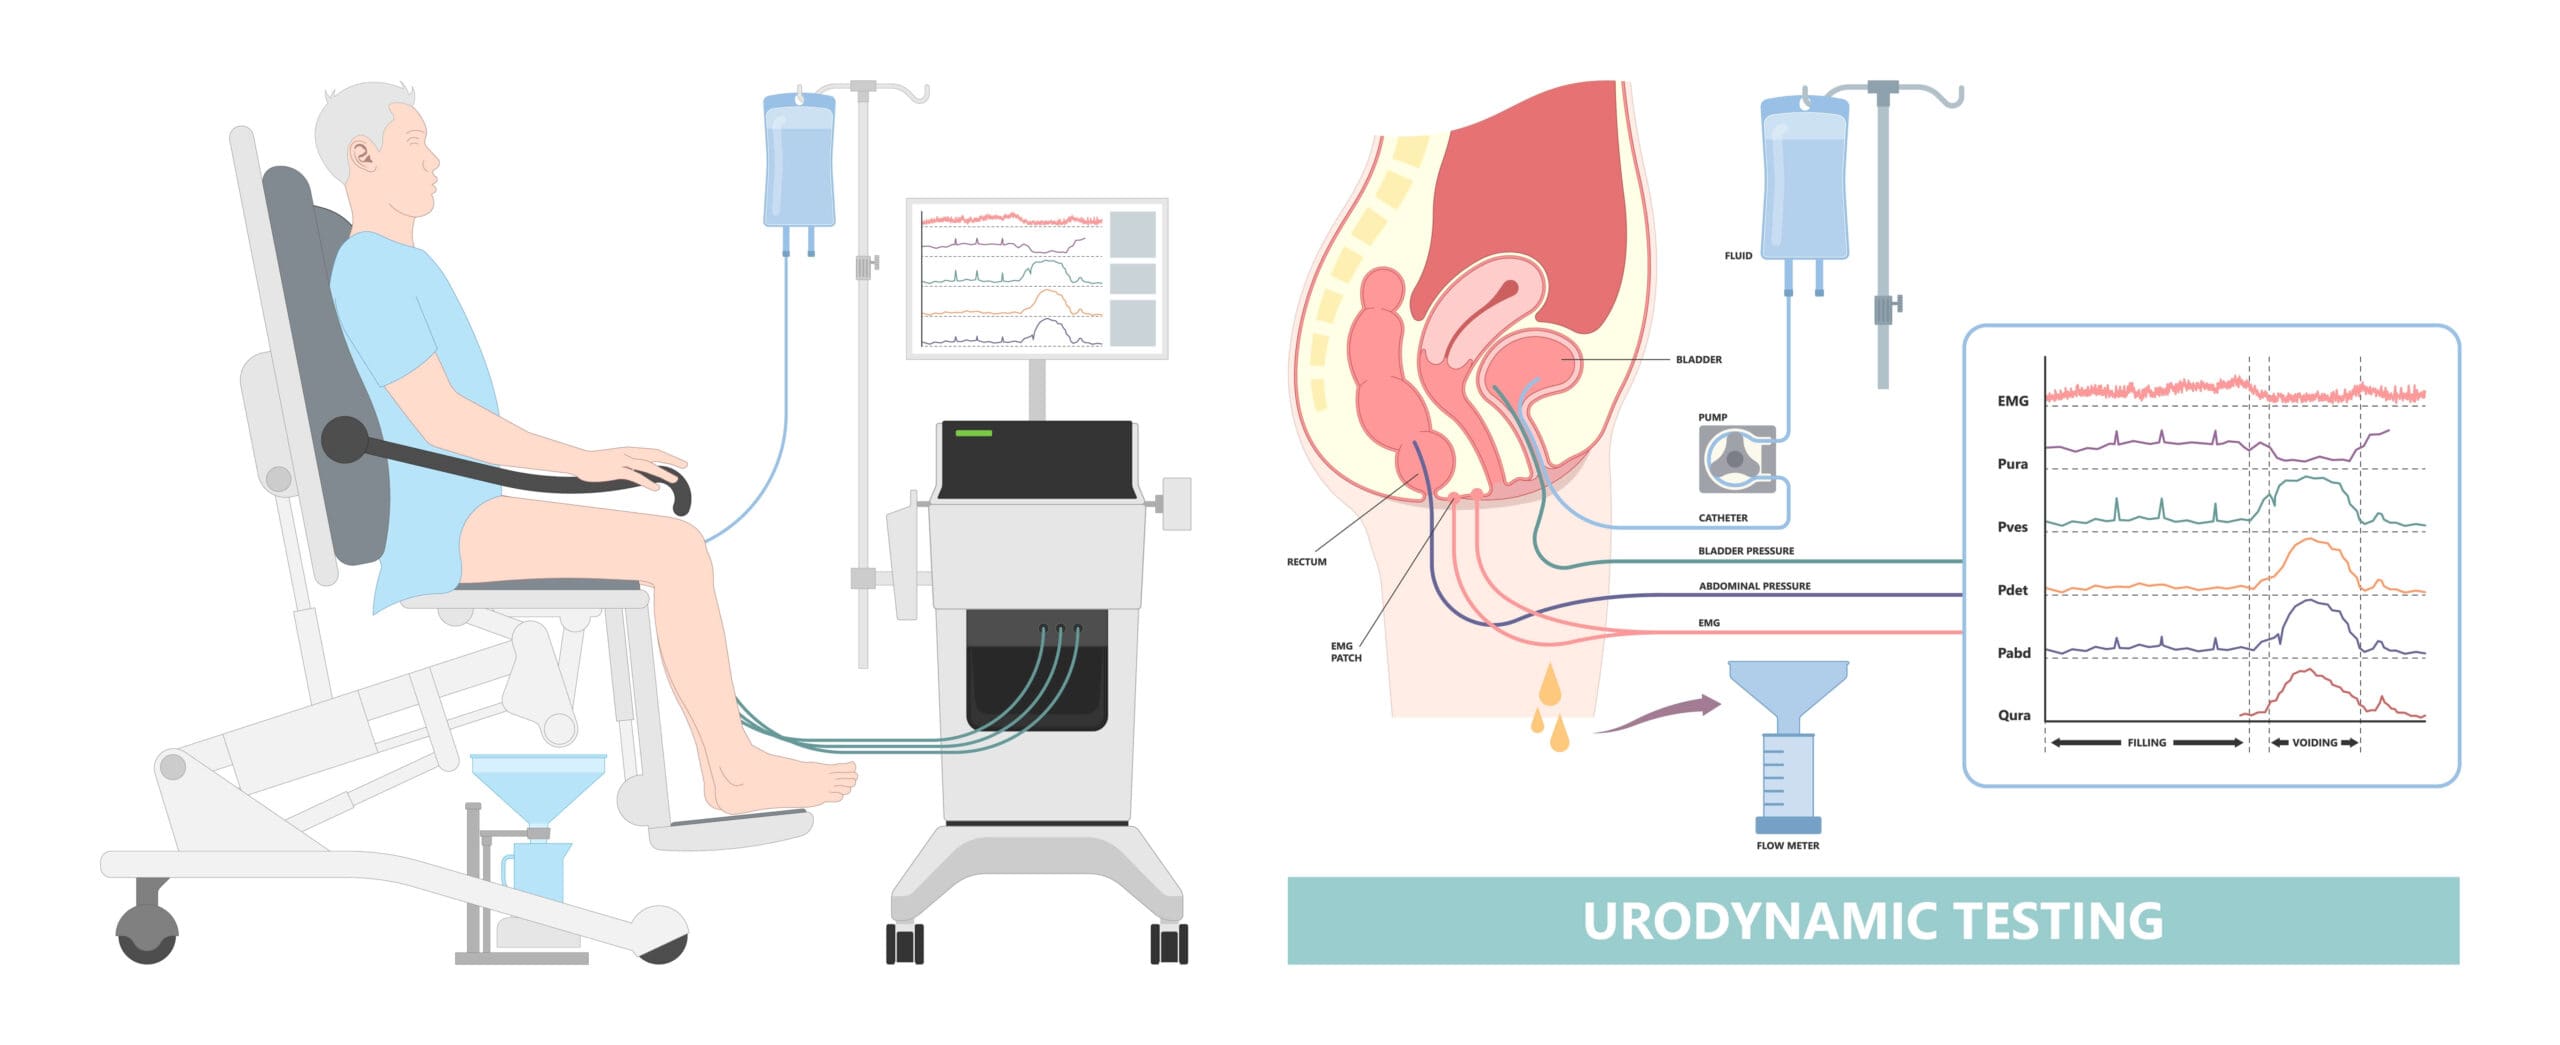
Most nursing programs don't cover urodynamics properly. You'll be thrown into the suite with a manometry system and told to figure it out. I learned the hard way that reading the manual isn't enough. Here's what actually works when you're running your first few studies solo. The core workflow starts before the patient even lies down. You need to verify calibration on both pressure transducers. Zero them to atmospheric pressure with the reference valve open. If you skip this step, your detrusor pressure calculations will be off by several centimeters of water and no one will catch it until the urologist reviews the tracings. I once had a resident question a voiding profile because the bladder pressure looked artificially elevated. It took twenty minutes to realize the reference line had disconnected during patient positioning. The recalibration took thirty seconds. Don't neglect the pre-study checklist.
Essential Urodynamics Training For Nurses Who Are Learning on the Job
There's a difference between knowing the steps and knowing the sequence that actually produces usable data. A standard urodynamic study combines cystometry, pressure-flow analysis, and often uroflowmetry. As the nurse, your job is catheter insertion, transducer setup, filling, and monitoring throughout. The physician interprets. That's the textbook version. The real version involves managing patient discomfort while keeping the recording continuous, troubleshooting artifact from muscle tension, and knowing when to stop and restart rather than salvage a bad tracing. Catheter selection matters more than people admit. A double-lumen catheter for the bladder and a single-lumen or specialized rectal catheter for abdominal pressure is standard. The rectal probe measures intra-abdominal pressure so you can subtract it from vesical pressure to get true detrusor pressure. I used to think the rectal catheter was optional for basic studies. That changed when I was covering a practice that saw a lot of female patients with pelvic floor dyssynergia. Without the abdominal pressure channel, you can't differentiate between high detrusor pressure and artifact from straining. The studies become uninterpretable. Factor in roughly fifteen to twenty extra minutes for proper placement, but the interpretability gain is significant. Infusion rate is another thing that gets glossed over. Most protocols use 50 to 100 milliliters per minute for standard cystometry. Slower rates are used for urodynamically sensitive patients. The problem is that if you're filling manually with a syringe, your rate fluctuates. A pump is better. But even with a pump, check the actual flow by watching the meniscus in thegraduated collection bag during the first few minutes. I've seen pumps deliver at half the set rate because of a kinked line that wasn't visible. You'll miss the real-time sensation change if your filling is slower than expected. The patient's first detrusor contraction might arrive at 400 milliliters instead of 200, and you won't know why until you review the volume column afterward.
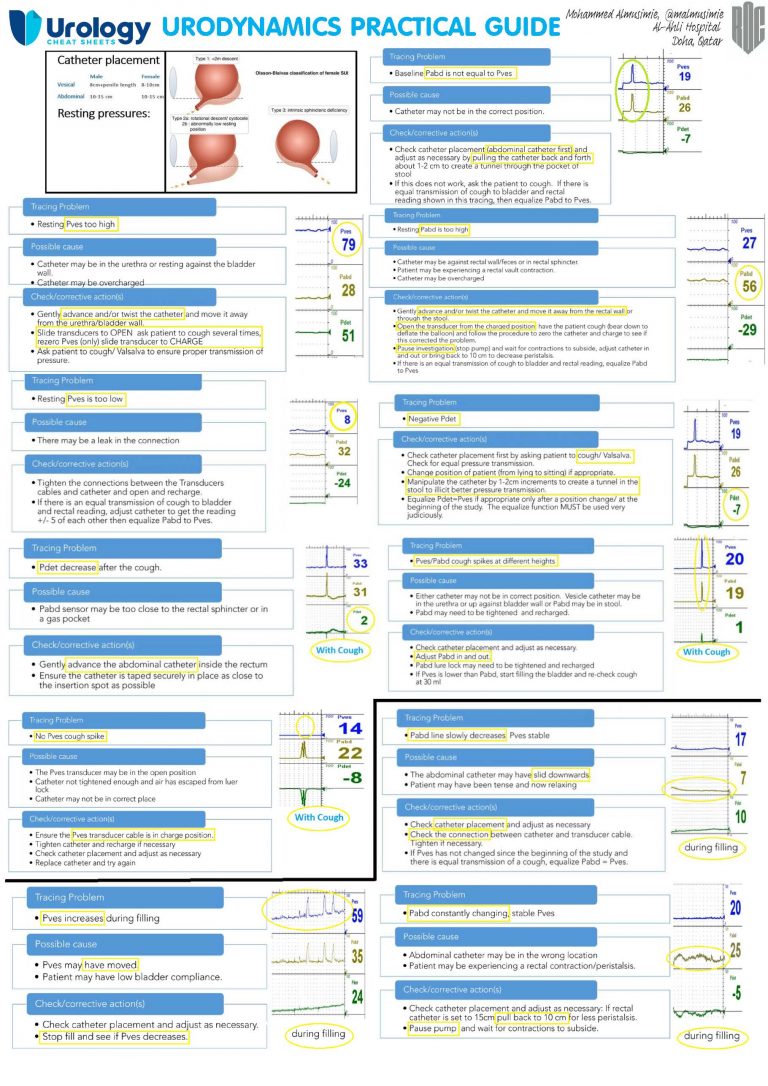
Artifact management is where most new nurses struggle. Movement, coughing, and pelvic floor tension create noise on the tracings. The trick isn't to eliminate it entirely. You can't. It's to recognize it in real time and document what was happening. If the patient coughs during filling, make a note on the tracing. If they're tense, pause and talk them through relaxation before continuing. I had a patient whose baseline pressure was riding 25 centimeters of water above zero due to chronic pelvic floor hypertonicity. The first reading I took looked like pathologic pressure. I spent five minutes getting her to breathe and re-zeroed the system with her in the relaxed position. The difference was night and day. That kind of patience saves studies. Documentation requirements are stricter than they used to be. Every phase needs timestamps, volumes instilled, patient-reported sensations, and observed voiding parameters. The standard International Continence Society terminology should be used consistently. If your facility has its own template, learn it inside out. I once had a study returned for inadequate documentation because I hadn't recorded the first sensation volume separately from the normal desire volume. Two distinct data points that both matter for diagnosis. One form field doesn't capture that nuance. Write them out as separate entries. When you're ready for formal training, look for programs accredited by the American Urological Association or the International Continence Society. These typically run one to three days depending on depth. Some hospital systems run internal fellowship-style rotations that span several weeks. The shorter courses teach you the mechanics. The longer ones teach you the exceptions. If your practice does a high volume of complex cases, the extended option is worth the time investment. You'll encounter conditions like spinal cord injury patients, post-radiation bladders, and neurogenic detrusor overactivity where the standard protocols need modification. Standard training doesn't always address these scenarios adequately.
Get the Full Details

There are also simulated training modules available from major urodynamics equipment manufacturers. Urotron, urotrac, and Laborie all offer software-based simulators that let you practice tracing interpretation without a live patient. I found these useful for building pattern recognition. You can see normal, abnormal, and artifact tracings side by side and train your eye to spot the difference. It won't replace hands-on experience, but it reduces the learning curve by maybe a week of actual clinic time. One thing nobody tells you about this work is the physical component. You're standing for hours, often in a cramped suite. The equipment is heavy and awkward to reposition. I developed shoulder pain after my first month before realizing I was holding the pressure transducer assembly at an awkward angle during long studies. Adjusting my stance and using a rolling stool made a noticeable difference. It's a small detail that affects your ability to stay focused during the later parts of a study when errors are most likely. The compensation for this skill set is real but uneven. Nurses with certified urodynamics credentials often see a pay premium, especially in academic centers and large urology practices. Some facilities require the credential for promotion. Others just list it as preferred and never enforce it. Check what your specific workplace values before investing heavily in certification. The Certificate in Urodynamics from the AUA costs a few hundred dollars plus travel time if the course isn't virtual. Budget accordingly.
If you're starting out, don't try to master everything at once. Learn the setup. Learn the calibration. Learn to recognize a clean tracing from a dirty one. The interpretation skills come with repetition. The first thirty studies will feel slow and uncertain. By study fifty, you'll be running them without thinking about the steps. That's the actual timeline. Not three weeks, not two months. About two to three months of regular exposure before it clicks.