Understanding the Us Army Physical Therapy Program
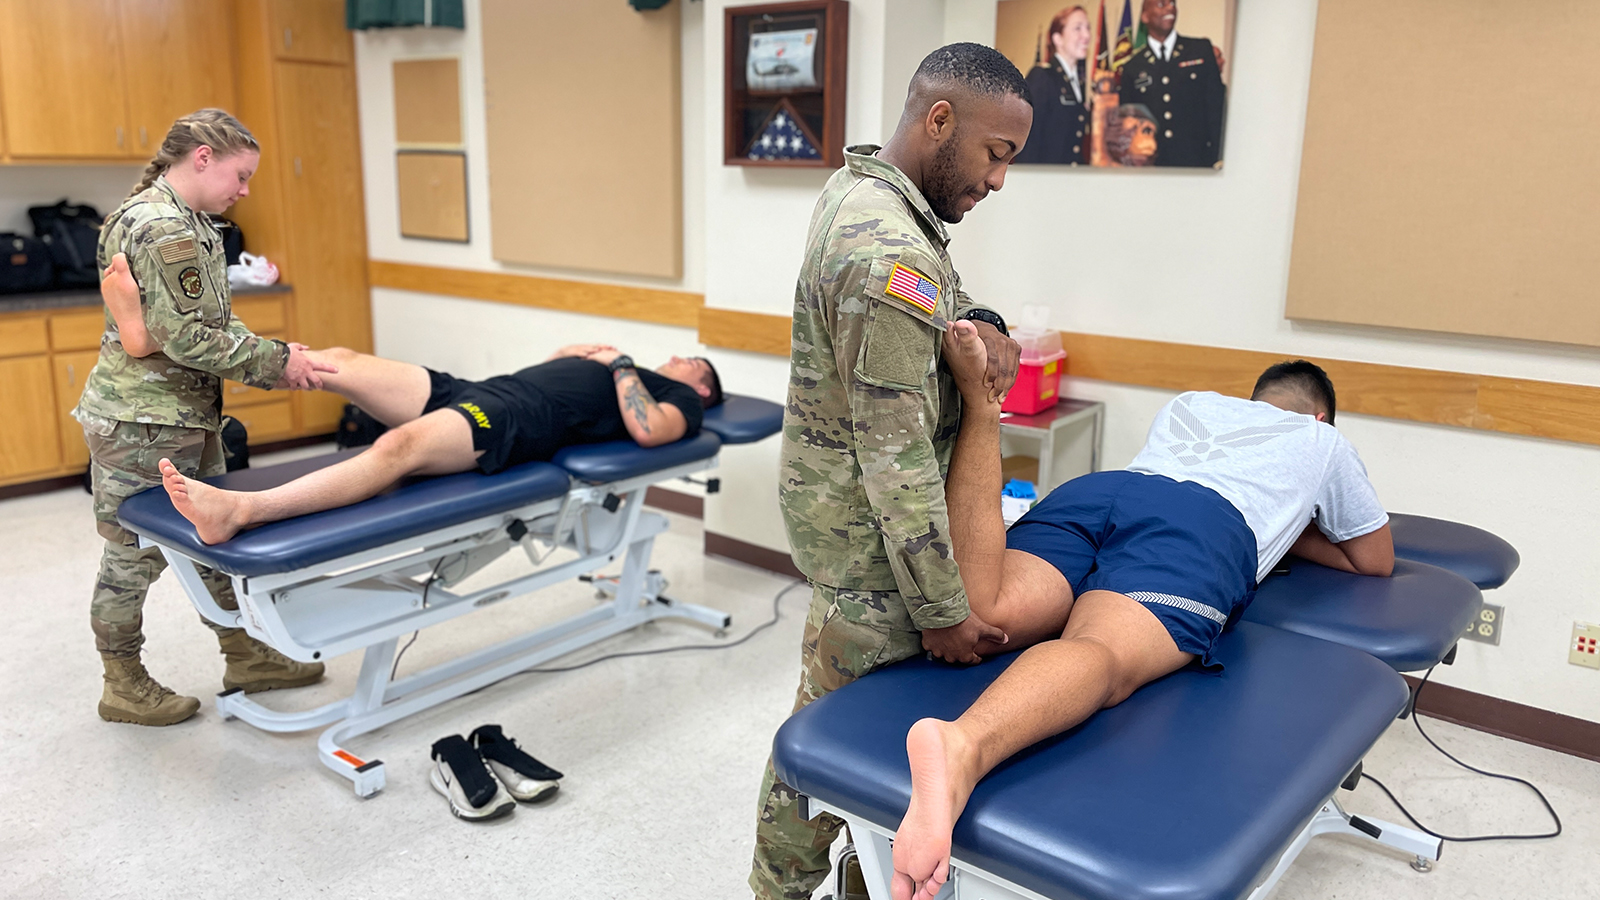
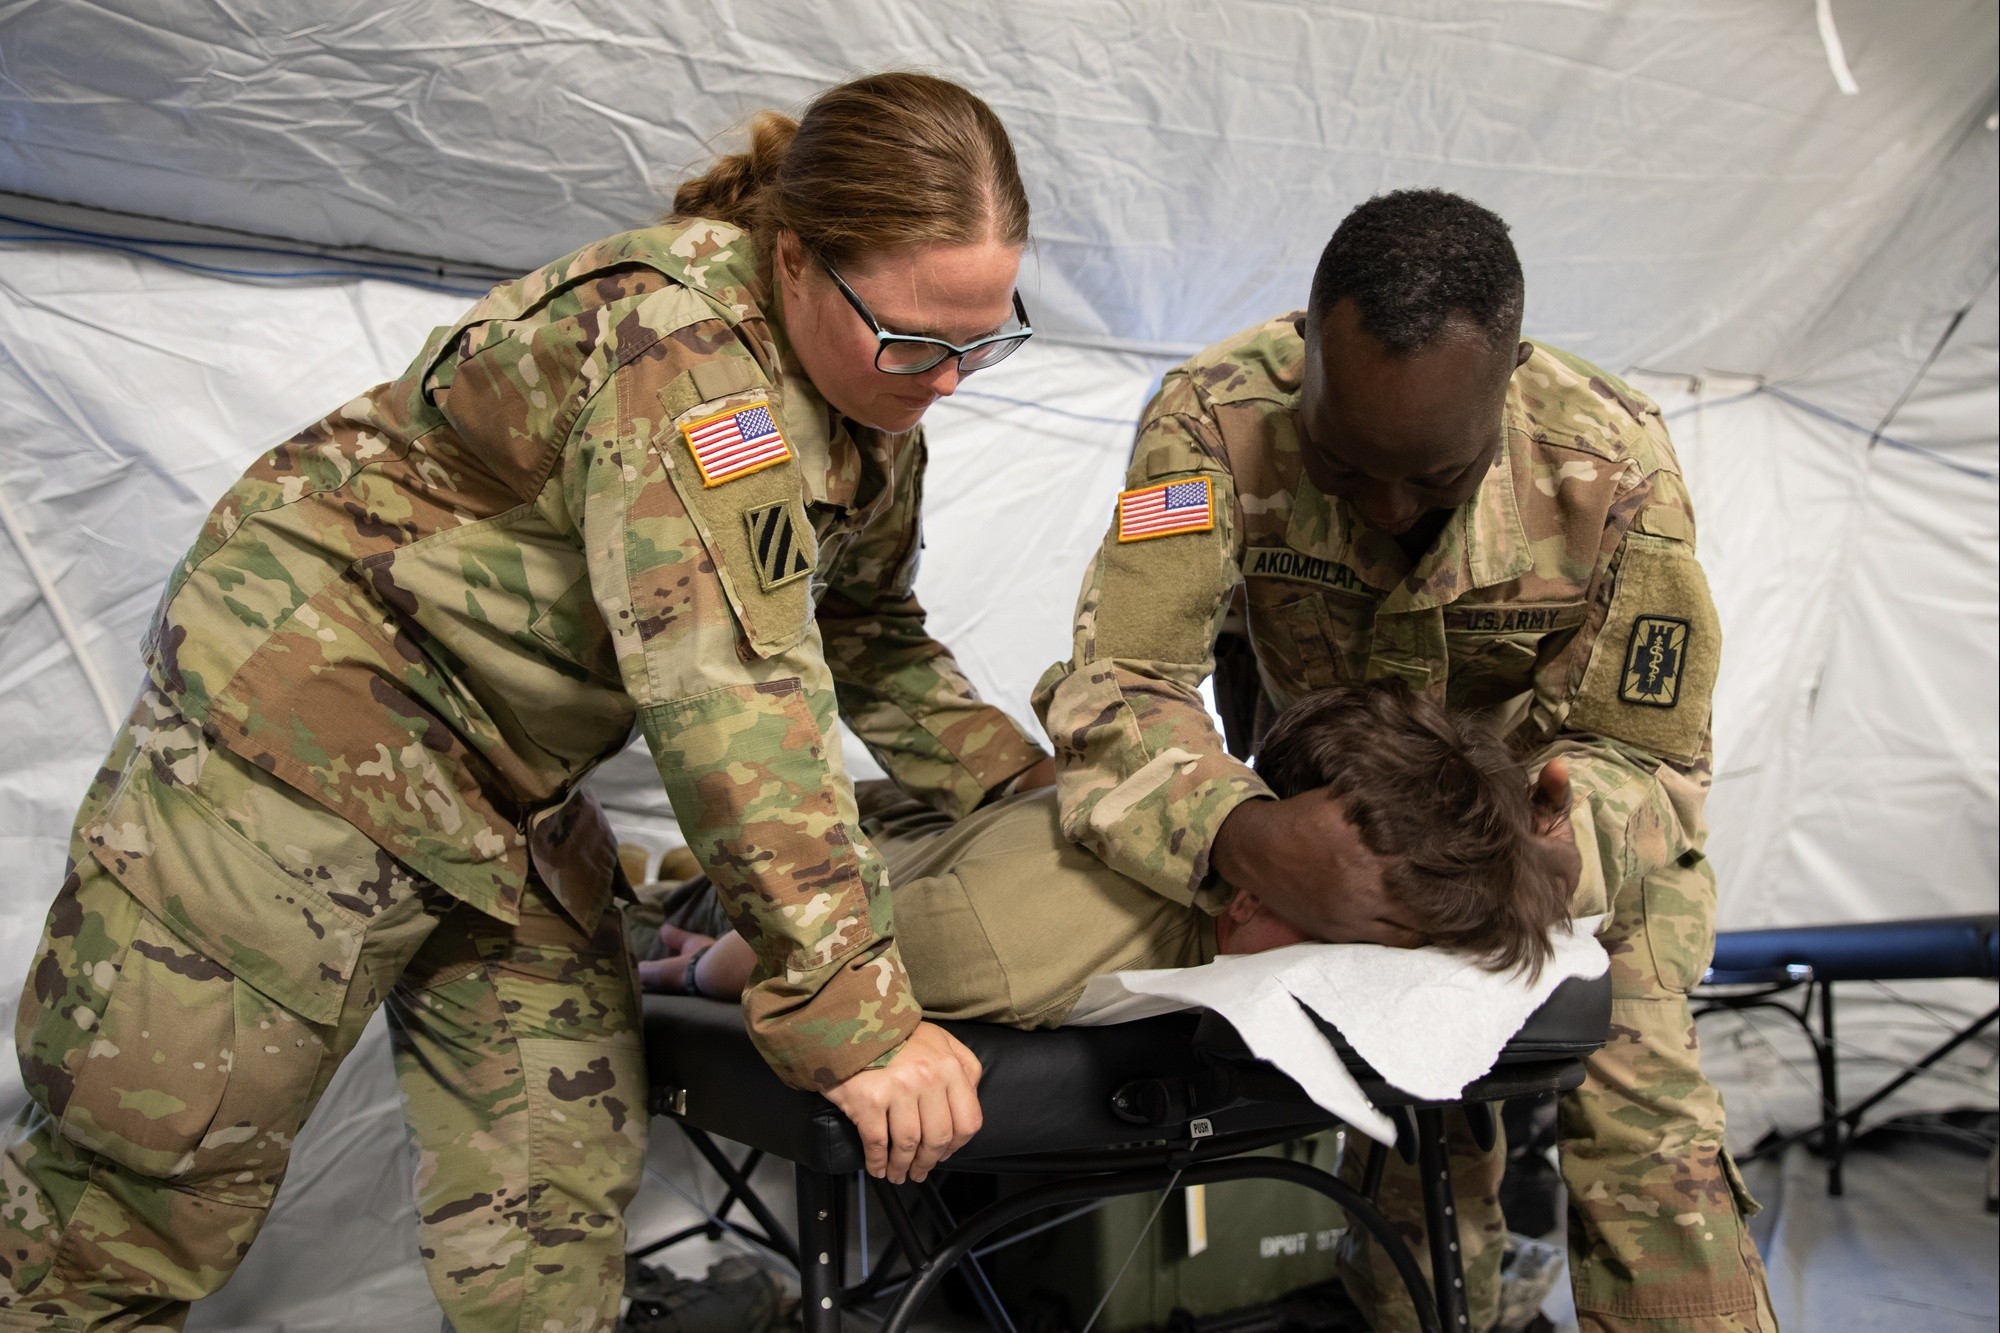
The Us Army Physical Therapy Program is the standardized framework that military healthcare providers use to manage rehabilitation and return-to-duty processes for soldiers. It's not a single piece of software you download — it's a combination of clinical protocols, documentation systems, and functional testing batteries that run through Military Health System facilities. If you're trying to navigate this as a civilian contractor, a new PT working at a MTF, or even a soldier trying to understand your own rehab timeline, the system can feel opaque because the documentation requirements are dense and the workflows shift between installations. At its core, the program ties into the Electronic Health Record system — specifically the Army's implementation through HealtheLife and the underlying AHLTA/AMISY infrastructure at most installations. Physical therapists document evaluations, progress notes, and discharge summaries using standardized templates. The functional testing piece is where most people get tripped up. You're expected to use validated instruments like the Functional Movement Screen, balance error scoring systems, isokinetic testing when available, and the Army's own fitness assessment correlations. I remember working a case a few years back where a soldier came in with a complicated lumbar radiculopathy. The protocol wanted me to push through the standard return-to-duty clearance battery, but his symptoms flared whenever he hit certain movement patterns. The workaround was straightforward once I knew it existed: I documented the modified protocol under the physician's deviation authority, flagged it in the record with a clear medical rationale, and coordinated with the ortho team to adjust the timeline. The system actually allows this, but the documentation has to be airtight or you come back for reviews. That's the part nobody tells you upfront — the audit trail matters more than the clinical outcome in a lot of cases.
Documentation Requirements and Common Pitfalls
The documentation side is where the program gets heavy. You need to capture initial evaluation, re-evaluation at specified intervals, plan of care changes, and eventual discharge or transition to another level of care. Each note needs to tie back to functional goals that connect to duty limitations. The common mistake I see is writing notes that describe what the soldier did in the clinic rather than what the intervention means for their operational readiness. reviewers can spot that distinction immediately and it delays everything. Another thing beginners miss is the relationship between the physical therapy record and the disability evaluation system. If a soldier's condition might lead to a medical board referral, your documentation becomes part of that legal process. I've seen notes that were clinically accurate but legally ambiguous because they used informal language. Stick to objective findings, standardized terminology, and measurable outcomes. It's less frustrating for everyone downstream. The program does have real limitations. Not every installation has access to isokinetic dynamometry or advanced gait analysis, so the quality of functional testing varies. Some protocols assume equipment and staffing levels that simply don't exist at smaller clinics. When that happens, you document the limitation and use the best available alternative, but that adds another layer of paperwork. There's no way around it.
What You Actually Need to Access the System
If you're a military PT or a civilian contractor working at an MTF, you'll need a CAC or PIV card, access through the DoD's identity management system, and training on the specific EHR platform used at your installation. There's no public download for the clinical documentation software — it's locked behind military credentialing. You'll go through your clinic's education officer for onboarding modules. The timeline for full access runs anywhere from two to six weeks depending on your clearance level and the installation's IT workload. Civilians outside the system who need to understand a soldier's therapy progress typically do so through the patient or the chain of command. There's no self-service portal for families or independent providers to pull records. That's a HIPAA and DoD privacy boundary that doesn't bend.
Get the Full Details

The Functional Testing Side
The testing battery isn't arbitrary. It's designed to correlate with the Army Combat Fitness Test and the physical demands of specific MOS jobs. A mechanic with a shoulder injury gets treated differently than a medic with the same injury because the duty requirements diverge. The therapist has to understand that mapping, which means knowing the duty profiles, not just the anatomy. I've watched experienced therapists fumble this part because they focused exclusively on tissue healing and forgot to factor in what the soldier actually has to do once they're back. Timing is another variable. The standard PT episode for musculoskeletal conditions in the Army environment typically runs anywhere from six to twelve weeks for straightforward cases. Complex cases with surgical intervention or multiple comorbidities can stretch much longer, and that's where the program's re-evaluation checkpoints become critical. Missing those scheduled re-evals creates gaps in the record that administrators flag during audits. The program works when you respect the documentation requirements as much as the clinical work. It's not the most elegant system, but it's consistent, and consistency is what keeps soldiers healthy and installations compliant. That's really all there is to it.