What Actually Gets Tested
Biostatistics on the USMLE isn't about deriving formulas from scratch. It's about recognizing study designs and applying the right interpretation under time pressure. Most students lose points because they misread what the question is asking, not because they don't know the math. I spent three hours one night going through NBME blocks and realized half the "hard" biostats questions were just testing whether you could distinguish between PPV and NPV when given different prevalence rates. The math itself takes about ten seconds if you know it. The trap is always in the wording. Start with sensitivity and specificity. These are intrinsic to the test. They don't change with disease prevalence. A test with 90% sensitivity catches 90% of people who actually have the disease. Specificity means 90% of healthy people test negative. Simple enough. Now move to positive predictive value and negative predictive value. These flip entirely based on how common the disease is in the population you're testing. That's where students get burned on exam day. Likelihood ratios are your best friend here. LR+ equals sensitivity divided by one minus specificity. LR- equals one minus sensitivity divided by specificity. If LR+ is greater than 10, the test result substantially increases the probability of disease. If LR- is less than 0.1, it substantially decreases it. You don't need to calculate these from raw numbers during the exam. Recognize that a highly sensitive test is designed to rule out disease, and a highly specific test is designed to rule it in. Snout and spin. Sensitive tests have high NPV in low-prevalence populations.
For confidence intervals, remember that if the interval crosses the null value, the result is not statistically significant at that alpha level. For odds ratios and relative risks, the null is 1. For mean differences, the null is 0. This single rule handles most CI questions without any calculation.
Usmle Biostatistics Cheat Sheet
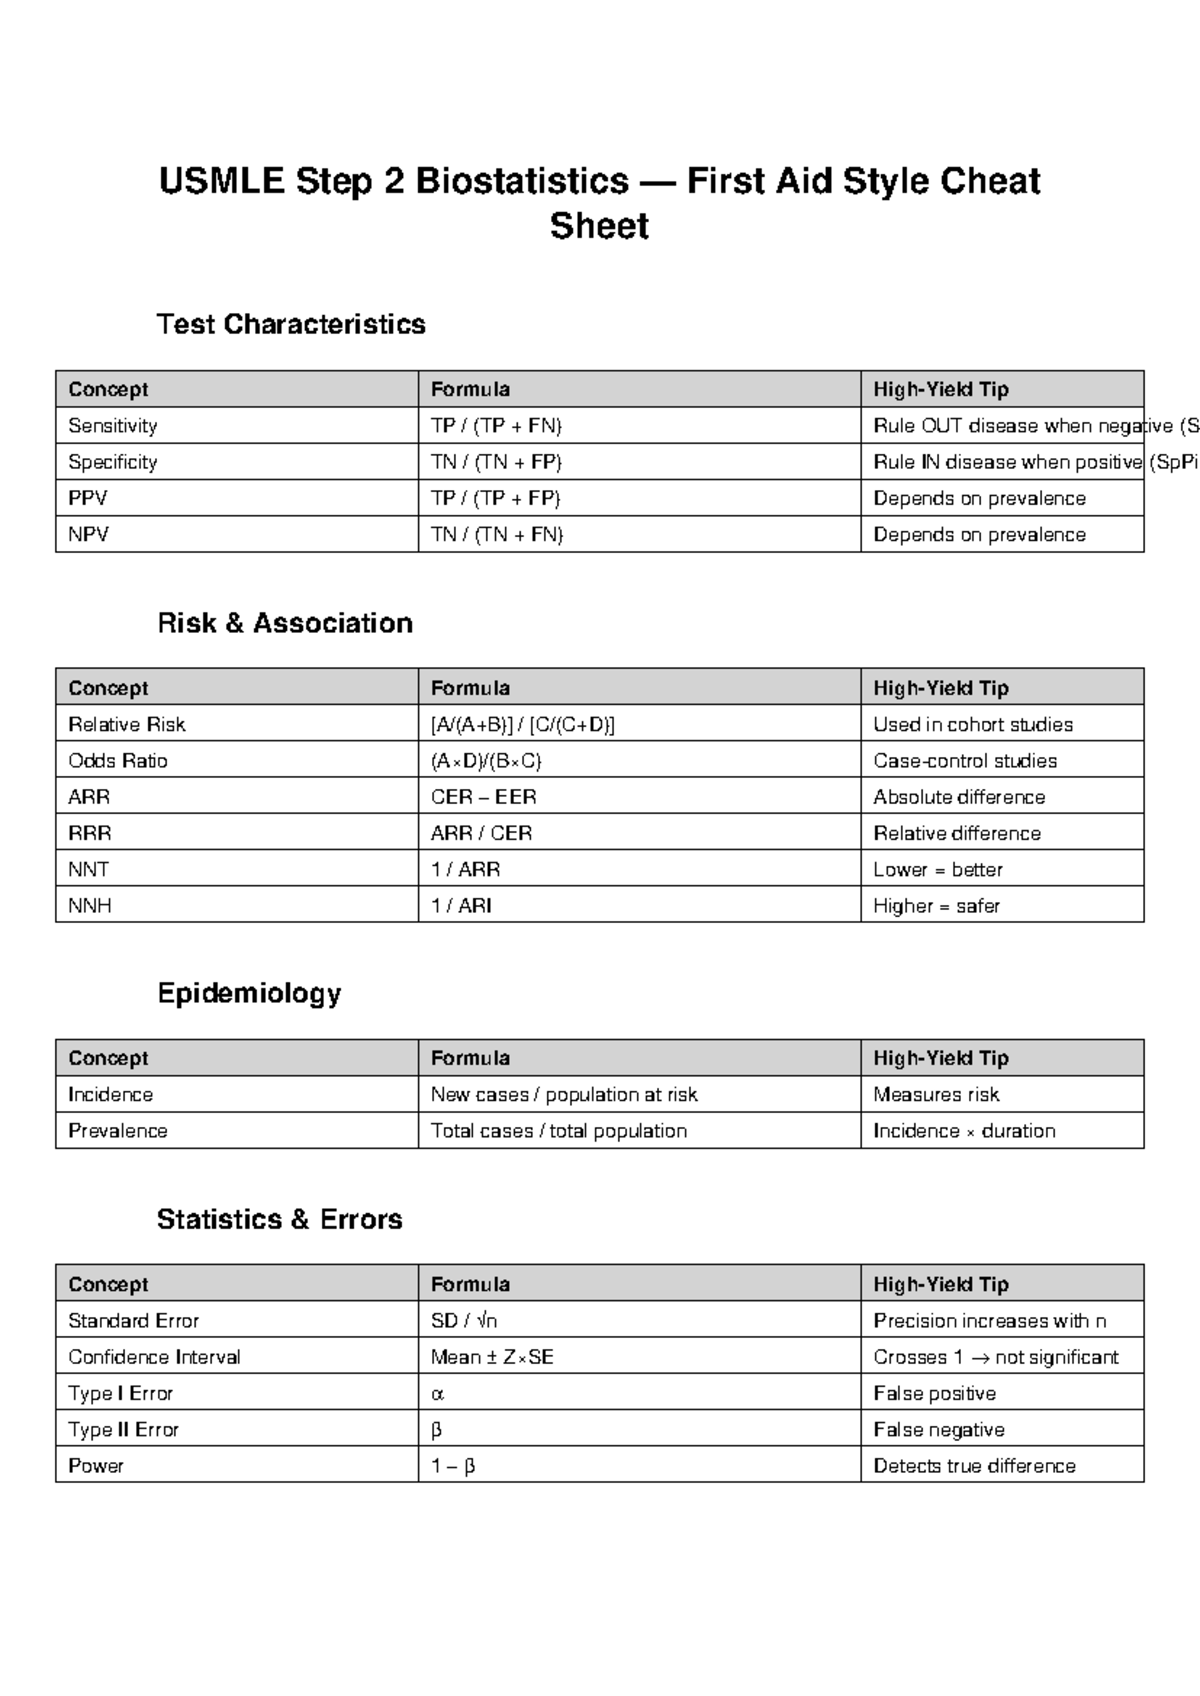
Here's what I actually kept on my one-page reference during the last two weeks of prep. Everything below is distilled from questions I got wrong and NBME explanations I re-read until they stopped confusing me. Diagnostic accuracy framework: sensitivity equals true positives over true positives plus false negatives. Specificity equals true negatives over true negatives plus false positives. PPV equals true positives over true positives plus false positives. NPV equals true negatives over true negatives plus false negatives. Positive likelihood ratio equals sensitivity over one minus specificity. Negative likelihood ratio equals one minus sensitivity over specificity. These four formulas handle roughly 60% of biostats questions on the exam. Study design quick guide: case-control studies calculate odds ratios. Cohort studies calculate relative risk. Randomized controlled trials give you the strongest evidence for causation but only when blinding and randomization are properly described. Cross-sectional studies give you prevalence, not incidence. Ecological studies are the weakest observational design and the NBME loves to punish students who generalize from them.
Get the Full Details

Statistical testing: type I error is alpha, the false positive rate. Type II error is beta, the false negative rate. Power equals one minus beta. When the NBME asks about increasing power, the answer is almost always increasing sample size, increasing effect size, or using a paired design when appropriate. P-values below 0.05 are conventionally significant, but the NBME sometimes gives you a p-value of 0.06 and asks whether you'd reject the null. You wouldn't. Don't overthink it. Regression basics: linear regression gives you a slope and intercept. Correlation coefficient r ranges from negative one to positive one. R-squared tells you the proportion of variance explained. The NBME will show you a scatterplot and ask whether the correlation is strong, weak, positive, or negative. Draw a line through the points in your head. Up and to the right means positive. Tight clustering means strong. Bias and confounding: selection bias happens when the study population doesn't represent the target population. Recall bias is huge in case-control studies because cases remember exposures differently than controls. Confounding occurs when a third variable is associated with both the exposure and the outcome. You control for confounding in the analysis phase with stratification or multivariate regression, or in the design phase with randomization or restriction.
Number needed to treat equals one over absolute risk reduction. Absolute risk reduction is the control event rate minus the experimental event rate. If a drug reduces mortality from twenty percent to fifteen percent, the ARR is five percent and the NNT is twenty. Meaning you need to treat twenty people to prevent one adverse outcome. The NBME gives you these numbers constantly and expects you to compute NNT in under thirty seconds.
Where People Lose Points
The biggest trap I've seen repeatedly is prevalence blindness. Students will calculate PPV correctly using a formula but plug in the wrong prevalence because they misread which population the study was conducted in. A test with 95% sensitivity and 95% specificity has a PPV of only about 16% when disease prevalence is one percent. Same test, same numbers, completely different clinical interpretation. This showed up on my UWorld blocks at least four times with slight variations. Another common error involves mistaking association for causation in observational studies. The NBME will describe a study finding that coffee drinkers have higher rates of pancreatic cancer and then ask whether coffee causes cancer. The answer is no. Confounding by smoking is the classic example. Coffee drinkers smoke more. Smoking causes pancreatic cancer. The study shows association, not causation. You need a randomized trial or a Bradford Hill assessment to make causal claims, and even then, the NBME wants you to be conservative. I also encountered a genuinely tricky question once where they gave you a study with a p-value of 0.04 but a confidence interval that crossed the null. This is mathematically impossible with standard reporting, which means either the data is fabricated for the question or there's a mismatch in how the CI was constructed. In practice, I learned to flag this pattern and go with the p-value unless the question is specifically testing whether you notice the inconsistency. The NBME occasionally includes these as distractors to see if you're actually reading the numbers or just pattern-matching.

How to Actually Memorize This
Spaced repetition works, but only if your cards force you to apply the concepts rather than just recall definitions. A card that says "what is sensitivity?" is useless. A card that shows you a 2x2 table with filled-in numbers and asks "what is the PPV?" is what you need. I made Anki cards for every biostats question I got wrong, and I rewrote the explanation in my own words rather than copying the UWorld explanation verbatim. That process alone took longer than making the card but it stuck far better. The Usmle Biostatistics Cheat Sheet approach of building your own one-pager is worth doing even if you don't bring anything into the exam. The act of condensing everything into a single page forces you to identify what actually matters versus what you can ignore. I spent an afternoon trimming mine down from two pages to one, and each removal represented a concept I decided I didn't need to memorize cold. That's a useful filtering exercise in itself. Timing practice matters more than most students realize. Do a set of twenty biostats questions in forty-five minutes, timed. Not because the exam is that fast per question, but because you'll encounter biostats interspersed with other topics and you need to build the mental speed of recognizing the question type within three seconds of reading the stem. When I started doing timed sets, my biostats accuracy went from about seventy-two percent to eighty-nine percent in two weeks. The improvement wasn't from learning new material. It was from recognizing patterns faster and stopping myself from overthinking.
What This Approach Doesn't Cover
A cheat sheet won't help you with questions that require understanding the nuance of study design flaws. If the NBME describes a case-control study where the control group was selected from a hospital population with diseases related to the exposure, that's Berksonian bias and it's a favorite topic. No formula catches that. You have to understand the mechanism. Similarly, survival analysis questions involving Kaplan-Meier curves appear periodically and require interpreting censoring correctly. The cheat sheet can remind you that censored patients are still included in the denominator at the time of censoring, but it won't teach you how to read the graph quickly under pressure. The other gap is Bayesian reasoning. The NBME occasionally asks you to update disease probability after a test result using pre-test and post-test probabilities. Likelihood ratios get you most of the way there, but when they ask for a numerical post-test probability, you sometimes need to convert to odds, multiply by the LR, and convert back. This conversion step trips up students who only memorize the LR rule of thumb. I kept a small reference for the odds-to-probability conversion formula: probability equals odds divided by one plus odds. It's not glamorous but it saves thirty seconds per question and those seconds add up. If you're starting from zero on biostatistics, I'd recommend going through the Biostats 101 section on UWorld before relying on any cheat sheet. The explanations there are actually well-written and cover the edge cases that a one-page summary inevitably omits. The cheat sheet is a review tool, not a primary learning resource. Using it as one will leave gaps that show up on the actual exam.