
What Happened to Usmle Step 2 Cs
The USMLE Step 2 CS exam no longer exists. It was discontinued in March 2021 by the NBME and FSMB. If you're searching for current ways to prepare for it, you won't find anything official anymore. The exam that replaced its clinical skills assessment function is the Step 2 Clinical Skills (CS) replacement path, which varies depending on your licensing trajectory. I went through the Step 2 CS process back when it was still active. My experience was in 2018 at the Prometric center in Checkers Hill, Jamaica, which was one of the international test sites. The whole thing took about four hours from arrival to departure, and here's what actually happened during those four hours.
Understanding the Usmle Step 2 Cs Format
The exam had two main components. First was the Communication Skills section where you interacted with standardized patients — actors trained to portray specific clinical scenarios with scripted histories. You had about 15 minutes per patient encounter, plus a few minutes to document your findings and order workup. Second was the Organic Part of the exam where you took computer-based clinical vignette questions covering basic clinical science concepts. Roughly 50-60 questions in about an hour and a half. The communication portion scored three areas: integrated spoken English, interpersonal skills, and clinical integrity. They weren't looking for perfect accents or medical mastery at that stage. They wanted to know whether you could take a history, communicate findings clearly, and maintain professionalism with a simulated patient. One thing most people don't realize — the standardized patients weren't grading you. A separate observer behind a one-way mirror was doing that, taking notes on a specific rubric while you interacted with the actor.
How It Actually Felt in the Room
The standardized patient room was small. A desk, two chairs, some anatomical models on the shelf for demonstration purposes if needed. You'd walk in, the actor would introduce themselves in character, and you'd have maybe twenty seconds to establish rapport before diving into the history. I remember one case where the patient was supposed to be a 45-year-old woman with right lower quadrant pain. She had a very specific script with emotional beats built in — she was anxious about possibly needing surgery, and if you didn't acknowledge that early, she'd get closed off and stop giving you information. That was a deliberate part of the test. The actor would actually become less cooperative if you rushed past the psychosocial elements. For documentation, you typed directly into a computer interface. Not handwritten notes. The system had templates that guided you toward the required sections: history of present illness, past medical history, review of systems, physical exam findings, and differential diagnosis. Missing sections didn't automatically fail you, but incomplete documentation was one of the more common reasons people didn't pass that particular component.
Get the Full Details

The Actual Workaround I Found That Worked
Here's something I learned after my first attempt didn't go as planned. In the communication section, I was so focused on getting the full history that I kept interrupting the standardized patient. She'd say something like "I've been having these headaches for weeks" and I'd immediately jump to "where exactly are the headaches?" before she'd finished describing other associated symptoms. The observer notation in my feedback report specifically called this out under interpersonal skills. I failed that section on my first sitting. My workaround for the re-sit was simple and somewhat counterintuitive. I practiced with study partners where I was explicitly forbidden from asking a follow-up question until the patient had finished their entire thought, even if it took thirty seconds of unprompted detail. It felt agonizing at first. But when I retook the exam, I caught myself about three times per encounter pausing instead of jumping in, and the patients — both the actors and later real patients during my rotations — gave me significantly more information voluntarily. That habit carried over beyond just the exam.
Common Pitfalls That Were Missed
Most preparation resources focused heavily on the clinical vignette questions, which makes sense because that's the part that looks like traditional board prep. But the failure rates tell a different story. The communication section historically had a higher failure rate among certain demographic groups, and not for the reasons most people assume. It wasn't primarily about English proficiency in the grammatical sense. It was about cultural communication norms — directness versus indirectness, how much detail to provide without being prompted, the balance between efficiency and empathy that American clinical settings expect. Another underappreciated detail: the physical exam portion of the encounter. You were expected to demonstrate at least some elements of the relevant physical exam on the standardized patient. Not a complete exam, but enough to show you knew what to check. I saw plenty of candidates who just sat and talked for fifteen minutes without ever positioning themselves to listen to lungs or palpate an abdomen, even when the case clearly called for it. That omission showed up in the clinical integrity scoring.
The Hard Truths About What Replaced It
Since the discontinuation, the landscape has changed significantly. The ECFMG now requires medical school students and graduates to demonstrate clinical and interpersonal skills through an alternative path. For international medical graduates, this typically means passing the OET (Occupational English Test) at a specified score level and fulfilling clinical skills requirements through approved programs. Some states have their own additional requirements on top of Step 1 and Step 2 CK scores. Here's what nobody sugarcoats about the current situation: the pathway is more fragmented than it was under the old Step 2 CS structure. Before 2021, every IMG went through the same Prometric-based exam regardless of which state they were targeting. Now you need to verify the specific requirements for each state medical board you're interested in, and those requirements can differ substantially. A requirement that satisfies California might not satisfy New York, and vice versa. This is genuinely harder than the old system was, and it's something anyone planning their USMLE pathway needs to factor in early rather than discovering it six months before they want to apply for residency. The old Step 2 CS did have real problems beyond the logistical issues that ultimately killed it. The cost was significant — roughly $1,500 to $2,000 including travel for international test centers, which meant most candidates had to travel internationally to take it since US-based centers were limited. The scheduling bottlenecks were notorious, with registration windows opening and filling within hours. These aren't nostalgic complaints. They were structural flaws that made the exam inaccessible to a large portion of the IMG population it was supposed to assess fairly.
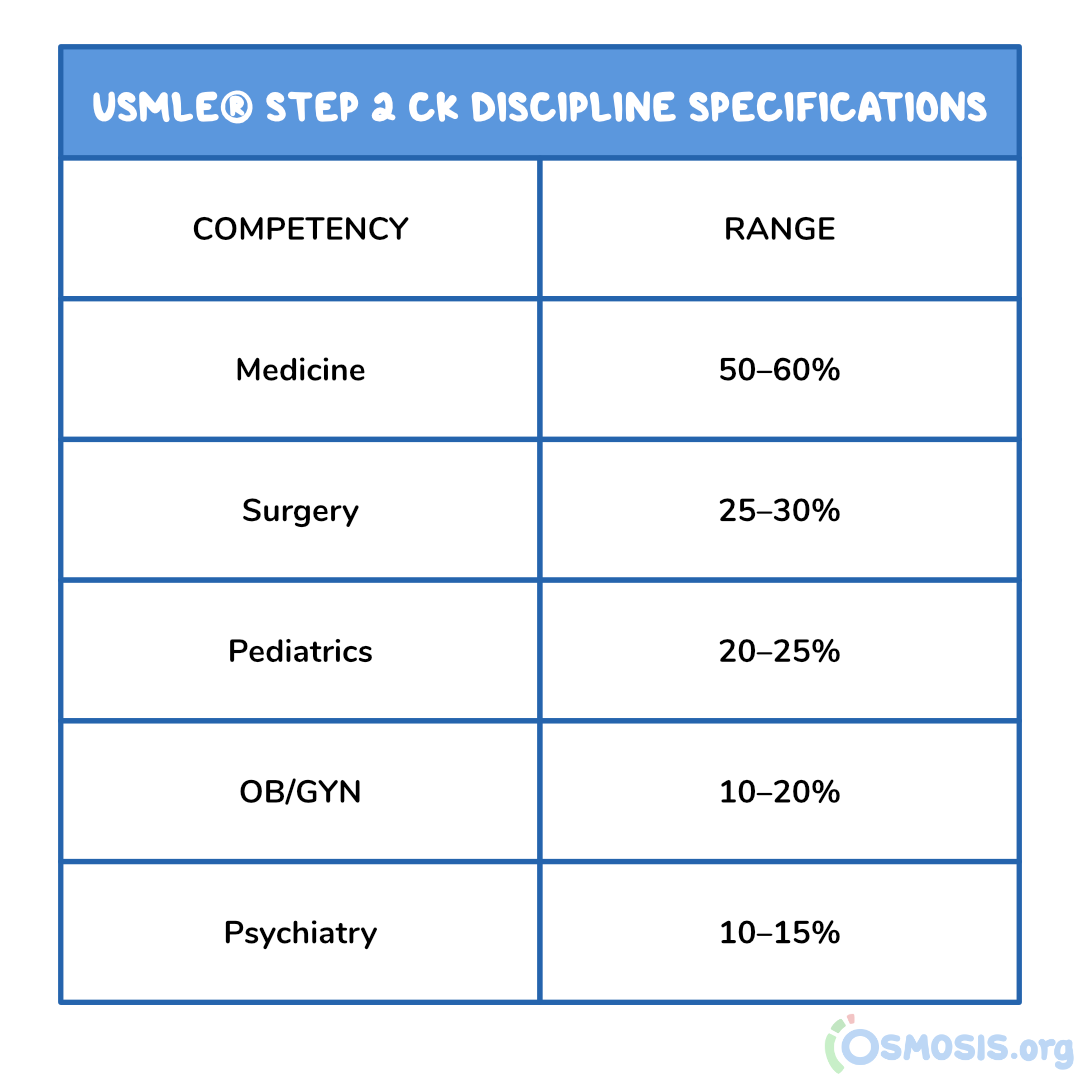
If you're currently navigating this pathway, the most actionable thing you can do right now is confirm your specific state licensing requirements and ECFMG certification path, then build a timeline around those constraints rather than the other way around. The old four-hour exam at Checkers Hill is just a memory at this point.



