Compounding Risk Assessment Under USP 800
Most people treat USP 800 risk assessments as a paperwork exercise. They fill out the table, tick the boxes, and move on. It does not work that way. The standard is blunt about what it expects. You need to actually assess the risk before you compound. Not after. Not during a survey when an inspector shows up at 4 PM on a Friday. USP 800 covers hazardous drug compounding. The core requirement is a documented risk assessment for every unique compounding event. This is not a generic form you slap on every batch of everything. It is specific. The assessment has to account for the drug, the facility, the personnel, and the process.
Usp 800 Assessment Of Risk
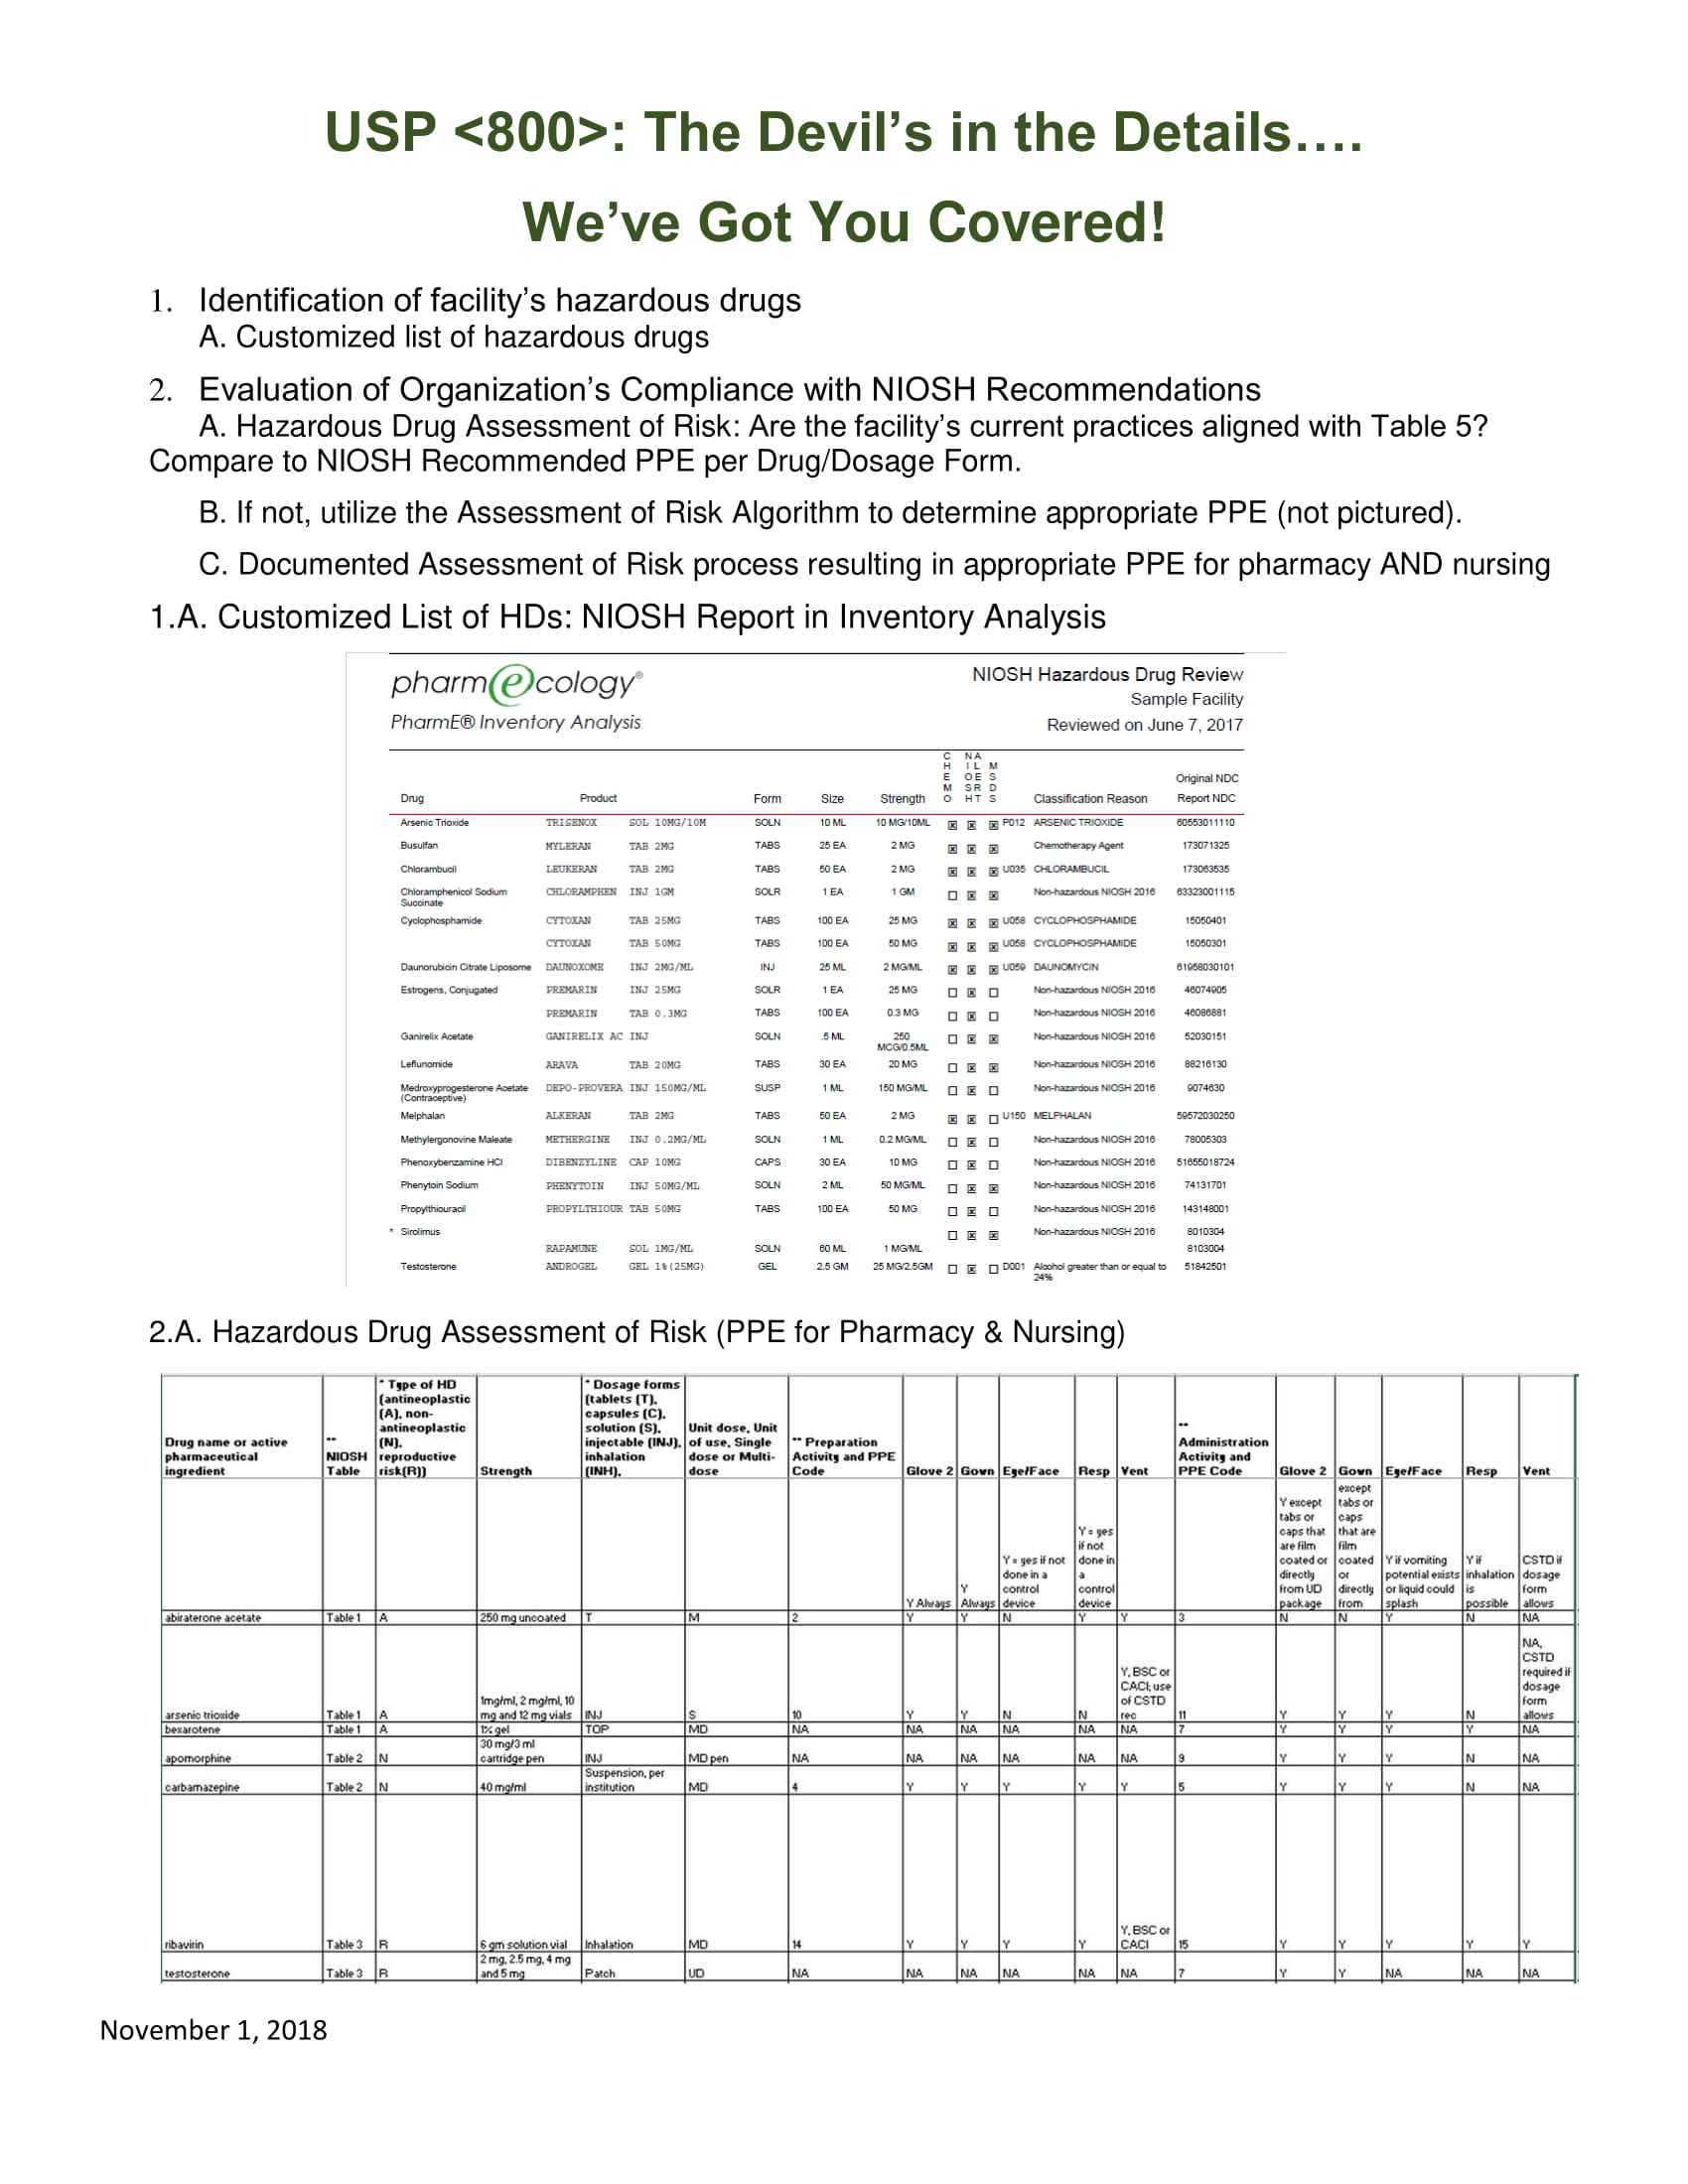
Here is the practical breakdown. You begin by identifying the hazardous drug(s). The NIOSH list is the starting point, not the endpoint. You need to know the dose, the concentration, and the volume. These three factors drive everything else. A low-dose oral solid does not carry the same risk profile as a high-concentration IV admixture prepared in an open system. Next you evaluate the compounding environment. USP 800 references ISO-classified areas. You need a Certified Pharmaceutical Engineering (C-PEC) for primary engineering control. That could be a containment vented encapsulation or a compounding aseptic containment isolator depending on what you are doing. The choice matters. It changes your risk rating.
Then you look at the personnel. Are they trained? Have they completed the competency assessment? Do they have access to the right PPE? This is where most facilities cut corners. They write a training policy and assume compliance. It does not work. I had a situation where a pharmacist kept reusing gloves between steps because the PPE room was on a different floor than the C-PEC. The risk assessment flagged single-use glove protocols. The physical workflow made compliance impossible. I redesigned the PPE staging area to sit adjacent to the C-PEC entry point and added a clearly marked glove change log at the station. That cut the violations from roughly one per shift to about one per week within a month. After that you document the process steps. Every action from weighing to final container closure gets reviewed. Open system transfers are higher risk than closed system drug transfer devices. If you are using CADtrs, note that. If you are doing manual transfers with syringes and needles, the risk score goes up significantly. You assign a risk tier. USP 800 defines low, medium, and high risk. The determination is not arbitrary. It follows the criteria in the standard. Low-risk compounds have the fewest sterile manipulations and the shortest beyond-use dating. High-risk compounds involve prolonged compounding, multiple transfers, or poor environmental controls.
Get the Full Details
Once you have the tier, you apply the corresponding testing and quality control requirements. Medium and high-risk compounds need environmental monitoring during and after compounding. You need to test the ISO class of the area. You need to document the results. Failure to maintain the required ISO class voids the beyond-use date assignments and opens you up to regulatory observation. The beyond-use date comes from Table 2 of USP 800 or Table 4 depending on the risk level and the storage conditions. It is formulaic but only if you get the inputs right. Input the correct risk tier, the correct storage temperature, the correct container type. Get any of those wrong and the BUD is invalid. Documentation is where this becomes a daily burden. Every compounding event needs a unique record. The assessment, the personnel involved, the materials used, the environmental conditions at the time of compounding, the final verification, and the BUD calculation. If you are compounding twelve different hazardous drugs a day, that is twelve distinct records. Some pharmacies use spreadsheet templates. Some use software platforms. Neither is inherently better. The key is that the records exist and they are retrievable.
Environmental monitoring is non-negotiable for medium and high risk. Surface sampling and airborne sampling during compounding. The frequency depends on your risk tier and your historical data. Facilities with clean records can sometimes extend intervals, but you cannot skip it. I saw a compounding pharmacy get a 197 observation because they had not sampled the C-PEC work surface in four months. The inspector asked to see the last twelve months of data. They had six months. That was the problem. A counter-intuitive point that most people miss: the risk assessment is not static. It needs to be updated whenever there is a change. New drug added to the formulary. Different manufacturer supplying the same API. Change in personnel training status. Modification of the C-PEC HEPA filter schedule. Any of these triggers a reassessment. The standard is clear on this. The written procedures should reflect the current state of operations, not the state from six months ago when the original template was created. Another nuance: the difference between USP 800 and USP 797. They are separate standards. USP 797 covers non-hazardous sterile compounding. USP 800 is specifically for hazardous drugs. Many facilities try to merge the two into a single workflow. That creates confusion. A compound that meets USP 797 criteria might still fall under USP 800 if the drug is on the NIOSH list. The risk assessment must follow the hazardous drug pathway regardless of whether the sterility profile looks low-risk by 797 standards. The two frameworks intersect but they are not identical.
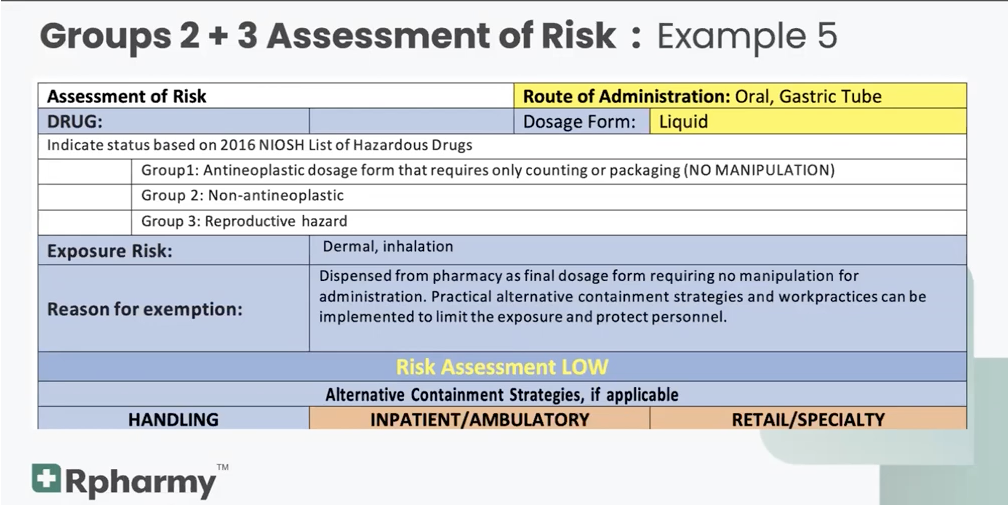
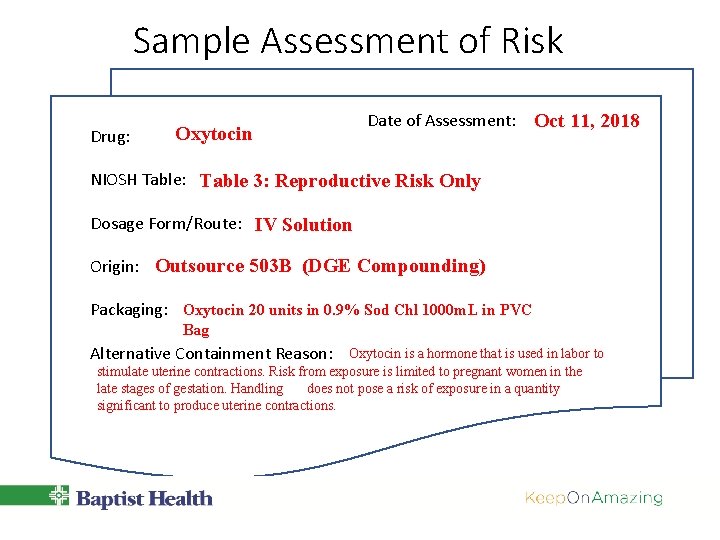
If you are a small compounding pharmacy doing occasional hazardous drug work, the documentation overhead can feel disproportionate. It is. There is no way around it. The standard does not provide a simplified pathway for low-volume operations. Your options are to invest in a streamlined digital tracking system, consolidate your hazardous drug workload into fewer sessions so the documentation batches together, or subcontract that portion of your work to a dedicated facility. None of those are perfect. The third one is the most practical if you are compounding fewer than five hazardous drug orders per week. The paperwork for a single order will cost you more in staff time than the margin on the order itself. The actual assessment worksheet should cover at minimum: drug identification, quantity and concentration, compounding technique, engineering controls used, PPE selected, personnel training verification, environmental conditions at time of compounding, risk tier assignment, beyond-use date derivation, and final verification signature. Nothing fancy. Just those fields. Most inspectors want to see exactly those elements on the page. I keep a running log of my risk assessment turnaround time. A straightforward low-risk hazardous drug compound with familiar materials takes about twelve minutes from drug identification through BUD assignment. A medium-risk compound with an unfamiliar NIOSH-listed drug and a new sterile technique averages forty-five minutes. High-risk compounds that require additional environmental sampling setup push toward two hours including the documentation and verification steps. Those numbers assume you have a clean formulary and trained staff. If you are pulling a drug for the first time, add another twenty minutes for literature review on the specific hazards and the recommended engineering controls.

The biggest failure mode I see is treating the risk assessment as a backward-looking exercise. People fill it out after compounding because the compounding is already done. That is incorrect and it is easy to catch. Inspectors compare the assessment timestamp against the compounding timestamp. If the assessment date is after the compounding date, the record is non-compliant. There is no workaround for that. You assess before you compound. Always. Another failure mode is using a master risk assessment for all compounds of a given drug. The standard requires a unique assessment per compounding event. Variations in dose, volume, container, and technique change the risk profile. A 10 mg dose in a 10 mL syringe is not the same risk scenario as a 10 mg dose in a 100 mL IV bag, even if the drug is identical. Document each one separately. If you need a starting template, the USP 800 standard itself does not provide a mandated format. It specifies what must be assessed, not how the document should look. You can build your own. Some professional organizations publish sample worksheets. The American Society of Health-System Pharmacists has resources. The key is that your document covers every required element and that it is specific to the compounding event, not a generic form.
The risk tier determines your testing frequency, your BUD, and your documentation depth. Get the tier wrong and everything downstream is wrong. A compound you classify as low risk but should be medium risk will skip required environmental monitoring. That is a compliance gap. A compound you classify as high risk when it qualifies as medium will unnecessarily restrict your BUD and increase your testing burden. Both errors have consequences. One gets you an observation. The other costs you money and staff time. There is no shortcut. The assessment is the foundation. Everything else builds on it. Write it correctly, update it when things change, and file it with the compounding record. That is the job.