A Quick Look at the Reproductive Tract's Inner Workings
The uterus and uterine tubes are one of those topics that gets covered superficially in almost every introductory course. Everyone knows eggs travel through the tubes, and everyone knows the embryo implants in the uterus. What most people miss is how the actual mechanics play out in a clinical setting, and why certain pathologies behave the way they do. I spent years reviewing histology slides and imaging studies on this. The details matter more than you'd think.
Understanding the Uterus And Uterine Tubes: Structure and Function
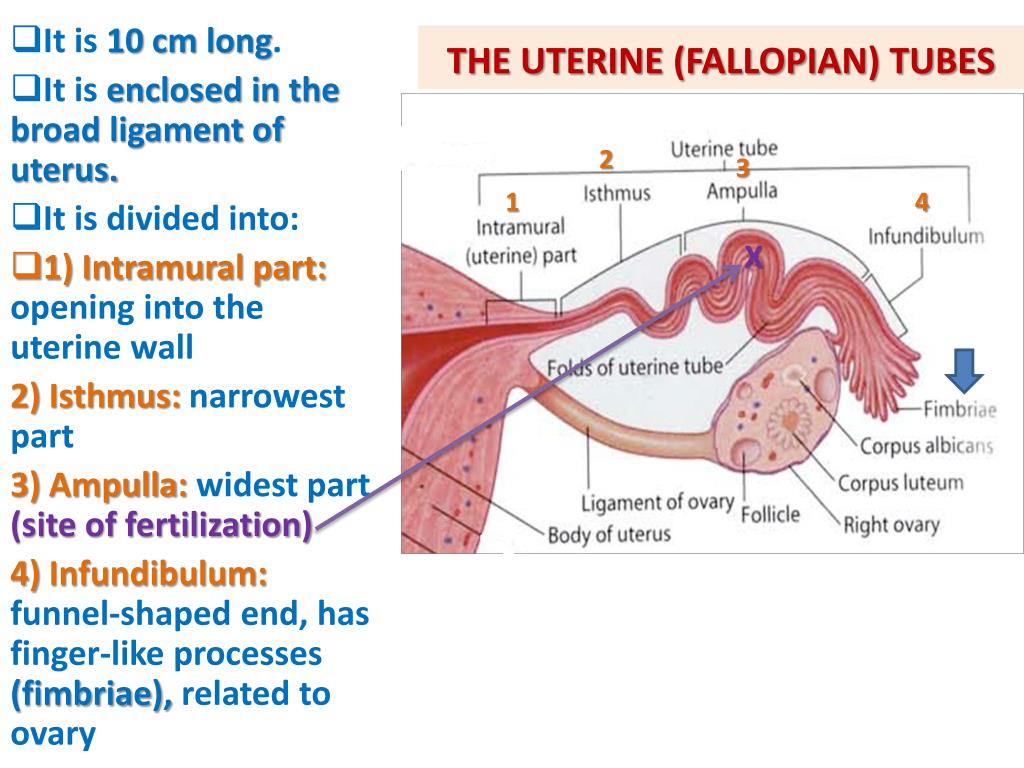
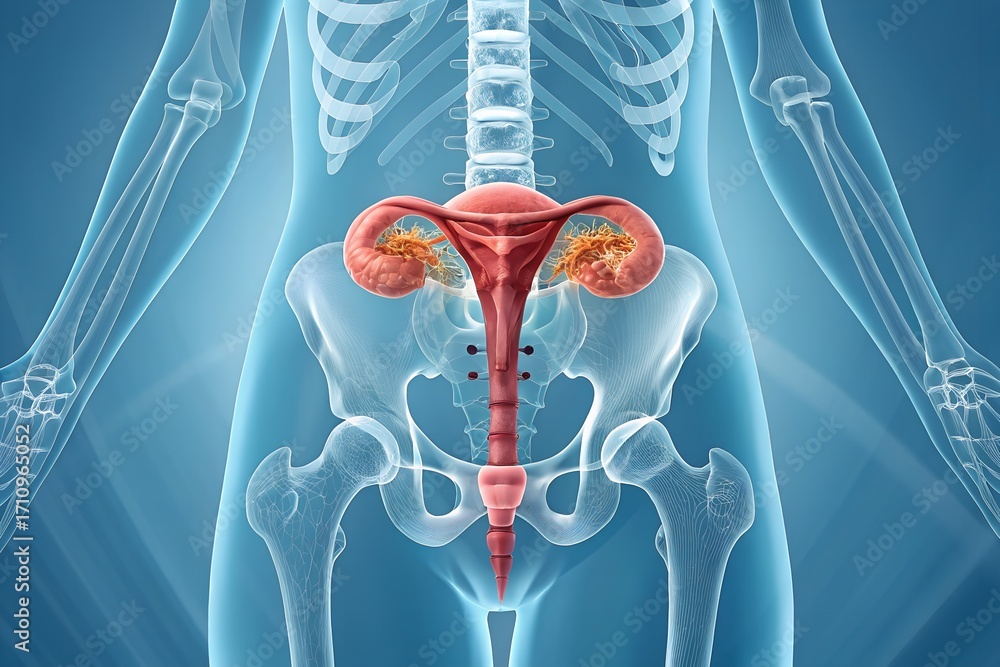
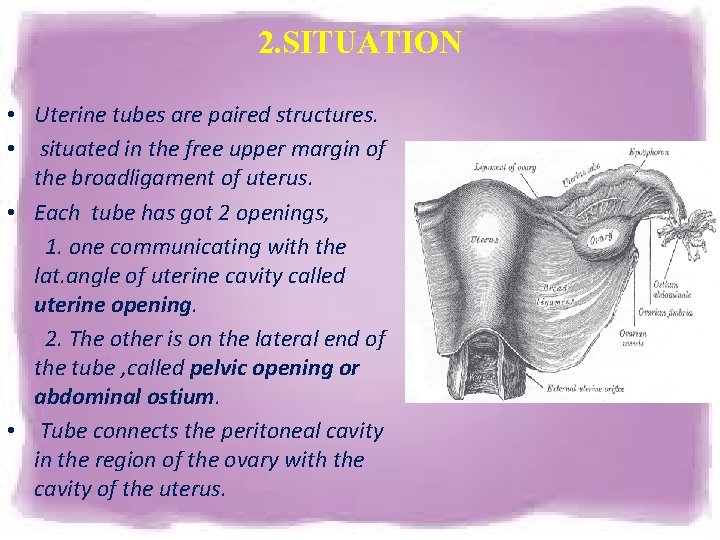
The uterine tubes, also called fallopian tubes, are roughly 10 to 12 centimeters long. They extend from the lateral margins of the uterus toward the ovaries but don't actually attach to them. The fimbriated end hovers near the ovary, and that close proximity is what allows the infundibulum to capture the released oocyte. The tube itself has four regions: the infundibulum with its fimbriae, the ampulla, the isthmus, and the intramural portion that passes through the uterine wall. Fertilization normally happens in the ampulla. That's the widest section, and the ciliated epithelium there creates currents that move the ovum toward the uterus. The smooth muscle in the tube wall also contributes through peristaltic contractions. Most ectopic pregnancies occur in the ampulla simply because it's the largest segment and the most common site for implantation when things go wrong. That's a pattern you'll see repeatedly in case studies. The uterus is a muscular organ with three layers. The outer serosa is the perimetrium. The thick middle layer is the myometrium, made of smooth muscle arranged in overlapping layers that contract during labor. The innermost layer is the endometrium, which has two sublayers. The stratum functionalis sheds during menstruation and regenerates each cycle. The stratum basalis remains attached to the myometrium and serves as the regenerative source for the functionalis. This distinction is important because any procedure that damages the basalis — D&C, infection, or excessive curettage — can lead to permanent scarring known as Asherman's syndrome.
The blood supply deserves attention too. The uterine arteries branch from the internal iliac and run through the broad ligament. The ovarian arteries, coming directly from the abdominal aorta, anastomose with the uterine arteries near the tubes. This collateral circulation matters surgically. If you're ligating vessels during a hysterectomy or tubal ligation, knowing where these anastomoses are prevents unexpected bleeding.
Get the Full Details

Common Misunderstandings and Clinical Pitfalls
One thing that consistently trips people up is the relationship between the tubes and ovarian placement. The tubes don't actively grab the ovary. They rely on fimbrial cilia and fluid currents to pull the oocyte inward. This means ovulation doesn't have to occur right at the fimbrial tip. It can happen slightly further away on the ovarian surface, and the oocyte can still be captured — though success drops noticeably with distance. This has implications for IVF retrieval timing and why transvaginal ultrasound monitoring matters when tracking follicle development. Another overlooked point is the lymphatic drainage pattern. The uterine tubes and the fundus of the uterus drain to the para-aortic nodes. The lower uterus and cervix drain to the internal and external iliac nodes. This isn't just anatomical trivia. When staging endometrial or cervical cancer, surgeons need to know which nodal basin to sample. A tumor at the fundus could metastasize to the para-aortic region even without involving the lower tract, and that changes the surgical approach entirely. I ran into a specific issue once while reviewing H&E slides from a pathology rotation. A patient had recurrent implantation failure after multiple IVF attempts. The endometrial biopsies looked normal on standard staining, but the gland-to-stroma ratio was subtly off. The crypts were tighter than expected, and the subnuclear vacuolization that normally appears in the secretory phase was delayed. We traced it back to mild chronic endometritis — plasma cells in the stroma that weren't flagged on the initial read. A simple 14-day course of doxycycline cleared it, and the next cycle showed proper secretory changes. The takeaway here is that standard histology without CD138 immunostaining for plasma cells will miss this diagnosis roughly half the time. If you're evaluating unexplained implantation failure, requesting that stain isn't optional.
What the Literature Gets Wrong About Tube Patency
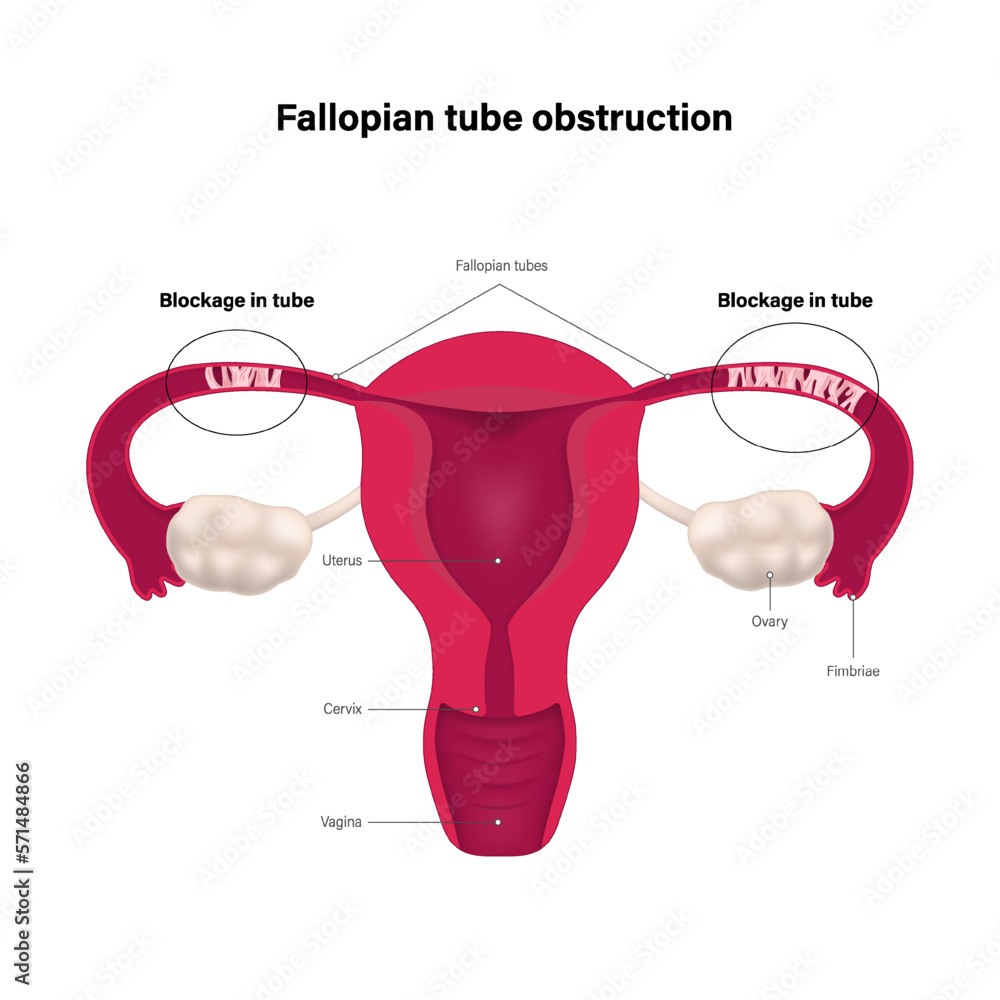
Hysterosalpingography, the X-ray dye test for tube blockage, is widely used but has a significant false-positive rate. Up to 30 percent of patients who fail the test on the first attempt will have patent tubes on repeat testing. The reason is usually proximal spasm — the isthmus contracts around the catheter tip and blocks dye flow, mimicking a true occlusion. This is why many clinicians now prefer saline infusion sonography or laparoscopy with chromopertubation for confirmation before labeling someone as having tubal factor infertility. The reverse is also true but less discussed. A tubal ligation can recanalize over time. The cut ends of the isthmus don't always seal completely, and epithelial bridges can form months or even years after the procedure. This is rare but well documented. Any patient who has had a tubal ligation and presents with a positive pregnancy test needs an immediate ectopic workup regardless of how long ago the procedure was performed.
Practical Considerations for Clinical Application
If you're studying this for boards or clinical rotation, focus on three things: the blood supply anastomoses, the lymphatic drainage zones, and the histological changes through the menstrual cycle. The cycle phases matter more than most students realize. Proliferative phase days 5 through 14 shows mitotic figures in the basalis with elongating glands. Secretory phase days 15 through 28 shows subnuclear then supranuclear vacuoles, then secretion into the gland lumen by day 21 in a textbook 28-day cycle. Decidualization of the stroma begins around day 24. If implantation doesn't occur, progesterone drops, prostaglandins increase, and the functionalis necroses and sheds. The hormonal feedback loop controlling all of this is straightforward in theory but messy in practice. FSH stimulates follicular growth, which increases estrogen. Rising estrogen eventually triggers the LH surge. The LH surge causes ovulation and transforms the ruptured follicle into the corpus luteum, which produces progesterone. Without fertilization, the corpus luteum regresses after about 10 days, progesterone falls, and menstruation follows. With fertilization, hCG from the developing embryo rescues the corpus luteum and maintains progesterone production until the placenta takes over around week 10. Polycystic ovary syndrome disrupts this at multiple points. Elevated LH relative to FSH drives excess androgen production from the ovarian stroma. The follicles arrest at the antral stage instead of selecting a dominant follicle. No dominant follicle means no surge and no ovulation. The endometrium receives continuous estrogen without the progesterone opposition needed for proper secretory transformation, which is why endometrial hyperplasia is a real concern in untreated PCOS. Metformin and letrozole are first-line interventions because they address insulin resistance and restore ovulatory cycles, not just because they lower androgens.
Endometriosis affects roughly 10 percent of women of reproductive age and 50 percent of those with infertility. The disease involves endometrial-like tissue outside the uterus, most commonly on the ovaries, pelvic peritoneum, and uterosacral ligaments. The classic triad is dysmenorrhea, dyspareunia, and infertility. But a significant number of patients are asymptomatic until they present for fertility evaluation. Laparoscopy remains the gold standard for diagnosis, and visual appearance alone isn't sufficient — biopsies are needed because superficial peritoneal lesions can look identical to reactive mesothelial changes. The adenomyosis distinction is worth noting because it overlaps clinically. Here the endometrial tissue invades into the myometrium rather than residing outside the uterus. The uterus becomes globally enlarged and boggy, usually between 12 and 14 weeks size. Heavy menstrual bleeding and painful periods are the main symptoms. Transvaginal ultrasound with high-resolution probes can detect it in most cases, but MRI is more accurate for mapping the depth of myometrial invasion. Hormonal suppression with a levonorgestrel IUD is the first-line treatment for symptom control. Hysterectomy is curative but obviously not acceptable for anyone desiring future fertility. When it comes to uterine fibroids, or leiomyomas, the submucosal type causes the most trouble for fertility even when small. A 2-centimeter submucosal fibroid distorting the cavity can reduce implantation rates by roughly 70 percent according to multiple meta-analyses. Hysteroscopic resection restores cavity architecture and improves outcomes significantly. Intramural fibroids larger than 4 centimeters may also impair fertility, but the evidence is less consistent. Subserosal fibroids generally don't affect fertility unless they're enormous enough to compress the tubes or distort pelvic anatomy.
The anatomical relationships in the broad ligament are another area where precision matters. The ureter passes under the uterine artery about 1.5 centimeters lateral to the cervix — the water under the bridge landmark from surgery classes. During a hysterectomy, this is where ureteral injury most commonly occurs if the vessel is clamped too far laterally or if the tissue is tractioned improperly. A ureteral stent placed preoperatively doesn't prevent injury but makes identification easier. The ovarian vessels cross anterior to the ureter, so the surgical sequence of ligating vessels matters. There's no shortcut through this material. The structures are small, the relationships are tight, and the clinical consequences of confusion are real. Focus on understanding why things happen the way they do rather than memorizing isolated facts. The anatomy tells you the story — once you see it, it sticks.