How to Assess Uvular Deviation and What It Actually Tells You
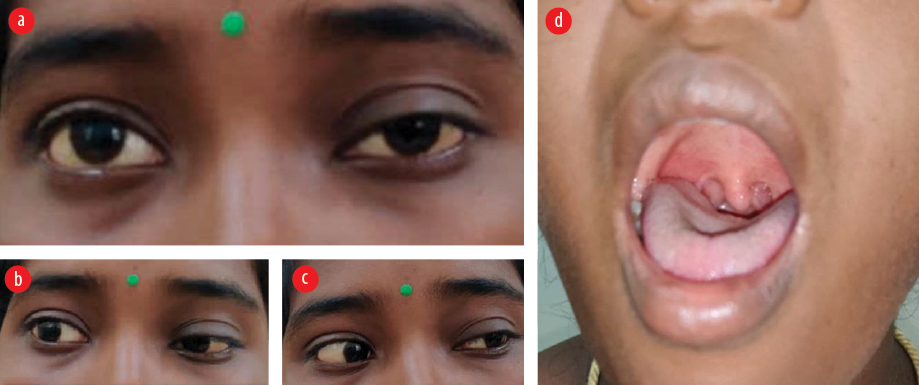
The uvula deviation test is one of those bedside exams that seems straightforward until you're actually looking at a real patient's open mouth and suddenly realize half the time it tells you very little. Here is how it works, where people mess it up, and what the finding actually means in practice. The uvula deviates as a sign of lower motor neuron dysfunction involving the vagus nerve. The vagus nerve provides motor innervation to most of the muscles of the soft palate including the levator veli palatini, tensor veli palatini (though the tensor is primarily CN V3), and the palatoglossus. When these muscles are weak on one side, the intact contralateral muscle pulls the uvula toward the healthy side. That is the basic mechanism. It sounds simple enough on paper. The reality of actually using this as a clinical tool is more complicated. Have the patient sit upright, keep their head centered, and say a sustained "ah." You do not need to depress the tongue with a tongue blade unless the gag reflex is hyperactive and interfering with your view. That part about the tongue blade is debated actually because just having the patient say "ah" activates the palate muscles enough. Watch the uvula. In a normal exam it lifts symmetrically and stays midline. With a unilateral CN X lesion it deviates away from the side of the lesion because the intact side contracts normally and pulls it over.
I have seen people try to assess uvular movement while the patient is half-lying down in a crowded ED with bright overhead lights. It is not reliable in that setting. Position the patient sitting upright with good ambient lighting and ask them to say "ah" three or four times to get a consistent baseline. One utterance is not enough because patients often tense up on the first attempt.
What People Get Wrong
The biggest mistake I see is assuming uvular deviation means a CN X problem. It does not always mean that. CN IX also contributes to some palatal innervation via pharyngeal branches and plexuses, so isolated CN IX lesions can occasionally produce subtle deviation. More importantly, uvular deviation only reliably indicates a lower motor neuron lesion of the vagus. A central lesion such as a stroke affecting the corticobulbar tracts typically spares the palate bilaterally or produces only mild transient weakness because the motor nuclei receive bilateral cortical input. This is critical because if you see a patient with a history of acute neurological deficit and normal uvular position, that does not rule out a stroke. The palate is surprisingly resilient to unilateral upper motor neuron injury. Another pitfall: the examiner often judges deviation by looking at the uvula alone without considering asymmetry of the soft palate itself. The hemipalate on the affected side will not elevate properly. The uvula may appear midline because the soft tissue asymmetry is compensating in certain positions. Always assess both the palate elevation and the uvular position together before drawing any conclusions.
Get the Full Details

A Specific Case From My Practice
I encountered a patient post-thyroidectomy who had hoarseness and dysphagia but a midline uvula on examination. At first glance this looked like no palatal weakness. But when I asked them to phonate at a higher pitch and sustained a prolonged "ee" sound, the left soft palate failed to elevate. The uvula remained essentially midline because the left and right side imbalanced was masked at the uvula tip level but obvious in the soft palate. The problem was a stretch injury to the left recurrent laryngeal branch of CN X. The deviation was not visible on routine "ah" testing. This is the kind of case where relying solely on uvular position misses a real lesion. If the initial exam is normal but clinical suspicion remains high, change the phonation task. Try sustained "ee" or ask the patient to blow out a candle. The added submental and pharyngeal engagement often unmasks subtle weakness. If you confirm uvular deviation away from one side, the next step is localization. Ask about associated symptoms: hoarseness suggests involvement of the recurrent laryngeal branch. Loss of the gag reflex on that side points to a more proximal lesion affecting both sensory and motor components. Dysphagia and nasal regurgitation of fluids indicate broader palatal palsy. Without those findings and an isolated uvular deviation with otherwise intact phonation and gag reflex, the lesion may be very focal and less clinically significant. Imaging is not automatically indicated for a single normal finding of mild uvular deviation discovered incidentally. If the deviation is new and accompanied by any other cranial nerve deficits, brainstem imaging with MRI is appropriate. Isolated unilateral vagus dysfunction is rare as a primary event. Most causes are secondary to surgical trauma, neoplasms along the nerve course, or vascular events. The differential is narrower than beginners assume.
Limitations and When the Test Fails Completely
Uvular deviation is not a sensitive test for early or partial CN X palsy. Up to 30 percent of patients with confirmed vagus neuropathy may not demonstrate obvious uvular deviation on routine examination. The palate has redundant innervation from the ipsilateral glosstrapngeal nerve and the pharyngeal plexus which can compensate for mild deficits. In these cases the exam feels completely unrewarding and you will be staring at a perfectly midline uvula for several minutes. That does not mean the nerve is fine. It means the test has hit its ceiling. For cases where bedside assessment is inconclusive but clinical suspicion persists, fiberoptic laryngoscopy provides direct visualization of vocal fold movement and palatal asymmetry. Electromyography of the palatal muscles is an option for research or neurophysiology labs but is not widely available or routinely performed in most clinical settings. Nasendoscopy is the practical next step. The test also becomes unreliable in patients with anatomical variants such as a bifid uvula, chronic tonsillar hypertrophy, or prior palatoplasty. Do not attempt to interpret deviation in these patients using standard criteria. The baseline anatomy distorts the assessment beyond usefulness.