What You Actually Need to Know About the VA Sleep Apnea Exam Process
The VA sleep apnea claim process is one of those things where the paperwork is half the battle and the actual exam is the other half, but most people treat it like the exam is the hard part. It is not. The hard part is making sure your symptoms are documented properly before you even walk into the examiner's office. I have seen too many veterans get a lower rating than they should because their BAH (Bellows Airway Hypersomnolence) or CPAP usage notes were vague or contradictory. When the VA schedules your Compensation and Pension exam for sleep apnea, the examiner is going to use the diagnostic criteria from the VA Schedule for Rating Disabilities, specifically section 38 CFR § 4.97-13, code 6847. That code covers obstructive sleep apnea, central sleep apnea, and mixed sleep apnea. The rating scale runs from 0% to 100%, and most claims land somewhere between 30% and 50%. A 50% rating requires the use of a CPAP device. That is the single most important threshold to understand.
Va Ace Exam For Sleep Apnea: What to Expect and How to Prepare
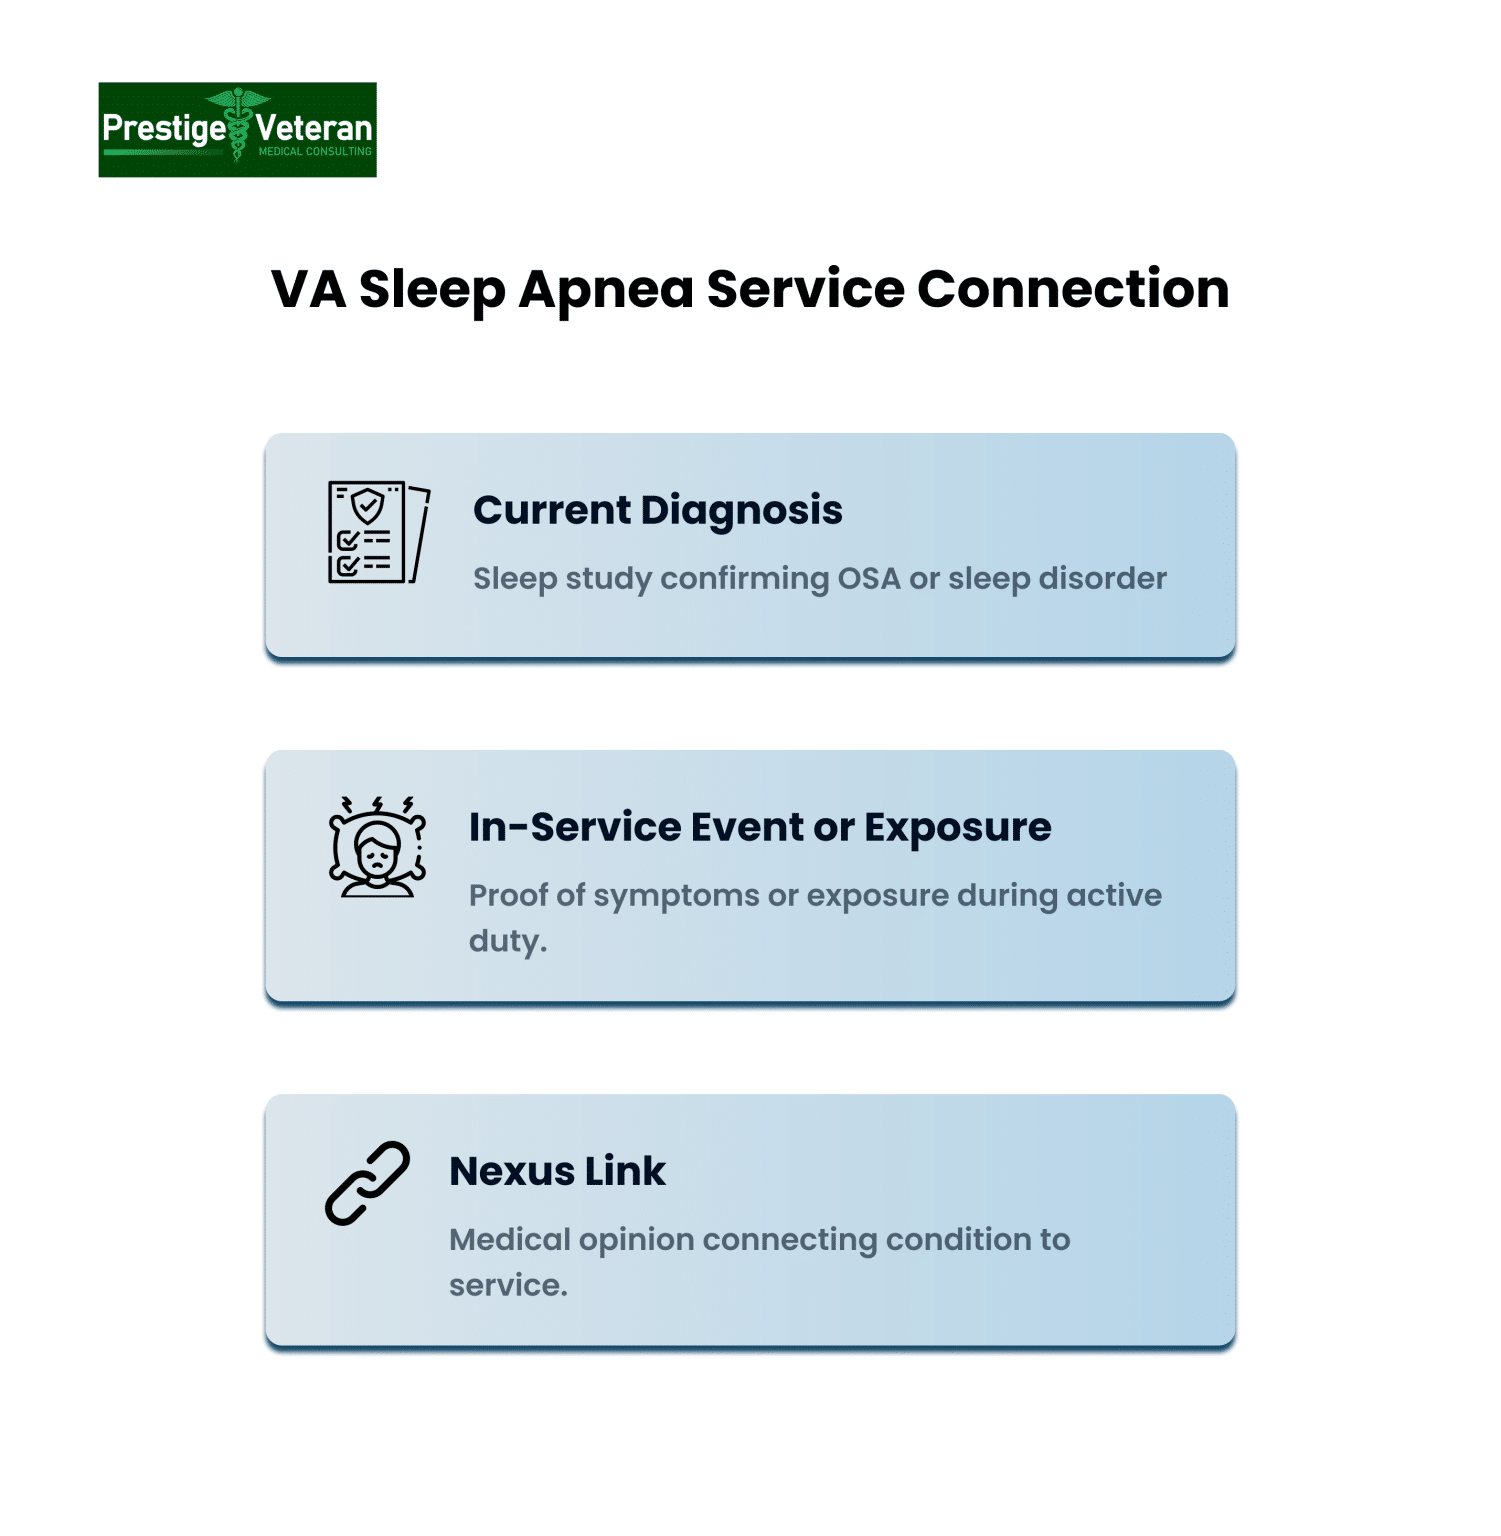
First, a clarification on terminology. There is no official VA product called "Va Ace Exam For Sleep Apnea." This is a commercial third-party service that helps veterans prepare for and navigate their C&P exams. Some veterans find it useful. Some find it overpriced. I will say this: if you already understand your own medical history and have your records organized, you do not need a middleman. If you have scattered records from multiple providers and no idea how to present them coherently, a service like that might save you a misstep or two. But it will not fix a weak medical nexus. Here is the practical walkthrough. Before your exam, gather three things. Your sleep study results, specifically the polysomnography report with your AHI (Apnea-Hypopnea Index) or RDI (Respiratory Disturbance Index). Your CPAP machine data if you use one. And a list of all daytime symptoms: fatigue, cognitive fog, morning headaches, witnessed apneas, partner complaints about your breathing. The examiner will ask about these. If your file does not already show them documented by a treating physician, you need to bring that evidence yourself. I ran into a specific problem last year with a veteran whose sleep study showed an AHI of 28, which should qualify him for at least a 30% rating. The examiner at the C&P visit noted the AHI but then wrote up the claim as a 10% rating because the veteran appeared alert during the exam. The examiner was conflating "looks awake now" with "does not have significant daytime impairment." I had the veteran submit a second opinion from his pulmonologist detailing his observed daytime hypersomnolence, his use of stimulant medication, and his wife's sworn statement about his sleep interruptions. The VA Regional Office eventually upgraded it to 50% after considering that supplementary evidence. The initial exam was not wrong per se, but it was incomplete. That is the real risk with these C&P exams.
One counter-intuitive point that most veterans miss: the AHI number matters less than the documented necessity of treatment. A veteran with an AHI of 15 who is prescribed and actively using a CPAP can get a 50% rating. A veteran with an AHI of 40 who refuses treatment may only get a 30% rating. The VA rates based on the severity of the condition as manifested by the treatment required, not purely on the raw apnea count. This is spelled out in the rating criteria but almost nobody explains it clearly at the exam itself. The examiner will not volunteer this. You have to make sure it is on the record. Another nuance: the difference between obstructive and central sleep apnea. Obstructive is far more common and easier to service-connect because it usually follows nasal surgery, tonsillectomy, or weight-related issues that the VA recognizes as secondary conditions. Central sleep apnea, caused by neurological or cardiac issues, requires a stronger nexus argument. If your central sleep apnea is linked to a service-connected heart condition, that changes the strategy entirely. You do not claim the sleep apnea directly. You claim it as secondary to the heart condition. The burden of proof shifts slightly and the medical literature on cardiogenic central sleep apnea becomes your supporting evidence base. Now, about the actual exam day. You will meet with a contracted examiner, usually a pulmonologist or a sleep medicine specialist. They will review your chart, ask you a standard set of questions, and sometimes run a quick pulse oximetry test. They are not there to diagnose you. They are there to fill out a VA-formatted questionnaire that becomes part of your claim file. Speak plainly. Do not inflate your symptoms. Do not downplay them either. The examiner is looking for specific checkboxes: Do you use CPAP? Do you have daytime somnolence? Are you hypersomnolent enough to require stimulant medication? Have you been hospitalized for sleep apnea?
Get the Full Details

If you claim a higher rating than what the examiner writes up, you will receive a revised examination report or a. You can request a corrected report if the examiner made an factual error, such as recording the wrong AHI number or omitting a treatment modality you are actively using. This happens more often than you would think. I have seen examiners copy-paste previous results from a different patient's file by mistake. Always read the output report carefully after the exam. There are real limitations to relying on third-party exam prep services. They cannot access your VA file directly. They cannot speak to the VA on your behalf unless you have given them formal representation through a VA-accredited agent. And some of these services use templated responses that sound generic and can actually hurt your credibility if the language does not match your actual clinical picture. If you use one, make sure the advice is tailored to your specific records, not just generic coaching scripts. The honest downside to the current VA sleep apnea examination process is that it is understaffed and overworked. Examiners may spend ten to fifteen minutes per case. That is enough time to get the basic data but not enough to explore the full functional impact of your condition. This is why bringing a written summary of your symptoms and your treatment timeline into the exam room is practically essential. One page, typed, with dates and dosages. Hand it to the examiner at the start. It forces the record to include details that might otherwise be lost in a rushed conversation.
If your claim gets denied or rated too low, do not accept the first decision. You can appeal through the Supplemental Claim lane if you have new and relevant evidence, or through the Higher-Level Review if you believe the VA made an error in applying the law to the facts you already submitted. A 10% rating when you clearly meet the 30% threshold is a common error that gets corrected on review. The system is not broken, but it is dense and slow. Patience and documented evidence beat emotional appeals every time.