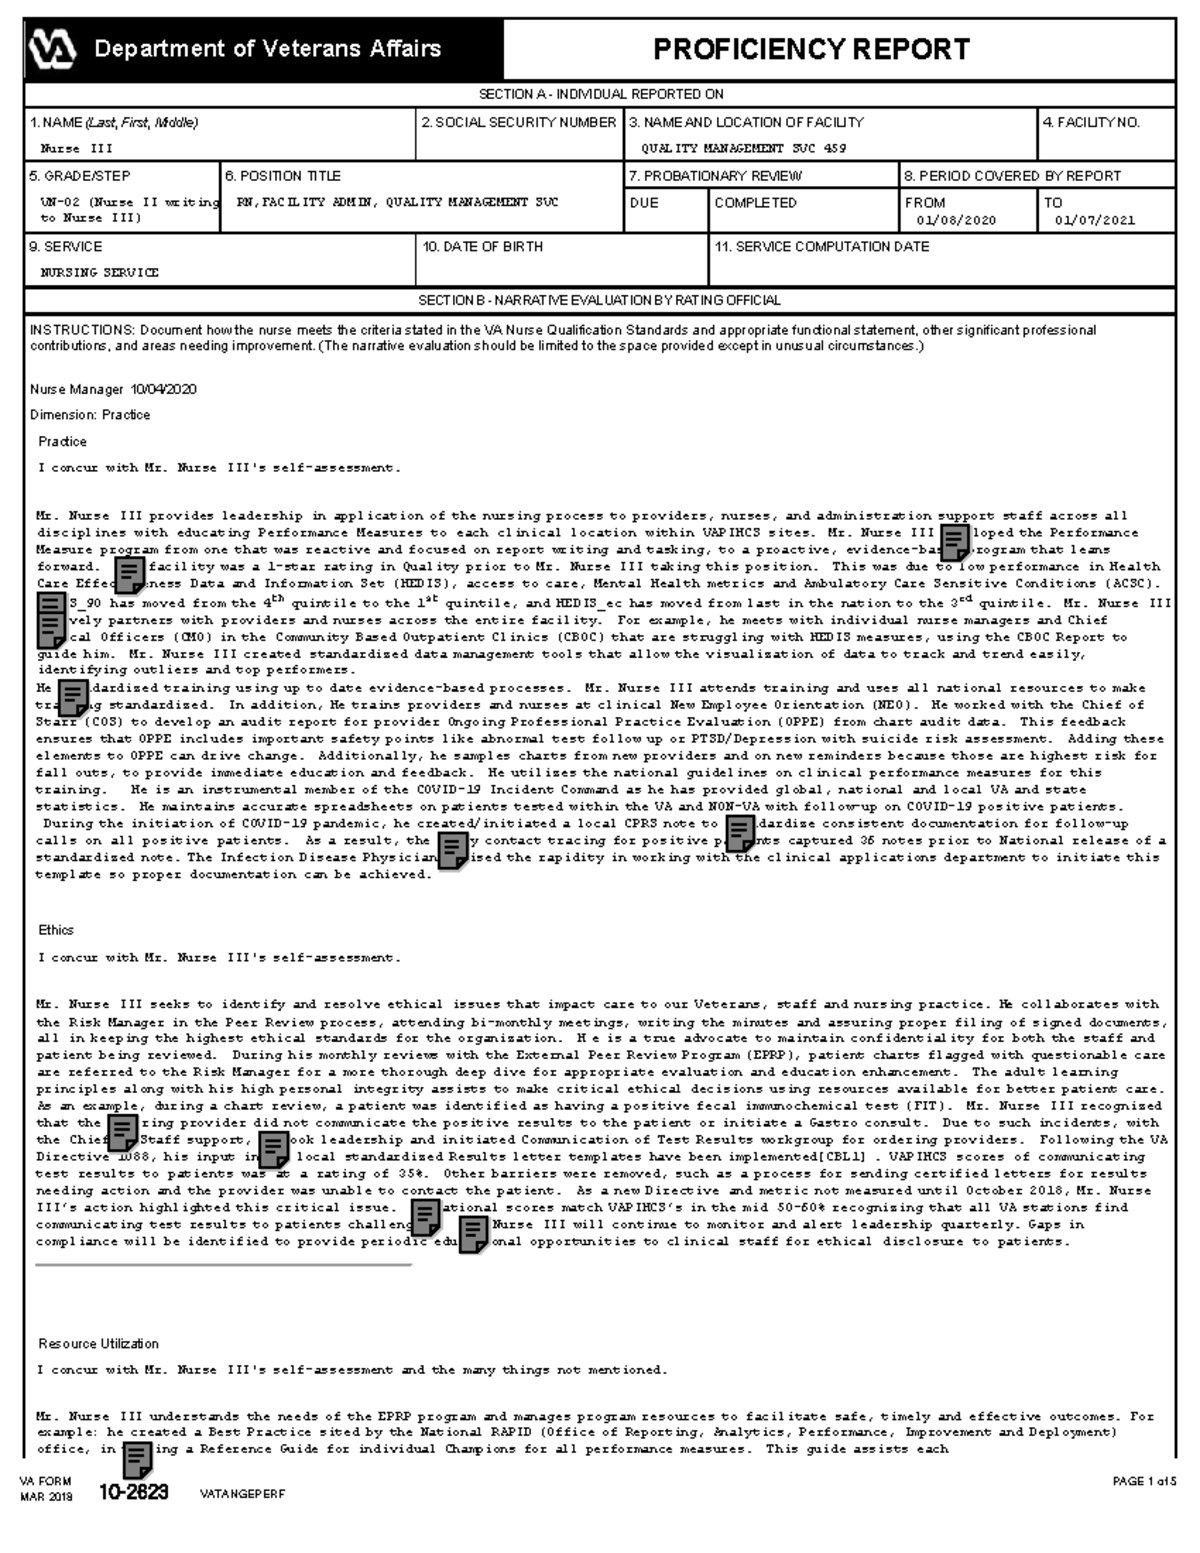
Navigating the VA Nurse II Proficiency Assessment
The VA nursing proficiency system is one of those things that sounds more complicated on paper than it actually is in practice. You're a Nurse II level, which means you've moved past the fresh graduate orientation phase and are expected to work with a reasonable degree of independence. The proficiency sample is basically a documented evidence package where you prove you can handle clinical situations at that level without constant supervision. I've watched people stress over this for months when the whole thing usually takes a weekend if you've been keeping your credentials organized along the way. Here is how it actually works.
What Is a Va Nurse Ii Proficiency Sample
At its core, the proficiency sample is a portfolio of clinical competence documentation. You are required to submit evidence across several domains: direct patient care, medication administration, care coordination, documentation accuracy, and professional development. Each domain has specific criteria tied to your scope of practice as a staff nurse at the VA. The document itself is typically structured around the VA's national nursing standards framework, which aligns closely with ANA principles but adds VA-specific requirements around veterans' services, PACT (Patient Aligned Care Team) model integration, and the particular regulations governing military-to-civilian healthcare transitions. Your facility may have local variations on top of that, so check with your Nursing Competency Council or your charge nurse about what your specific VISN expects.
The Actual Components You Need to Gather
Most people underestimate how much of this is already sitting in your charting system. You do not need to go generate new work products from scratch. Here is what typically makes the cut: Three to five case studies or patient care narratives from the review period, ideally showing complexity that justifies the Nurse II level. These should include your assessment, your plan, interventions you carried out, and how you evaluated outcomes. Pick cases where you exercised independent clinical judgment, not just protocol-driven tasks. The evaluators want to see the thinking process. Medication administration records or pharmacology competency sign-offs. If you have any recent IV push, chemo, or high-alert medication competencies on file, pull those. If your facility uses a specific eMAR verification system, a screenshot or printout from that system carries more weight than a generic pharmacy form.
Get the Full Details

Documentation samples. A few examples of your progress notes, care plans, or discharge summaries. Keep them de-identified but complete enough that someone unfamiliar with your unit could still evaluate the clinical reasoning. I once had a reviewer mark down my case study because the lab values were included but not interpreted within the narrative. The data was there, I just failed to connect it. Lesson learned to flag every abnormal value and state what it meant for the plan of care. Continuing education certificates. Any BLS, ACLS, PALS, or specialty certifications. Also include in-services, workshops, or training modules completed during the period. The VA tracks a lot of this through VHA eLearning, so log into that portal and download your transcript. It covers everything in one place. A self-reflection or professional development statement. This is where you write a few paragraphs about your growth area, what you are still working toward, and how you plan to get there. Be honest. Writing something vague like "I want to improve" reads like you did not put thought into it. Mention specific skills, specific goals, and a concrete timeline.
How to Actually Build and Submit It
Start by pulling the current year's template from your facility's nursing education or competency page. The format changes occasionally and using an outdated template is the fastest way to get sent back for a revision. I learned this the hard way during my own Nurse II review. I spent about four hours compiling materials only to be told the document header needed the fiscal year notation that was added in a mid-cycle update. The template update notice had gone out in an email I never opened because I was drowning in patient assignments. Now I check the nursing education intranet weekly instead of waiting for reminders. Once you have the right template, fill it in sections rather than trying to complete the whole thing in one sitting. Documentation compilation alone can take a day if you are pulling records from multiple patients across different shifts. Do it in thirty-minute blocks between assignments so you do not burn out on it. Have your preceptor or charge nurse review it before you submit. Not because they need to grade it, but because they will catch formatting errors and missing signatures that automated checks will miss. One of my early reviews got stuck for two weeks because a single competency co-signature was missing from an attachment. The reviewer did not point it out in their feedback, just put it on hold. Your charge nurse would have caught that in thirty seconds.
Submit through whatever portal your facility uses. Some VISNs use the VA's internal competency management system, others use a shared drive with a submission form. Follow the exact path listed on your facility's nursing orientation page. Do not email it to a supervisor unless that is the stated procedure. There is a difference between informal feedback and official submission, and mixing them up delays everything.

Things Nobody Tells You About the Review Process
The reviewers are other VA nurses, usually at the Nurse III or clinical nurse specialist level. They are not trying to fail you. They are trying to verify that you meet the published standard, which is a lower bar than most people assume. A perfect score is not required. You pass by demonstrating consistency and competent judgment across the domains, not by producing flawless clinical work. That said, there are common mistakes that sink reviews. The biggest one is submitting evidence that does not clearly show your role. If a chart excerpt shows orders and interventions but does not indicate what you personally assessed or decided, the reviewer has to assume it was done by the attending or the team, and it does not count toward your portfolio. Always annotate your submissions with a brief note about your specific actions and clinical reasoning. Another frequent issue is recency. Some facilities require that all clinical evidence fall within a twelve-month window. Others allow older material if it is supplemented with recent examples. This varies by VISN, and the policy is rarely highlighted during orientation. Check your local competency handbook or ask your nursing education contact before you waste time pulling six-month-old documentation that will not count.
There is also the problem of over-submitting. More is not better. Reviewers are volunteers working alongside their regular duties, and a three-hundred-page packet gets skimmed. Twelve to twenty well-chosen pages with clear annotations is easier to evaluate thoroughly and tends to produce a faster turnaround. I recommend aiming for quality and relevance over volume.
When It Does Not Go Smoothly
Sometimes the review comes back with deficiencies. This is normal and not a reflection of your overall competence. The feedback will list specific gaps, and you usually get one revision cycle to address them. Do not get defensive or submit a rewritten packet that changes the original evidence. Fix exactly what was flagged and resubmit with a brief note addressing each point. In rare cases, reviewers disagree on whether submitted work meets the standard. This happens most often on borderline cases where the clinical judgment is sound but the documentation is thin. If you are in that situation, the best move is to ask for a clarification meeting rather than guessing at what additional evidence would satisfy the concern. One phone call with your competency council contact can resolve something that would otherwise stall for weeks. If your facility consistently has long backlogs on proficiency reviews, escalate through your nursing leadership. The VA has system-wide targets for turnaround time, and your manager can apply pressure if the delay is impacting your career progression or your ability to advance to Nurse III. I have seen reviews move from four months to six weeks after a charge nurse sent a polite but direct email to the VISN nursing education office citing the backlog timeline.

A Practical Note on Timing
Most VA facilities align proficiency reviews with your annual performance appraisal cycle, but the dates are not always synchronized. Some units do them in the spring, others in the fall, and a few operate on rolling submission windows. Find out your deadline early and build in buffer time. A realistic timeline from start to finished submission is about ten to fourteen business days for someone who is organized, and twenty to thirty days for someone who is starting from scratch and navigating an unfamiliar template. Keep a running folder on your work computer or a secure flash drive with completed competencies, CE certificates, and annotated case examples throughout the year. The people who struggle with this process are the ones who treat it as an annual emergency rather than an ongoing record-keeping habit. It takes maybe twenty minutes a month to stay current, and that saves you three weekends of panic during review season. The whole system is bureaucratic but functional. You do not need to be perfect. You need to be organized, honest about your development areas, and careful about documenting your own clinical contributions. The rest is paperwork.