What Actually Happens When You Map a Healthcare Process
Most people treat value stream mapping like a diagramming exercise. It is not. It is a measurement tool that reveals how long a patient actually spends in a system versus how long work is actually being done on them. The gap between those two numbers is where your improvement work lives. I spent three years trying to get teams to use this properly. The problem was not the method itself. The problem was that people drew boxes and arrows without going to the actual floor. They built a map from memory. Memory is wrong. That is why most healthcare VSM projects produce a pretty chart and no real change.
Value Stream Mapping In Healthcare Examples
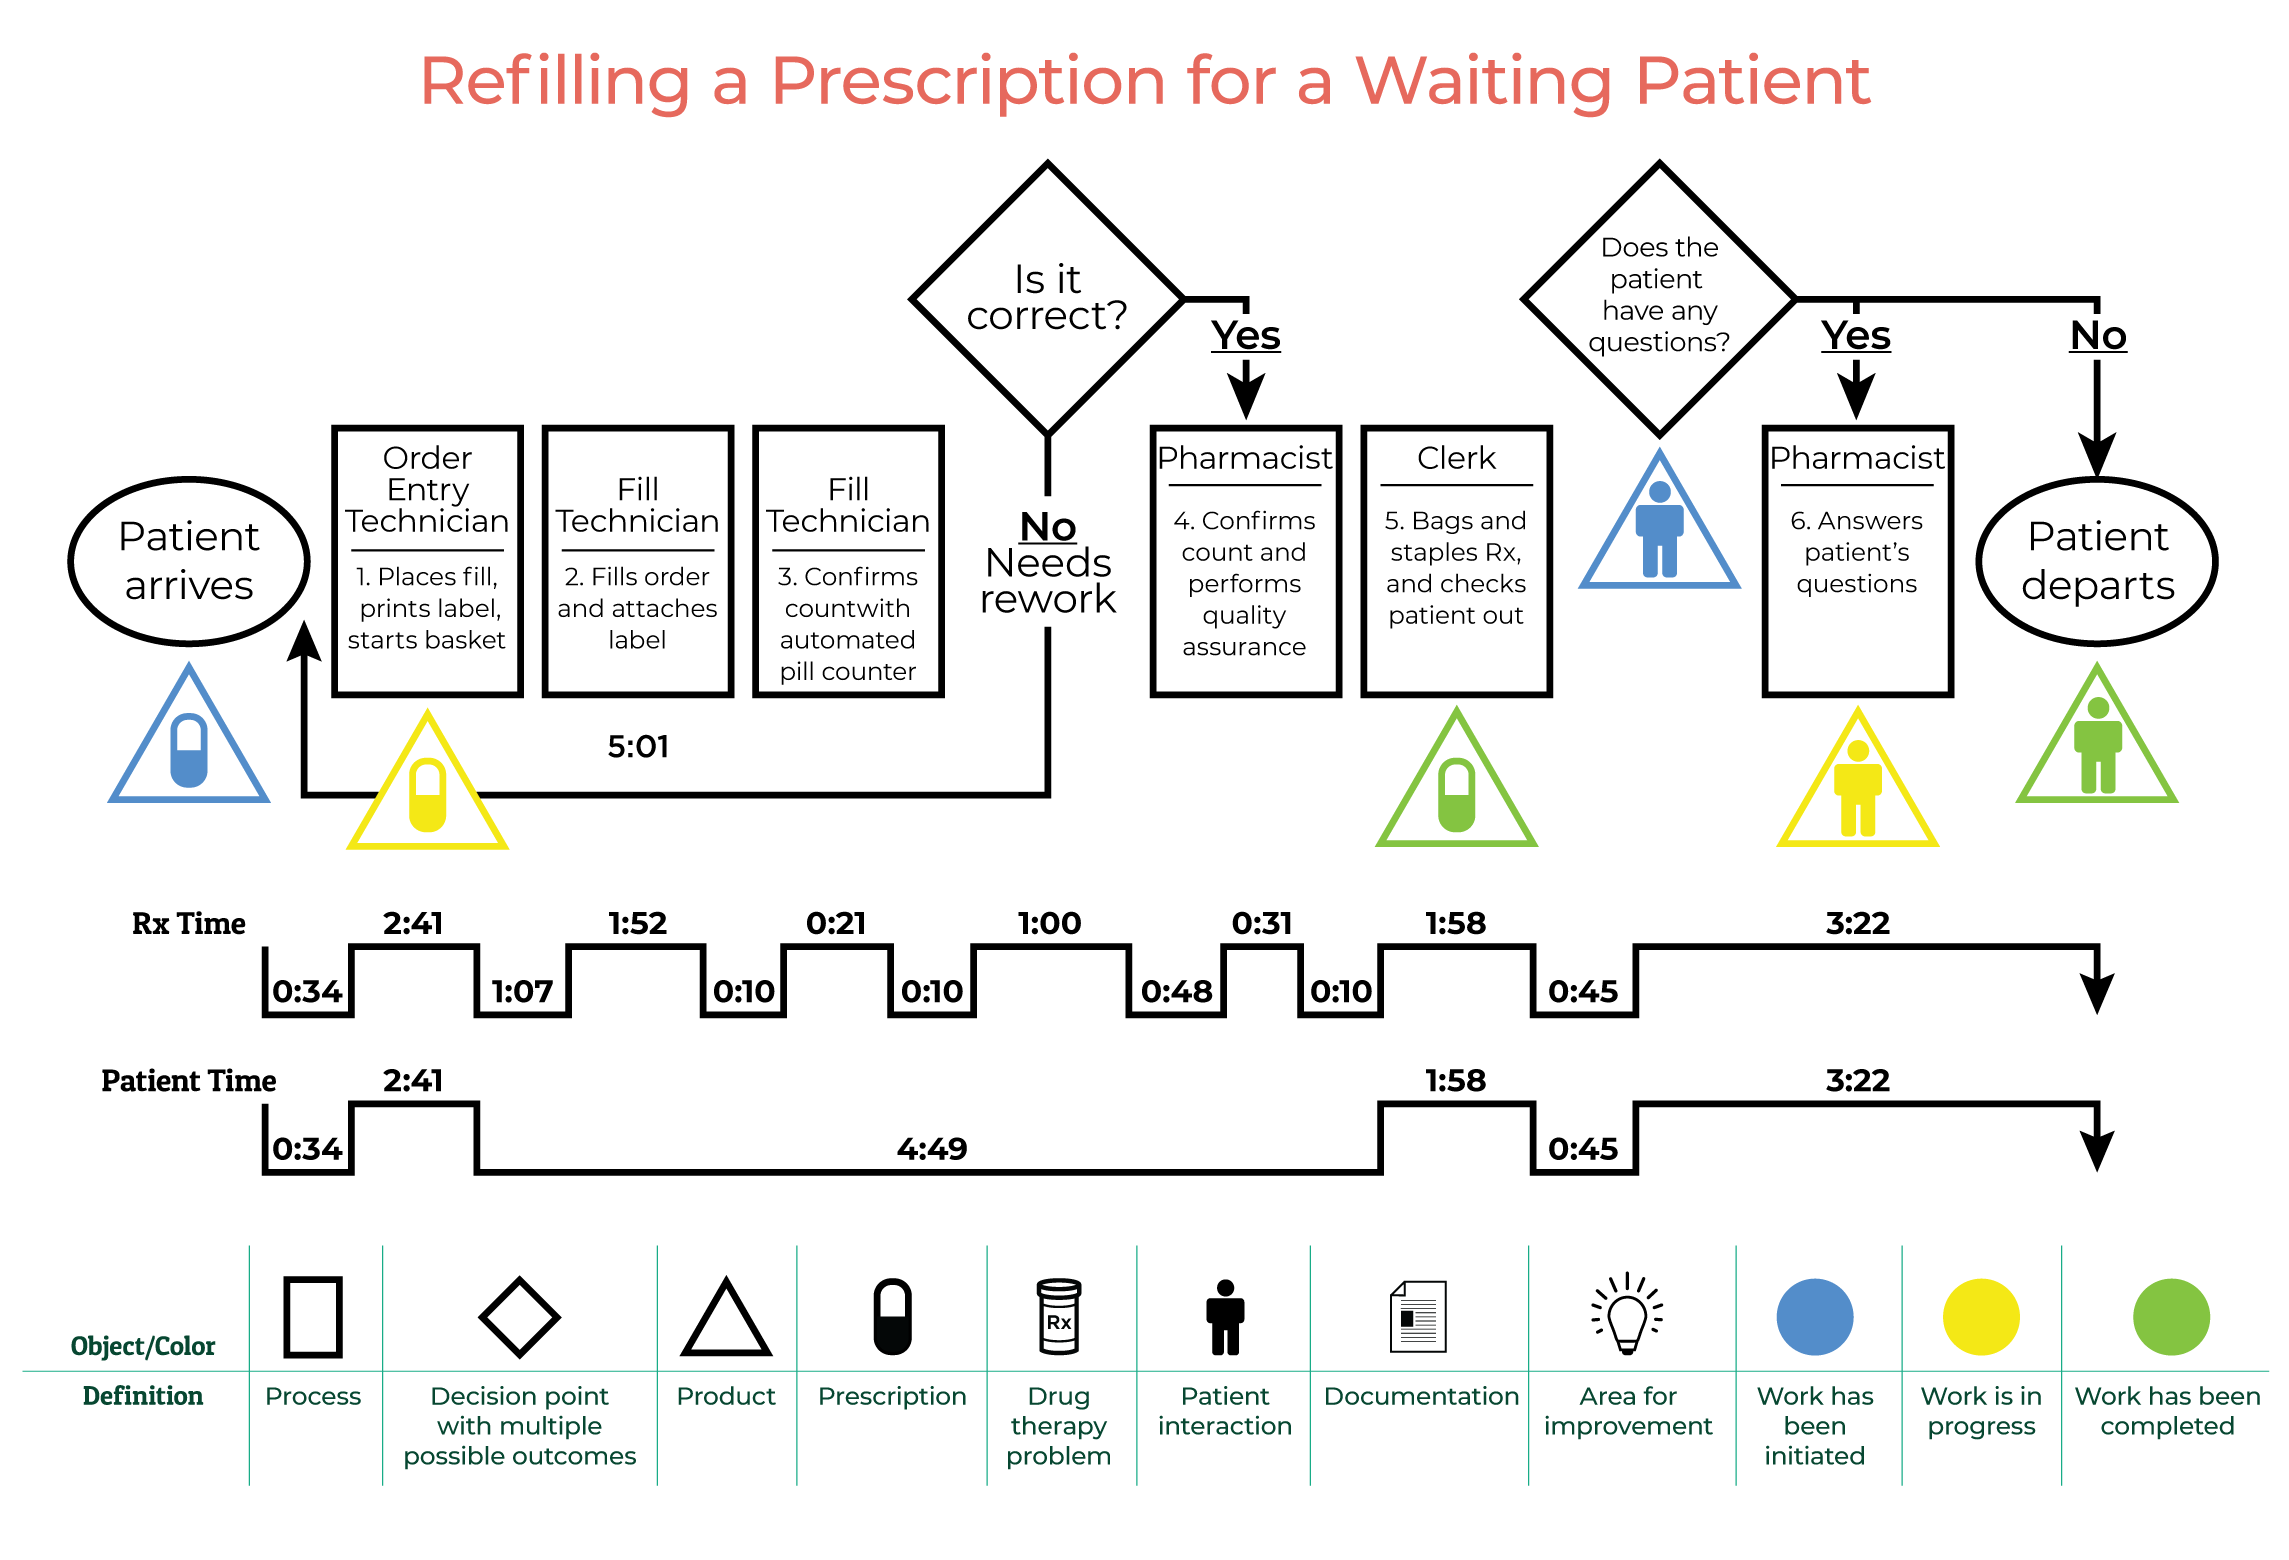
Before I walk through how to actually build one, here are a few real cases I have seen work. An outpatient imaging clinic mapped their MRI scheduling flow and found that 68 percent of the total lead time was patients waiting in the holding area because technologists were clearing imaging carts between patients. The actual scan time was four minutes. The cart cleanup took eleven. Fixing the cart process dropped total cycle time from 47 minutes to 19. A hospital discharge process showed that a single lab result was stuck in a physician inbox for an average of six hours before anyone saw it. The VSM revealed the result routing rule had changed two years ago during an EMR upgrade and nobody updated the team. Correcting the routing cut discharge paperwork time by roughly four hours per patient. A pharmacy verification step in an urgent care center showed 22 minutes of wait time that did not appear in the EHR logs at all. It was caused by a manual signature workflow that existed only on paper. The map made the invisible visible.
How To Build One Without Wasting Two Weeks
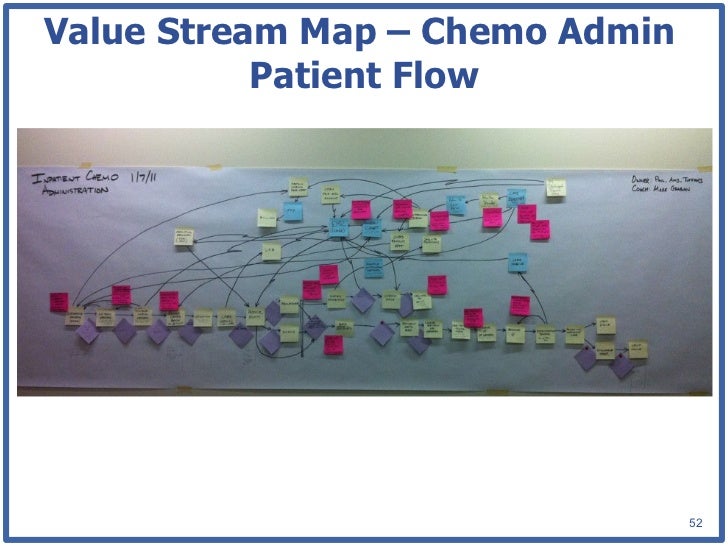
Start by picking a single patient journey, not a department. A journey has a clear start and end. Discharge is a journey. A radiology visit is a journey. "Lab testing" is not a journey because it overlaps with a dozen different processes. Pick something with edges. Go to the actual place where the work happens. Stand there. Watch real patients move through it. Time each step with a stopwatch or a phone app. Do not ask staff how long something takes. Ask them to show you. Their estimate will be wrong by at least 40 percent. I learned that the hard way on a pre-op scheduling project where everyone insisted the intake took ten minutes. It took 41. Draw the process flow first. Use sticky notes on a wall or a whiteboard. Keep it simple. One note per step. Arrange them left to right in the order they occur. Then add the timeline underneath each step. Write down the actual elapsed time, not the policy time. Policy says a nurse review takes 15 minutes. In reality it takes 3 hours because the pharmacist is out to lunch and the reviewing nurse is covering three units.
Get the Full Details
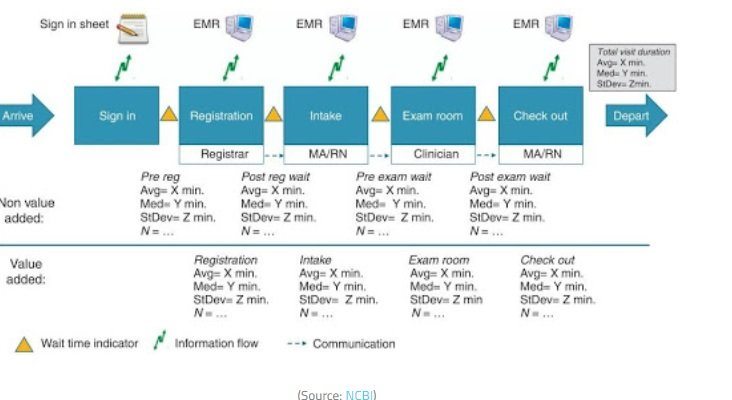
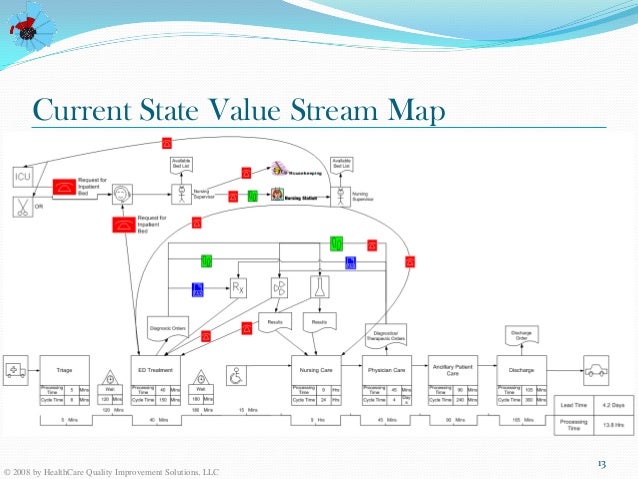
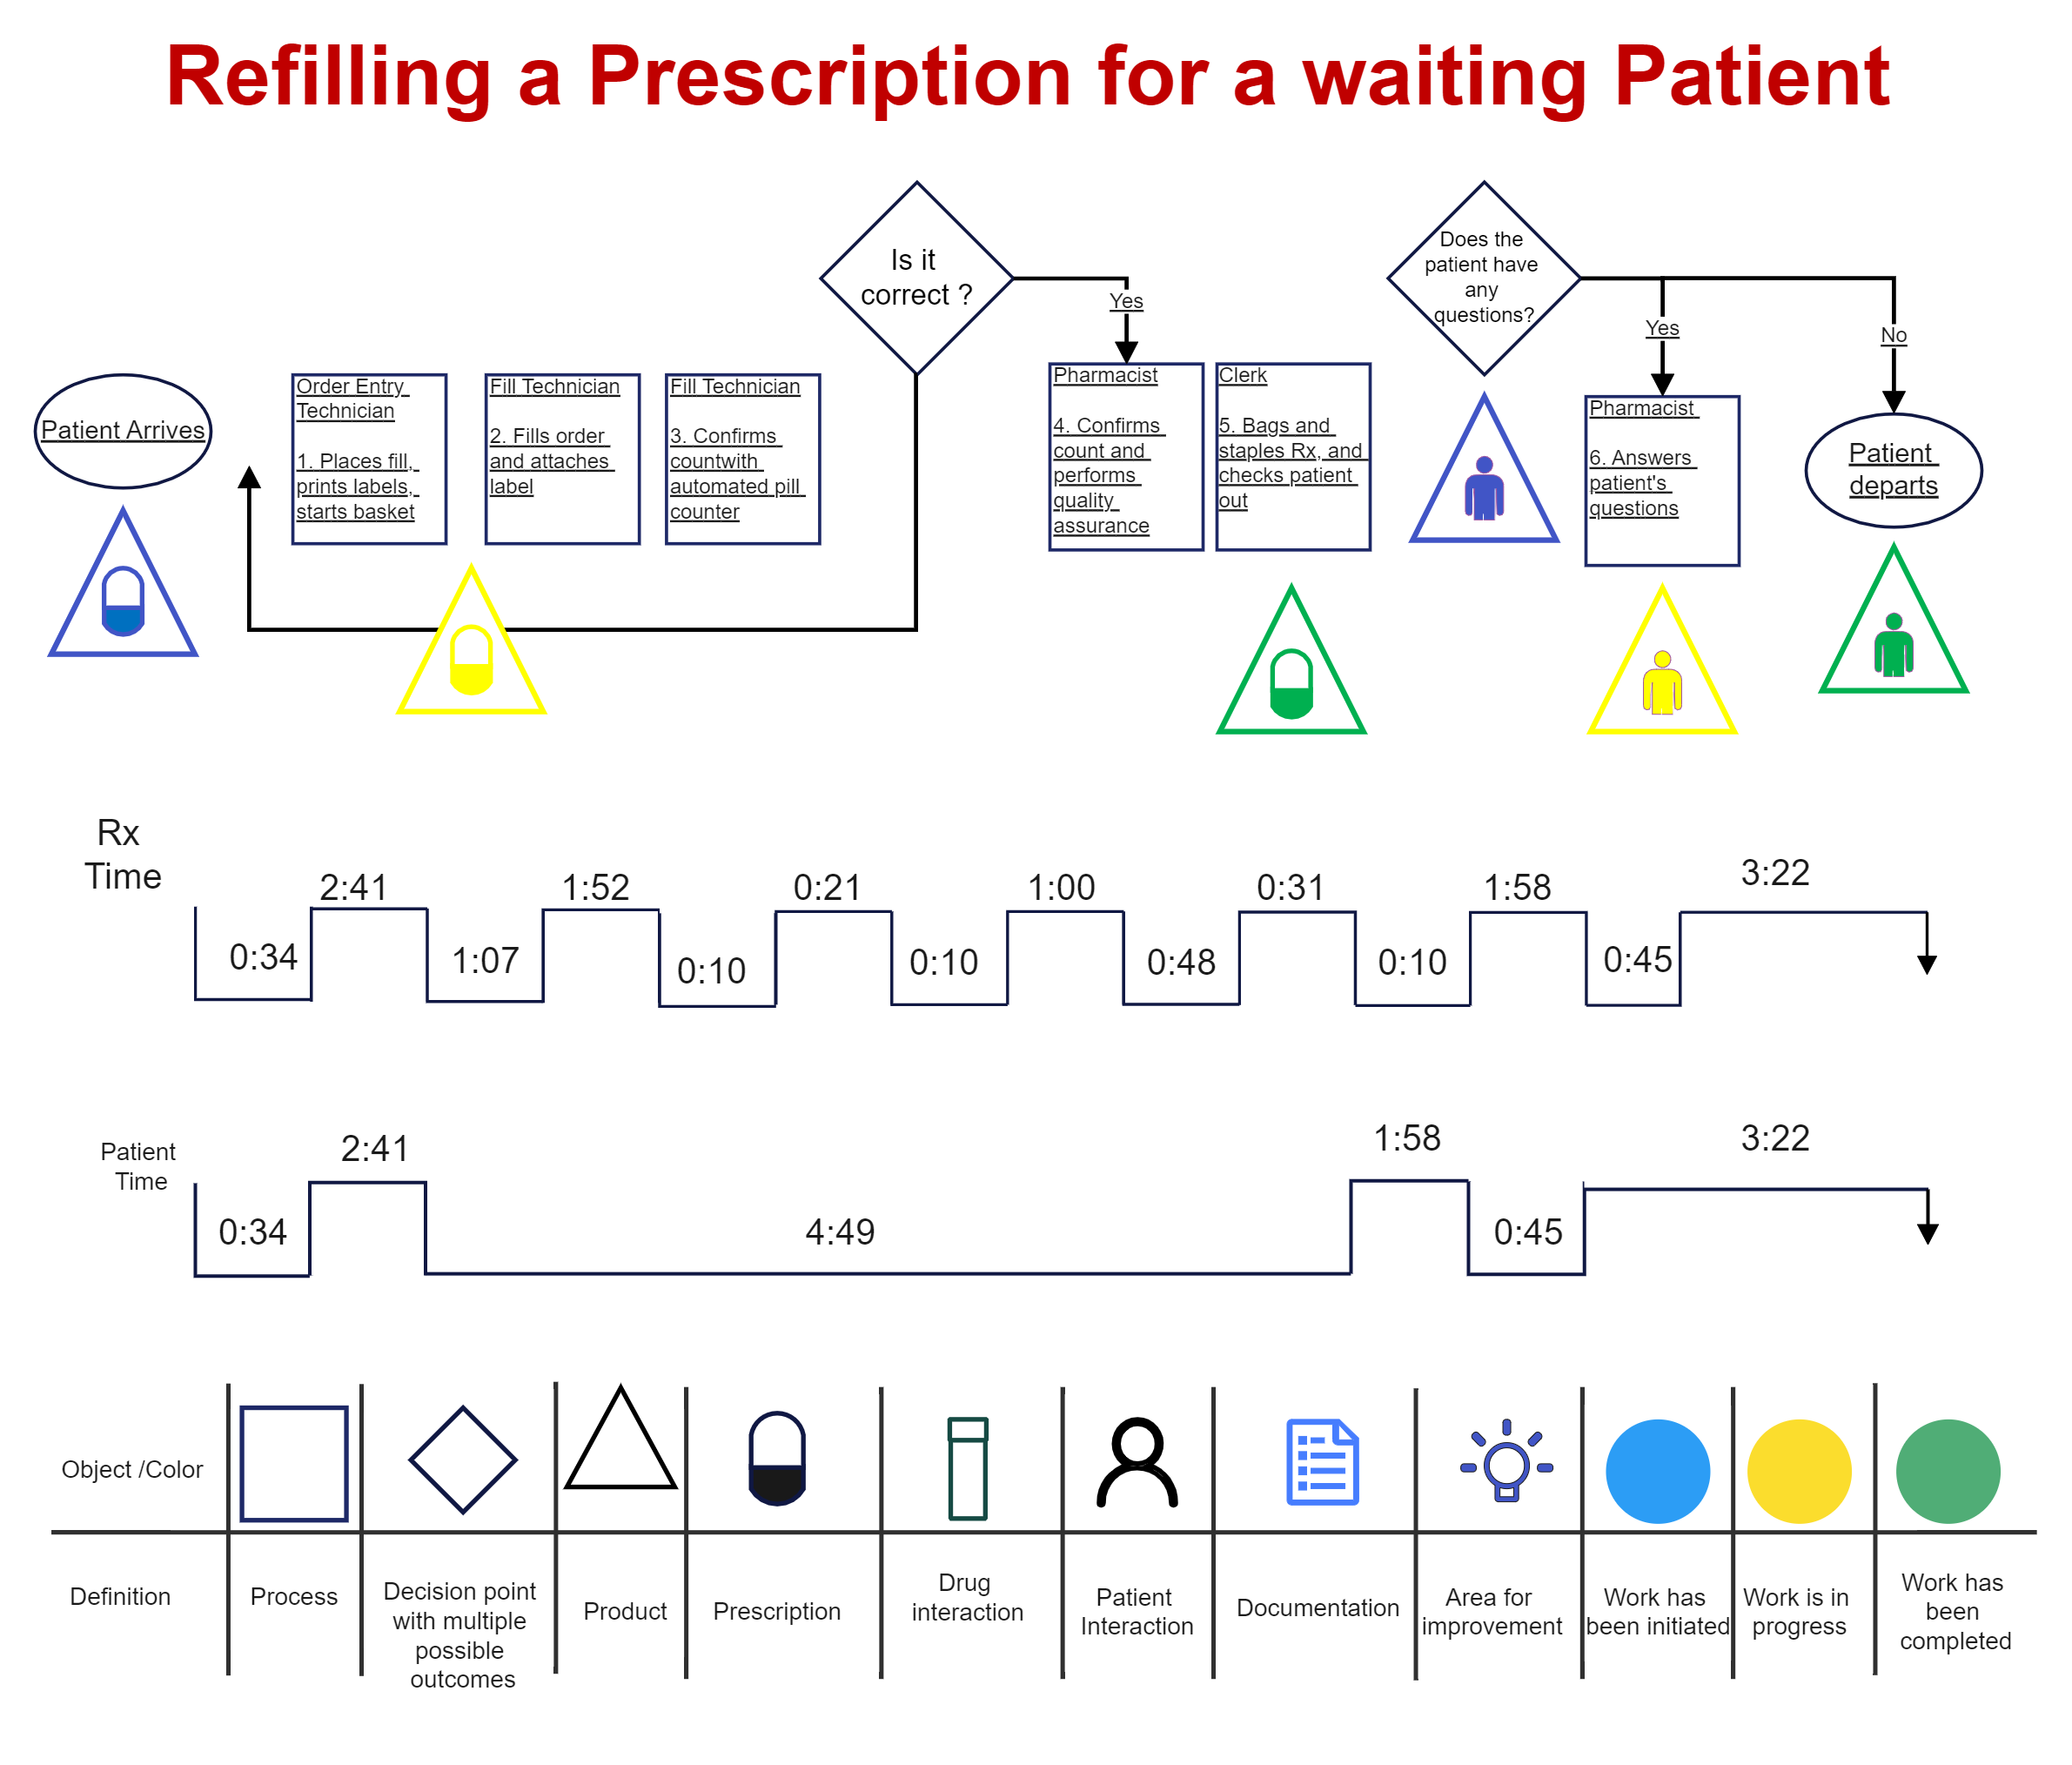
After the process flow, add the information flow. This is the part most people skip. Track every form, order, notification, or handoff that triggers the next step. Paper forms, emails, alerts, status pages. Map how information moves, not just how patients move. In healthcare, information delays are usually the bottleneck, not physical movement. Calculate the process cycle time by adding up only the steps where actual work is being done. Calculate the total lead time by measuring from the patient entering the process to the patient leaving it. Subtract the two. That difference is your waste. It is also your biggest opportunity.
Common Mistakes That Make The Map Useless
The first mistake is including every possible variation in one map. You cannot map elective surgery, emergency surgery, and follow-up procedures on the same diagram. They are different processes. Map one at a time. The second mistake is drawing timelines based on averages. Averages hide the outliers. If your step shows an average wait of 12 minutes, check whether that 12 minutes is seven minutes for 90 percent of patients and 45 minutes for the remaining 10 percent. In healthcare, the long tail usually tells the story. Draw separate timelines for the common case and the exception case. The third mistake is building the map alone. I used to try to do it myself when I was younger and faster. Now I bring together the person who does the work, a manager who authorizes changes, and a data person who can validate the numbers. Three people minimum. If you bring five, it slows down. If you bring two, you will miss something obvious.
A Specific Edge Case I Ran Into
Once, during a VSM project for a pediatric oncology infusion center, the map showed zero waiting time between the chemotherapy preparation step and the administration step. The numbers looked perfect. Then a nurse pointed out that the chart was wrong because the actual process included a mandatory double-check by a second pharmacist, but that second check was never recorded in the system. The workflow simply assumed it happened. The VSM had no data point for it. The workaround was to shadow a pharmacist for two full shifts and manually log every double-check event, regardless of whether the system captured it. We ended up adding 18 minutes of actual wait time that the original map had missed entirely. The final map showed 34 minutes of wait time, not zero. That was the improvement target. This happens more often than you would think. Electronic health records are terrible at capturing verification steps, handoffs, and informal communication. If your map looks too clean, it is probably wrong.
Advanced Nuance: The Takt Time Problem
One counter-intuitive thing about value stream mapping in healthcare is that takt time, the rate at which you need to complete a process to meet demand, is rarely constant. Manufacturing has steady demand patterns. Healthcare does not. A morning admission surge followed by a quiet afternoon is normal. A mass casualty event is not. When you calculate takt time for a healthcare process, use a rolling window rather than a single snapshot. A 48-hour rolling average during peak and non-peak periods gives you a number you can actually build against. A single hour of data will mislead you into thinking your process is under capacity when it is not. Another thing beginners miss is that the biggest waste in healthcare VSM is often the rework loop. A lab result comes back abnormal, the provider orders a repeat, the patient returns, and the cycle starts again. These loops do not show up on a linear map. You have to draw them as side branches and track how many patients fall into each branch. In one project, the rework loop for a single coagulation test accounted for 23 percent of total cycle time. The fix was not faster testing. It was better sample collection technique at the blood draw station.
When This Method Fails Completely
Value stream mapping does not work well for highly variable, low-volume, unpredictable processes. If your process involves rare diagnoses, custom treatments, or emergency protocols that happen once a month, the map will be so noisy that it is not useful. In those cases, run individual case reviews or use a different lean tool like A3 problem solving instead. The method also struggles when the bottleneck is external to your control. If your process depends on a transport service, a central lab, or a specialist who works across three hospitals, your map will show long waits that you cannot fix. Document the external dependency clearly and focus your improvement work on the steps you can actually influence.
Practical Resources
If you want a starting template, the Lean Health Institute offers a free printable VSM symbol legend and a basic healthcare worksheet. You can find it at leanhealth.org/resources. It is not perfect but it covers the standard symbols and the timeline format most people need. For a more detailed guide, the Medical Group Management Association has a practitioner workbook that walks through a full example using an outpatient surgery pathway. It is available through mgganet.com under their practice management section. You can also build your own map on a blank wall with sticky notes and a timer. That is often faster and more accurate than buying expensive software. The best tools are the ones people actually use.