What the Vanderbilt Assessment Scales Actually Are
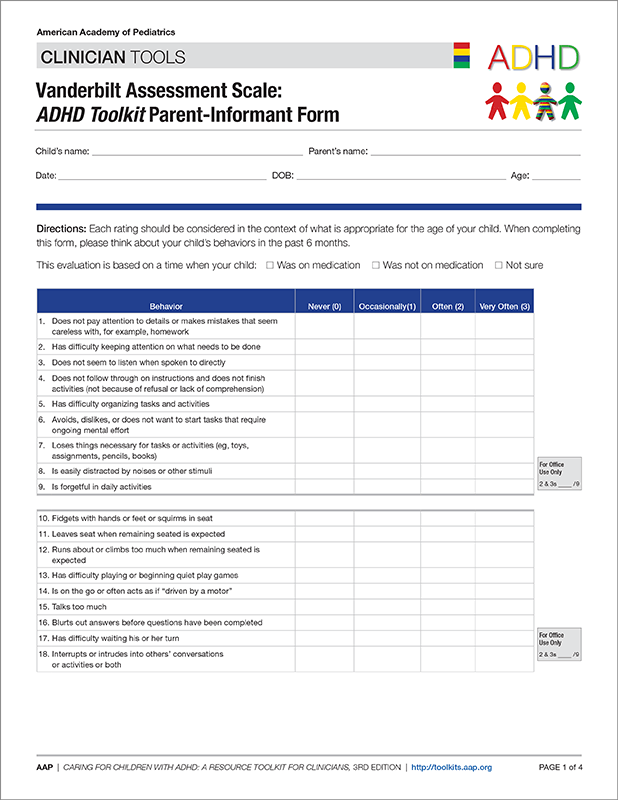
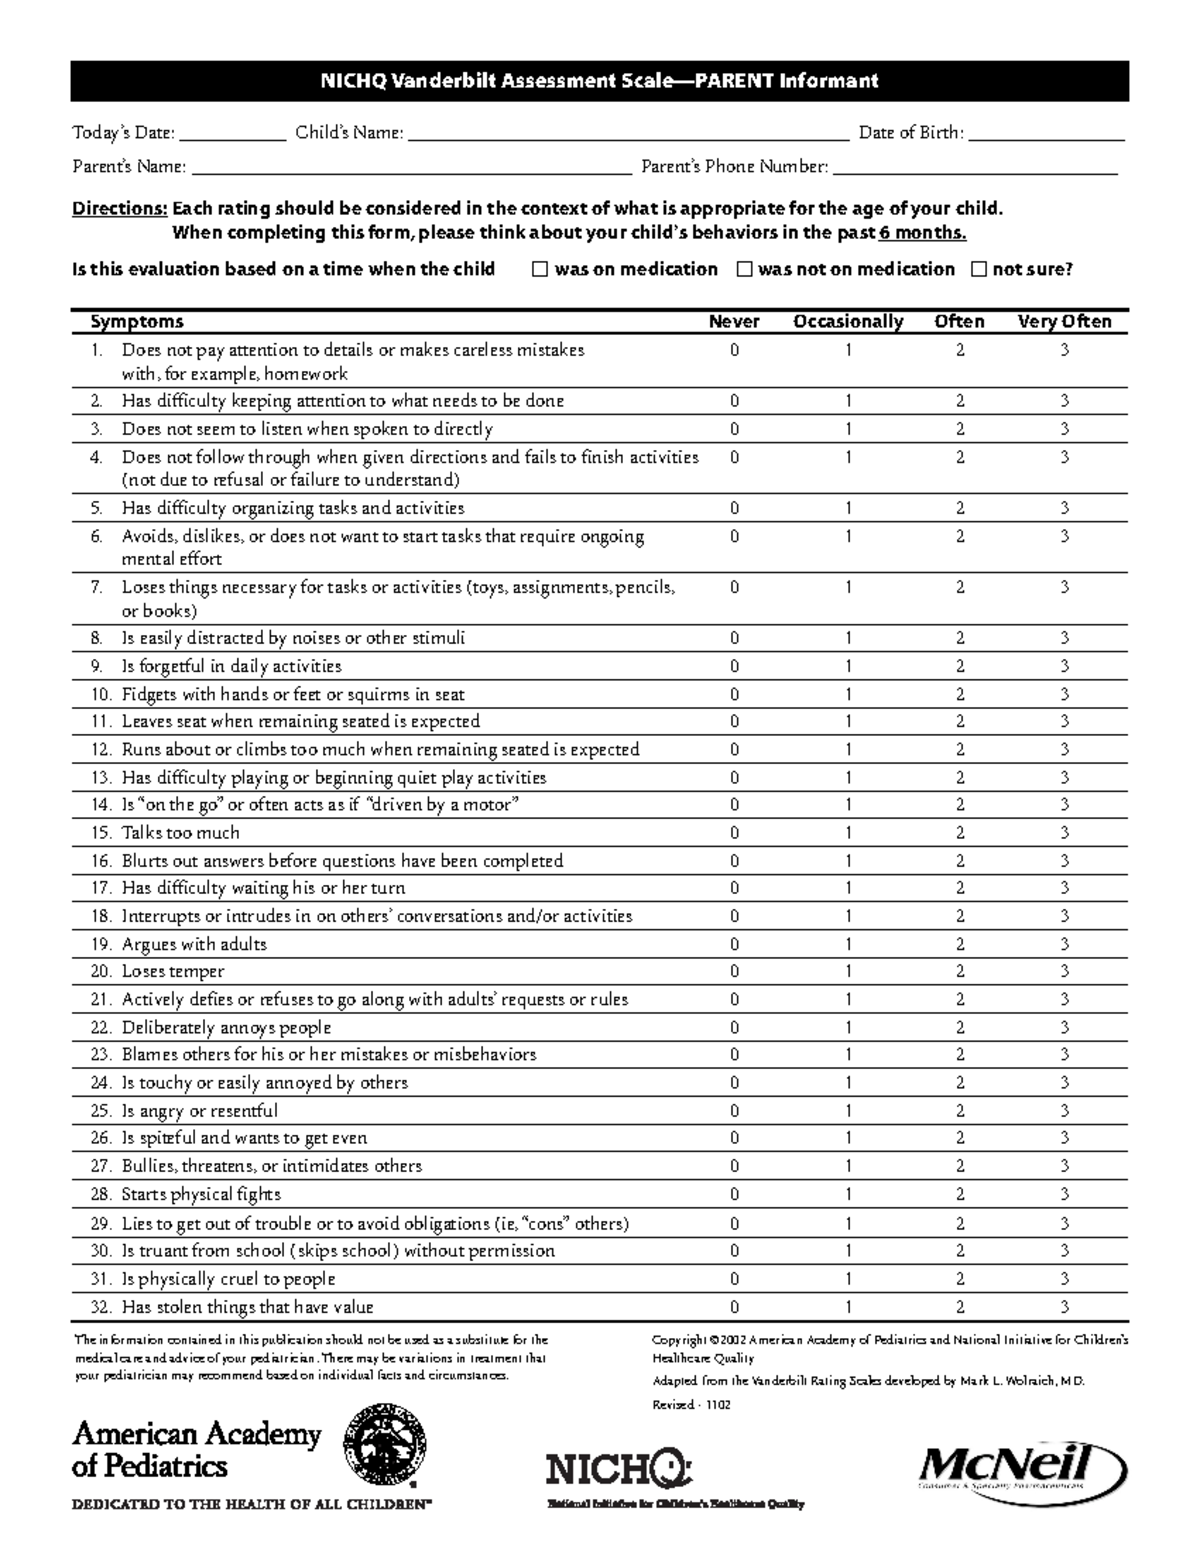
The Vanderbilt ADHD Diagnostic Rating Scale is a psychoeducational instrument, not a diagnostic tool on its own. It is a standardized rating form that screens for ADHD and comorbid conditions in children ages 6 through 18. The scale has two main versions: one filled out by parents and one filled out by teachers. Both forms cover the same core symptom clusters but come from different observation contexts. The parent version asks about behaviors observed at home and in the family environment. It covers inattentive symptoms, hyperactive-impulsive symptoms, and screening for oppositional defiant disorder and conduct disorder. It also includes items on learning concerns, sleep problems, and a functional impairment checklist. You get a free, public-domain copy from the CDC website or from the Vanderbilt University psychiatry department resource pages. No license fee, no paywall, no subscription required. Each item uses a four-point Likert scale: not applicable, occasionally applicable, often applicable, or very frequently applicable. To score the form, you count how many items in each DSM criterion cluster are rated as "often" or "very frequently" applicable. For inattention, that means counting the relevant items from the first symptom block. For hyperactivity-impulsivity, you do the same for the second block. A diagnosis requires a threshold number of endorsed symptoms, which typically means at least six out of nine in either domain for children under 17.
Here is where people commonly mess up: the impairment section is separate from the symptom count. A child can meet symptom thresholds but not show functional impairment, or vice versa. The impairment items ask whether the symptoms cause problems at home, with peers, at school, or in other activities. If the impairment items are all blank or negative, the scale suggests the findings may not be clinically significant regardless of symptom count. This is an important guardrail that most parents miss entirely.
Practical Experience with Real-World Administration
I have distributed and reviewed hundreds of these forms over the years. One recurring problem is parent response bias. A parent who is highly stressed, sleep-deprived, or dealing with a chaotic home situation will tend to endorse symptoms at higher rates than the child actually exhibits. I ran into this specifically with a family where the mother worked two jobs and the household was unstable. The completed form looked like textbook ADHD with full impairment across all domains. When I cross-referenced with the teacher version and conducted a structured interview, the picture was markedly different. The child's symptoms were situational, not pervasive. The workaround is straightforward but easy to overlook. Always require both parent and teacher versions before drawing any conclusions. If they conflict substantially, that discrepancy itself is clinically meaningful and warrants further evaluation. Do not accept a single form as sufficient evidence. Also, ask parents to consider the child's behavior over the past six months specifically, not just the current week or month, since ADHD criteria require symptom duration of at least six months.
Get the Full Details
Common Pitfalls That Adults Overlook
The Vanderbilt scale does not account for age of onset. A child might score high but have clear onset after age 12, which would rule out ADHD under DSM-5 criteria. The form itself has no field documenting when symptoms first appeared. You have to ask that separately, either through a clinical interview or by reviewing prior school records. Another issue is that the Vanderbilt was normed primarily on school-age children in the United States. It is not validated for adolescents in college or for adults, and you should not use it to screen anyone over 18. There are adult-specific instruments like the ASRS v1.1 that are far more appropriate for older populations. Using Vanderbilt on a college student is a category error. The scale also does not differentiate between ADHD presentations. It gives you combined, predominantly inattentive, and predominantly hyperactive-impulsive classifications based on which cluster crosses threshold, but it cannot capture subtle differences like what-appears-to-be-inattentive-that-is-actually-anxiety-driven or hyperactivity-that-is-actually-manic. Those distinctions require clinical judgment that the form alone cannot provide.
Where the Scale Falls Short
The Vanderbilt has real limitations. It relies entirely on observer report, which introduces recall bias, cultural interpretation differences, and the possibility that a parent or teacher misunderstands what constitutes a clinically significant symptom. A teacher might rate a quiet, Daydreamy child as low-risk when in fact that child is struggling severely internally. Conversely, a parent dealing with a genuinely challenging child might conflate normal developmental behavior with pathology. The comorbidity screening subscales for ODD and conduct disorder are crude. They flag possible concerns but cannot diagnose those conditions. If a parent scores high on the ODD items, the next step is a proper clinical assessment, not a conclusion drawn from the Vanderbilt alone. For these reasons, the Vanderbilt should be treated as a screening and monitoring instrument, not a standalone diagnostic tool. It is useful for initial identification, for tracking symptom changes over time during treatment, and for comparing ratings across settings. It is not sufficient to confirm or rule out ADHD by itself.
How to Use It in Practice
If you are a parent looking to use this form, start by downloading the current version from the official Vanderbilt or CDC source. Fill out the parent section honestly, going back over the last six months rather than focusing on recent events. Have the teacher complete the corresponding form independently without discussing answers with you beforehand. Bring both completed versions to the evaluating clinician along with any existing school records or prior evaluations. Do not submit only one form and expect a complete assessment. If you are a clinician using this instrument, administer both versions whenever possible, score carefully against DSM-5 thresholds, and use the impairment section to determine clinical significance. Consider supplementing the Vanderbilt with additional measures such as continuous performance tests, rating scales from other sources like Conners or BASC-3, and a thorough developmental and family history. The scale is a starting point, not an endpoint.


