Getting the Vanderbilt ADHD Teacher Assessment Form Sorted Out
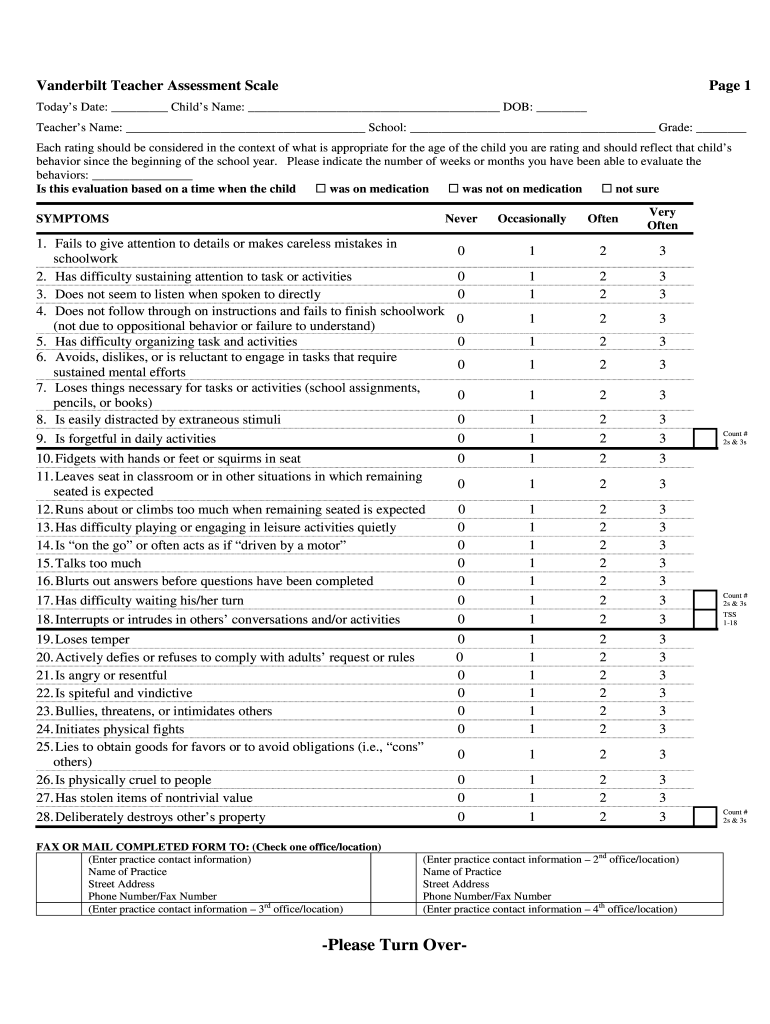
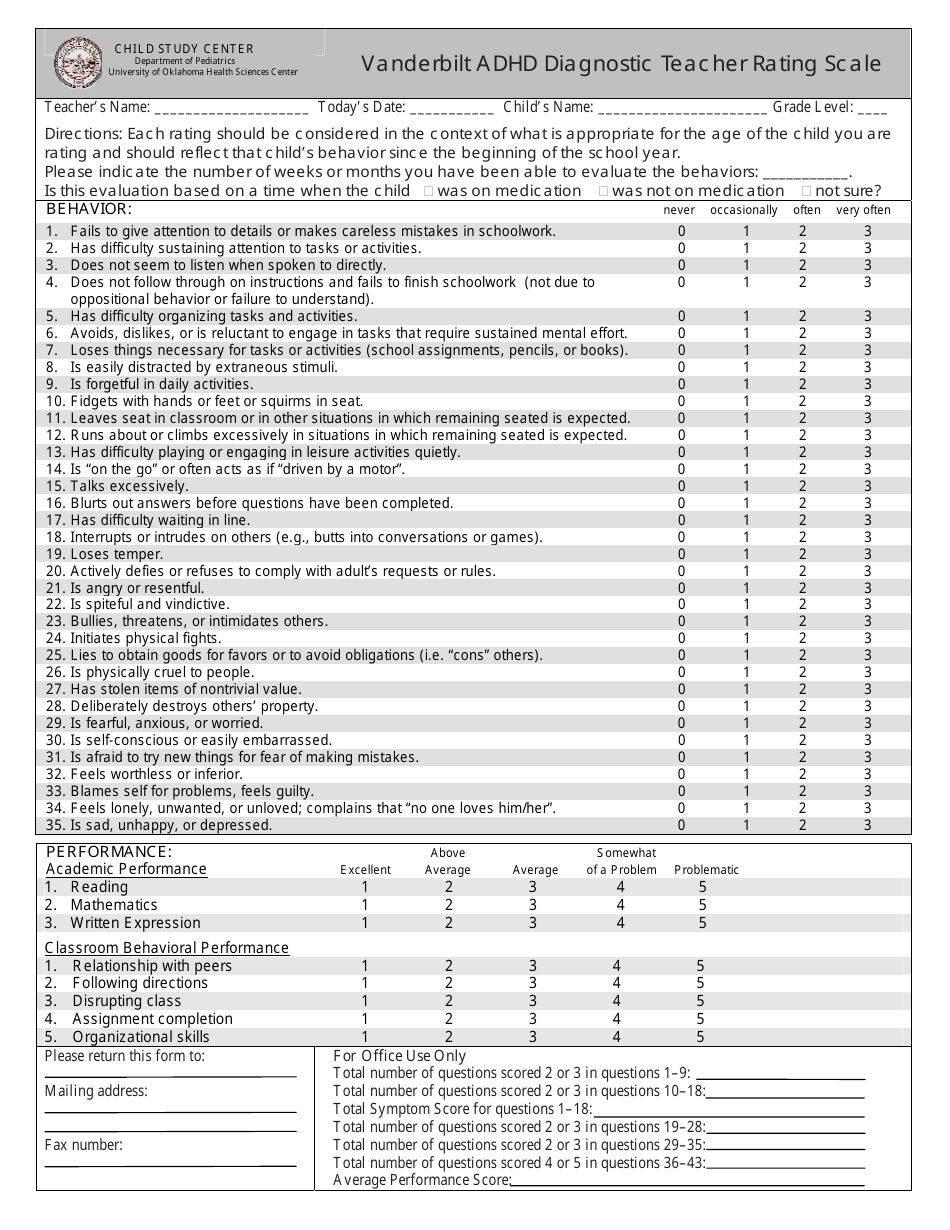
The Vanderbilt ADHD Diagnostic Rating Scale is one of those tools you see everywhere once you start paying attention. It's the most commonly used teacher-rated screening instrument in pediatric settings, and for good reason. It's free, it's brief, and it covers the DSM criteria pretty cleanly. But using it right isn't as simple as printing off a PDF and sliding it into a desk drawer. I've spent years watching people misuse this form. Teachers fill it out without understanding what they're rating, parents get confused between the different sections, and schools treat it like a compliance checkbox instead of a diagnostic aid. The form itself is straightforward. The implementation is where things fall apart.
Vanderbilt Adhd Teacher Assessment
Here's how to actually use it without generating garbage data. First, get the current version from a legitimate source. The original was published by the American Academy of Pediatrics and is available through several free clinical repositories. Make sure you're looking at the official form with all three parts: Part A and B cover the 18 DSM symptoms split into inattentive and hyperactive-impulsive clusters, Part C measures performance impairment across settings, and the supplementary sections cover oppositional defiant disorder, anxiety, and learning metrics. The critical detail everyone skips is the Likert scale direction. Each symptom is rated on a 0-3 scale: 0 is "never," 1 is "sometimes," 2 is "often," and 3 is "very often." The cutoff for clinical significance is a rating of 2 or 3 on at least six of the nine inattentive items or six of the nine hyperactive-impulsive items, plus evidence of impairment on the Part C section. Get that wrong and you're either over-referring or missing kids who actually need help. I remember a case where a teacher completed the form for a student who would act out during transition times but functioned perfectly during structured blocks. She marked "very often" on items about losing things and difficulty sustaining attention, which spiked the inattentive score. But those behaviors were context-dependent, not pervasive. The workaround I used was to ask her to rate each item separately for math class, reading time, and group work. That breakdown revealed the inattention was really boredom-driven, not ADHD. The raw form without that kind of follow-up would have sent that kid down a completely wrong path.
Practical Distribution and Collection
Send the form home with the student at the beginning of a grading period, not mid-semester when someone is already frustrated. Teachers need at least three to four weeks of observation across different subjects and activities to give reliable ratings. A form completed after two weeks of a difficult unit will inflate scores regardless of whether ADHD is present. Collect them anonymously when possible. If teachers know which student the form is about before they fill it out, behavioral biases creep in. I've seen forms where the teacher's overall impression of a "difficult" child inflated every score uniformly, making it impossible to distinguish between ADHD symptoms and general classroom management problems. Having them complete it blind to the student's identity before revealing which child they're rating makes a measurable difference in data quality. Part C is where most people botch interpretation. The impairment section asks about performance at home and at school across five domains: academic, social, family, community, and extracurricular. You need at least moderate impairment in two or more domains to meet the functional impairment criterion. A kid who scores high on symptoms but has zero impairment in multiple settings doesn't meet the threshold, and that's by design. The DSM requires both symptom presence and functional impact.
Get the Full Details

One thing the form doesn't capture well is twice-exceptional students. Kids who are gifted and have ADHD often mask their symptoms in structured environments where they can intellectually compensate. A teacher might rate these kids as "sometimes" on almost everything because the child keeps up academically. The impairment shows up in Part C as perfectionism, anxiety, or social friction rather than classic attention deficits. If you're seeing low symptom scores but clear functional problems, consider whether the child might be compensating at a cost that the Vanderbilt form won't show you directly. When you receive the forms back, verify completion before sending follow-ups. Incomplete forms are worse than useless because they create false certainty. A partially filled form suggests the teacher didn't have enough exposure to the student's behavior across settings, which is itself data. Flag it and redistribute rather than working with incomplete information.
Scoring Pitfalls
Don't convert raw scores to percentages and call it analysis. The scoring is categorical, not continuous. A score of 27 out of 54 on the inattentive subscale sounds like half the symptoms are present, but the diagnostic threshold is specifically six out of nine items at severity level 2 or 3. Percentage calculations obscure that binary distinction and invite people to draw conclusions the tool wasn't designed to support. The ODD screening section on the supplementary form is often overlooked but clinically important. About a third of children with ADHD also meet criteria for oppositional defiant disorder, and the comorbidity changes treatment planning significantly. If a child scores in the clinically significant range on that section, factor it into the referral conversation rather than treating it as background noise. The form has limitations that nobody talks about enough. It's a screening tool, not a diagnostic instrument. A positive screen should trigger further evaluation, not confirm ADHD. School psychologists sometimes use it as if it's conclusive, which creates problems when the child is later evaluated elsewhere and the results differ. The Vanderbilt is meant to be one data point among many: parent rating, clinical interview, cognitive testing if indicated, and observation across settings. Treat it as a starting line, not a finish line.
Another gap is cultural bias. The language assumes neurotypical classroom behavior as the baseline. Children from different cultural backgrounds may express restlessness or inattention differently, and the fixed response options don't account for that variability. I've had situations where teachers from one cultural background rated a child's behavior as pathological when that same behavior was considered normal in the child's home culture. Discussion with the family and consideration of cultural context matters more than the raw score.
Where to Access the Form
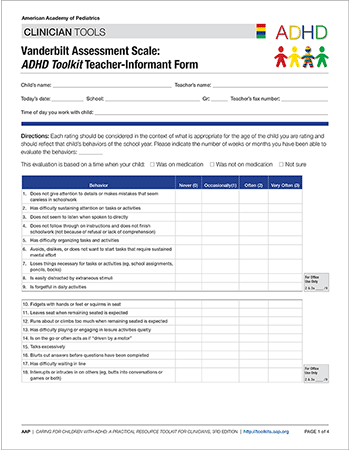
The official Vanderbilt ADHD Diagnostic Rating Scale is in the public domain and can be downloaded from the American Academy of Pediatrics website or the HealthyChildren.org portal. There are also copies hosted by state Department of Education websites and pediatric practice networks. Avoid third-party sites that charge money for it. The original is freely available, and any platform selling it is just repackaging public clinical material. Make sure you download the correct version. There are separate forms for parents and teachers, and they look nearly identical but serve different functions. The teacher form asks about behavior in the classroom setting specifically. Using the parent form for teacher input or vice versa throws off the ecological validity of the data since the contexts are different by design. Keep a record of which version you're using and the date. The form has been around since the late 1990s and there have been minor revisions. Some districts use older versions that may have slight wording differences, and those differences can affect how teachers interpret items. Consistency matters if you're tracking the same child over time across multiple school years.