Managing Crohn's on a Plant-Based Diet
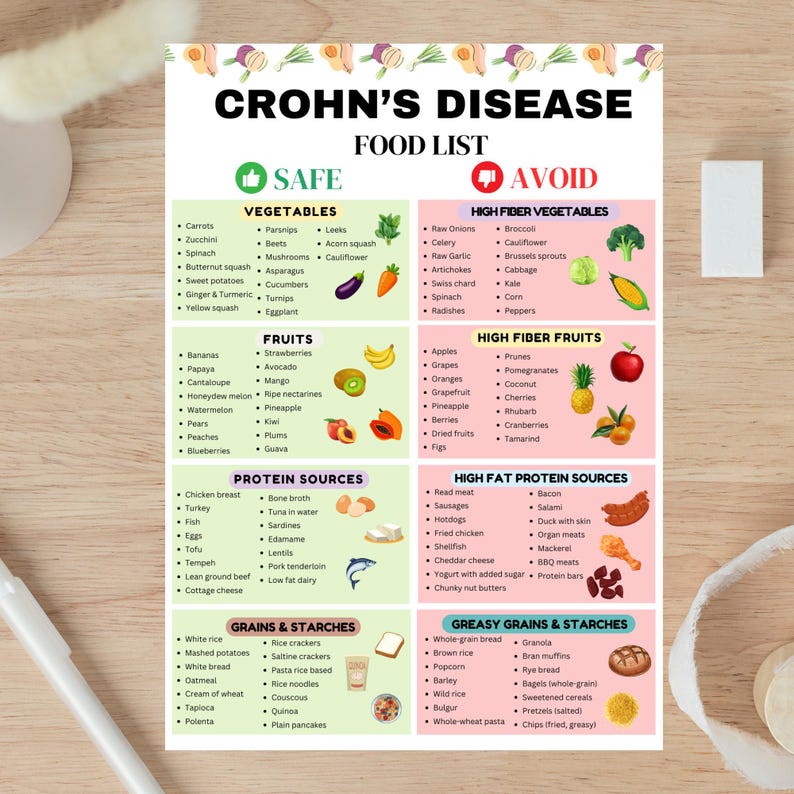
It is possible to manage Crohn's disease while eating vegan, but it requires more deliberate planning than most people realize. The conflict is straightforward: standard vegan eating patterns emphasize whole grains, legumes, raw vegetables, and high fiber, all of which can irritate an inflamed digestive tract. Crohn's flares typically demand the opposite—low residue, easily digestible foods. Learning to navigate between these two requirements is where most people struggle. The core principle is flexibility. You are not following one fixed diet. You maintain at least two distinct eating protocols depending on whether you are in remission or actively flaring. During remission, a more varied plant-based diet is usually tolerable. I still avoid extreme fiber sources like raw kale, popcorn, corn, and nuts with skins. Roasted or well-cooked vegetables work fine for most people.lentils and beans are tolerated by some but not others, so introducing them slowly is necessary. Oats, rice, quinoa, and tofu are reliable staples that most people with Crohn's handle without issues. The goal during remission is maintaining nutritional adequacy while gradually expanding variety.
During flares, the diet narrows significantly. This is where things get uncomfortable because many people expect a vegan Crohn's diet to look like salads and smoothies. It does not. During active inflammation, you are looking at white rice, refined pasta, peeled potatoes, banana, applesauce, well-cooked carrots, and possibly some tofu or tempeh if those proteins are tolerated. Raw vegetables are off the table. Legumes are usually off the table. High-fiber whole grains are off the table. Think bland, low-residue, easy to pass through a narrowed intestine without causing obstruction or irritation. The transition between these two states is where people get caught. Going from a flare-safe diet back to a varied vegan diet too quickly is a common mistake. I once had a patient who felt great after a flare settled and immediately returned to her usual intake of raw vegetables, beans, and nuts. She was back in the hospital within three days with another flare. The rule is to reintroduce foods one at a time, waiting three to five days between each new addition, so you can actually identify what is causing problems instead of guessing after a disaster.
Nutritional Considerations That Matter
Vegan Crohn's management has specific nutritional risks that go beyond what applies to the general vegan population. Malabsorption is the key word here. Crohn's commonly affects the terminal ileum, which is where vitamin B12 is absorbed. If your ileum is inflamed or has been surgically removed, oral B12 supplementation may not be sufficient and you may need injections regardless of how much fortified food you consume. This is not something to discover after you have developed neurological symptoms. Iron deficiency is another major concern. Plant-based iron (non-heme iron) is less bioavailable than animal-based iron, and Crohn's can cause chronic blood loss in the intestinal tract. Pairing iron-rich foods with vitamin C helps with absorption, but this only matters if you are not currently experiencing a flare that prevents absorption altogether. In those cases, intravenous iron or supplements under medical supervision are necessary. Calcium and vitamin D are concerns for anyone on a vegan diet, but they are especially relevant for Crohn's patients because many are on corticosteroids during flares, which accelerate bone density loss. Fortified plant milks, calcium-set tofu, and supplementation are standard recommendations. A DEXA scan every one to two years during active treatment is worth doing rather than skipping.
Get the Full Details

Omega-3 fatty acids deserve attention. The anti-inflammatory properties of alpha-linolenic acid from flaxseed, chia, and walnuts may help some people with IBD, though the evidence is mixed. The practical recommendation is to include a source of ALA daily and consider an algae-based DHA/EPA supplement since the conversion rate from ALA to the longer-chain forms is poor in most people. Zinc deficiency is frequently overlooked. Zinc absorption happens primarily in the small intestine, which is often affected in Crohn's. Vegan diets contain phytates that inhibit zinc absorption, making the problem worse. Pumpkin seeds, cashews, and legumes are decent sources when tolerated, but supplementation may be necessary during periods of poor absorption.
Practical Meal Framework
A simple way to structure meals depends on your current disease state. Remission meals: Base of cooked grains like quinoa or brown rice. Well-cooked vegetables such as zucchini, spinach, or sweet potato. A protein source like tofu, tempeh, or lentils if tolerated. Healthy fats from olive oil or avocado. Fruit like banana or canned peach. Flare meals: White rice or refined pasta as the base. Peeled, well-cooked vegetables only. Tofu or smooth nut butters if those proteins are tolerated. Banana or applesauce for fruit. Small frequent meals are easier to handle than three large ones because they place less demand on an inflamed digestive system at any one time.
Hydration matters more during flares because diarrhea increases fluid and electrolyte loss. Oral rehydration solutions or broth-based soups are more useful than plain water during active symptoms. The standard sports drinks are acceptable in a pinch, though the artificial sweeteners in some can worsen diarrhea for certain people.

What This Approach Cannot Do
A vegan Crohn's diet is not a treatment for Crohn's disease. It does not induce remission through some magical anti-inflammatory mechanism. It is a dietary framework that can coexist with medical treatment and may reduce certain triggers, but it should never replace prescribed medication or medical supervision. Some people promote plant-based diets as a cure for IBD. This is not supported by the evidence and relying on diet alone instead of proper medical care has resulted in preventable hospitalizations and surgical interventions. The diet also does not work the same way for everyone. Crohn's is heterogeneous, meaning the location and severity of inflammation vary significantly between individuals. Someone with colonic Crohn's may tolerate more fiber than someone with stricturing small bowel disease. An individualized approach guided by a gastroenterologist and a registered dietitian who understands both IBD and vegan nutrition is the most reliable path forward. Food diaries are useful but only if you record accurately. I have seen people write down what they thought they ate rather than what they actually ate, then wonder why their symptoms do not match their identified triggers. Recording everything including oils, condiments, and snacking habits for at least two weeks during a flare provides more actionable data than a vague recollection of "healthy eating."