Understanding The Vasculature Of The Upper Limb
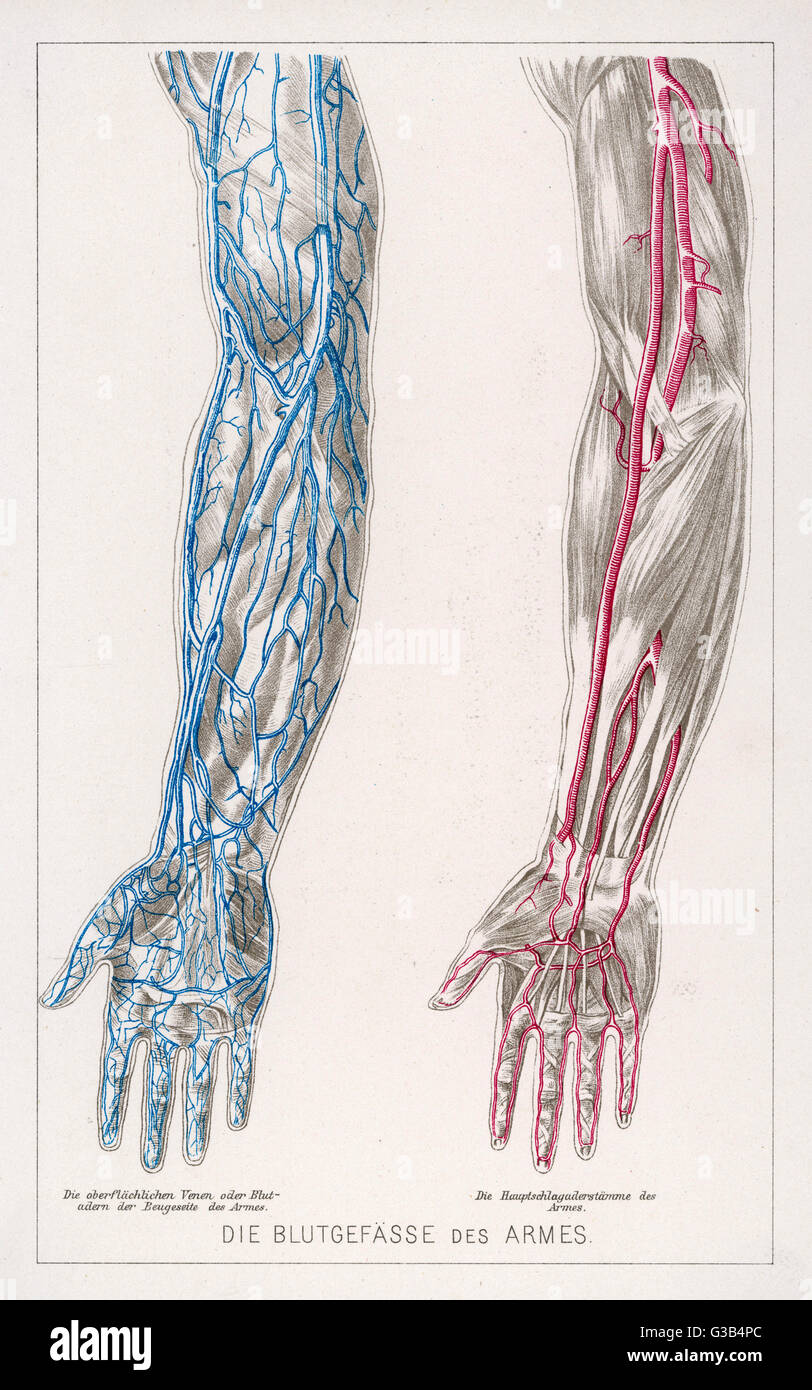
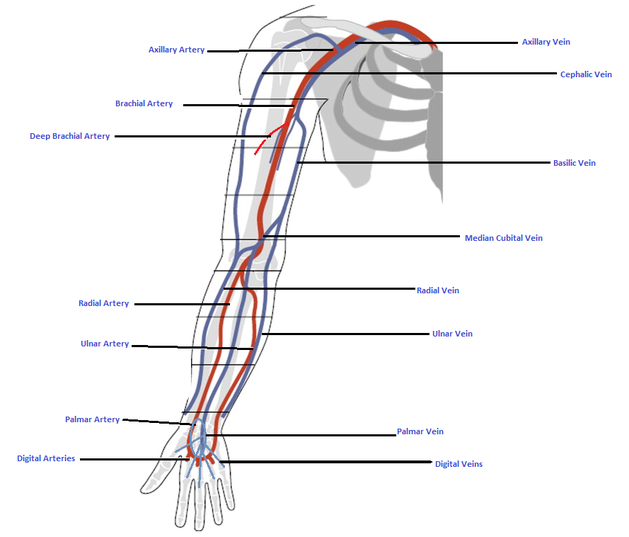
The blood supply to your arm follows a pretty predictable pattern from a gross anatomy standpoint, but when you actually get down to it - whether you are studying for dissection labs or trying to understand vascular access points - there are nuances that textbooks gloss over. The brachial artery runs as the direct continuation of the axillary artery and travels down the anterior compartment of the upper arm. It is what most people think of as the "main artery of the arm," and it gives rise to the profunda brachii, which supplies the triceps and hugging the humerus in the radial groove. That last part matters clinically because fractures of the mid-shaft humerus can injure that vessel. The bifurcation into the radial and ulnar arteries typically happens around the level of the cubital fossa, deeper than most students realize. You will feel the pulse at the lateral aspect, but anatomically the split occurs more medially and proximally than surface landmarks suggest. Both arteries then give off significant branches before continuing distally. The radial artery is the one you use for checking pulses at the wrist, and it forms the superficial palmar arch along with contributions from the ulnar.Veins And Arteries Of Arm
The venous system is a whole different beast. The arm has two parallel systems: superficial and deep veins. The superficial veins - cephalic, basilic, and median cubital - are what you see and what phlebotomists use. They do not follow the same names as the accompanying arteries except at the hand and forearm where they generally share the arterial name with "superficial" added. Here is something counter-intuitive that I learned the hard way: the basilic vein does not reliably drain into the brachial vein at the level most anatomy texts show. In my experience, about 15 to 20 percent of people have an anomalous termination where the basilic joins the axillary vein much higher up, sometimes at the level of the third rib rather than near the coracobrachialis. If you are doing central line placements or venous mappings based purely on textbook diagrams, that discrepancy will bite you. My approach was to use ultrasound pre-procedure rather than relying on anatomical assumption. A quick longitudinal scan from the antecubital fossa upward tracing the basilic takes about thirty seconds and shows exactly where it joins the deep system. That saved me from a botched IV insertion on a patient who needed reliable venous access for contrast studies.
The deep veins accompany their corresponding arteries as venae comitantes - usually paired veins flanking a single artery. These are less variable in their course, which is probably why they are described more consistently in atlases. The brachial veins are typically paired and join to form the axillary vein at the inferior border of the teres major muscle. At the forearm level, the radial vein pairs with the radial artery and supplies drainage from the lateral forearm and thumb side of the hand. The ulnar vein does the same on the medial side. The interosseous veins, which drain between the bones, connect both systems and provide important collateral pathways. When one major vessel is obstructed, these connections matter. I encountered a case once where a patient had a partially thrombosed ulnar vein from repeated catheter placements, and the interosseous system was carrying enough flow to keep the hand perfused without obvious ischemic symptoms. The arterial system has its own collateral networks. The anastomosis around the elbow is dense and involves the radial recurrent artery, ulnar recurrent artery, and the interosseous recurrent branch. This is why you can sometimes maintain distal perfusion even when the brachial artery is occluded proximally - the collateral circulation through these recurrent branches can sustain flow to the forearm and hand. It is not ideal, and the pulses will be diminished, but it is the reason upper extremity amputations below the elbow are sometimes viable even with proximal arterial injuries.Palmar Arch Details And Clinical Relevance
The superficial palmar arch is primarily ulnar in origin but receives a radial contribution through the superficial palmar branch. It gives rise to the common palmar digital arteries. The deep palmar arch is primarily radial in origin and lies deeper, giving off the proper palmar digital arteries and the deep branch that anastomoses with the ulnar system. Most people have a dominant arch over the other, and the one that is less prominent varies between individuals. When I was doing vascular surgery rotations, we had a case where a patient presented with hand ischemia and all non-invasive testing pointed to a proximal blockage. The angiogram revealed an incomplete superficial palmar arch - the ulnar artery contribution was essentially absent, making the hand entirely dependent on the deep arch. That variation meant any thrombotic event in the radial artery would be catastrophic for perfusion. The surgical team had to go straight to embolectomy rather than attempting endovascular approaches first because the marginal collateral capacity left no room for delay.For imaging purposes, duplex ultrasound is the workhorse. It shows flow direction, velocity, and can detect stenoses down to fairly significant degrees. Magnetic resonance angiography gives excellent soft tissue correlation but is overkill for most straightforward questions. Computed tomography angiography is fast but involves contrast and radiation, so it is reserved for pre-surgical planning or trauma evaluation where speed and comprehensive vascular mapping matter.
The radial pulse at the wrist is palpable in most people, but the ulnar pulse is significantly harder to assess clinically. That does not mean the ulnar artery is small - it is comparable in caliber. It is simply covered by the flexor retinaculum and adjacent tendons, making direct compression against bone nearly impossible at the wrist level. Some clinicians skip ulnar assessment entirely, which is a mistake when evaluating for Allen test purposes or planning harvest sites for coronary bypass grafting.