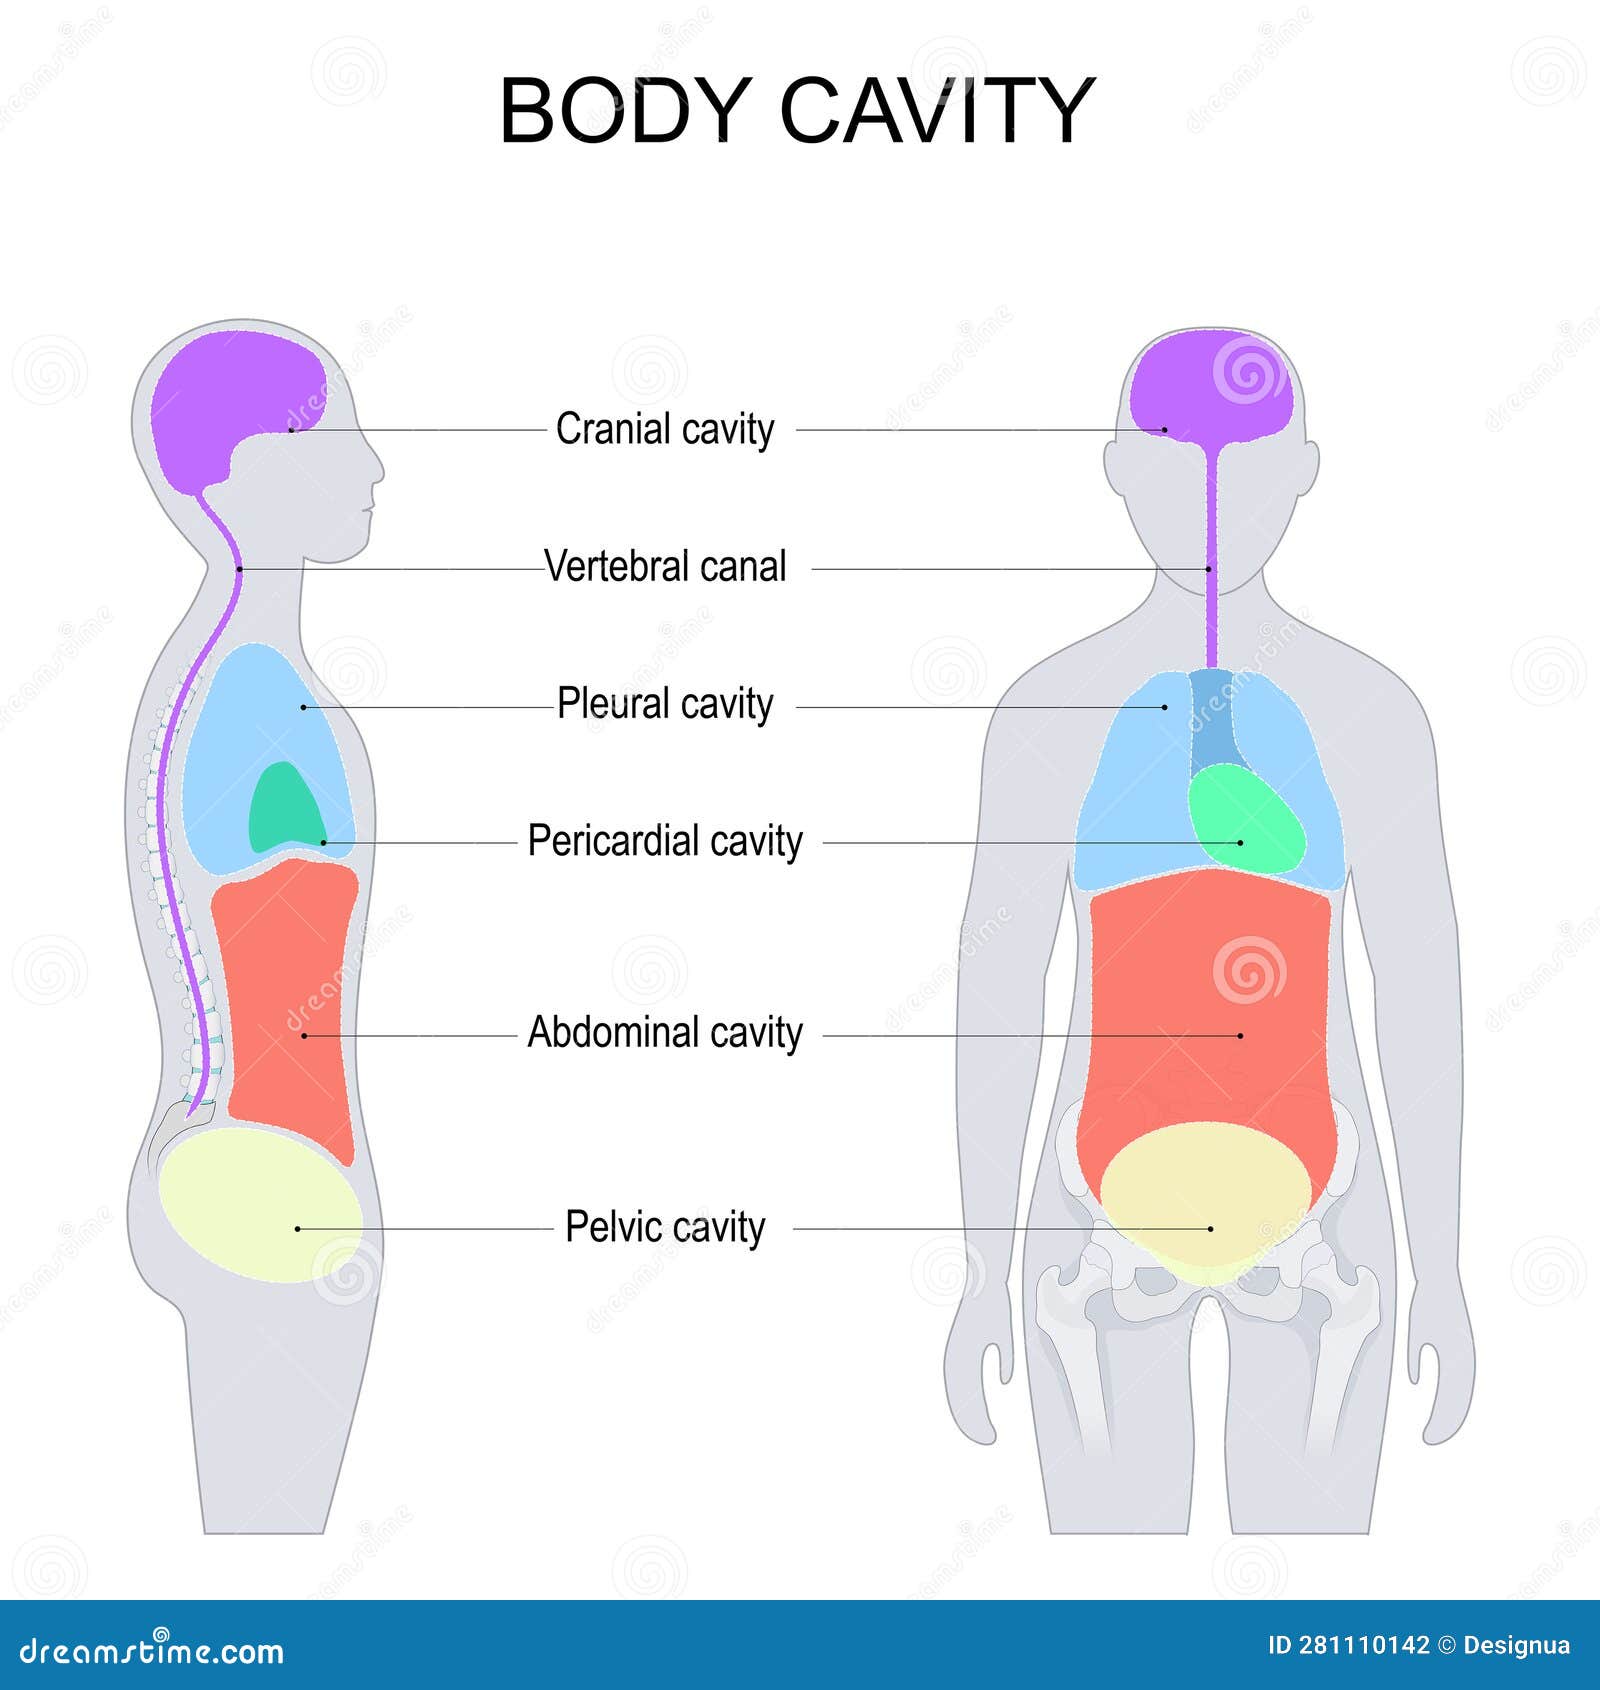
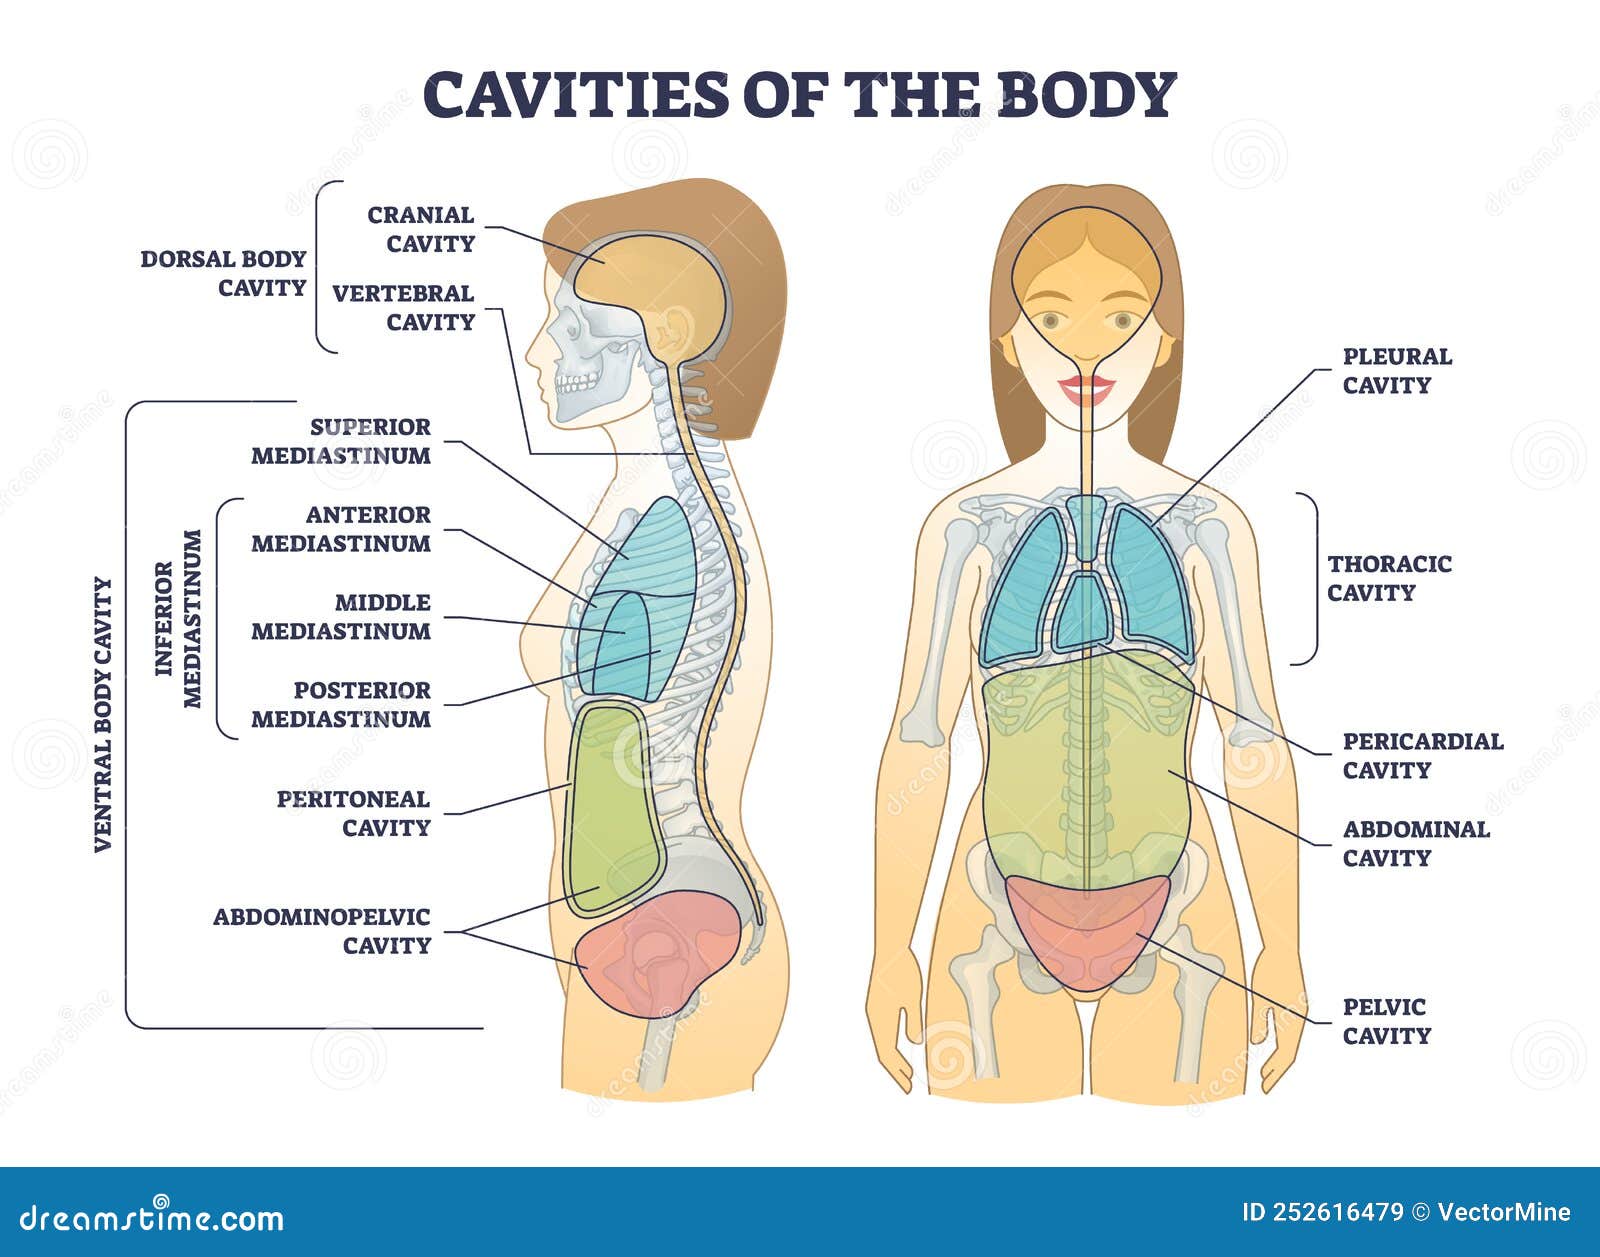
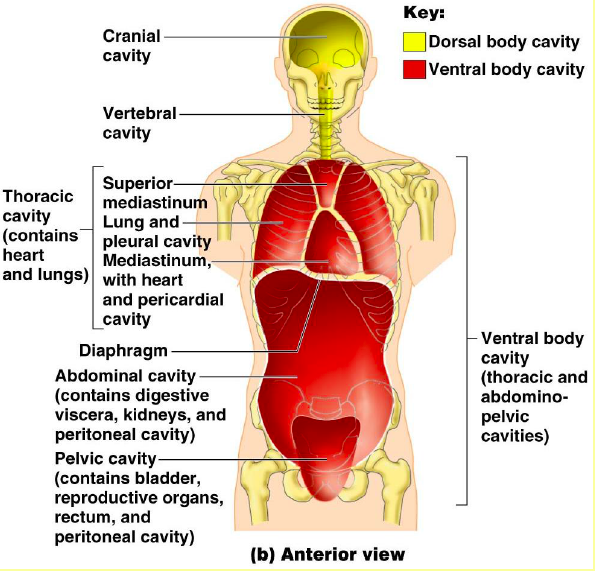
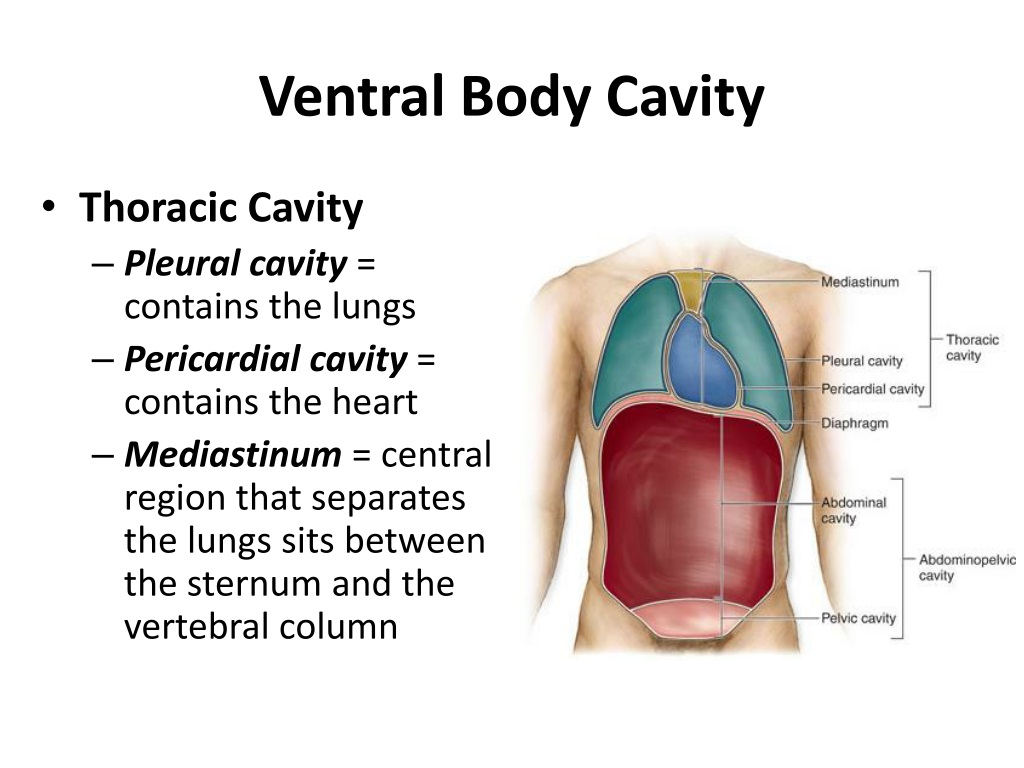
The ventral body cavity is just the front half of your coelom, split into two main spaces by the diaphragm. Above it sits the thoracic cavity with the heart and lungs. Below it is the abdominopelvic cavity holding the digestive organs, kidneys, liver, spleen, and the reproductive stuff. That is literally it. No mystery.
I spent three years doing gross anatomy labs and dissection prep, and the thing that always trips people up is how these organs actually sit relative to each other. The peritoneal reflections are not symmetric. You learn that pretty quick when you are trying to identify the mesenteric attachments on a cadaver that has been sitting in formalin for six months. Everything sticks together differently than the diagrams show.
Ventral Body Cavity Organs and Their Coverings
Not every organ in there has the same type of serous covering. The intraperitoneal organs are suspended by mesenteries and can move a bit. The stomach, most of the small intestine, the transverse colon, the spleen. They have that extra layer of peritoneum wrapping around them completely. The retroperitoneal organs are stuck to the posterior abdominal wall. Kidneys, pancreas, duodenum (the second through fourth parts), ascending and descending colon. They only get peritoneum on their anterior surface.
This matters because if you are planning surgery or interpreting imaging, the difference changes everything about approach and visibility. A laparoscopic cholecystectomy goes through the intraperitoneal space. A retroperitoneal nephrectomy requires a completely different port placement and you are working against gravity the whole time.
The Mediastinum Confusion
People often lump the mediastinum into the ventral cavity without realizing it is technically a separate compartment within the thoracic cavity. It contains the heart, thymus, trachea, esophagus, great vessels, and lymph nodes. The heart itself sits in the pericardial cavity, which is a potential space between the parietal and visceral layers of serous pericardium. Normally there is about 15 to 20 mL of serous fluid in there. More than that and you have a pericardial effusion. Less and the layers stick together, which happens after pericarditis.
The pleural cavities around the lungs are separate from the pericardial space. They share the same embryological origin from the lateral plate mesoderm, but they are distinct potential spaces. If you need to remember which side the stomach sits on, it is the left. Liver is mostly right but extends across the midline. Spleen is strictly left upper quadrant, tucked under ribs 9 through 11. That is why a left lower rib fracture can lacerate the spleen. I saw that happen in the trauma bay. Patient came in with Kehr sign, referred pain to the left shoulder from diaphragmatic irritation.
Common Pitfalls
The biggest mistake students make is treating the ventral cavity as one continuous empty space. It is not. The transverse mesocolon divides the greater sac into the supracolic and infracolic compartments. The omental bursa (lesser sac) sits behind the stomach and is only accessible through the epiploic foramen of Winslow. If you are learning surgical anatomy, you need to understand that the lesser sac is a real dead space that abscesses can form in, and it does not communicate freely with the rest of the peritoneal cavity.
Another thing nobody emphasizes enough is how the position of these organs changes with respiration and posture. The diaphragm descends about 1 to 2 cm during normal inspiration and up to 7 cm during forced breathing. The liver and stomach shift with it. On a supine CT scan, the intestines spread out differently than on an upright film. If you are reading radiology, always note the patient position.
When Things Go Wrong
Hernias are the classic problem here. Direct inguinal hernias push through Hesselbach's triangle, medial to the inferior epigastric vessels. Indirect ones go through the deep inguinal ring, lateral to those vessels, and follow the path of the processus vaginalis. Femoral hernias are below the inguinal ligament and have a higher strangulation rate because the femoral canal is tight. I had a patient who presented with bowel obstruction from a femoral hernia that was not visible externally. She was obese, and the hernia sac was deep in the canal. CT caught it, but on physical exam alone you would miss it.
Adhesions are another issue. Any intra-abdominal surgery creates them. The peritoneum heals by fibrosis, and bands of scar tissue can tether loops of bowel. Small bowel obstruction from adhesions accounts for about 60 percent of all SBO cases in developed countries. The first operation you ever have is usually the last one you want.
Practical Notes
If you are studying for boards, focus on the peritoneal relationships. Know which organs are intraperitoneal versus retroperitoneal. That question shows up constantly. Understand the arterial supply too. The foregut, midgut, and hindgut divisions map to the celiac trunk, superior mesenteric artery, and inferior mesenteric artery respectively. The transition zones are clinically important because they are watershed areas prone to ischemia. The splenic flexure is one of them. So is the rectosigmoid junction.
Also learn the venous drainage. Portal hypertension changes everything about how blood flows through these organs. The coronary vein of the stomach and the left gastric vein connect to the azygos system. Esophageal varices form there. Caput medusae forms at the umbilicus where the paraumbilical veins reconnect with the superficial epigastric system. These are not trivia. They are life-threatening complications you need to recognize.
The ventral body cavity organs do not exist in isolation. They are constrained by fascial planes, suspended by mesenteries, and their blood supply follows predictable embryological patterns. Once you internalize those patterns, the anatomy stops being a memorization exercise and starts making actual sense. I stopped struggling with it once I started thinking about it in terms of developmental origins rather than spatial relationships alone. The midgut rotates 270 degrees counterclockwise during fetal development. That rotation is why the appendix ends up in the right lower quadrant. Everything else follows from that.
Gallery Ventral Body Cavity Organs
Dorsal and Ventral Body Cavities for Internal Organs or Viscera Stock ... - All For One
Dorsal And Ventral Body Cavities For Internal Organs Or Viscera Vector Illustration ...
Ventral Cavity , Dorsal and Ventral: What Are They, Differences, and More – GOMW
Ventral Cavity , Dorsal and Ventral: What Are They, Differences, and More – GOMW
What Is Mantle Cavity For at Imogen Holman blog