Spinal Nerve Branches: What Actually Happens After the Rootlets Merge
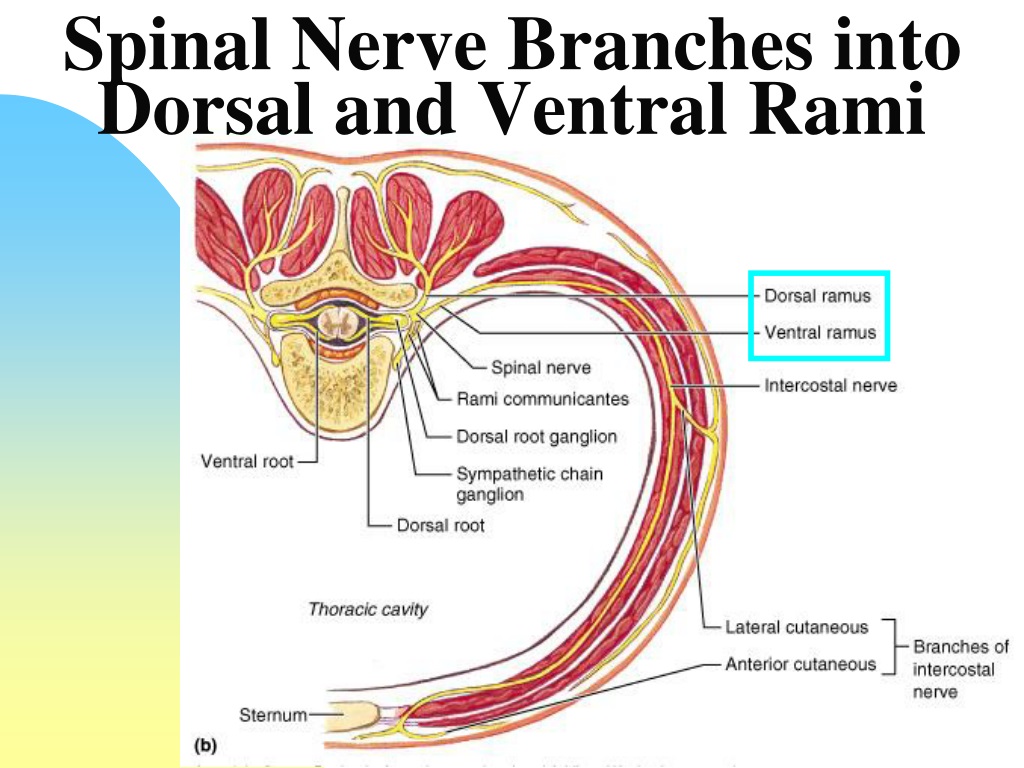
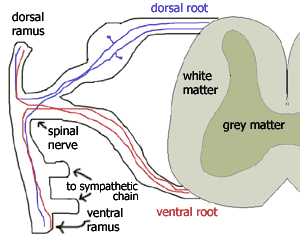
Once the dorsal and ventral roots join to form a spinal nerve, that nerve trunk is only about two centimeters long before it immediately splits. The ventral ramus of a spinal nerve takes the larger share of fibers and heads forward and outward toward the body periphery. The dorsal ramus is smaller and simply turns backward to supply the deep back muscles and overlying skin. Most people studying for boards remember the dorsal ramus and forget how significantly the ventral ramus dominates the innervation map of the entire trunk and limbs. The ventral ramus carries both motor and sensory fibers, just like the mixed spinal nerve it branches from. In the cervical, brachial, lumbar, and sacral regions, these rami interweave to form plexuses. The plexus arrangement means individual peripheral nerves end up containing fibers from multiple spinal levels, which is why a single nerve can motor-innervate muscles derived from more than one myotome. The thoracic ventral rami from T2 through T11 are different. They do not form plexuses. They remain as distinct intercostal nerves running along the inferior border of each rib, providing segmental innervation to the chest and abdominal wall musculature and skin in a fairly predictable dermatomal pattern. One thing anatomy texts rarely stress enough is the contribution of the gray and white rami communicantes. The white ramus, present only at T1 through L2 levels, carries preganglionic sympathetic fibers into the paravertebral ganglion. The gray ramus carries postganglionic sympathetic fibers back and joins the ventral ramus. This means every ventral ramus from T1 to L2 has a sympathetic component woven into it. If you are planning a regional block in that zone, neglecting the sympathetic fibers can explain why a patient still reports vasodilation or temperature changes after what should have been a complete motor-sensory block.
I spent far too long on my first year of clinical rotations trying to map why a T10 surgical incision caused unexpected flank numbness that extended beyond the supposed dermatome. The problem was not a misidentified nerve root. It was the anterior cutaneous branch and lateral cutaneous branch of the intercostal ventral ramus both being affected by retraction. I learned to anticipate that dissecting near the mid-axillary line during a laparoscopic procedure could easily injure the lateral cutaneous branch, producing a patch of numbness that patients find more distressing than the surgical pain itself. Mapping the incision sites to avoid that branch cut postoperative complications almost entirely. A counter-intuitive point that trips up students repeatedly is assuming the ventral ramus always carries more motor fibers than sensory. That holds true for many limb nerves, but in the thoracic intercostal system, the sensory component is substantial and the motor component is limited to the intercostal muscles, transversus thoracis, and abdominal wall muscles. The body wall dermatomes are dense with sensory endings, and the motor demand is lower than you would expect from a nerve that appears so large on a dissection table. Overestimating the motor dominance of the ventral ramus leads to poor expectations when interpreting EMG studies of intercostal regions. Another frequent mistake involves the lumbar plexus. The L1 ventral ramus does not just contribute to the iliohypogastric and ilioinguinal nerves. It also sends a branch that joins the genitofemoral nerve and frequently anastomoses with the subcostal nerve from T12. This cross-talk means a proximal lumbar lesion can produce sensory changes in the T12 distribution if you are not tracking the anastomotic connections. I had a case where a retroperitoneal hematoma compressed the L1 ventral ramus near the psoas margin, and the patient presented with groin numbness that did not fit a clean L1 pattern. Imaging showed the hematoma extending upward enough to catch the T12-L1 communication. The workaround was CT angiography to confirm the exact compression site, followed by conservative management since the fibers were stretched rather than transected.
The brachial plexus ventral ramus contributions from C5 through T1 are where the real clinical complexity lives. The posterior cord receives contributions from the posterior divisions of all three trunks, and the medial and lateral cords receive subsets from the anterior divisions. This means the ventral ramus fibers are not traveling in neat, named bundles until you reach the terminal branches. A proximal traction injury to the upper trunk, for example, will affect muscles innervated by the axillary nerve and the suprascapular nerve, but it may spare the radial nerve's proximal branches depending on the exact angle and severity of the stretch. Knowing the ventral ramus architecture helps you predict which muscles will be weak and which will appear relatively intact. There are situations where ventral ramus blocks are useful, particularly for thoracoabdominal surgery. An erector spinae plane block at the thoracic level indirectly targets the ventral ramus as it passes near the transverse process before it diverges into its posterior and anterior branches. This technique has replaced some intercostal nerve blocks because it avoids direct needle passage near the parietal pleura, reducing pneumothorax risk. However, the block does not reliably anesthetize the anterior cutaneous branch unless you add a supplementary injection or use a higher volume with careful spread. I usually add a paramedian injection to catch the anterior cutaneous branch when I need complete abdominal wall coverage for a midline incision. Without that addition, the patient will complain of sharp anterior pain despite adequate lateral and posterior anesthesia. Sacroiliac joint procedures involve the L4, L5, and S1 ventral rami contributing to the sacral plexus and ultimately the superior gluteal nerve and sciatic nerve. A misdirected needle during an SI joint ablation can inadvertently injure the L5 ventral ramus as it courses over the ala of the sacrum before joining S1. The resulting foot drop is a known complication, not a rare anecdote. The workaround is strictly using fluoroscopic landmarks that keep the trajectory anterior to the sacral ala and avoiding deep penertation past the posterior Superior iliac spine plane. I check the L5 root projection on every imaging study before advancing the needle past the posterior iliac crest.
Get the Full Details
One limitation worth stating plainly is that ventral ramus anatomy varies more than standard textbooks suggest. The communications between adjacent rami, the presence of accessory branches, and the exact points where plexus formation begins all have documented variation. A study of cadaveric specimens showed that the lumbar plexus configuration varied in nearly 30 percent of cases when looked at closely. If you are relying solely on textbook diagrams for surgical planning or interventional procedures, you are accepting a margin of error that can matter. Cross-sectional imaging before any invasive work in the lumbar or sacral region is the practical fix, even if it adds time to the workflow. The ventral ramus also carries proprioceptive fibers from muscle spindles and Golgi tendon organs within the myotomes it supplies. These fibers travel back through the same pathway as the motor efferents and are often overlooked when interpreting reflex changes after nerve injury. A diminished abdominal reflex after a ventral ramus lesion does not always indicate a central process. It can simply reflect peripheral proprioceptive disruption from the ventral ramus injury itself. Testing abdominal reflexes in patients with known ventral ramus pathology should be interpreted with that peripheral component in mind. For students and clinicians who need a quick reference, the ventral ramus anatomy can be summarized by region: cervical and brachial plexus regions supply the upper extremity with extensive interweaving; thoracic ventral rami form segmental intercostal nerves without plexus formation; lumbar and sacral plexus regions supply the lower extremity with significant fiber mixing and anastomotic connections. The sympathetic rami communicantes attach to every ventral ramus from T1 to L2. The dorsal ramus is the smaller posterior branch responsible for intrinsic back muscles and the skin over the spinous processes. Keeping that basic framework in mind prevents most of the common errors that show up in both exams and clinical practice.
If you want a single actionable tip that covers most of the pitfalls, trace the nerve rather than memorizing the named branches. Follow the ventral ramus from the spinal nerve exit point through its division into anterior and posterior branches, through any plexus connections it enters, and to its terminal distribution. The tracing approach takes longer initially but reduces mistakes on imaging interpretation, procedural planning, and clinical reasoning far more than repeated rote memorization of branch names ever will.