Getting the Angle Right When It Actually Matters
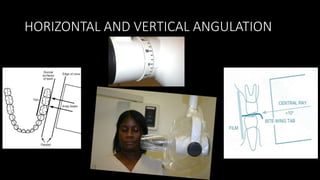
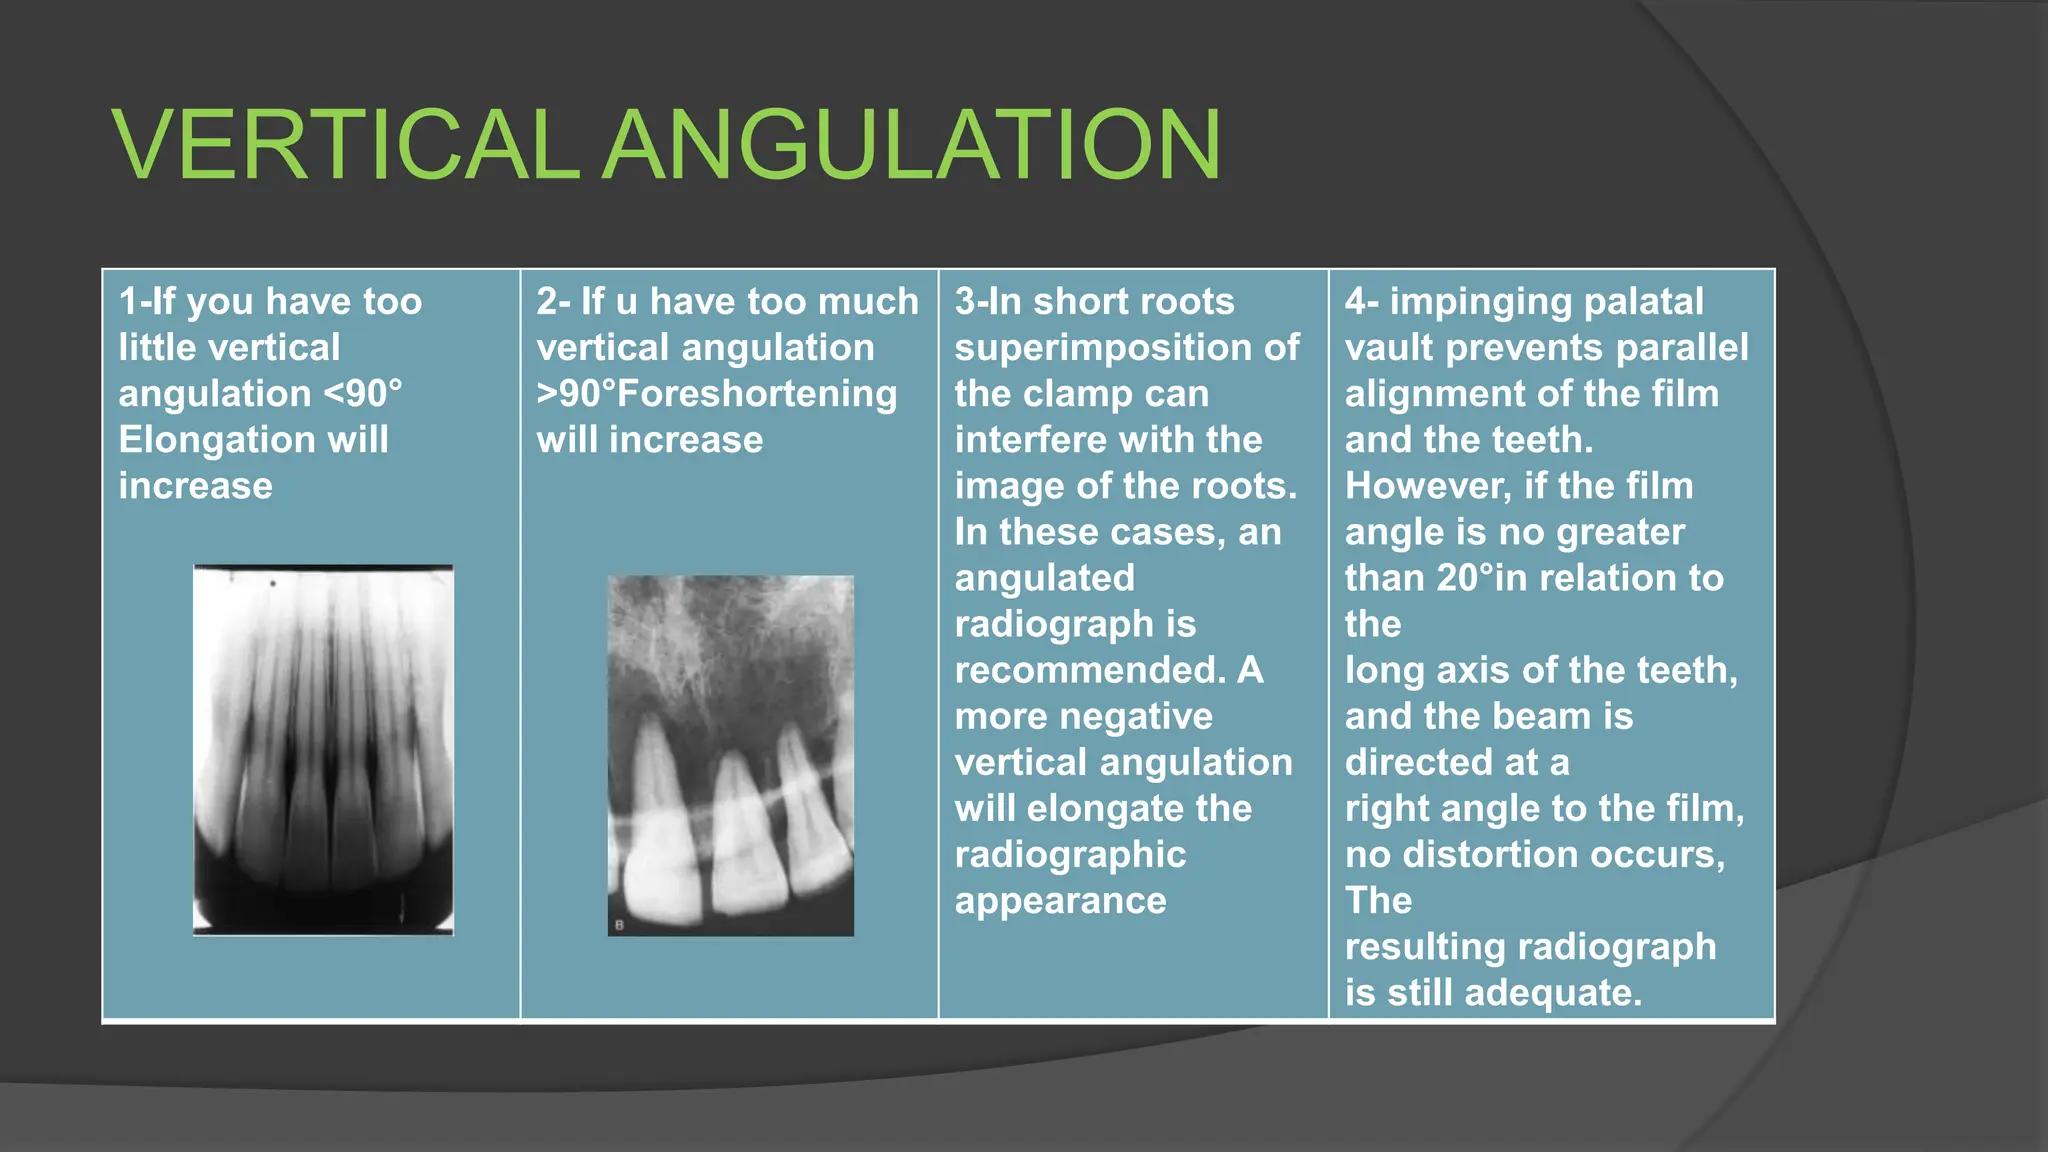
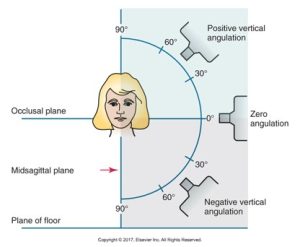
I ran into a case last year where a patient had severely rotated mandibular premolars with buccal tipping so pronounced that standard bisecting angle geometry was producing every image on the sensor upside down. Not foreshortened or elongated—just flipped because the tooth axis was pointing more toward the cheek than inward toward the tongue. Took three tries and I ended up masking the buccal anatomy with lead tabs to figure out which surface was actually facing the film. That kind of thing forces you to rethink how you're applying vertical angulation principles on the fly. Vertical angulation in dental radiography refers to the mesiodistal tilt of the central x-ray beam relative to the plane of the image receptor. It's one of the two critical angles you set manually—the other being horizontal angulation—and it directly controls whether structures appear foreshortened or elongated on the resulting image. The ideal target depends on which region you're imaging and whether you're using the parallax technique or the bisecting angle method. There isn't a single perfect degree, but there are workable ranges that experienced clinicians stick to without really thinking about it anymore.
Vertical Angulation Dental Radiography: What Actually Happens in the Chair
The standard reference charts you see in textbooks list vertical angulation ranges like 0 to 30 degrees for anterior mandibular teeth, 40 to 50 degrees for anterior maxillary teeth, 60 to 70 degrees for premolars, and 70 to 80 degrees for molars. These numbers come from the bisecting angle technique and they're approximations that assume normal anatomical positioning. When anatomy is normal, following them produces diagnostically acceptable images the vast majority of the time. Most of the quality problems I see in clinic come from people applying these ranges without adjusting for individual variation in tooth orientation, arch curvature, or patient mouth opening limitations. Here's what tends to get glossed over in the instruction manuals: the vertical angulation you choose interacts with the source-to-sensor distance in ways that most operators don't account for. If you're using a long cone (8-inch or 16-inch PID) versus a short cone, the effective beam divergence changes the amount of magnification, which means your angulation judgments need to shift slightly. A 5-degree adjustment at 8 inches of exposure length produces noticeably different results than the same 5-degree adjustment at 16 inches. I've seen junior clinicians switch cone lengths mid-session and not recalculate their angulation at all, then wonder why half their images look off. It's not a big conceptual leap but it's easy to overlook when you're focusing on getting the PID placement correct. The other thing nobody emphasizes enough is how saliva and blood affect your ability to maintain consistent vertical angulation. When the field is wet, the PID slips. The sensor shifts. Your hand position drifts by a degree or two between each shot, and that's enough to change the diagnostic quality of posterior interproximal images. I started using a dry-field protocol before setting up any bite blocks or sensor positioning—cotton rolls, suction, a little air—because maintaining the angle you think you've set is basically impossible when the mouth is a slipping hazard. This usually cuts the process down from needing two retakes per quadrant to roughly one per quadrant.
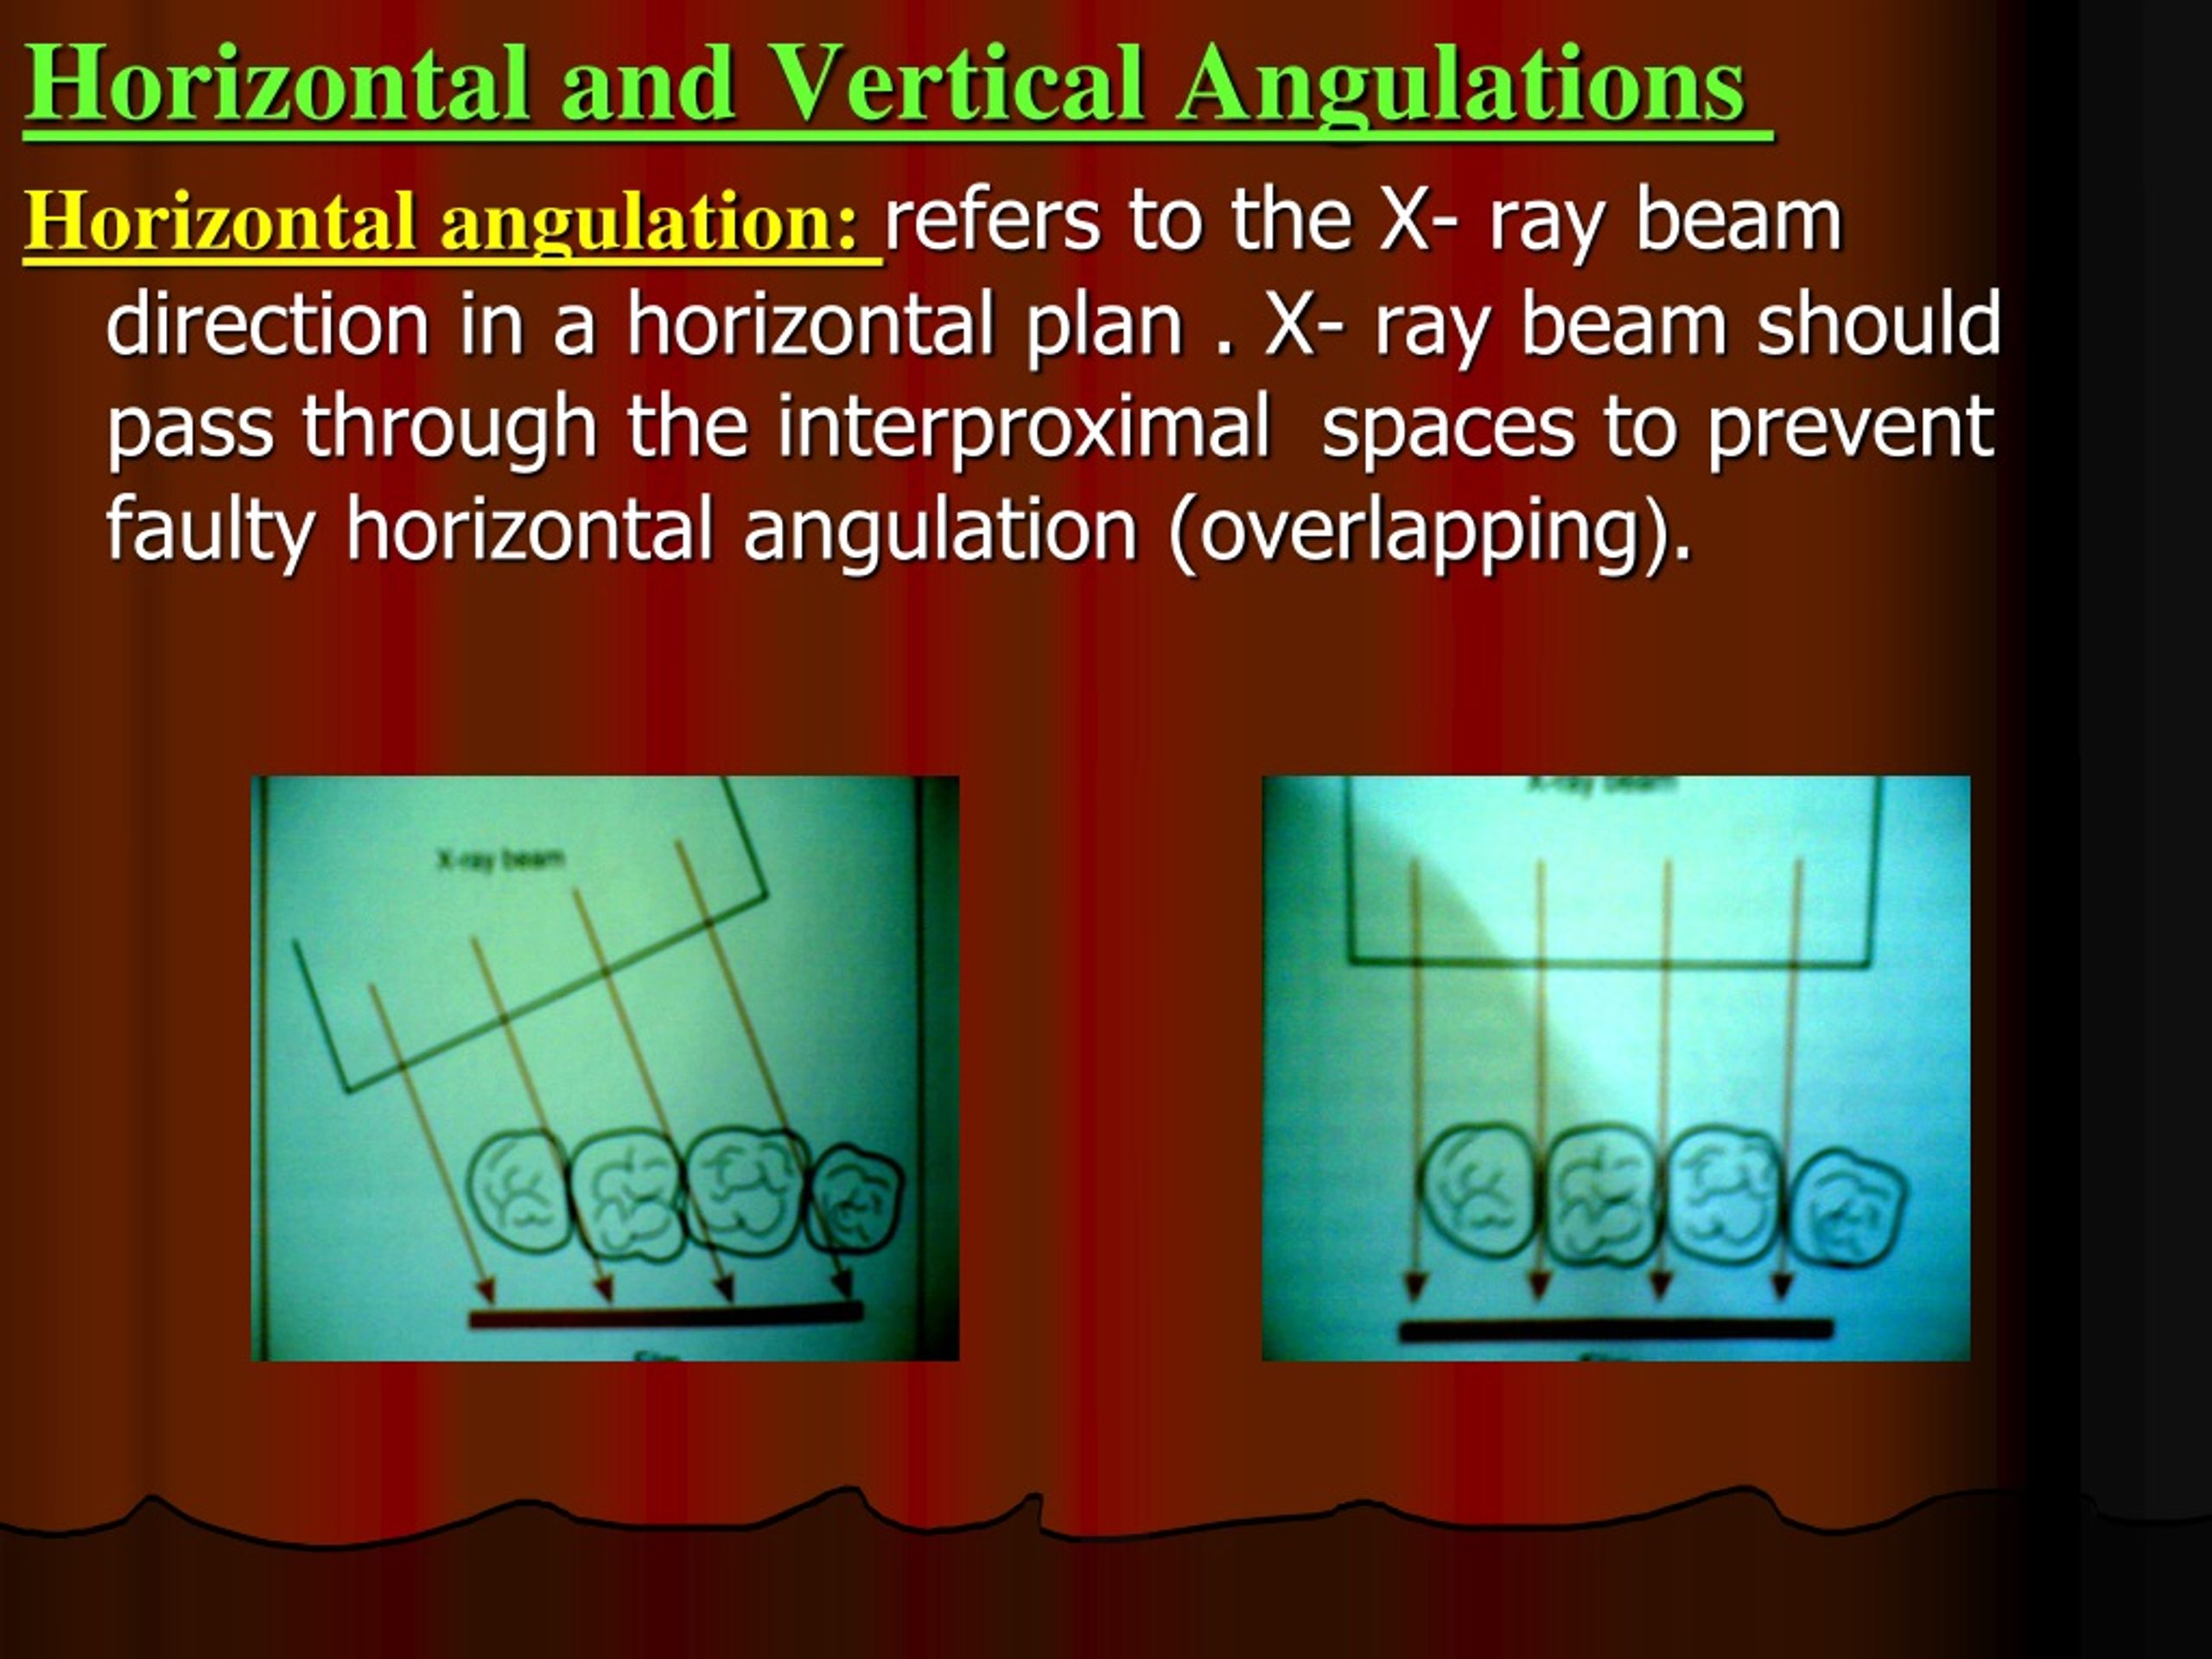
There's also a practical limitation to vertical angulation as a standalone concept. It only works reliably when you have a clear line of sight between the x-ray source and the image receptor with nothing obstructing the beam path. Anatomical structures like the hard palate, the zygomatic arch, or overlappingCondyle processes in panoramic-like situations will degrade image quality regardless of how precisely you've set your vertical angulation. In those cases, the real solution is changing your horizontal angulation or your source-to-object geometry, not fiddling with the vertical dial. Some clinicians keep adjusting vertical angulation when the problem is actually interference from adjacent structures, and they end up with images that look technically correct but are diagnostically useless because the anatomy they're trying to see is superimposed over bone that shouldn't be there. If you're working through a case that isn't cooperating—pediatric patients, patients with trismus, or anyone with limited mouth opening—you'll find that vertical angulation becomes much harder to control precisely. The PID can't reach the intended target area without hitting soft tissue, which means you're either compressing tissue (which changes the apparent tooth position) or angling the beam at an unnatural trajectory. I've had good success using a 9-inch short-cone setup with a slightly increased vertical angulation to compensate for the reduced object-to-receptor distance when the mouth won't open wide enough for standard positioning. It's not ideal but it's workable, and the alternative is often just referring the patient out for CBCT imaging anyway. The takeaway from all this is that vertical angulation is a tool, not a rule. You set it based on the anatomy you're imaging, the equipment you're using, and the patient's actual capabilities in the chair. The textbook ranges are a starting point. What happens next depends entirely on whether the tooth is angled, whether the arch is curved, whether the sensor is sitting flat against the teeth, and whether the beam path is clear of obstructions. When those variables line up, you get clean images. When they don't, you adjust based on what you're seeing rather than what the chart says you should be doing.
Get the Full Details