Most people don't realize vertigo is usually a peripheral balance issue, not a brain problem. The inner ear sends garbled signals and the brain tries to compensate on its own. That process can take weeks or months without guidance. Physical therapists who specialize in vestibular rehab speed this up significantly by using targeted maneuvers and exercises.
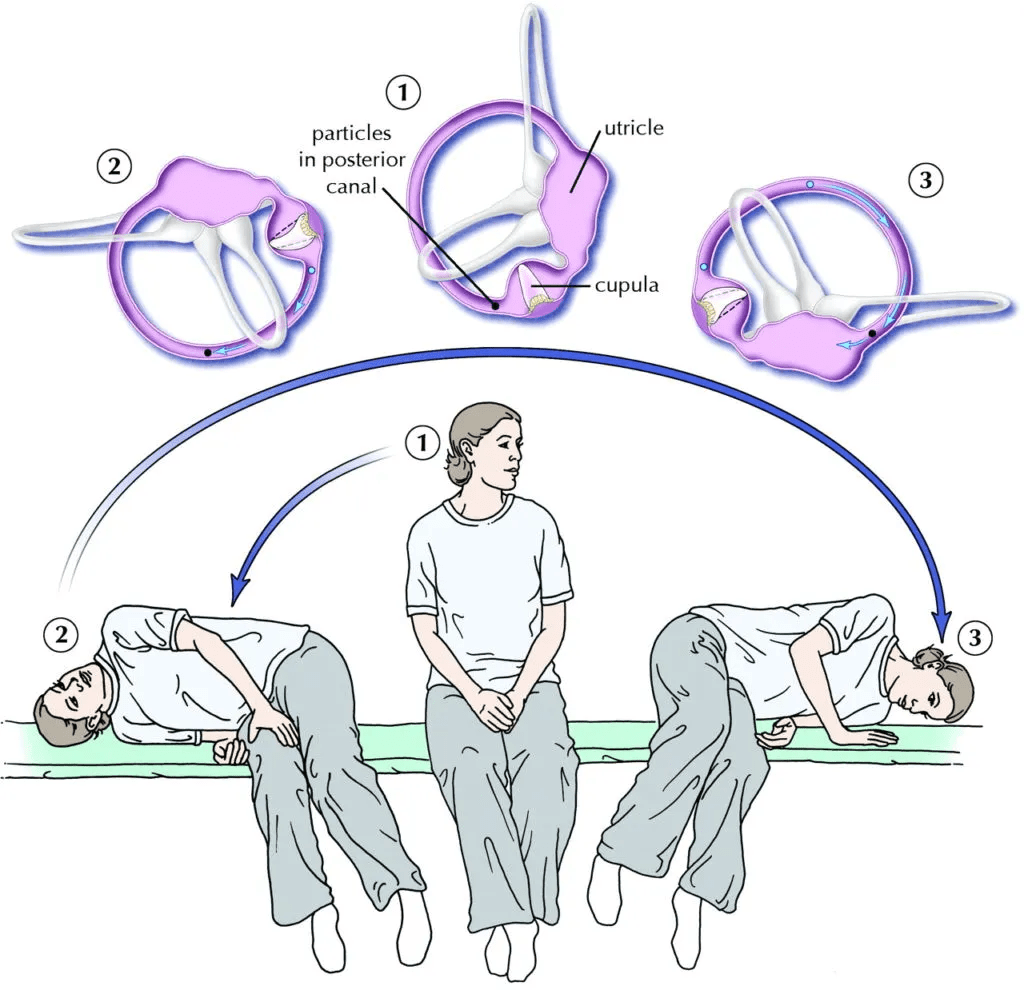
The Epley maneuver remains the gold standard for posterior canal BPPV, which accounts for roughly 50 to 60 percent of all peripheral vertigo cases. You lie back, the therapist turns your head forty-five degrees to the affected side, you drop back quickly, wait thirty seconds, then rotate your body and head through a series of positions. Each position holds until the nystagmus stops. That usually means the canaliths have migrated out of the semicircular canal and into the utricle where they belong. The whole thing takes about five minutes in skilled hands. A single session resolves symptoms in about eighty percent of patients. Some need a second or third appointment a week later if debris remains.
What to Expect During Vertigo Physical Therapy Treatment
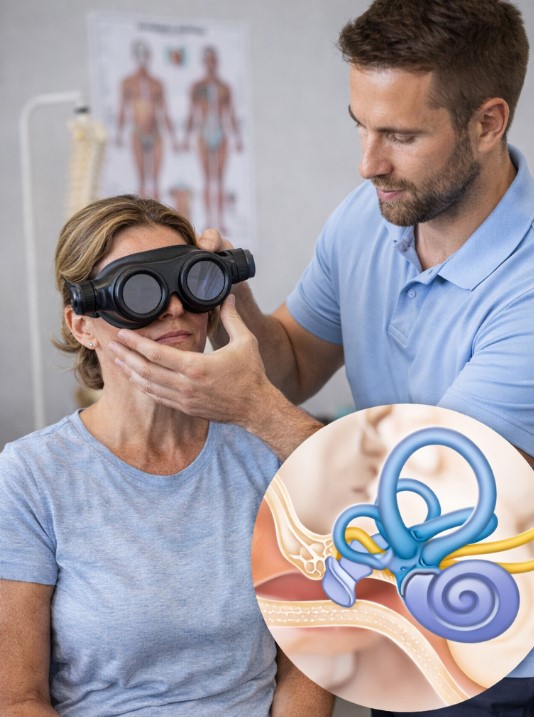
The first visit is mostly assessment. Your therapist will check your oculomotor function, cervical range of motion, gait, and a battery of positional tests like Dix-Hallpike and supine roll. They're looking for spontaneous nystagmus, latency, adaptation, and fatigability. These details tell them whether you're dealing with BPPV, vestibular neuritis, Meniere's disease, or something cervicogenic that mimics true vertigo.
After the evaluation comes the treatment portion. If BPPV is confirmed, they perform the appropriate canalith repositioning procedure. For vestibular neuritis or labyrinthitis, they move straight into habituation exercises and gaze stabilization. The most common technique is the VOR x1 exercise, where you hold a thumb at arm's length and keep your eyes locked on it while moving your head side to side or up and down. You do this for two to three minutes, three times a day. It feels uncomfortable at first. The room may spin more. That's expected. The nervous system adapts over two to four weeks.
For persistent imbalance without acute spinning, therapists use compensatory strategies. You learn to rely more on visual and somatosensory cues when your vestibular input is unreliable. Saccadic pursuit training helps too. You track moving targets with quick eye movements while your head stays still. This strengthens the neural pathways that bypass the damaged peripheral system.
I ran into a patient last year who presented with what looked like classic posterior canal BPPV. Dix-Hallpike produced a brief torsional nystagmus, standard presentation. We did the Epley twice with no improvement. The third time, during the supine roll test, I noticed the nystagmus was purely horizontal and beat toward the ground regardless of which side was down. That's not posterior canal. That's horizontal canal cupulolithiasis. A standard Epley will not touch that. I switched to the Barbeque Roll maneuver instead, which repositions the debris along the long arm of the horizontal canal. One session, two minutes of actual maneuvering, and the patient's symptoms dropped from an eight out of ten to a two. Wrong diagnosis, wrong maneuver, wasted time and continued suffering. This happens more often than you'd think because textbook presentations don't cover every variation.
Another thing clinicians miss regularly is the relationship between cervical dysfunction and vertigo. Neck proprioception feeds directly into the vestibular nuclei. Patients with chronic neck tension or whiplash history often present with dizziness that gets mislabeled as BPPV or vestibular neuritis. Cervicogenic dizziness doesn't respond to repositioning maneuvers. It responds to manual therapy, dry needling, and specific neck stabilization exercises. I've seen patients cycle through three or four rounds of Epley before someone checked their cervical ROM and realized the real driver was their SCM trigger points referring dizziness signals into the vestibular system.
The Habituation Protocol and Why It Matters
Habituation exercises work by repeatedly exposing the central nervous system to provoking movements until the response decreases. This is fundamentally different from canalith repositioning. You're not moving crystals. You're training your brain to stop overreacting to faulty signals. The protocol involves identifying every head position and movement that triggers symptoms and practicing them in a graded sequence.
Start with slow head turns while standing still. Then add walking. Then add visual clutter like reading text while moving your head. Then progress to faster movements and less stable surfaces. Most patients complete this phase in six to eight weeks with daily practice. The key is consistency over intensity. Doing three minutes of exercises twice a day beats doing twenty minutes once a week. The vestibular system needs frequent, repeated exposure to rewire.
There's a common misconception that you should push through severe symptoms during these exercises. That's backwards. You want mild to moderate provocation, not debilitating episodes. If your vertigo spikes to a six or seven out of ten during an exercise, you're going too hard. Dial it back. The goal is adaptation, not exhaustion. Going too aggressive actually delays recovery by triggering central sensitization, where your brain learns to amplify dizziness signals instead of dampening them.
For persistent cases that don't respond to standard protocols, therapists sometimes incorporate binocular vision assessment. Up to thirty percent of chronic vestibular patients have underlying vergence or accommodation deficits that compound their symptoms. Standard exercises won't fix those. Vision therapy or prism lenses become necessary adjuncts. This is another area where general physical therapists sometimes miss the connection because binocular vision screening isn't routinely included in vestibular rehabilitation training programs.
Limitations and When Physical Therapy Won't Help
Vestibular rehab doesn't work for central vertigo caused by stroke, tumor, or multiple sclerosis. If your nystagmus is purely vertical, direction-changing, or doesn't fatigue with repetition, that's a red flag for central pathology. These patients need neurology referral, not more Epley maneuvers. The same applies if you have focal neurological deficits like limb weakness, dysarthria, or severe headache with your dizziness.
Anterior canal BPPV is another scenario where standard treatment protocols fall short. It represents only about five percent of BPPV cases but is notoriously difficult to diagnose because the Dix-Hallpike response is atypical. The Lempert or Gattaceca maneuver is the preferred repositioning technique, but many therapists haven't been trained in it. If your posterior canal treatment repeatedly fails and anterior involvement is suspected, ask specifically about this.
Medication dependency is a quiet problem in vestibular rehab. Prescribing betahistine, benzodiazepines, or meclizine long-term actually slows central compensation. These drugs suppress the very neural plasticity that makes vestibular rehabilitation work. If you're on chronic vestibular suppressants, discuss tapering with your prescriber before starting aggressive rehab. The first two weeks can feel worse as the medication leaves your system and your brain starts processing signals again. That temporary worsening is normal and doesn't mean the therapy is failing.
Severe phobia of movement, or kinesophobia, is another bottleneck. Some patients develop intense anxiety around head movements after repeated vertigo episodes. The fear itself generates symptoms through hyperventilation and muscle tension, creating a feedback loop that looks like treatment resistance. These patients benefit from gradual exposure and sometimes cognitive behavioral support alongside the physical exercises. Skipping this psychological component often leads to dropout around week three, which is precisely when neuroplastic changes should be becoming measurable.
What Home Programs Look Like
Most therapists give you a written protocol for home practice between visits. A typical program includes the Brandt-Daroff exercise for habituation, which involves sitting on the edge of a bed, lying quickly to one side with your head turned forty-five degrees up, holding for thirty seconds or until dizziness stops, returning to sitting, and repeating on the other side. You do five repetitions per session, two to three sessions daily. It's less precise than clinical repositioning but effective for maintaining gains between appointments.
Gaze stabilization with vantage point variation is the next tier. You focus on a stationary target while introducing different head positions and speeds. Slow horizontal sweeps progress to fast horizontal sweeps, then vertical, then diagonal. Each progression adds neurological demand. The brain has to maintain visual fixation under increasingly difficult conditions, which forces vestibular compensation pathways to strengthen.
Balance training on unstable surfaces comes later in the program. A foam pad or balance board adds proprioceptive challenge that forces your central nervous system to integrate vestibular, visual, and somatosensory information simultaneously. This mimics real-world conditions like walking on uneven ground or turning your head while navigating a crowded space. Most patients add this in the third or fourth week when acute symptoms have subsided enough to tolerate the challenge.
The timeline for full recovery varies. Posterior canal BPPV often resolves in one to three sessions. Vestibular neuritis typically takes six to twelve weeks of consistent exercise. Meniere's disease management is more about symptom reduction and attack frequency control than resolution. Cervicogenic dizziness responds fastest when the underlying neck dysfunction is addressed directly, usually four to six weeks of combined manual therapy and exercise.
Your therapist should re-evaluate you every two to three weeks during the active treatment phase. If your symptoms aren't improving after two weeks of consistent home exercise, something is wrong with either the diagnosis or the exercise selection. Pushing harder in the same direction rarely fixes that. You need a reassessment, not more of the same routine.
Gallery Vertigo Physical Therapy Treatment
Physical Therapy for BPPV in Salem, Oregon | Safe & Effective Vertigo Treatment at HWY Physical ...
Can Physical Therapy Help With Vertigo? Treatments, Techniques & What to Expect - Physical ...
BPPV (Benign Paroxysmal Positional Vertigo) - ProMet Physical Therapy P.C.
exercises for vertigo | Vertigo exercises, Rehabilitation exercises, Physical therapy exercises
Vertigo; eppley Occupational Therapist, Physical Therapist, Physical Therapy Student, Epley ...