Understanding the Pleura for Clinical Practice
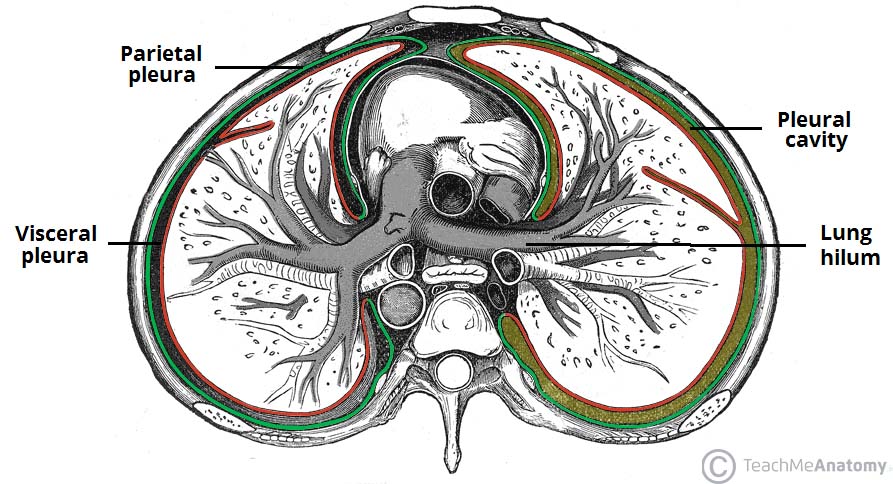
The pleura is two separate layers of serous membrane, and confusing them is something I see residents and even some attending physicians mess up on rounds. The visceral pleura covers the lung surface directly, while the parietal pleura lines the chest wall, diaphragm, and mediastinum. Between them sits the pleural space, a potential space that normally contains about 10 to 20 milliliters of lubricating fluid. That fluid comes from both layers but is primarily produced by the parietal side and reabsorbed by lymphatic stomata on the parietal surface. The visceral pleura is innervated by the autonomic nervous system. It has no somatic sensory fibers, which means it cannot detect pain from the chest wall or diaphragm. The parietal pleura, on the other hand, receives somatic innervation from the intercostal nerves in the costal region, the phrenic nerve in the mediastinal and diaphragmatic regions, and sometimes contributions from the vagus. This is not a trivial detail. It determines why a lung tumor pressing on the chest wall causes sharp localized pain but the same tumor growing within the lung parenchyma causes almost no discomfort until it invades the parietal layer. I have lost count of how many times I have watched a trainee call a pleural effusion "visceral" when they meant the fluid was tracking along the lateral chest wall, which is parietal pleura. The terminology matters because it guides imaging interpretation and procedural planning. A loculated effusion adjacent to the fissure sits between visceral layers, while a subpulmonic effusion collects under the diaphragmatic parietal pleura and can mimic hepatomegaly on an upright X-ray if you do not look at the lateral costophrenic sulcus.
Another thing people miss: the visceral pleura is relatively insensitive to temperature and touch, which is why thoracoscopic surgery on the lung surface itself does not require extensive local anesthesia of the lung. But stick a needle through the parietal pleura and the patient will feel it immediately, often before the anesthesiologist even finishes prepping the site. During my first year of residency, I attempted a diagnostic thoracentesis and anesthetized only the skin and subcutaneous tissue down to the rib. I missed the parietal pleura injection by maybe two millimeters and the patient called out mid-procedure. I stood there holding the needle, realized my mistake, and completed the tap while they breathed through it. That experience taught me to inject a full cuff of lidocaine along the entire parietal pleural track before advancing anything further. The reflex physiology is worth noting. Irritation of the parietal pleura triggers the typical pleuritic pain pattern and can cause splinting, shallow breathing, and reflex cough. The visceral pleura contributes to reflex regulation of bronchial smooth muscle tone but does not generate conscious sensation. This distinction becomes clinically relevant when you are interpreting a CT scan showing pleural thickening. Thickening confined to the visceral layer, as seen in some cases of prior asbestos exposure, presents differently from diffuse parietal thickening, which is more likely to cause restrictive lung physiology and true pain. A practical boundary you need to know: the visceral and parietal pleura are continuous at the lung root, forming the pulmonary ligament inferiorly. This is where the pleural reflection passes from the mediastinal surface to the diaphragmatic surface. During video-assisted thoracoscopic surgery, the pulmonary ligament is often divided to allow full expansion of the lower lobe after wedge resection. If you do not divide it completely, the lobe can remain partially collapsed postoperatively, and the differential diagnosis for post-op atelectasis includes technical error versus mucus plugging, which leads to unnecessary bronchoscopy in some cases. I learned this the hard way on a case where a patient had persistent O2 saturation issues in the low nineties on room air after a VATS wedge, and the fluoroscopy showed the left lower lobe refusing to fully expand. The fix was simple once identified: the pulmonary ligament was intact and needed to be released. I did not need to go back to surgery; we managed it conservatively and it resolved within 48 hours as the lung gradually expanded around the restraint.
When you are studying this for boards or clinical rotations, focus on the innervation difference, the fluid dynamics, and the reflex pathways. Those are the points where questions actually land, and they are also the points where clinical decisions diverge. Misunderstanding which layer is involved changes how you approach analgesia, how you interpret imaging, and how you decide whether a procedure needs regional block versus general anesthesia.
Get the Full Details