What Vital Observations Normal Range Actually Means in Practice
Most people look at a lab sheet or an EHR dashboard and assume the reference range printed next to a number is a hard rule. It isn't. A "normal" range is a statistical band derived from a population, usually the middle 95 percent of healthy adults. That means roughly one in twenty people who are perfectly fine will fall outside it. The trick isn't memorizing the bands, it's knowing when to trust them and when to treat them as a starting line. I spend most of my time working in acute care settings where we run through vital observation protocols dozens of times a day. Over the years I have learned that the Vital Observations Normal Range concept is far more useful when you think of it as a decision trigger rather than a verdict. Here is a practical breakdown of how it works on the floor.
Standard Adult Vital Observations Normal Range Reference
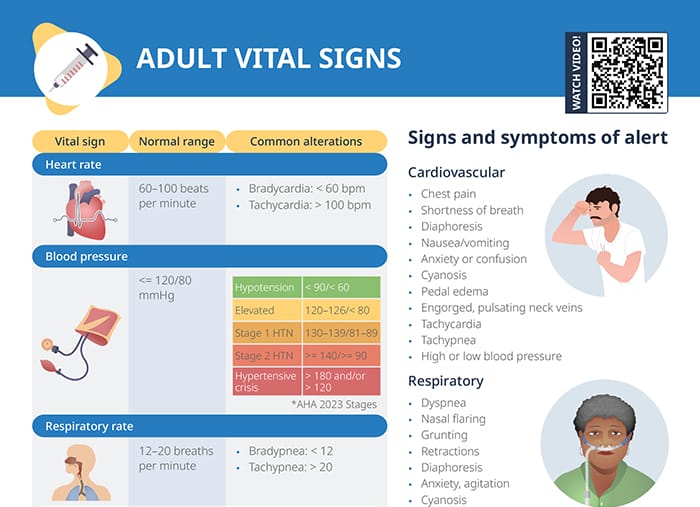
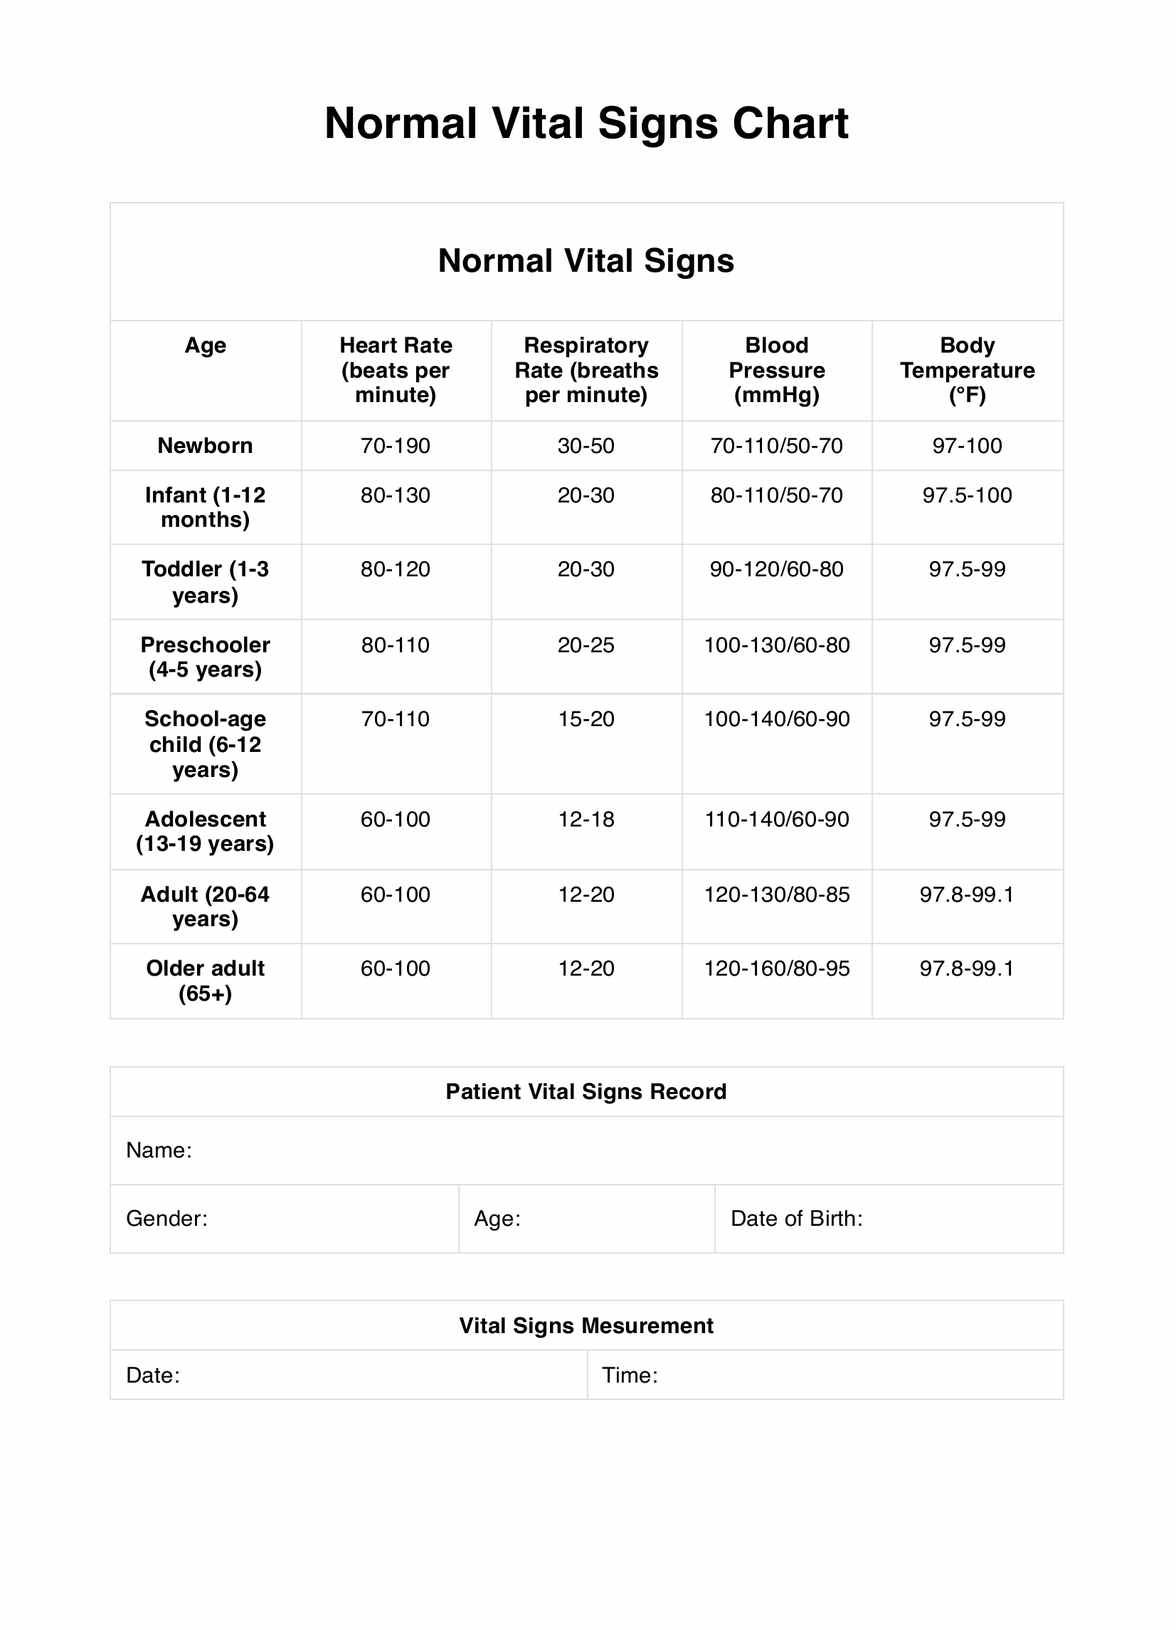
The baseline ranges for a resting adult at a typical healthcare facility are fairly consistent across most references, though individual institutions may set slightly different trigger thresholds. Here is what you are generally looking at: The most common mistake I see — and I have made it myself — is isolating a single parameter instead of looking at trends. A heart rate creeping from 78 to 95 over three hours is more clinically significant than a one-time reading of 108 after the patient ran to the bathroom. Trend data beats a single snapshot every time. Here is the practical workflow I use when I am reviewing vital observations:
First, establish whether the patient has a known chronic condition that shifts their baseline. Diabetics, hypertensives, COPD patients, and people on beta-blockers all sit at a different normal than the textbook ideal. If you do not have their baseline, assume it is off and document that assumption clearly. Second, check for compensatory patterns. A tachycardic patient with a normal blood pressure may be in early shock before the pressure drops. A bradycardic patient with warm extremities and a normal mental status is probably fine. The same heart rate in a diaphoretic, pale patient with altered consciousness is an emergency. Context changes everything. Third, verify the measurement technique before escalating. I once spent twenty minutes chasing a blood pressure that read 185/102 on an automated cuff only to realize the patient had their arm positioned below heart level while lying in a semi-Fowler's position. The reading was off by roughly 20 mmHg from the error alone. Repositioning and remeasuring brought it down to a credible 160/88. Always double-check the mechanics before you react.
Get the Full Details

Fourth, use escalation protocols, not personal guesswork. Most facilities have structured warning scores — NEWS2 in the UK and Australia, MEWS in many US hospitals, and similar early warning systems elsewhere. These tools convert raw numbers into weighted scores that trigger specific response pathways. They are not perfect, but they are better than hoping your instinct is right at 3 AM.
A Specific Edge Case That Cost Me Sleep
There was a patient a few years ago — post-operative hip replacement, routine recovery — whose temperature sat at 37.4°C, pulse 94, blood pressure 118/76, respiratory rate 16, and SpO2 96 percent. By the standard Vital Observations Normal Range criteria, she was essentially unremarkable. No alarms. No flags. I flagged the low-grade temperature as post-op atelectasis and moved on. Two hours later she deteriorated rapidly. The fever was actually the prodrome of a septic event from an infected surgical site. Looking back, I should have tracked the trend more aggressively. The temperature had climbed from 37.0°C to 37.4°C over four hours, which is a meaningful drift even though both points sit inside the normal band. I learned two things from that: serial measurements matter more than absolute values, and a low-grade persistent temperature in a post-surgical patient deserves more scrutiny than the standard range suggests. I started documenting temperature trends with a simple delta notation — change from the previous reading — on every set of vitals going forward. It added maybe thirty seconds per charting cycle and caught several similar cases early since then.
When the Normal Range Completely Fails You
There are several scenarios where relying on textbook normal ranges is actively dangerous: Pregnancy. A resting heart rate of 90 to 100 is completely normal in the third trimester due to increased blood volume. A respiratory rate of 20 to 22 is also typical. Applying non-pregnant ranges to pregnant patients generates false alarms and misses real problems. Sepsis in the elderly. Older adults frequently mount blunted inflammatory responses. A septic patient may present with a normal or even low temperature, a heart rate that is only mildly elevated, and a blood pressure that looks adequate until it suddenly does not. In this population, a change from baseline is almost always more informative than the absolute number.

Medications that mask abnormalities. Beta-blockers suppress tachycardia. Steroids blunt fever. Anticholinergics affect temperature regulation and respiratory patterns. When I encounter a patient on these medications, I widen my own internal zone and look harder for subtle signs — skin changes, mental status shifts, urine output — that automated systems will not flag. Athletic conditioning. A resting heart rate in the mid-40s is normal for an endurance athlete but would trigger a bradycardia workup in a sedentary person. I have seen athletes sent for unnecessary cardiac evaluations because the standard range was applied without context.
Tools and Resources
Most clinical institutions provide access to early warning scoring calculators through their EHR systems. If you are working outside a hospital, the National Early Warning Score (NEWS2) calculator from NHS England is freely available online and is widely referenced internationally. For pediatric ranges, the Pediatric Early Warning Score (PEWS) tools are essential since adult ranges are irrelevant for children. I also keep a laminated quick-reference card in my workspace with the core ranges and the most common adjustment notes. It takes up maybe four square inches and saves me from second-guessing myself during busy shifts. The British National Formulary and UpToDate also have well-maintained reference sections that I consult when I encounter a borderline case I am unsure about. If you are studying for clinical exams, I recommend learning the ranges first, then drilling the exceptions. The exceptions are what actually show up on the wards and in the field. Memorizing "60 to 100 for heart rate" gets you through flashcards. Knowing that a patient on metoprolol may present with a heart rate of 58 at rest and still be hemodynamically stable is what keeps patients safe.
Practical Takeaways for Vital Observations Normal Range
The ranges are a tool, not a truth. Always consider baseline, trends, context, and confounding factors before acting on a single number. When in doubt, repeat the measurement, check the technique, and look at the whole patient rather than the isolated value. That habit alone will catch more problems and create fewer false alarms than any memorized range ever will.