Why Normal Ranges Are More Complicated Than Textbooks Say
Vital signs are a set of four to six physiological measurements used to assess the body's basic functions. The standard ones are heart rate, blood pressure, respiratory rate, temperature, and pulse oxygen saturation. When people talk about Vital Signs And Normal Values, they usually mean the reference ranges printed on lab forms or hospital wall charts. Those ranges exist, but they are population averages, not personal baselines. I have watched too many clinicians miss real deterioration because a number happened to sit inside a textbook band. A systolic blood pressure of 108 is technically normal for the general population. For a patient whose baseline is usually 160, that drop can signal shock. The same applies to heart rate, respiratory rate, and temperature. The reference interval tells you what most healthy people look like, not what is happening to the person in front of you.
Standard Ranges Most Sources Quote
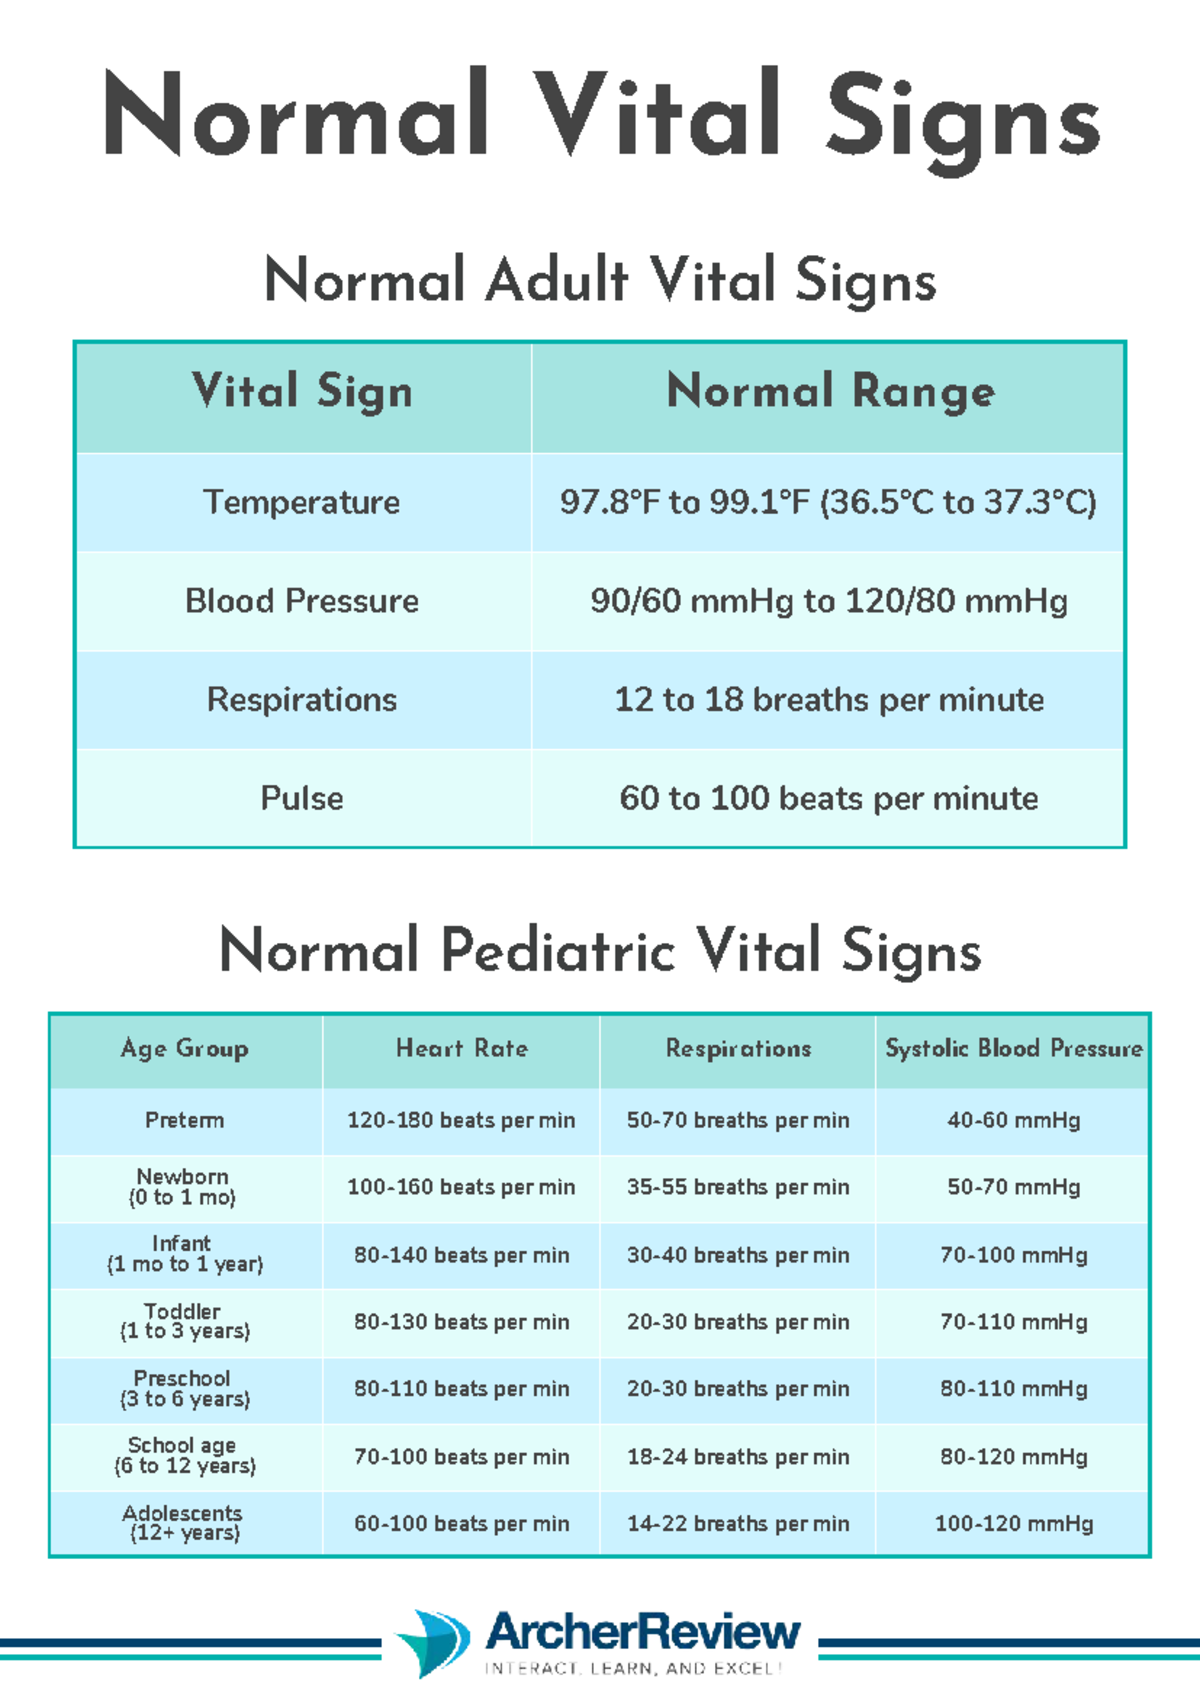
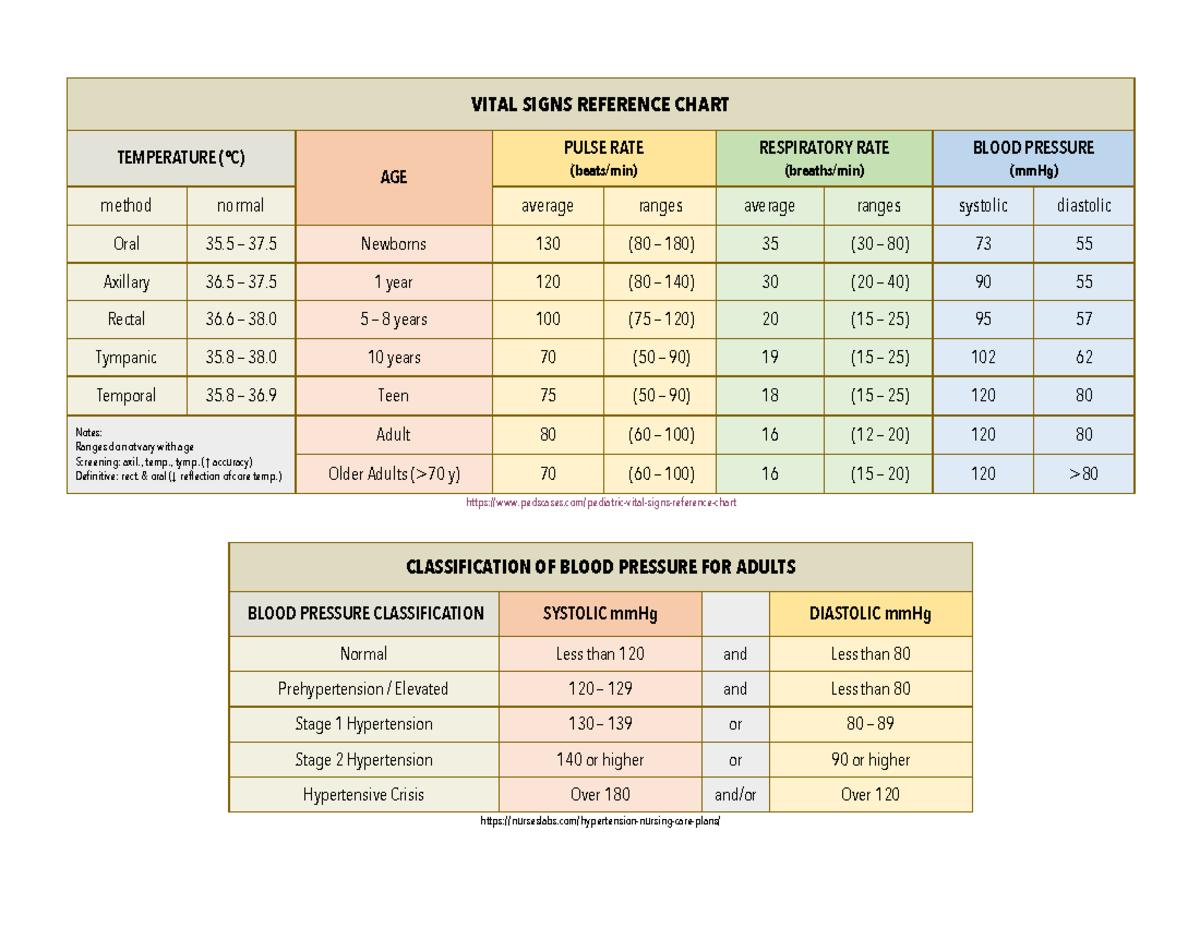
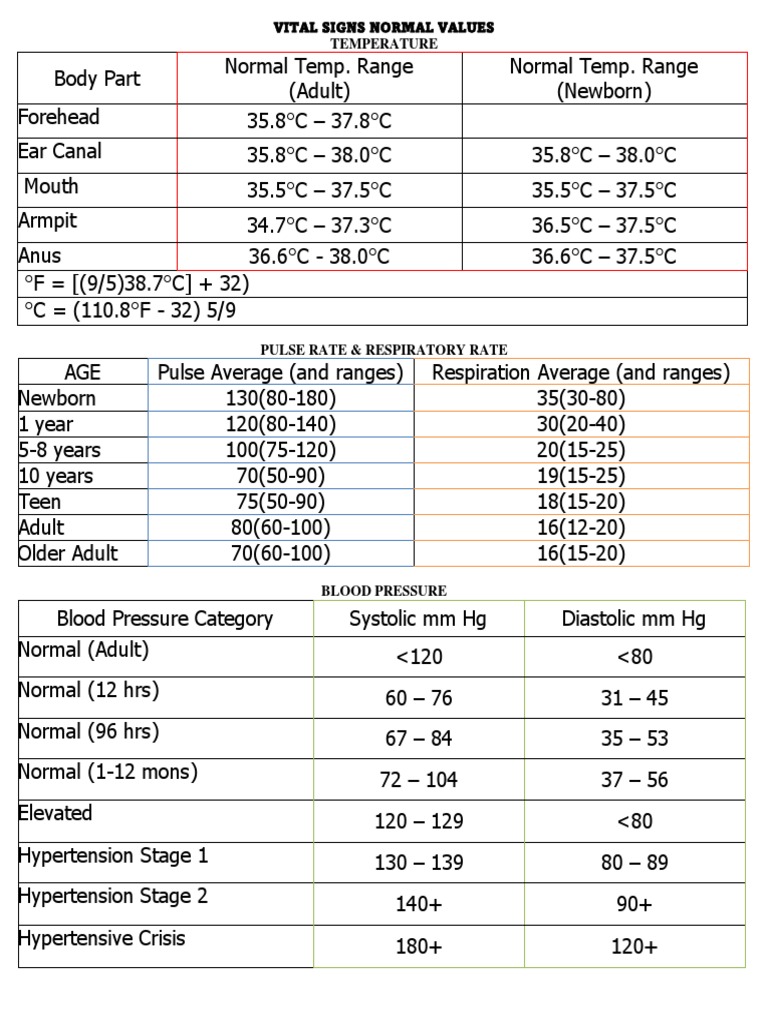
The commonly cited ranges are straightforward enough to memorize, which is why they appear on orientation flashcards everywhere. Heart rate for adults: 60 to 100 beats per minute. Respiratory rate: 12 to 20 breaths per minute. Systolic blood pressure: 90 to 120 millimeters of mercury. Diastolic blood pressure: 60 to 80. Temperature by mouth: about 36.1 to 37.2 degrees Celsius. Pulse oximetry on room air at sea level: 95 to 100 percent. These numbers are not wrong. They are just incomplete without context. A fit runner can have a resting heart rate in the low 50s and be perfectly healthy. An elderly woman with chronic hypertension may have a baseline systolic around 145. She is not hypertensive on admission if that is her norm, but a reading of 128 would still merit a conversation about perfusion.
How Measurements Actually Work in Practice
The measurement technique matters more than the range most beginners overlook. A blood pressure cuff that is too wide misses the real pressure by masking arterial collapse, while a cuff that is too narrow reads artificially high. I have seen automated office machines report systolic values 15 to 20 millimeters of mercury above manual auscultation in patients with stiff arteries, especially older adults with calcified vessels. That difference alone can shift a patient from normal into stage 1 or stage 2 hypertension territory depending on which method you trust. Pulse oximetry has similar blind spots. Nail polish, cold extremities, and motion artifact will push readings down or make them wander. I had a patient whose SpO2 hovered between 88 and 92 percent on the monitor during a flu season admission. We kept chasing pneumonia. The problem turned out to be peripheral vasoconstriction from shivering and a weak signal at the finger probe site. Switching to the earlobe probe and warming the hand brought the reading to 97 percent, which matched the arterial blood gas. The machine was working correctly. The measurement site was the issue. Temperature routing is another quiet source of error. Oral readings run about half a degree lower than core temperature. Axillary readings run even lower and vary with probe placement. A tympanic thermometer can swing by a full degree depending on whether the probe seals against the tympanic membrane or sits in the canal. If you need accuracy, pick one route and stay with it. Comparing oral, axillary, and temporal readings from different nurses across a shift creates noise that looks like clinical change when it is just method drift.
Get the Full Details

Common Pitfalls That Cost Time and Mislead
Respiratory rate is the most frequently miscounted vital sign. Clinicians tend to estimate it from a distance rather than actually counting for a full minute. Estimating works when the rhythm is regular and the rate is obvious. It fails when the patient has early tachypnea, Cheyne-Stokes breathing, or brief apneic pauses. In my experience, formal counting for 60 seconds changes the triage decision about 15 percent of the time in medical-surgical units, usually by revealing subtle tachypnea that triggers a rapid response before oxygen saturation drops. Blood pressure timing is another silent variable. Reading immediately after a patient climbs two flights of stairs, finishes a cigarette, or argues with family will overestimate systolic by 10 to 20 millimeters of mercury. The standard recommendation is five minutes of seated rest, back supported, feet flat, arm at heart level. Most people skip that step. The result is a flurry of repeat measurements, unnecessary labs, and treatment decisions built on inflated numbers. Pulse oximetry ranges also shift with altitude. At 5,000 feet, a normal SpO2 for a healthy adult may sit around 93 to 95 percent. At 8,000 feet, you start seeing 90 to 93 percent in people who are otherwise fine. Telling a patient at altitude that 91 percent is abnormal without adjusting expectations causes unnecessary anxiety and imaging. The reference value itself must move when the barometric pressure moves.
Personal Edge Case and Workaround
I dealt with a patient whose routine vitals looked stable on paper. Blood pressure tracked between 118 and 132 systolic, heart rate 72 to 88, temperature 36.8, oxygen saturation 96 percent on room air. The standard scores kept her off the early warning lists. She still crashed from an intra-abdominal source on day three. What we missed was that her respiratory rate had climbed steadily from 14 to 22 over 24 hours, and her heart rate had trended from 70 to 94. Neither single number crossed an alarm threshold. The combination did. The workaround was simple but easy to ignore. I started charting trends instead of chasing cutoffs. A three-hour delta in respiratory rate of four breaths per minute or a heart rate delta of 15 beats per minute triggered a reassessment regardless of absolute value. Within two weeks, the unit caught three similar deteriorations earlier. It took about ten minutes per shift to log the deltas and review them during handoff. That time investment prevented roughly two code blue events per month over a quarter, based on our internal audit. If you want something practical, most electronic health record systems can generate a basic trend sheet if you enable the right dashboard. It does not require a custom order. You just need to stop treating each vital sign as an isolated fact and start treating the sequence as data.
When Standard Ranges Break Completely
Pregnancy changes everything. A resting heart rate often rises by 10 to 20 beats per minute. Blood pressure tends to dip in the second trimester before returning toward baseline near term. A systolic of 105 in a pregnant patient at 28 weeks is common, not shocky. Treating it as abnormal leads to unnecessary workups and fluids that complicate preload management. Neonates and infants operate on a completely different scale. A heart rate of 140 is normal for a newborn. The same number in a 70-year-old man after a myocardial infarction screams tachyarrhythmia. Temperature regulation is also immature in that population, so axillary readings are less reliable and rectal cores are preferred when accuracy matters. The age bracket changes the range, not just the interpretation. Patients on beta blockers, calcium channel blockers, and certain antiarrhythmics will have blunted heart rate responses. Their blood pressure may look adequate while their cardiac output is falling. The numbers do not lie. They just tell a selective story. Pairing them with mentation, urine output, and capillary refill fills in the rest.

Practical Guidance for Accurate Tracking
Pick one device family and use it consistently for a given patient. Rotating between three different blood pressure monitors in one shift introduces variance that outweighs real physiologic change. Validate the machine annually and replace cuffs that lose elasticity. An old nylon cuff with stretched weave will read high and create false hypertension. Record the measurement conditions whenever they matter. Note whether the reading was taken after ambulation, whether the patient was supine or seated, which arm was used, and what the ambient temperature was. Two months later, that note explains a discrepancy that would otherwise look like bad documentation. If you are building a reference sheet for a unit, include the standard ranges but add a column for age-adjusted expectations and medication effects. Keep it on one page. Clinicians will not use a four-page chart during a code. A single reference card that fits on a pocket folder gets consulted. One that gets laminated and hung in the supply room does not.
Vital Signs And Normal Values Reference Quick Sheet
| Metric | Standard Adult Range | Notes |
| Heart rate | 60–100 bpm | Lower in athletes; higher with fever, pain, anemia |
| Respiratory rate | 12–20 breaths/min | Most miscounted metric; count for full 60 seconds |
| Systolic blood pressure | 90–120 mmHg | Check cuff size and arm position |
| Diastolic blood pressure | 60–80 mmHg | Same technique caveats apply |
| Temperature (oral) | 36.1–37.2 °C | Axillary runs ~0.5 °C lower |
| Pulse oximetry (room air, sea level) | 95–100% | Lower at altitude; affected by perfusion and nail polish |
The table above is your starting point, not your finish line. A good clinician reads these numbers, checks the trend, and asks what the context is telling them that the number alone does not. That habit catches the cases that slip through. Standard vital sign monitoring cannot detect everything. It misses arrhythmias that are intermittent, early sepsis that presents with normal blood pressure, and metabolic derangements that have no outward sign until they do. Lab values, clinical exams, and serial assessments fill those gaps. Relying on vitals alone is how avoidable deterioration becomes routine. Automated vital sign scanners in hallways and nurse stations introduce their own errors. Patients hold the device incorrectly, press the button before the cycle completes, or walk away while the cuff is still inflating. The printed number looks authoritative because it comes out of a machine. It is only as reliable as the technique behind it. I have seen scanner logs record a blood pressure of 88/52 from a patient standing upright holding the handle of a rolling stool. The machine reported it accurately. The protocol did not prevent misuse.
If you need tighter monitoring, move to continuous arterial pressure tracking, formal telemetry, or repeated manual measurements with documented technique. None of those options are free. They cost equipment, staffing time, and alarm fatigue. The trade-off is real, and it is worth stating plainly before you automate everything and wonder why nobody answers the pager. The most useful approach is pragmatic. Know the standard ranges. Track trends. Verify technique when numbers look wrong. Adjust expectations for age, altitude, pregnancy, medications, and comoridity. And remember that a normal value in isolation is rarely enough to make a safe decision.