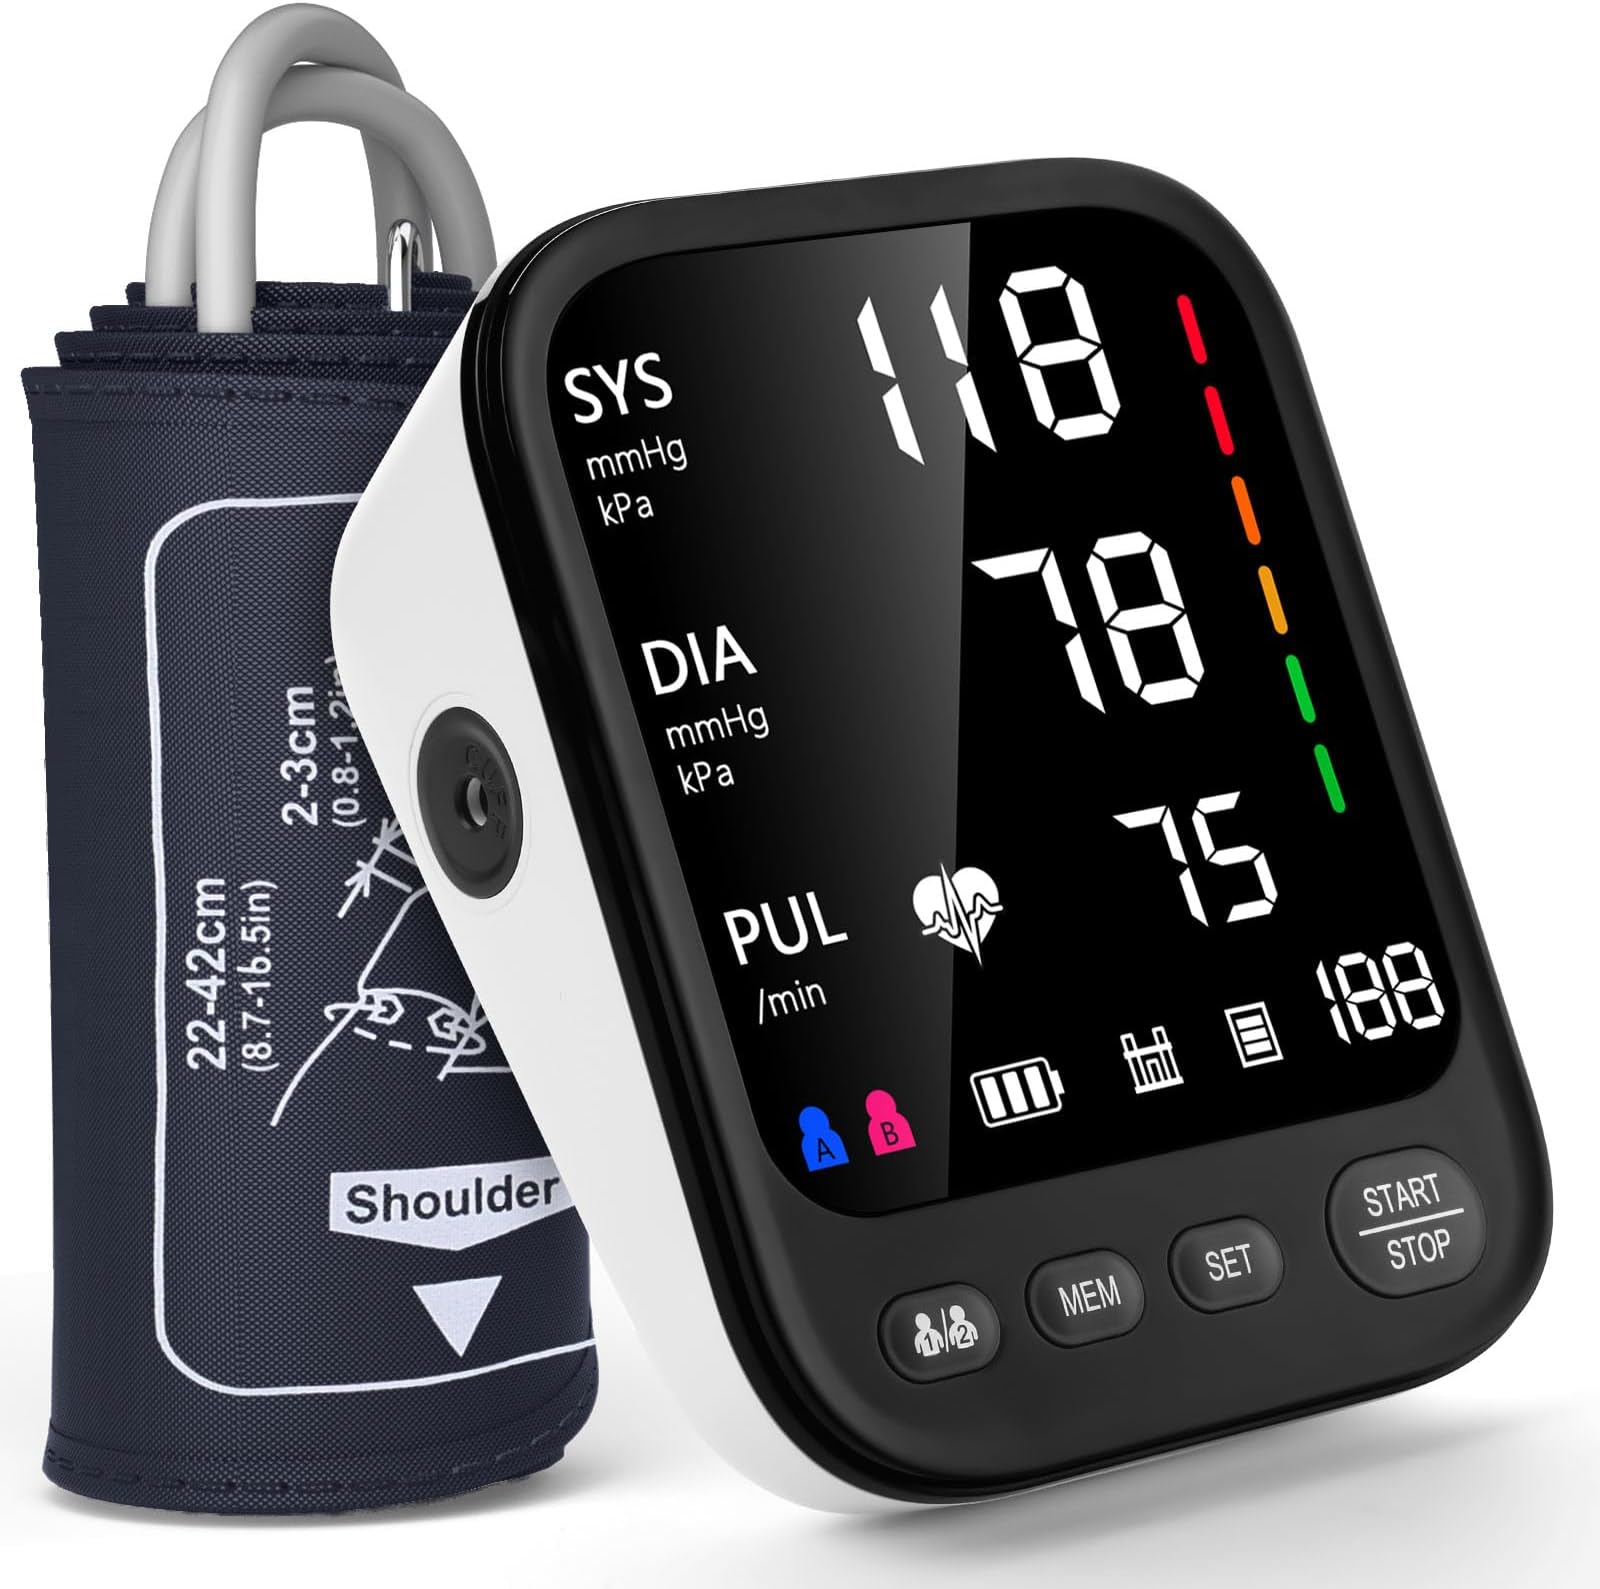
Manual Versus Automatic Blood Pressure Monitoring
Vs Automatic Blood Pressure: What Actually Works
I've been dealing with blood pressure measurement tools in clinical settings for years now, and the debate between manual and automatic monitors comes up constantly. Most people think it's straightforward — just pick one and go. It isn't. The reality is messier, and picking the wrong approach can give you readings that look fine on paper but are completely wrong in practice. Manual blood pressure means using a sphygmomanometer with a stethoscope. You inflate the cuff, listen for Korotkoff sounds, and note the pressure when you hear the first beat and when the sound disappears. Automatic monitors do this electronically — they inflate the cuff, use oscillation detection, and give you a readout. No listening required. Neither method is objectively better. They're better or worse depending on your situation, your environment, and honestly how careful you're being. Here's where it gets tricky. Automatic monitors are generally more accessible, which is why they dominate home use and most clinic workflows now. But they have a known issue with arrhythmias. If someone has atrial fibrillation or frequent ectopic beats, the oscillometric algorithm can get confused and produce readings that swing wildly between attempts. I ran into this a few months back with a patient whose home monitor was showing 140 over 90 one minute and 118 over 76 the next. We compared it against a manual reading and the manual was consistently in the 120s over 80s range. The automatic monitor was just guessing between beats. That's not a rare edge case — it's a documented limitation in the literature. The workaround was straightforward: switch to manual measurements for anyone with a known irregular rhythm, and flag the automatic readings as unreliable in the chart.
Another thing people don't always account for is cuff size. Both manual and automatic systems are only as good as the cuff fit. An automatic monitor with a standard adult cuff on someone with a large arm will read higher than the actual pressure. I've seen this happen repeatedly with automated pharmacy kiosks where the cuff is fixed-size and barely accommodates most arms above 16 inches. The reading can be off by 10 to 20 millimeters of mercury just from a poor fit. With manual measurement, you can swap cuffs freely. With many automatic units, you're stuck with what's provided unless you bring your own validated cuff, which most machines won't even accept. Positioning matters for both methods, but automatic monitors are less forgiving of bad posture. If the arm isn't supported at heart level, the oscillometric sensor still takes the measurement — it just gives you a wrong number and you have no idea. With manual measurement, the operator can often sense when something feels off. The sounds change. The pulse character shifts. There's a human feedback loop that the machine doesn't have. For home use, an automatic upper-arm monitor from a reputable brand is usually the right call. Look for devices validated by organizations like the Stroke Association or the British Hypertension Society. Wrist monitors exist but they're finicky — you have to hold them exactly at heart level every single time, and most people don't. Finger monitors are worse. Don't bother with those.
If you're measuring manually, the learning curve is real. You need to know where to place the stethoscope, how quickly to deflate, and how to distinguish the first Korotkoff sound from ambient noise. A lot of people who try manual measurement at home give up within a week because the sounds are subtle and their technique is inconsistent. That's fine. Automatic is probably the better choice for most home users. The biggest pitfall I see with automatic monitors is the expectation of perfection. These devices are accurate within about 5 millimeters of mercury under ideal conditions. That's close enough for screening and most routine tracking. But if you're making medication decisions based on a single reading from an unvalidated device, you're working with noise, not data. Take three readings, spaced two minutes apart, and average them. Write down the numbers. Bring the log to your doctor. That's what actually moves the needle.
Get the Full Details