Getting Patients From Walking to Running After Injury
The walk-to-run progression is one of those things that sounds straightforward on paper and falls apart the moment you try to apply it to real people. Most PT programs I see just copy-paste a generic template, which works fine for textbook cases and wrecks people who don't fit the mold. The core idea is simple enough: you take someone who can walk without pain and gradually introduce running mechanics while managing tissue load. But the actual implementation is where most programs go wrong. I spent years watching people bounce between programs, never quite making the transition because nobody was actually monitoring their response to each stage. You'd have someone who could jog for thirty seconds on day one of a run program and still be doing the same thing three weeks later, only now with added knee irritation because the baseline wasn't actually solid.
Walk To Run Program Physical Therapy
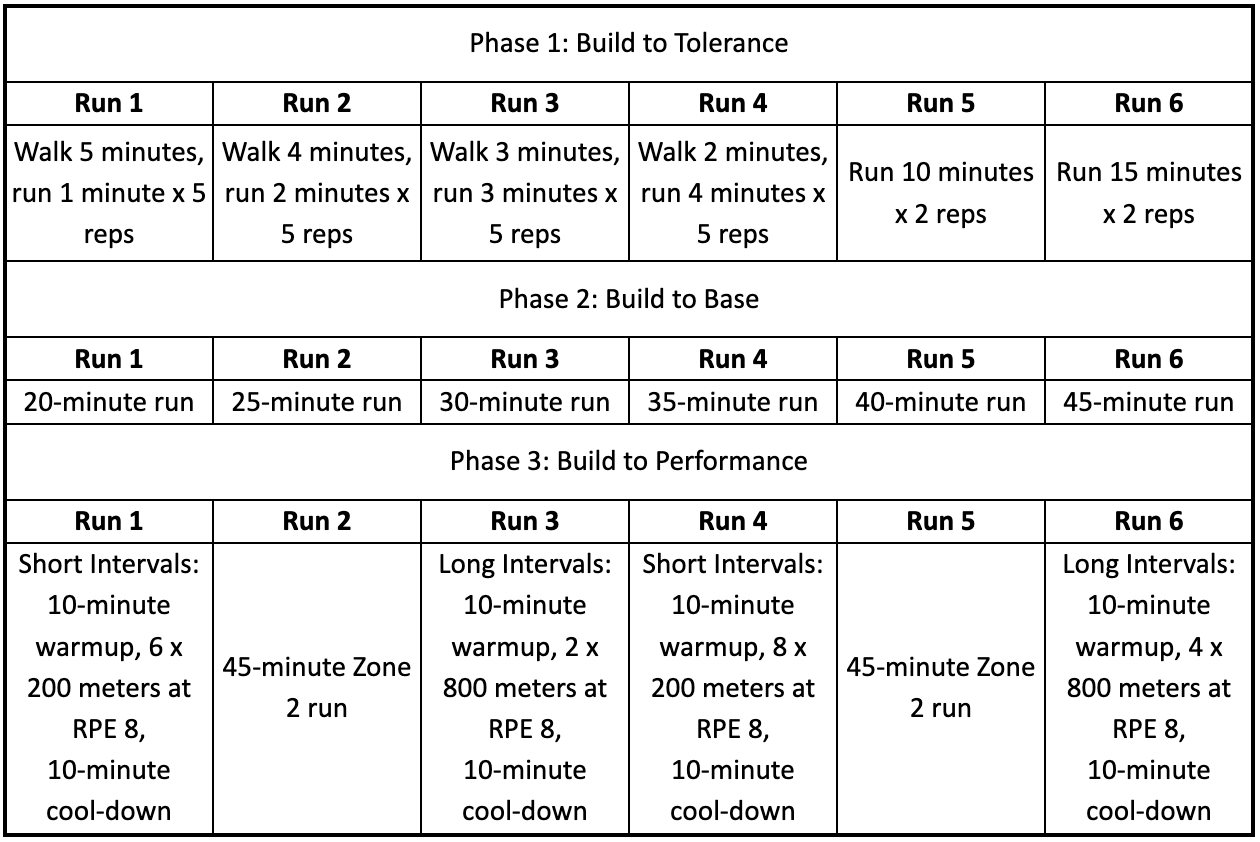
At its foundation, this approach structures the return to running around measurable progressions rather than arbitrary timelines. You're not counting weeks. You're counting reps, distance, and symptom response. The typical framework moves through walking tolerance, walk-jog intervals, continuous jogging, and then running-specific strength work. Each stage has hard criteria before you advance. If a patient can't complete the current stage without a symptom spike that lingers past twenty-four hours, they stay there. Period. Here's what I actually use in practice. I start with a walking assessment that most people skip. Can they walk thirty minutes at a moderate pace without limping? Can they do it on uneven ground? Can they handle stairs without guardrails? If the answer to any of those is no, you're not ready for the walk-jog transition. I've seen too many programs throw people into interval training when their walking mechanics were already compensated. That just layers running stress on top of existing problems. Once walking clears, you move into walk-jog intervals. A common starting point is thirty seconds of jogging followed by ninety seconds of walking, repeated eight to ten times on a flat, predictable surface. The key variable most programs ignore is the surface. Concrete is brutal for returning runners. Grass or a track surface cuts joint loading significantly and makes the early stages tolerable instead of miserable. I always send my patients out to a rubberized track or a packed dirt path before anything harder.
The progression itself follows load management rules. I typically increase either duration or intensity but not both in the same session. A common mistake is adding more jogging time while also pushing for faster paces, which doubles the mechanical demand without giving tissues time to adapt. The 10 percent rule gets thrown around a lot in these programs, but it's too rigid. What matters more is symptom monitoring. If someone's pain during the session stays at three or below and doesn't flare afterward, you're probably in a safe zone. Above four during exercise or any next-day worsening means you backed off too slowly. Strength work is non-negotiable and where most programs underdeliver. Running places roughly two to three times body weight through each leg per stride. If someone's hip abductors and glutes are weak, that force goes somewhere else. Usually the knee or the Achilles. I prescribe single-leg squats, Bulgarian split squats, and calf raises with progressive loading at least twice weekly throughout the entire return-to-run process. Not before. Not after. During. People treat strengthening like it's optional prep work instead of the actual foundation. Here's a specific problem I ran into repeatedly that most templates don't address. Patients who've had ankle sprains or Achilles issues often develop a subtle but consistent hesitation on the affected side during the push-off phase of running. It shows up as slightly reduced knee flexion on landing and a shorter stride on that side. Most coaches miss it because they're watching for obvious limping. What I started doing is having patients run in place first and watching the ground contact symmetry. If one foot taps down noticeably sooner than the other, that's your tell. The workaround is adding single-leg hops and bounds on the affected side before progressing interval time. Ten minutes of that, twice a week, usually fixes the symmetry issue within two to three weeks. Skipping it just means the patient runs with a compensation pattern that becomes permanent if you advance too fast.
Get the Full Details
Another thing nobody talks about is foot strike pattern. You'll hear opinions about forefoot versus heel striking that range from well-informed to completely unhinged. The practical reality is that most returning runners naturally shift toward a more forefoot strike because it feels safer on irritated tissues. That's fine as long as it doesn't create calf or Achilles problems. I don't coach strike pattern unless it's extreme. I coach cadence instead. Getting someone to a step rate above one hundred seventy steps per minute reduces load on the knees and hips significantly. It's a simpler intervention with more predictable results. Timing estimates vary enormously depending on the injury. An ACL reconstruction with a good rehab beforehand might see a return to light jogging around week six to eight, with full running capability around month four to five. An Achilles repair is slower. Eight weeks minimum before any jogging, and we're usually talking three to four months before comfortable continuous running. Stress fractures require you to skip straight to cycling or swimming until healing is confirmed, which adds months. There's no shortcut that doesn't involve either re-injury or surgery. The biggest bottleneck I see is psychological. Patients either rush forward because they're eager or they stall because they're scared. Both are problems. For the eager ones, I use objective criteria and refuse to budge when they haven't met the threshold. For the scared ones, I break things down into smaller steps and celebrate the tiny wins. Both approaches require you to actually know the patient instead of following a script.
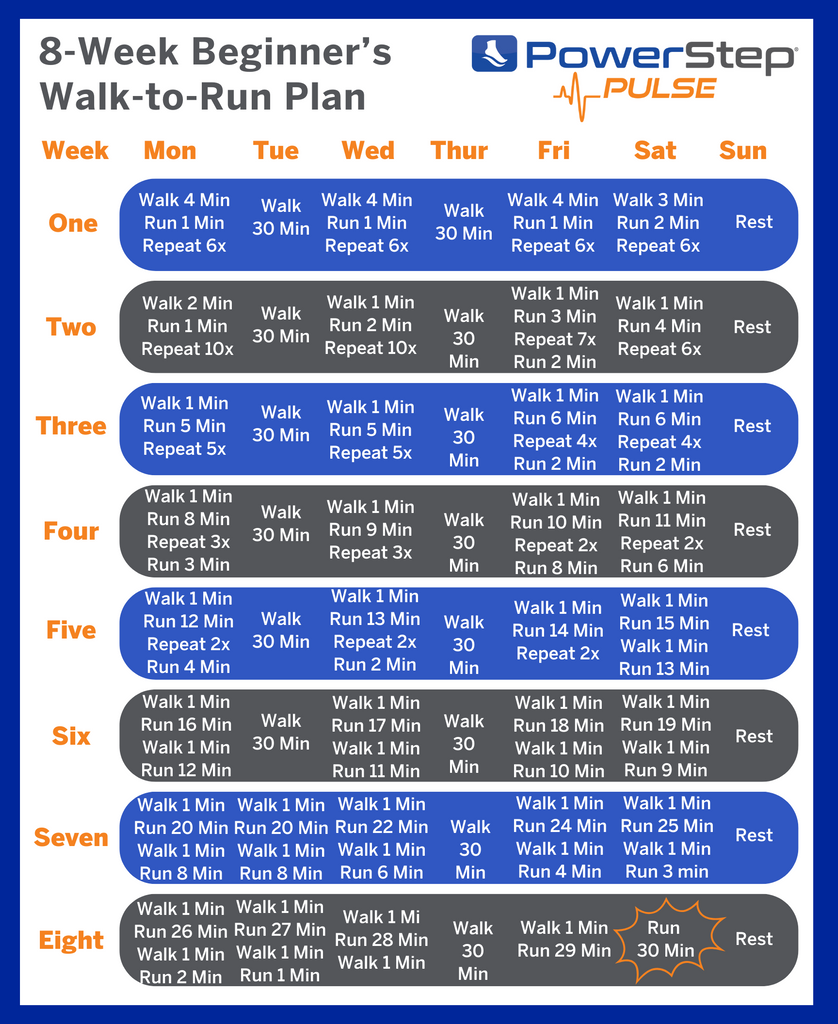
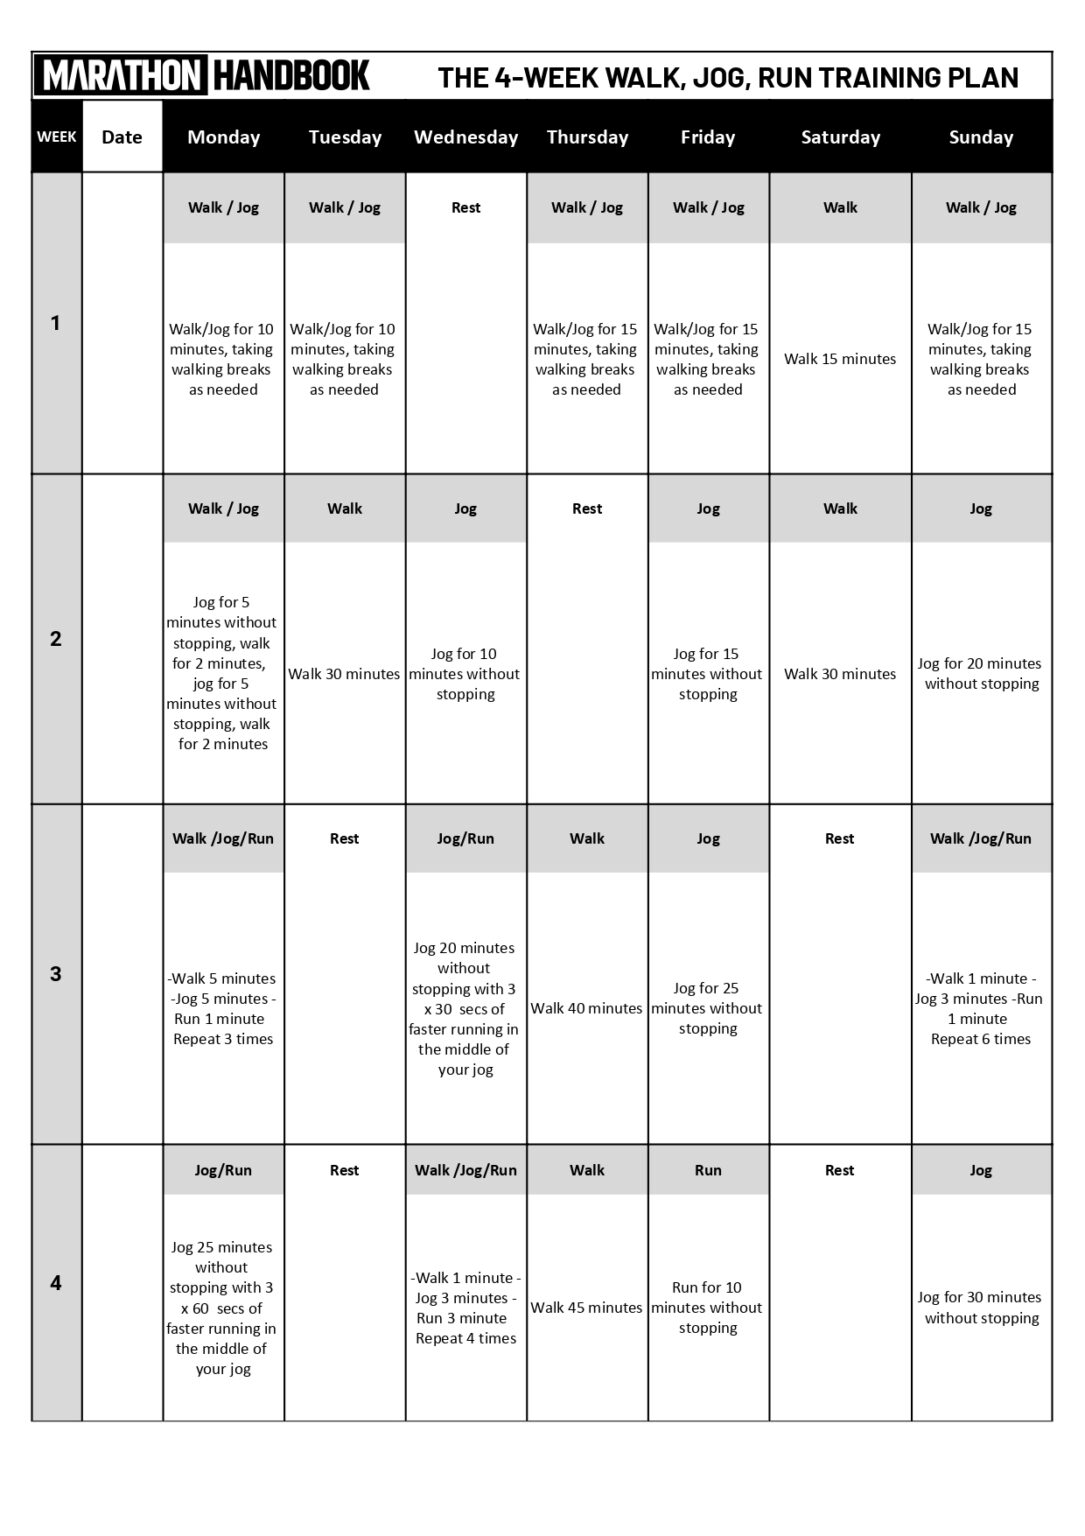
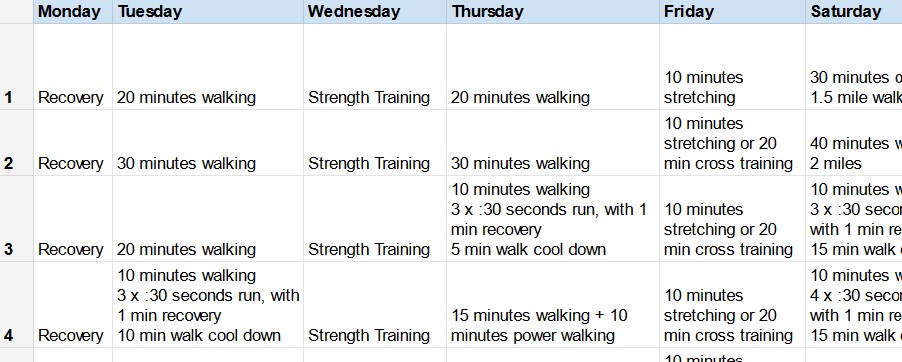
Programs like the official C25K exist and they work for healthy people. They don't account for post-injury tissue status, so they're a poor fit for anyone coming back from something. The Galloway method of run-walk intervals is closer to what you need clinically, but it still assumes a baseline fitness level that injured people don't have. Building your own progression from first principles gives you more control than adapting someone else's plan. If someone asks me for a starting template, I give them something like this and adjust based on their assessment. Walk twenty minutes comfortably three times a week for a week. Add a thirty-second jog every two minutes for the last five minutes. Repeat for another week. Then increase jog intervals to forty-five seconds. Then sixty. Then ninety. Then two minutes. At each step, if symptoms spike, drop back one level and hold there until they settle. Strength training happens on the same days as the walking or jogging, not on separate days where it gets skipped. By the time someone completes this, they're usually running continuously for twenty to thirty minutes, which for most injured patients represents months of work. The honest limitation of walk-to-run programs is that they require consistency and patience, neither of which comes naturally to people recovering from injury. People want to get back to what they love, and the linear progression doesn't match the non-linear reality of healing. Some days you feel great. Some days you can barely walk. The program needs to accommodate that fluctuation without making the patient feel like they're failing. That's the part that can't be coded into an app. It takes a therapist who's actually watching and adjusting in real time.