Understanding weight standards for older women
Most people looking at a Weight Chart For Seniors Female want something simple, but the reality is more complicated than a single table. The charts you see online are usually adapted from NHANES data or BMI-based references, and they have real limitations when applied to actual seniors. Let me explain how these charts actually work and where they fall apart.Weight Chart For Seniors Female
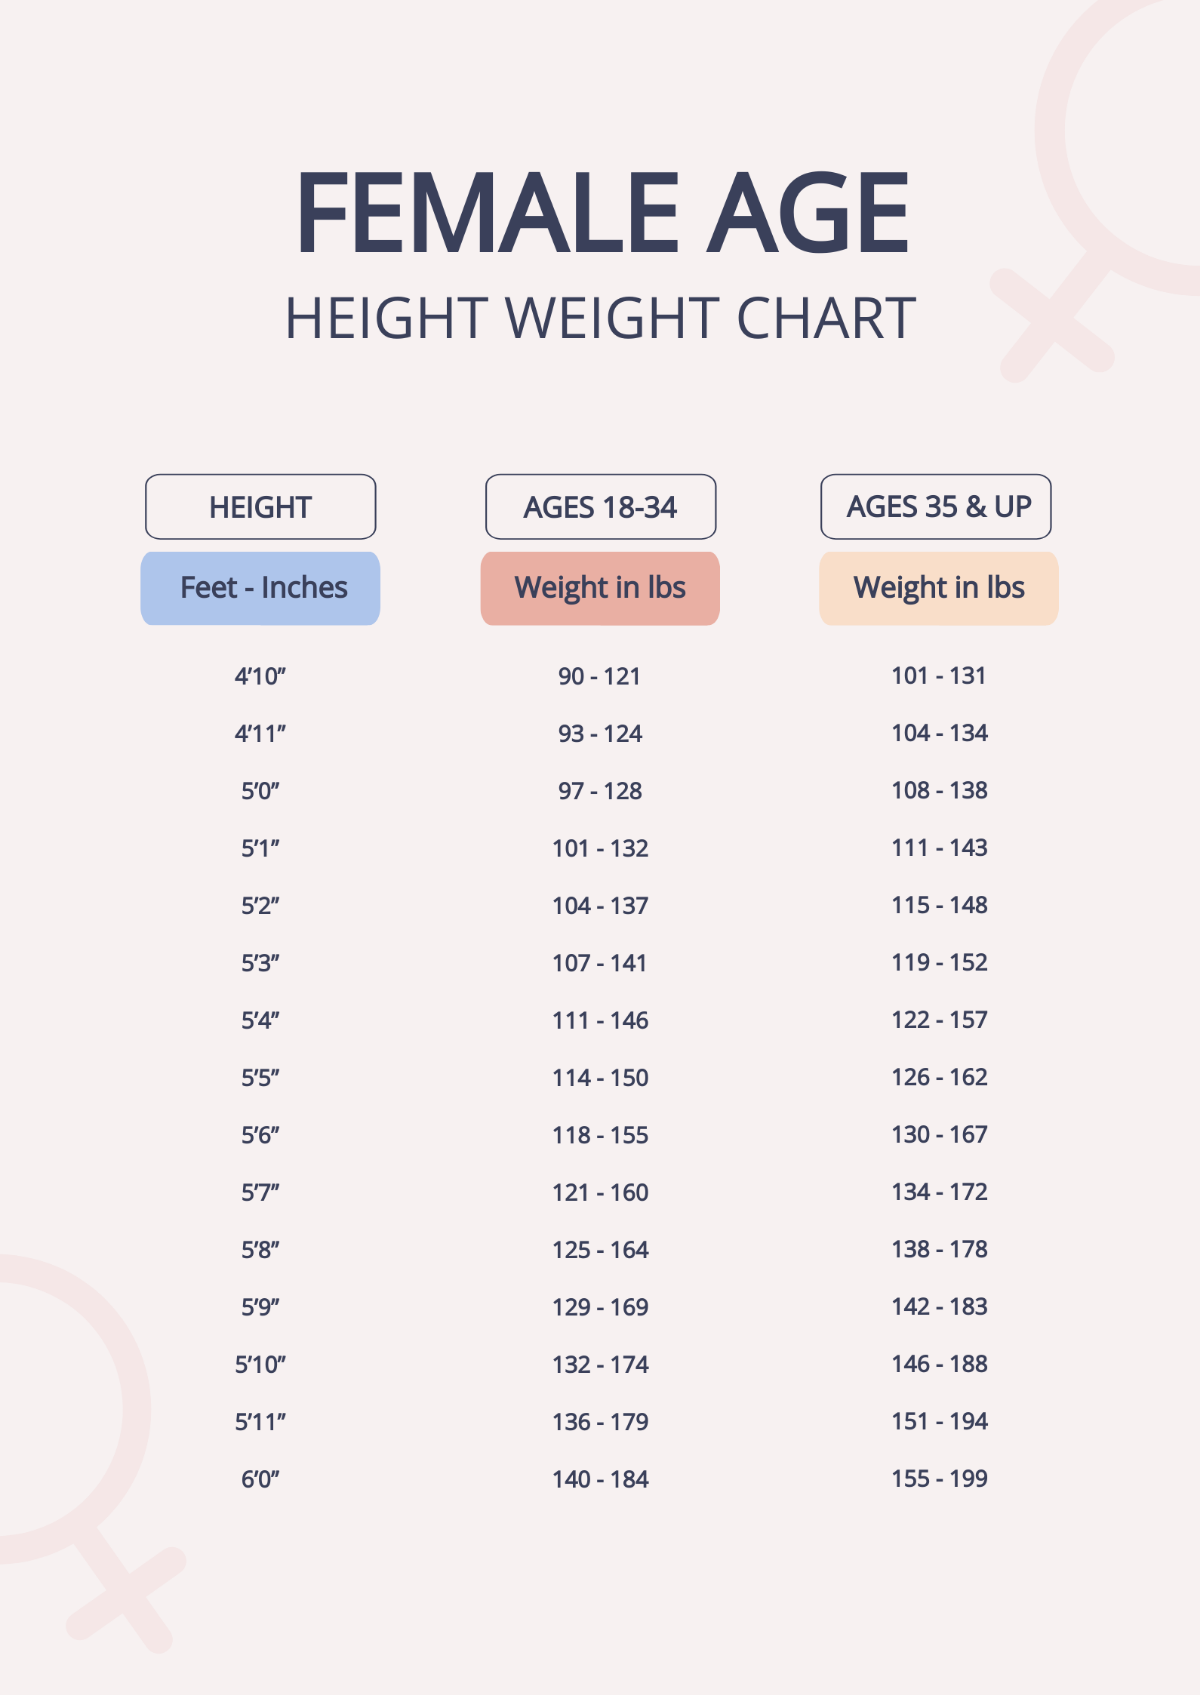
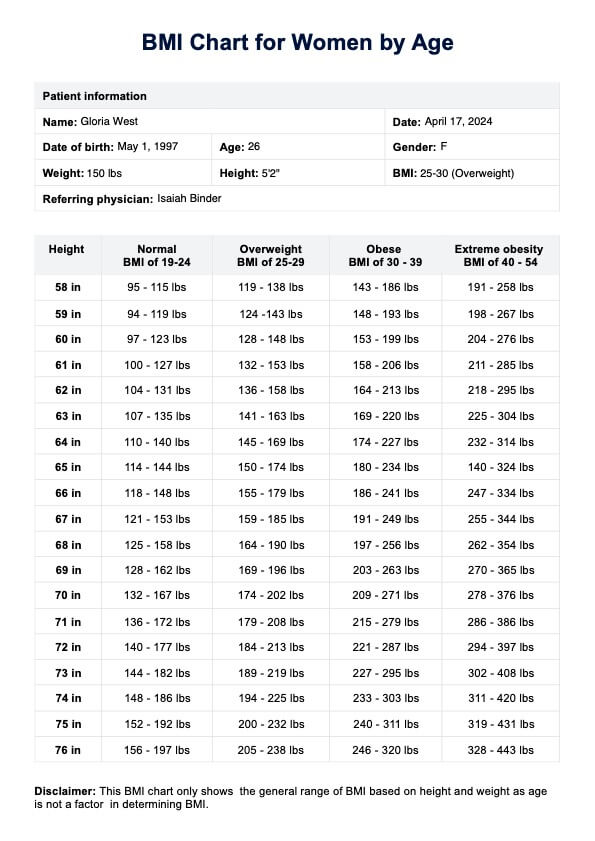
The standard approach uses height paired with age brackets to suggest a range. Here is what a typical reference looks like at a glance:5'0" (60 inches): 65-74 years: 111-141 lbs 75+ years: 116-148 lbs
5'4" (64 inches): 65-74 years: 123-157 lbs 75+ years: 128-164 lbs
5'8" (68 inches): 65-74 years: 137-174 lbs 75+ years: 143-182 lbs
Get the Full Details

Why the chart fails in practice
I dealt with this directly when working with a client whose mother was seventy-eight. She was at the low end of the chart for her height, technically within range but barely. The chart looked fine on paper. What it didn't show was that she had lost twelve pounds over eighteen months without trying. That kind of unexplained weight loss in an older woman is a red flag for everything from thyroid issues to early-onset dementia to medication side effects. The chart wouldn't have caught it because she was still "in range."What actually matters more than the chart
Instead of fixating on a number, look at body composition and functional status. Handgrip strength, walking speed, and balance tests predict health outcomes far better than weight alone. A woman who weighs 155 pounds at seventy-two and can climb two flights of stairs without rest is in a much better position than someone who weighs 135 pounds and struggles with the same task. BMI itself becomes unreliable after about sixty-five because it doesn't distinguish between muscle and fat, and older women lose muscle mass naturally. Two women the same height and weight can have completely different health profiles based on body composition. That's why the chart should never be the final word.A more useful approach
When to ignore the chart entirely
If there is osteoporosis, chronic kidney disease, congestive heart failure, or a history of eating disorders, standard weight tables don't apply. These conditions change what a healthy weight looks like. An endocrinologist or geriatrician can establish a personalized target range based on lab work, bone density scans, and metabolic markers. That takes about twenty minutes in a clinical setting and is worth infinitely more than any downloaded chart. The bottom line is that a weight chart for an older woman is a starting point, not a diagnosis. It's useful for spotting obvious problems, but it misses most of what actually matters in this population.