Writing an HPI for a Wellness Exam When There Is Nothing to Report
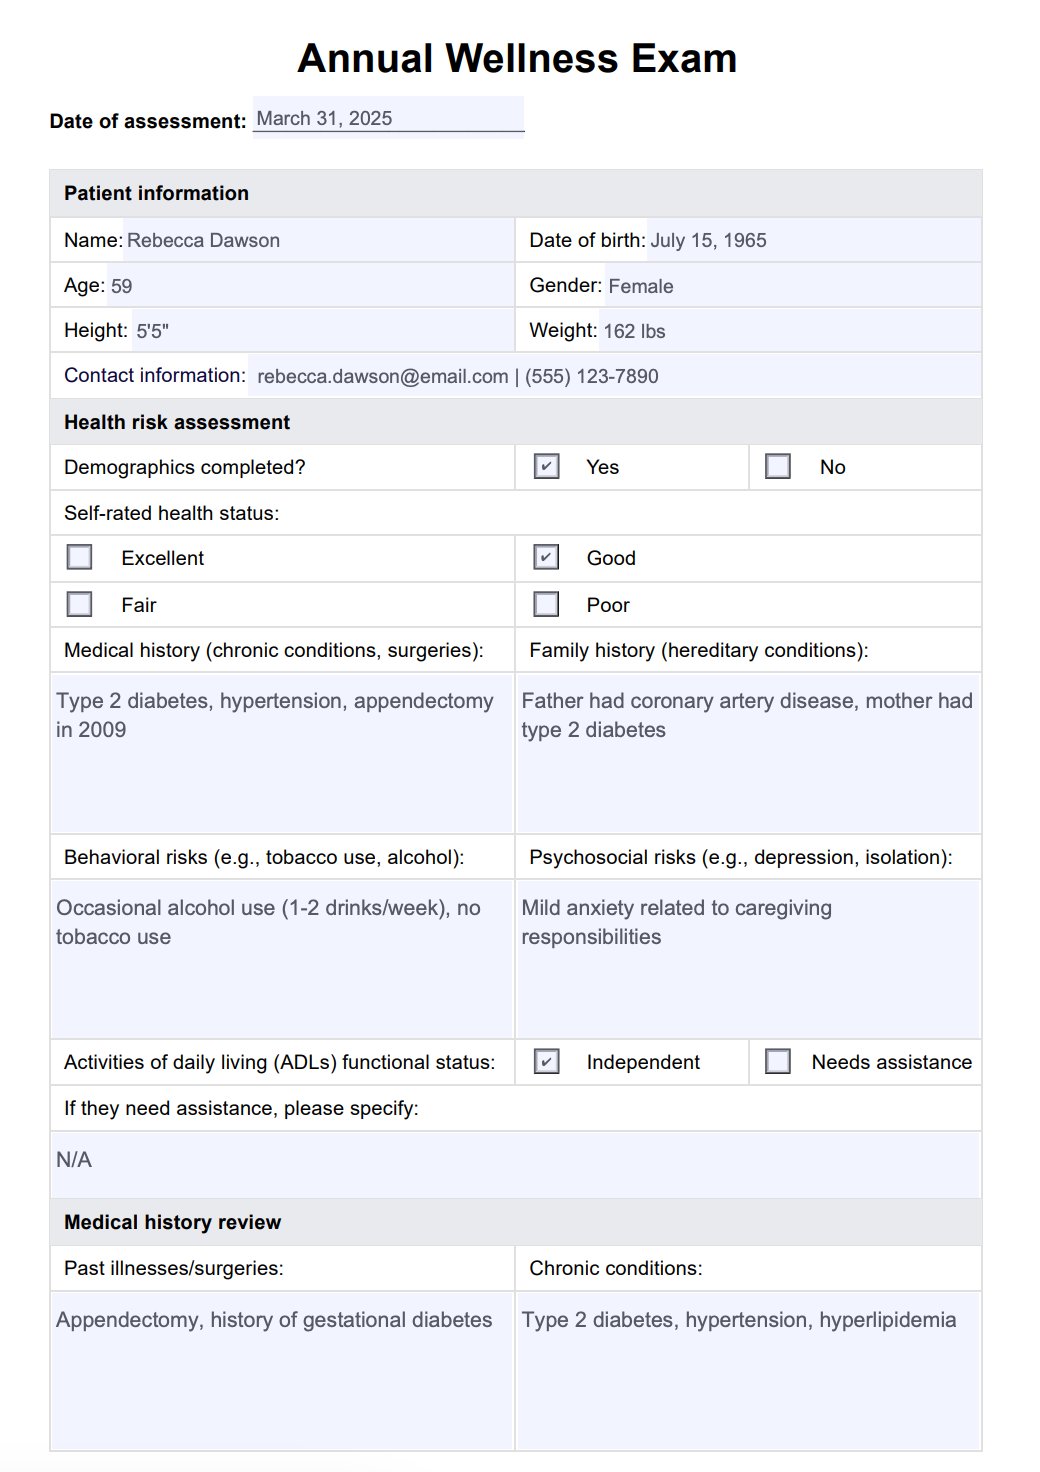
The History of Present Illness is supposed to document why a patient is presenting today. In a true wellness or preventive visit, that reason doesn't exist. The patient is here because their last exam was more than twelve months ago. They feel fine. This creates a documentation problem that most EHR templates do not handle gracefully, and it shows up constantly in audits. I ran into this directly when a payer audit flagged a wellness visit where the HPI was left blank because the encounter template had no required field for it. The reviewer considered it a missing component and reduced the claim. The fix wasn't to invent symptoms that weren't there. It was to document the encounter's purpose and the review of systems that confirmed absence of complaints, which satisfies the medical necessity requirement for an annual preventive visit under CPT 99381 through 99397.
Wellness Exam Hpi Example Structure
For a new patient aged 42 presenting for an annual preventive examination, the HPI might read like this. The patient is a 42-year-old female who presents today for her annual wellness examination. She reports feeling well overall with no acute concerns. She denies chest pain, shortness of breath, palpitations, syncope, headaches, visual changes, abdominal pain, changes in bowel or bladder habits, fevers, chills, or unexplained weight loss. She endorses routine exercise three times weekly and denies tobacco use. She last completed a physical examination twelve months ago with no abnormalities noted. This visit is being scheduled per USPSTF-recommended preventive care intervals. For an established patient, the structure shifts slightly. The patient is a 68-year-old male who presents for his routine annual preventive examination. He reports feeling at his baseline. He denies any new or worsening symptoms. He specifically denies chest discomfort, orthopnea, edema, dysuria, hematochezia, melena, lightheadedness, or focal neurological deficits. His chronic conditions, hypertension and hyperlipidemia, remain stable on current medications. He reports no medication side effects. He last had a preventive visit eleven months ago. He is here today to maintain his preventive care schedule. These examples share a pattern. You state the patient's reason for being here, confirm they are asymptomatic, enumerate the relevant denial categories for their age and sex, and connect the visit to guideline-based preventive care. The HPI in a wellness exam is not about pathology. It is about establishing that no active problem brought the patient in today while still meeting the documentation standard for a chief complaint and HPI component.
What the EHR Usually Gets Wrong
Most built-in templates force you into a symptomatic HPI box that asks for onset, location, duration, character, aggravating factors, and radiation. These are the OLDCARTS or OPQRST elements meant for diagnostic visits. Using them for a wellness visit either produces garbage documentation or requires you to fill every field with negations, which looks suspicious to auditors. The workaround I use is to bypass the encounter's symptom-driven HPI template entirely. I create a separate HPI note field if the EHR allows it, or I use a free-text note attached to the visit type. In Epic, this means choosing the wellness encounter type rather than a problem-oriented one, which changes the default template. In AthenaHealth, I use the preventive exam note template instead of the standard SOAP. In Meditech, the wellness module has its own HPI section that doesn't ask for onset or severity. If your system forces the standard HPI template regardless of encounter type, the practical solution is to enter a single sentence in the chief complaint field like "Routine annual wellness examination" and then move the HPI content into a progress note or a separate assessment and plan section. Some audit reviewers accept this arrangement. Some don't. The safest approach is to verify with your credentialing body or compliance officer which structure your specific EHR version requires.
Get the Full Details
The Review of Systems Does the Heavy Lifting
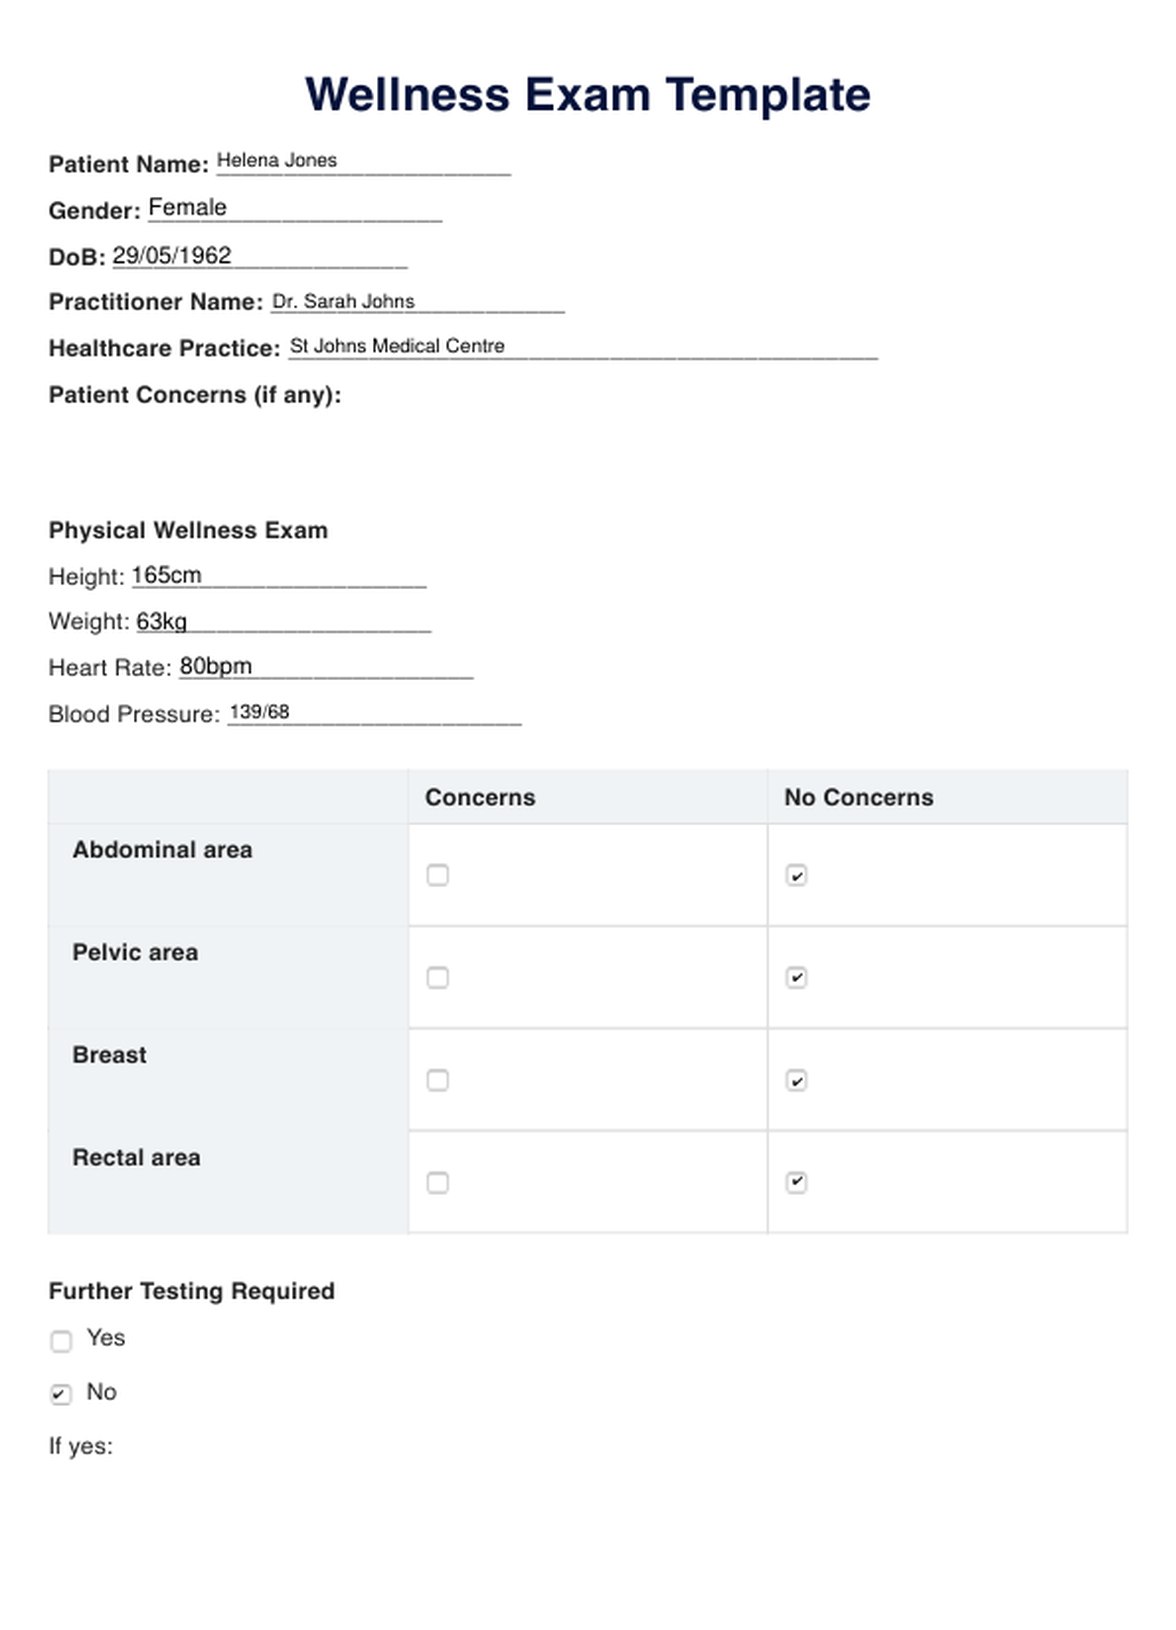
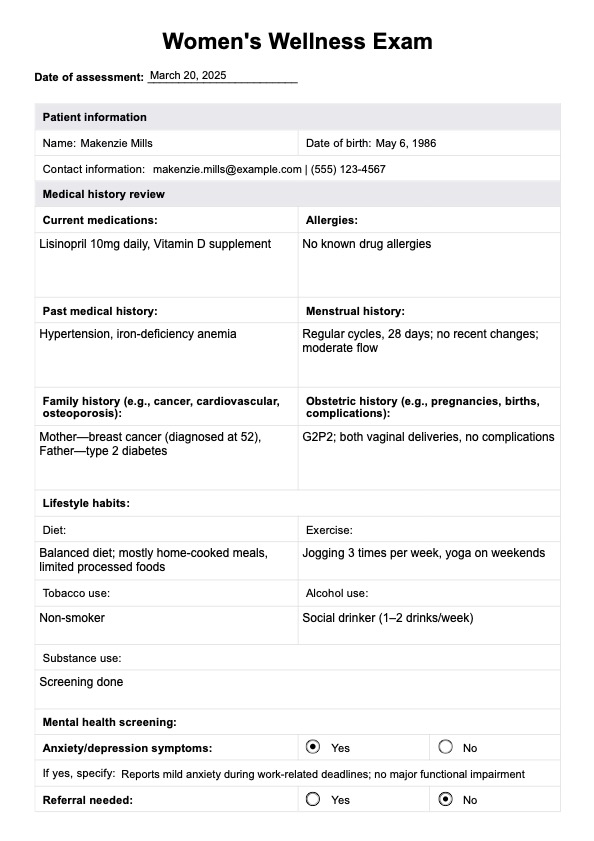
Here is a point that beginners consistently miss. The HPI for a wellness visit carries very little weight on its own. The real documentation anchor is the complete review of systems. You need to document at least a ten-system ROS for a comprehensive preventive exam, and most payers expect a head-to-toe ROS that is thorough enough to support medical necessity. A complete ROS in this context lists every system and notes either "negative" or "denies symptoms." For example: General: denies fever, chills, fatigue. HEENT: denies vision changes, hearing loss, sore throat. Cardiovascular: denies chest pain, palpitations, edema. Respiratory: denies cough, dyspnea, hemoptysis. Gastrointestinal: denies nausea, vomiting, diarrhea, constipation, abdominal pain. Genitourinary: denies dysuria, hematuria. Musculoskeletal: denies joint pain, swelling, stiffness. Neurological: denies headache, syncope, weakness, numbness. Psychiatric: denies anxiety, depression, mood changes. Endocrine: denies heat or cold intolerance, polyuria, polydipsia. Hematologic: denies bleeding or bruising. Allergic: denies known allergies. Lymphatic: denies lymph node swelling. Skin: denies rashes or lesions. Breast: for females, denies breast lumps or discharge. This list should be documented in full, even though every item is negative. Documenting a negative ROS is not a formality. A truncated ROS is the most common documentation deficiency I see in wellness visit audits. Reviewers check that you actually performed a systems review rather than simply writing "ROS negative" and moving on. Specificity matters more than brevity.
Common Pitfalls That Sink Claims
The first pitfall is leaving the HPI blank because there is nothing to write. This is a documentation error, not a clinical one. Every encounter requires a chief complaint and an HPI component. The chief complaint can be one sentence. The HPI can be three sentences stating asymptomatic status and relevant denials. But the fields cannot be empty. The second pitfall is conflating the HPI with the past medical history. Writing "Patient has hypertension and hyperlipidemia" in the HPI is incorrect. Those belong in the past medical history section. The HPI describes the present encounter. Chronic conditions that are stable and not the reason for today's visit do not go in the HPI. Mentioning them only if they are actively being managed during this encounter. The third pitfall is using a problem-focused HPI template and filling it with negations that don't match the encounter type. A reviewer who sees a detailed cardiac review of systems and a full neurologic assessment documented under a problem-oriented HPI for "routine physical" will question whether the visit was actually a diagnostic encounter billed as preventive. Keep the documentation scope aligned with the encounter type. A preventive visit HPI should be proportionate to a preventive visit.
A Practical Walkthrough
Here is the sequence I follow for a new patient wellness exam. First, I enter the chief complaint as "Routine annual preventive examination." Second, I write the HPI as a brief statement of asymptomatic presentation with relevant negative findings appropriate to the patient's age and sex. Third, I complete the full review of systems using a systematic template. Fourth, I document the physical exam findings, again following the preventive exam guideline structure for the patient's demographic. Fifth, I complete the assessment and plan, which includes risk factor assessment, counseling points, and any screening tests ordered. For an established patient aged 55 with a history of prediabetes, the HPI gains one additional element. The patient reports her fasting glucose has remained in the 100 to 115 range over the past year on continued lifestyle modification. She denies symptoms of hyperglycemia including polyuria, polydipsia, or blurred vision. This single sentence connects a chronic condition to the current encounter without converting the visit into a problem-focused exam. The rest of the documentation remains structured around the preventive framework. One edge case I encountered involved a patient who presented for a wellness exam but reported a new mild knee ache during check-in. The question was whether this converted the visit to a problem-oriented encounter. I documented the knee ache in the HPI as a minor new symptom, completed a problem-focused evaluation of the knee, and still billed the preventive exam separately with modifier 33 if applicable. The key was documenting both encounters distinctly so the billing reflected the actual work performed. If you skip the problem documentation, you risk under-coding. If you fold the problem into the preventive HPI without a separate evaluation, you risk upcoding.
What This Doesn't Solve
Writing a clean HPI for a wellness exam does not guarantee claim acceptance. Payer policies vary significantly. Some commercial plans require specific ROS depth. Medicare Advantage plans may have their own documentation requirements beyond standard Medicare guidelines. Some Medicaid programs require the HPI to be embedded in a specific note format. Your documentation strategy should account for the mix of payers you see, not just the EHR template defaults. The other limitation is time. A thorough wellness visit with complete HPI, full ROS, comprehensive physical exam, and counseling documentation typically requires twenty-five to thirty-five minutes of direct patient contact. If your scheduling model allocates fifteen minutes for a preventive exam, the documentation will suffer. No amount of template optimization fixes an inadequate time allocation. You either adjust the schedule or accept higher audit risk. If your organization struggles with wellness exam documentation quality, the most effective intervention is not another template change. It is targeted feedback to providers based on actual audit findings. I reviewed fifty wellness visit notes from our clinic after a single internal audit cycle. Forty-two of them had incomplete ROS documentation. Thirty-eight had HPI sections that were either blank or copy-pasted from a prior year's problematic note. After a single one-hour session where I walked through three documented examples and two rejected audit cases, the next cycle showed twenty-eight incomplete notes down to seven. The change came from seeing concrete examples of what went wrong, not from reading a policy document.
The core principle is straightforward. A wellness exam HPI exists to confirm that the patient presented for prevention, not for a new or worsening problem, and that the encounter was thoroughly evaluated despite the absence of active complaints. The documentation should be complete, accurate, and aligned with the preventive nature of the visit. Anything longer than that is noise.



