Understanding Nerve Pain: What Actually Happens
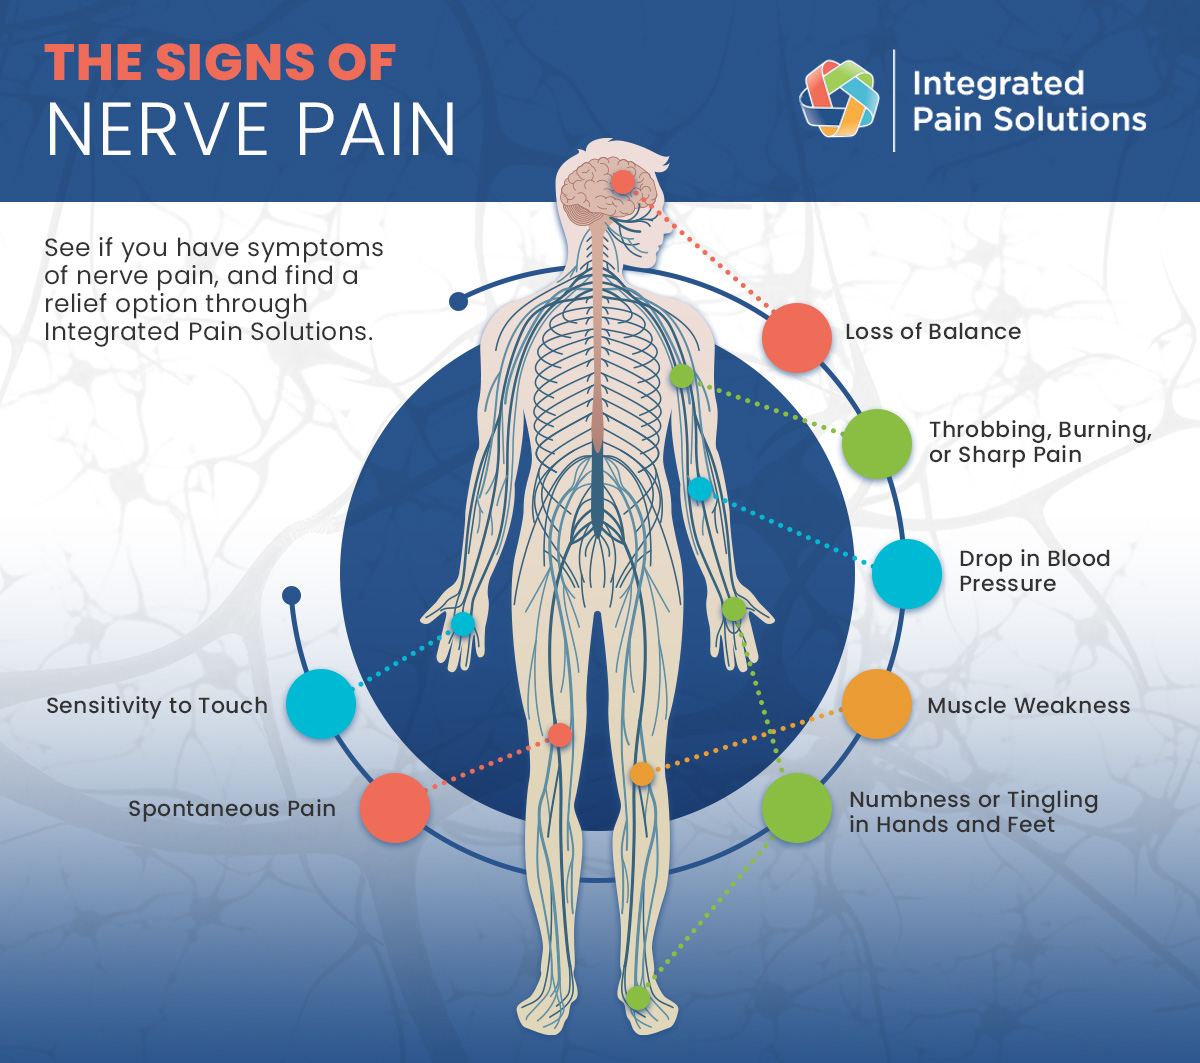
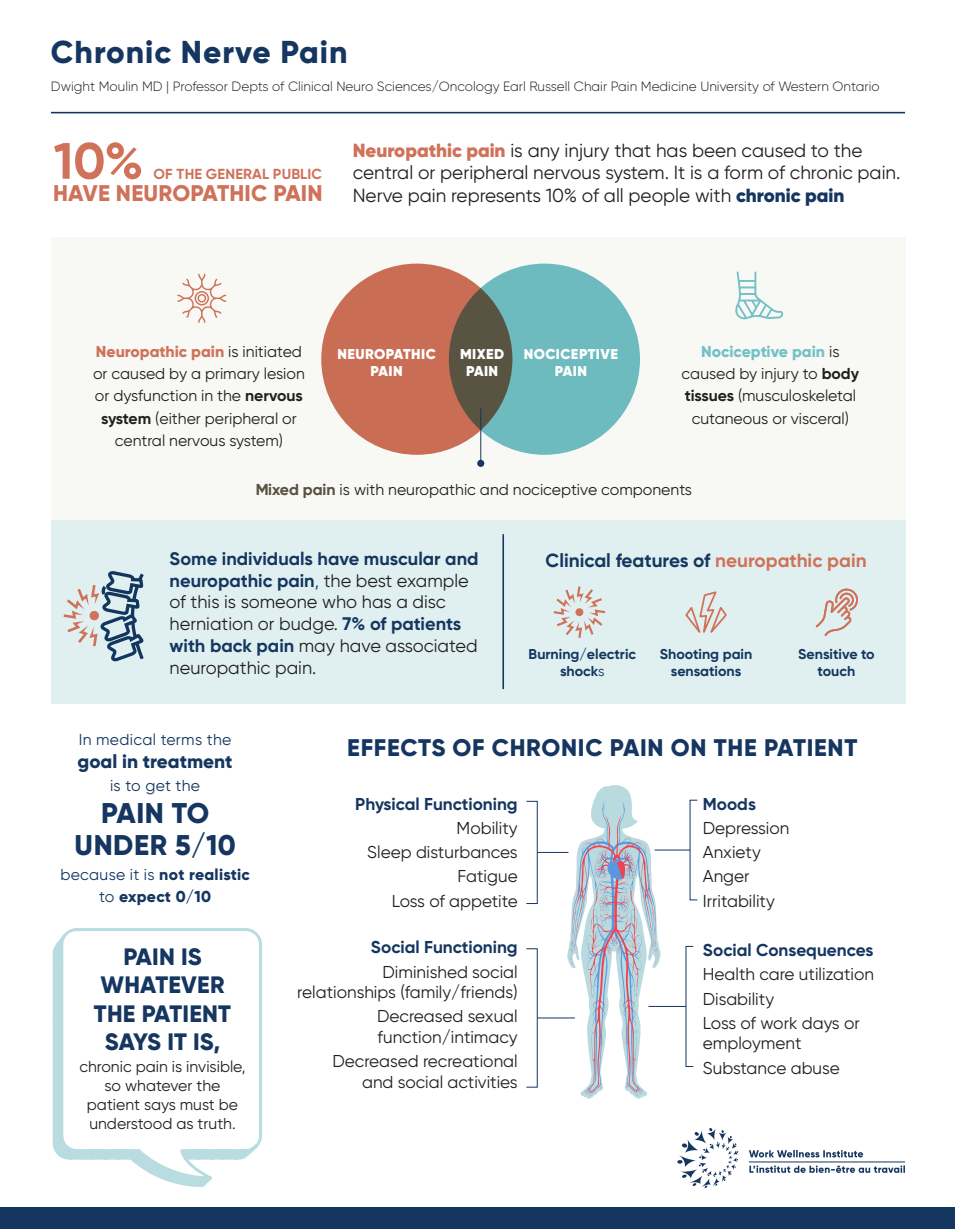
Nerve pain, clinically called neuropathic pain, doesn't behave like the ache you get from a bruised knee. The signals get tangled somewhere along the pathway between your nerves and your brain. It fires without a clear cause, or worse, fires at the wrong intensity. I spent three years managing my own radiculopathy before I figured out that the standard anti-inflammatories were doing basically nothing for the burning sensation radiating down my leg. The resource in question covers the basics most people encounter: distinguishing between types of nerve pain, identifying common triggers, and laying out a practical treatment sequence. It starts with the foundational stuff—what makes nerves misfire, why medications targeting inflammation often miss the mark for neuropathic cases, and which approaches have actual clinical backing versus just trending on social media. The guide emphasizes tracking patterns, because nerve pain variability can easily fool you into thinking something is getting worse when you are actually just hitting a normal fluctuation. One detail beginners consistently overlook involves the difference between positive and negative symptoms. Positive symptoms are the extra sensations: burning, tingling, electric shocks. Negative symptoms are what gets lost: numbness, weakness, reduced sensation. Mixing these up leads people to chase treatments for the wrong problem. If your main issue is numbness rather than pain, no amount of addressing the burning will restore feeling.
What Works and What Does Not
I tried the usual first-line approaches before finding anything sustainable. Gabapentinoids like gabapentin and pregabalin are the standard prescription moves. They help some people, cause cognitive fog in others, and do absolutely nothing for a significant subset. I watched a colleague taper off pregabalin after three months because the dizziness made his work impossible. The medication was barely touching the pain anyway. Topical treatments using lidocaine or capsaicin show real utility for localized nerve pain. The evidence is stronger here than for many oral options. A 5 percent lidocaine patch applied directly to the affected area can take the edge off without systemic side effects. It does not help if the pain originates deeper than where the patch can reach. I learned that the hard way with deep radicular pain where the nerve root irritation sits too far from the skin surface. Magnesium supplementation comes up frequently in wellness discussions around nerve pain. The scientific support exists but is thin. Some studies show modest benefit for certain types of neuropathy, while others find no difference. The safe upper limit for supplemental magnesium runs roughly 350 mg per day for most adults. Going above that tends toward gastrointestinal discomfort rather than improved nerve function. The guide covers this nuance better than most sources I have seen.
Edge Cases and Workarounds
Here is a specific problem I ran into that the standard literature does not address well. Some people develop allodynia alongside their nerve pain. Allodynia means normally harmless stimuli become painful. Clothing brushing against affected skin can feel like sandpaper. I had a patient who could not tolerate wearing socks because the seam caused shooting pain. Standard nerve pain protocols did not address this at all. The workaround involved a combination approach. We switched from topical to oral treatment briefly to reduce overall nerve excitability, then gradually reintroduced protective padding to the skin. The key was timing. Adding the padding too early made the allodynia worse. Waiting too long meant the patient suffered unnecessarily. We found a window somewhere in the middle that worked for her specific case. Another tricky situation involves diabetic peripheral neuropathy coexisting with other conditions. Sometimes the nerve pain comes from diabetes, sometimes from another source like spinal stenosis, and sometimes from both. Treating just the most obvious cause leaves the remaining pain unaddressed. The Wellness Guide 101 Nerve Pain resource mentions this overlap but does not go deep enough into diagnostic differentiation. I wish authors would spend more time on how to figure out which mechanism dominates in a given patient.
Get the Full Details

Limitations and When to Move On
No single approach works for everyone, and nerve pain treatments carry real trade-offs. Medications like amitriptyline help some people with neuropathic pain but cause significant sedation and dry mouth. The benefit-to-burden ratio depends entirely on individual tolerance and lifestyle. If you work a shift job or need alertness for safety-critical tasks, the sedation might be disabling regardless of pain relief. Interventional procedures like nerve blocks provide temporary relief at best. They can help diagnose which nerve is involved, which guides long-term treatment planning. The pain relief typically lasts weeks to a few months, not years. Some people need repeated procedures, which introduces cumulative risks. The guide notes this honestly, which I appreciate more than I see in most wellness resources. Physical therapy and graded exposure help maintain function while the nervous system recalibrates. Movement prevents deconditioning that makes pain perception worse over time. The counter-intuitive part is that rest often increases sensitivity rather than reducing it. I know people who stopped moving entirely during a flare and ended up worse afterward because their baseline conditioning dropped. The nervous system interprets reduced input as a signal to become more sensitive, not less.
Practical Tracking Approach
Simple tracking makes a real difference in treatment decisions. I recommend logging pain intensity, location, quality, timing, and what was happening before the pain changed. Note medications taken, sleep quality, stress levels, and physical activity. This pattern recognition helps distinguish nerve pain from musculoskeletal sources, which sometimes overlap in ways that confuse both patients and clinicians. The most useful metric is function, not pain score. A person reporting eight out of ten pain who can still walk, sleep, and work is in a different position than someone at four out of ten who cannot do any of those things. Treatment goals should focus on restoring function while reducing symptom burden. The Wellness Guide 101 Nerve Pain mentions this principle, though I think more resources should lead with it rather than burying it near the end.