ADLs Are The Backbone Of Every Nursing Assessment You'll Ever Do
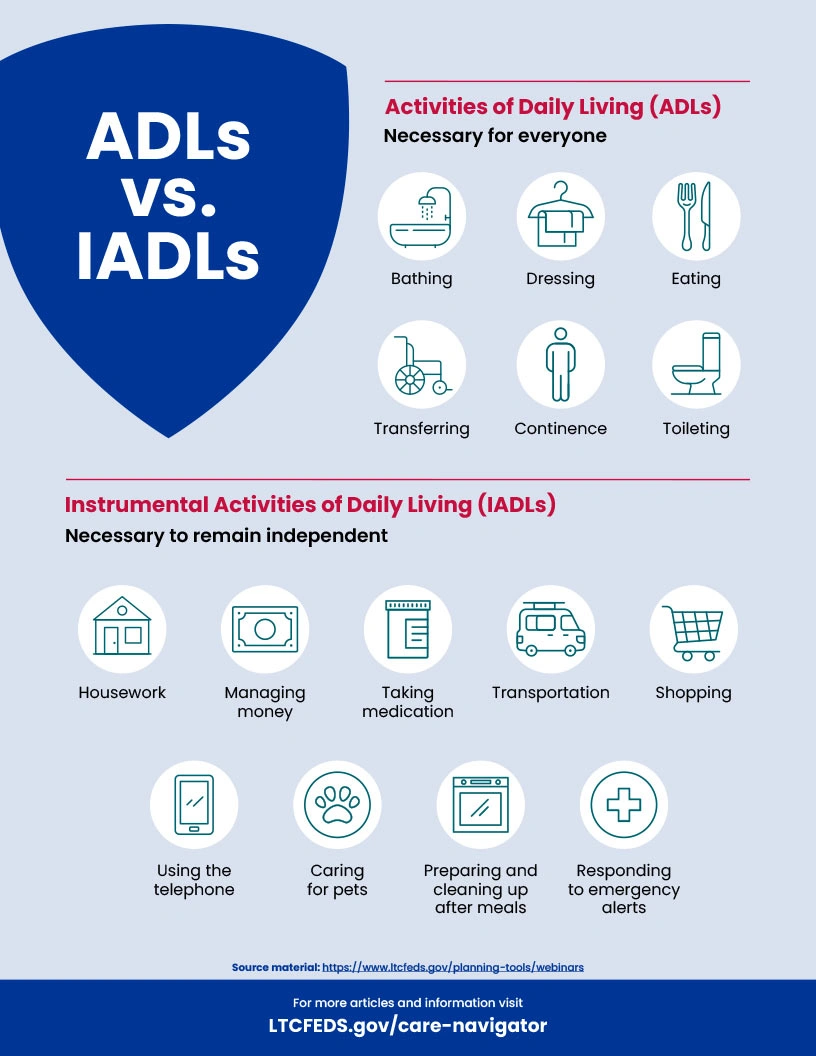
If you've ever sat down to write a discharge plan or fill out an admission assessment, you've dealt with ADLs whether you knew the term or not. Activities of Daily Living refers to the basic set of tasks people perform every day to take care of themselves. In nursing, we break them into two categories: basic ADLs and instrumental ADLs. The distinction matters more than most new nurses realize, and getting it wrong early on will cause problems down the line. Basic ADLs cover the fundamentals: eating, bathing, dressing, toileting, transferring (moving from bed to chair and back), and maintaining continence. These are the things you cannot function without. Instrumental ADLs are more complex—they include managing medications, handling finances, doing housekeeping, preparing meals, using the telephone, and shopping. IADLs tell you whether someone can live independently. Basic ADLs tell you how much hands-on care they need. The standard tool you'll see everywhere is the Katz Index of Independence in ADLs. It scores six basic ADLs as independent or dependent. A completely independent patient gets a 6. A patient who needs help with all six gets a 0. Barthel Index is another common one, and it's a bit more granular. You'll also run into the FIM—Functional Independence Measure—which was originally designed for rehabilitation settings and carries a 18 to 126 scoring range. Each tool has its own grading system, and your facility will usually standardize on one. Know which one before you start charting.
Here's something most textbooks gloss over: ADL assessments are notoriously unreliable if done as a checklist from memory. I spent weeks trying to complete accurate assessments after shift transitions, and the numbers never matched what I saw on the floor. Patients would tell you they were "fine" when they clearly needed two-person assist for ambulation. The workaround I ended up using was straightforward—I'd observe the patient perform at least one ADL per shift rather than relying on their self-report or the last nurse's notes. It takes roughly ten minutes per patient per shift, but it cut my inaccurate documentation down to almost nothing. You can't assess dignity and safety from a checkbox. The deeper issue people miss is that ADL decline doesn't always show up where you expect it. I once had a patient whose Barthel score looked stable for three weeks, then one morning she couldn't button her shirt. Fine motor dexterity dropped before gross motor skills did. That was the first sign of an impending neurological issue we hadn't caught yet. ADLs aren't just about mobility and basic self-care. They reveal subtle declines in coordination, cognition, and strength that vital signs alone won't flag. Dressing, especially, is a surprisingly sensitive indicator because it requires sequencing, fine motor control, and balance all at once. Another counter-intuitive point: high ADL scores don't necessarily mean a patient is safe for discharge. I worked a case where a patient scored 5 out of 6 on Katz—independent in everything except bathing. The discharge planner moved to release because the score was "good enough." That patient fell in the bathroom two days later because nobody asked about the shower chair he didn't have at home. An ADL score is a snapshot, not a safety guarantee. Context always matters more than the number.
There are real limitations to relying on ADL assessments alone. They're subjective by nature. Two nurses can observe the same patient and assign different functional levels depending on their experience and expectations. They also tend to underrepresent cognitive impairment—if someone can physically feed themselves but forgets to eat for two days, the ADL score won't catch that. For that reason, ADL assessments should always be paired with a cognitive screening tool like the MMSE or MoCA. Relying on ADLs without cognitive assessment is a well-documented gap in care planning. If you want something more robust, the Minimum Data Set (MDS) used in skilled nursing facilities covers ADLs across multiple domains and feeds into CMS reimbursement. It's far more comprehensive but also far more time-consuming. In acute care settings, you'll typically use a shortened version during admission and reassess at defined intervals—usually every 30 days or at disposition. Documentation standards vary by region and facility type, so check your local policy rather than assuming a universal requirement. The practical takeaway is simple and not particularly exciting. Learn your facility's standard ADL tool cold. Observe before you document. Track trends over time rather than fixating on a single score. And remember that ADLs are clinical data, not paperwork. The numbers on that sheet drive care plans, staffing ratios, equipment orders, and discharge decisions. Treat them with the same seriousness you'd treat a lab result.
Get the Full Details