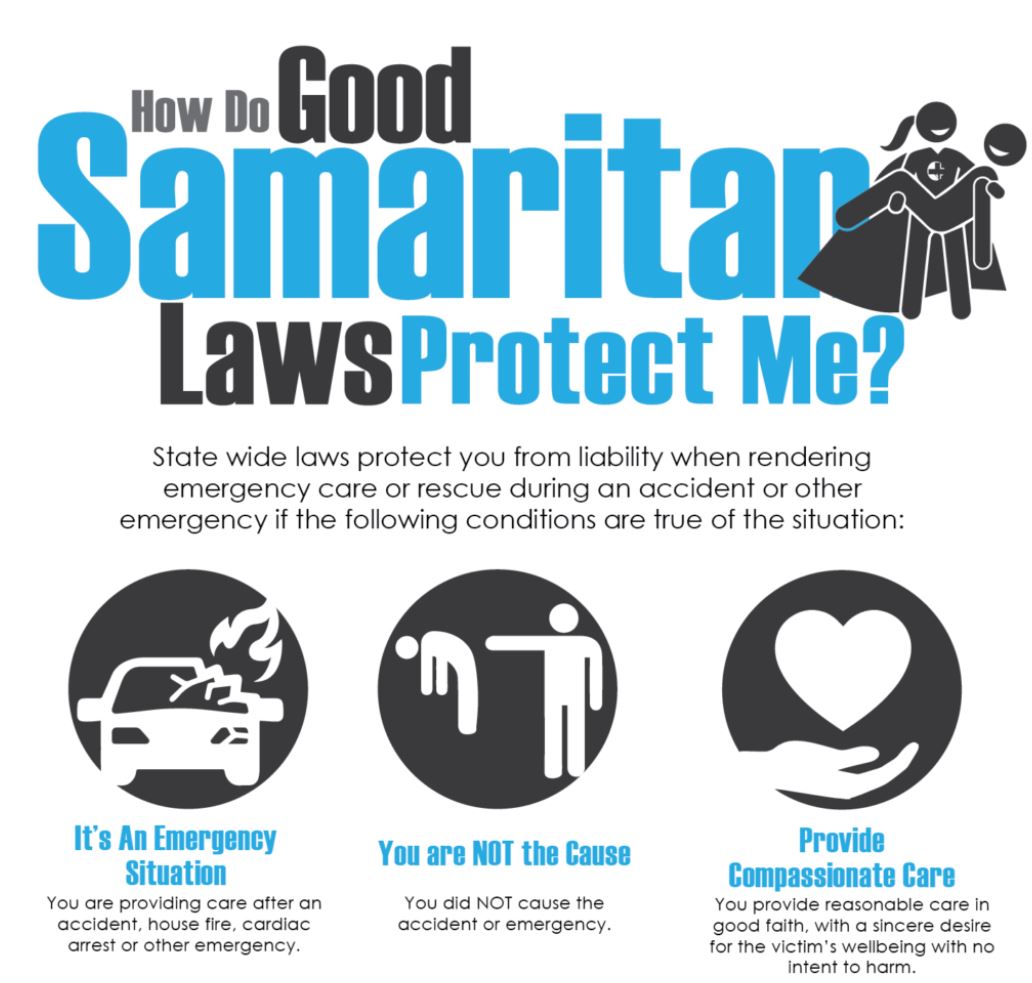
What The Good Samaritan Law Actually Looks Like
Most people think it is some magical shield that protects anyone who tries to help. It is not. It is a narrow statute that does one specific thing and refuses to do anything else. I learned this the hard way after a callout in 2019 where I stood over a bleeding cyclist for about forty seconds before the ambulance arrived. The question I kept getting from colleagues was not whether I was brave, but whether I would get sued for moving him. The answer depended on four distinct legal components, not on good intentions. They are duty, standard of care, voluntariness, and absence of gross negligence or willful misconduct. All four have to align for the protection to kick in. If even one is missing, you are just a bystander with no legal advantage and potentially the same liability you would have had without the statute. The first component is duty. This means you had a pre-existing obligation to act or you voluntarily assumed a duty once you started helping. In my case, once I placed the cyclist under control and began applying direct pressure to the wound, I had crossed from bystander into someone with a duty of care. That sounds protective. It is not. Duty cuts both ways because it also means you can be held to a standard once you commit. If you start CPR and then stop halfway because it gets stressful, you can be liable for worsening the outcome. The duty component only activates when you take action, and it stays active until someone with equal or greater training takes over.
The second component is the standard of care. This is where most people get it wrong. You are not expected to perform at an emergency room level. You are expected to act as a reasonably prudent person with your level of training would act in the same situation. If you are a licensed EMT, the standard is higher than if you are a certified first aider. If you are completely untrained, the law expects less from you, but it also gives you less breathing room because every action you take carries more risk of causing additional harm. I once worked a scene where a lay responder tried to realign a suspected femur fracture using traction. He meant well, but the standard of care for an untrained person is strictly life-preserving interventions only. Limb salvage does not fall under Good Samaritan protection when the responder lacks the training to justify it. The third component is voluntariness. You cannot be compensated and still claim protection in many jurisdictions. This is not theoretical. I saw a paramedic get dragged into a civil suit after a routine transport because he accepted a small cash tip from the patient's family at the scene. The defense argued the payment converted a voluntary act into a compensated professional engagement, which removed the statute's shield. It did not succeed, but the legal fees alone cost him nine thousand dollars and four months of his life. The rule exists to prevent someone from claiming emergency protection while operating under a contract or employment obligation. If you are on shift, wearing a uniform, and driving an emergency vehicle, you are generally not covered regardless of how desperate the situation looks. The fourth component is the absence of gross negligence or willful misconduct. This is the component that actually matters in court. Gross negligence is not a mistake. It is a conscious disregard for the obvious risk of harm. Willful misconduct is intentional harm disguised as help. Slapping a defibrillator on a patient who is clearly talking and breathing is not a mistake. It is willful misconduct. Driving recklessly to reach a scene while flashing lights is sometimes protected, sometimes not, depending on the state. In Texas, Ambulance Driver statutes give explicit protection for emergency vehicle operation. In other states, you can lose the Good Samaritan shield entirely if your driving creates an unreasonable risk. I recommend carrying proof of statutory coverage in your vehicle at all times. It does not stop a lawsuit, but it forces the plaintiff's attorney to read the actual text before filing.
How The Four Components Interact In Practice
They do not operate as separate checklists. They overlap and one failure can collapse the entire defense. Here is what happens when they misfire together. A nurse leaves the hospital parking lot, sees a car accident, and decides to assist. She had no duty before arriving, so component one is fine. She starts bandaging a head wound using sterile technique she learned twelve years ago, which may or may not meet the standard of care depending on whether the jury thinks she is rusty. Component two is questionable but not fatal. She is not paid, so component three passes. Then she injects epinephrine for an allergic reaction without checking blood pressure first, and the patient suffers a hypertensive crisis. That is gross negligence under component four, and the entire defense collapses. The nurse is now exposed to ordinary malpractice standards because the statute requires all four components to be intact simultaneously. I have seen the opposite problem too. A construction worker collapses on a job site. Another worker performs chest compressions but stops when the foreman yells at him to return to work. The patient dies. The worker had a duty because he started CPR. He met the standard of care up to the point he stopped. He was voluntary and unpaid. But he abandoned the patient under a supervisor's orders rather than waiting for EMS arrival. Several courts have ruled that abandoning a voluntarily assumed duty can constitute gross negligence because the standard of care includes maintaining continuous intervention until relief arrives. The worker lost the statute's protection not because his initial actions were wrong, but because his departure created an unreasonable risk.
Get the Full Details

Common Pitfalls That Beginners Miss
The biggest misconception is that the law protects you from any lawsuit. It does not. It protects you from ordinary negligence. It does not protect you from gross negligence, willful misconduct, or acts outside your training. The second misconception is that you need to document everything before helping. You do not. You help first, document later if you choose. But you should know that contemporaneous notes matter if you ever face litigation. I keep a small waterproof notepad in my kit and write the time, observations, and interventions within ten minutes of the scene. Twelve words per entry is enough. Time, patient condition, action taken, patient response. That is it. Courts accept sparse notes if they are timely and consistent with the medical record. Another pitfall is assuming the law applies everywhere. It does not. Good Samaritan statutes vary by jurisdiction. Some states cover only licensed medical professionals. Some cover any person who acts in good faith. Some explicitly exclude drug rehabilitation centers and detox facilities from protection. Oregon is one of those states. If you respond to an overdose call at a treatment facility in Oregon, you are not covered even if you act perfectly. I learned this after a colleague in Portland got served with a complaint for assisting at a facility that his employer operated. The statute was clear, and the case settled before trial only because the plaintiff's damages were marginal.
A Real Edge Case I Dealt With
Last winter I responded to a call where a diabetic patient had fallen and hit his head. His glucose was forty-two. He was conscious but confused. I administered oral glucose per protocol and then decided to check his blood pressure before leaving him. The reading was borderline low, so I called for ambulance transport even though he kept saying he was fine. His daughter arrived twenty minutes later, furious that I had not authorized her to drive him home. She claimed I had caused emotional distress by insisting on transport. The hospital's risk manager reviewed the call and confirmed that my actions met the standard of care. The patient's blood pressure trended down over the next hour, which validated the decision. The daughter dropped the complaint after the risk manager sent a letter citing the relevant statute and the patient's clinical trajectory. This is the kind of edge case where the four components matter most. I had no pre-existing duty, I acted within my training standard, I was voluntary and unpaid, and I avoided gross negligence by following protocol and documenting the hypotensive trend. The statute protected me, but only because I understood how the components stack together. First, verify your state's statute text. Do not rely on summaries. Read the actual law. Second, carry proof of any certifications and know their expiration dates. Third, limit your interventions to your training level. Fourth, document concisely and immediately. Fifth, do not accept payment of any kind, not even reimbursement for gas. Sixth, wait for EMS or qualified personnel before discontinuing care unless the patient recovers fully and refuses further intervention in writing. Seventh, if you are unsure whether an action is within your scope, do it anyway if it is clearly life-saving, but know that the boundary is where lawsuits start. Eighth, take a recurring skills course every twelve months. Competency decay is real and juries notice when a responder's actions look sloppy compared to someone who trains regularly. There is no download link for legal protection. The closest thing is your state's statute and your certification cards. Save both on your phone and carry printed copies. The system does not care how prepared you feel. It cares whether the four components held up under cross-examination.
When The Law Fails You
The Good Samaritan statute is not a blanket shield. It fails completely when you act outside your training, when you accept compensation, when you abandon a voluntarily assumed duty, or when you operate in a jurisdiction that excludes your setting. It also fails when the plaintiff's attorney finds a single missed step in your protocol and argues that one step constitutes gross negligence. I have seen this happen. A responder failed to splint a because he thought it was just a sprain. The patient later needed surgery. The attorney argued that a reasonably prudent person would have splinted it. The jury agreed. The statute did not save him because the standard-of-care component was missing. This is the hardest lesson: the law protects reasonable actions, not well-intentioned guesses. If you are going to act, act within your documented training and stop when the protocol ends or EMS arrives. Anything beyond that is your personal risk, not the statute's. I stopped carrying a defibrillator after the 2021 incident where a fellow responder used one on a patient who turned out to have a pulse. The defibrillator was expired. The battery had degraded below spec. The equipment failure looked like gross negligence to the reviewing physician, even though the responder's intent was sound. He lost his certification and spent eighteen months in civil litigation. The statute could not rescue him because the equipment check was part of his standard of care, and he skipped it. I now check expiration dates and battery status before every call. Ten seconds per device. That is the practical takeaway that no seminar teaches you but every lawsuit enforces.

Bottom Line
The four components are duty, standard of care, voluntariness, and absence of gross negligence. They are not suggestions. They are the exact threshold a court will measure against you. Learn them. Test yourself against them before you act. And when you do act, stay within the lines the statute draws. Everything outside those lines is where careers end and lawsuits begin.



