Breaking Down The Breathing Assessment Pals Tool
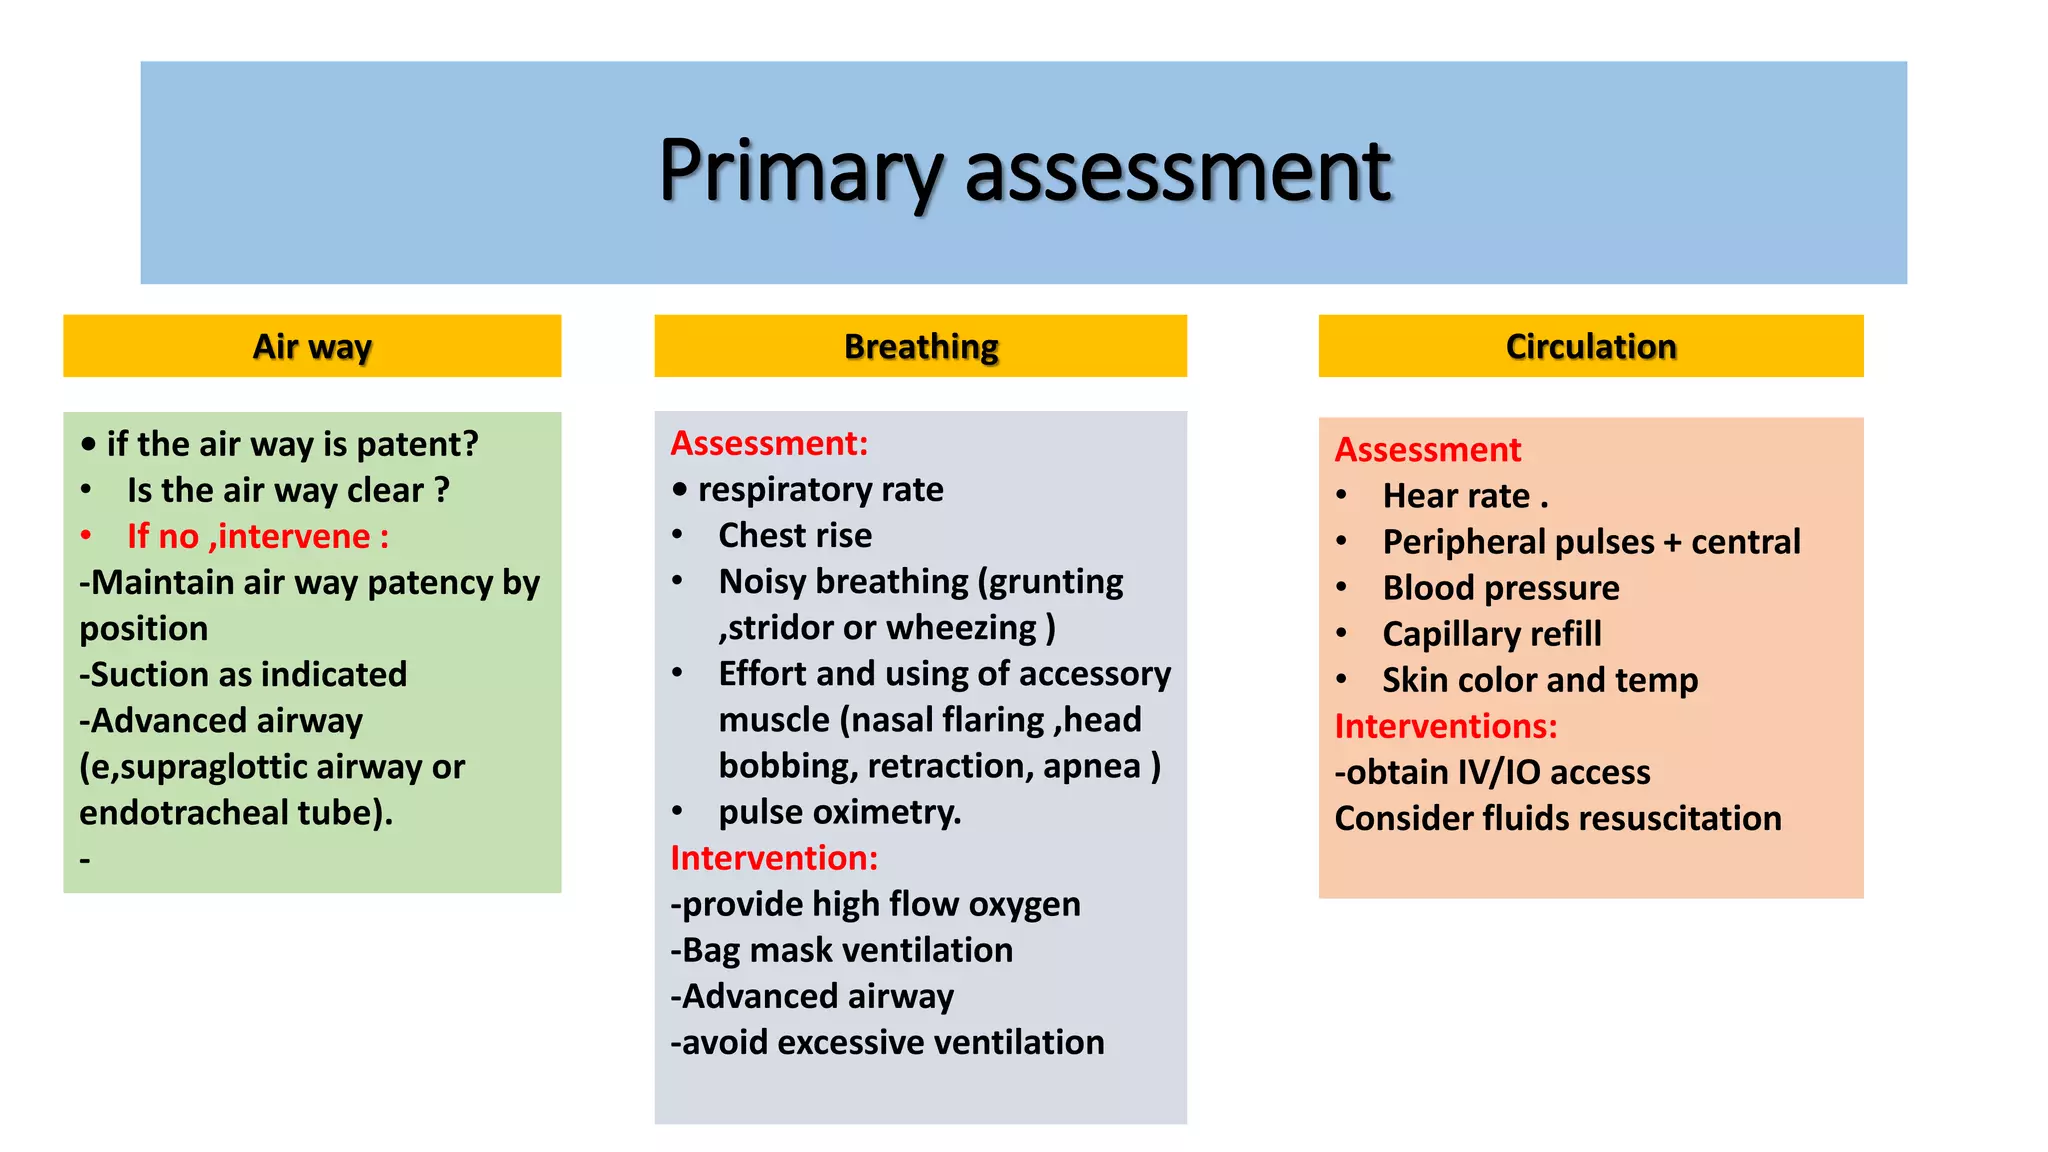
The Breathing Assessment Pals are basically a set of structured cards and scenario guides designed to walk clinicians through a systematic respiratory assessment. They're commonly used in nursing schools, EMT programs, and hospital orientation modules. The whole point is to make sure you don't skip steps when evaluating someone's breathing, which sounds obvious until you've been on a busy shift and realize you've been rushing through lung sounds without checking accessory muscle use. I remember working with a newer nurse who was convinced she had a handle on respiratory assessments after reading a textbook chapter. Then she got paired with a real patient who had early COPD exacerbation signs, and she missed the subtle increased respiratory rate and the use of pursed-lip breathing entirely. She was so focused on lung auscultation that she didn't look at the patient first. The Assessment Pals framework addresses exactly this kind of tunnel vision by forcing you through a sequence: inspection, palpation, percussion, then auscultation, each with specific checkpoints built into the cards.
What Are The Components Of The Breathing Assessment Pals
The main components break down into several areas that the tool covers systematically. First there is the observation checklist, which includes respiratory rate, rhythm, depth, and pattern recognition. Things like thoracic expansion symmetry, use of accessory muscles, nasal flaring, and skin color changes all get their own dedicated section. Second is the auscultation mapping guide, which shows exactly where to place the stethoscope for each lobe and what normal versus abnormal sounds should be categorized under. The third component is the patient history integration section, reminding you to correlate findings with the patient's baseline, recent illnesses, smoking history, and current medications. The fourth is a red flag scoring system that highlights which findings require immediate escalation rather than routine follow-up. One thing most people don't realize about using these cards effectively is that the format matters more than memorizing every item on the list. I learned this the hard way during a pediatric rotation where I had a child with a mild respiratory infection. I went through every component mechanically, but the kid was breathing at forty-two per minute and I hadn't even noted the grunting. The Pals card for pediatric patients has a separate sidebar specifically for age-appropriate respiratory rates, and I had used the adult version instead. My workaround was simple: I started carrying both pediatric and adult versions in my pocket and always checked the age bracket before pulling a card. The auscultation mapping piece deserves a bit more attention because it is where most assessments go sideways. The standard approach teaches twelve lung sound points, but in practice many clinicians concentrate only on the anterior lobes and skip the posterior segments entirely. I once had a patient whose crackles were exclusively in the right lower lobe posteriorly, and because I hadn't fully rotated them, I reported clear lungs on the initial assessment. The breathing assessment component that catches the most misses is this posterior mapping reminder, which the Pals tool makes explicit rather than leaving it to individual habit.
How To Actually Use These In Practice
The tool works best when you treat it as a reference rather than a script. Pull the relevant card before you start your assessment, review the components once so they are on your mind, then put the card away and do the assessment naturally. If you hold the card the entire time you are listening to someone's lungs, it makes the patient uncomfortable and slows you down unnecessarily. I usually keep one card at my station and only pull a fresh one when I am doing a new patient intake or a particularly complex respiratory case. The red flag scoring section is where the tool earns its keep, honestly. It ranks findings from routine observation to immediate intervention, and having that visual hierarchy prevents the common mistake of underreacting to borderline symptoms. A respiratory rate of twenty-two in an elderly post-surgical patient is not a nothing finding, and the scoring system flags that correctly. But here is the limitation: the tool assumes a certain level of foundational knowledge. If you cannot distinguish between coarse and fine crackles or you do not know what tracheal breath sounds indicate, no amount of checklist following will save you from misclassifying a finding. The Assessment Pals are a structure, not a substitute for clinical competence. Another practical issue I encountered involves the paper versus digital versions. The physical cards tend to get damaged quickly in a clinical environment, and several colleagues have reported laminated copies becoming slippery and hard to read under fluorescent lights. The digital app version exists but requires an internet connection on most hospital networks, which is often unreliable on the floors. My recommendation is to print the core assessment pages on cardstock and laminate them yourself if you need something durable, or just use the digital version on a personal device with screenshots saved offline.
Get the Full Details

The history integration piece is also somewhat underdeveloped in my experience. The cards mention pulling patient history, but they do not provide a structured way to incorporate that information into your final assessment readout. I created my own shorthand notation system alongside the Pals cards that records both the objective findings and the relevant history in a single glance, which has made my documentation significantly faster during charting. The tool itself does not address this workflow gap, which is worth knowing if you plan to use it extensively in a busy clinical setting. Overall, the Breathing Assessment Pals give you a reliable framework that most beginners and intermediate clinicians will find useful, particularly for reducing the kind of oversight that comes from rushing through assessments. They are not a complete replacement for building your own clinical intuition, and they have limitations around durability and integration with real-world workflow. But for the price and effort involved, they fill a genuine gap in respiratory assessment training that many programs otherwise leave to individual discretion.